
How to Actually Fill Out Medicare Cost Report Worksheets Without Losing Your Mind
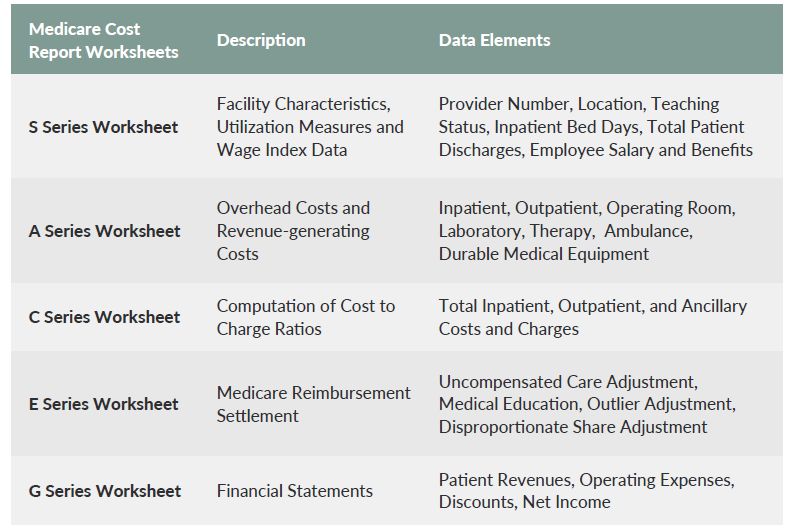
The Medicare cost report is a spreadsheet-driven filing system that hospitals and other healthcare providers use to reconcile their actual costs against Medicare reimbursement rates. The worksheets are the individual forms CMS requires you to complete — Worksheet S-3, Form CMS-2552-10, the whole routine. Most people who tell you it is complicated are either exaggerating or have never done it straight through on a clean year. I worked in hospital revenue cycle long enough to know that the actual mechanics of Medicare Cost Report Worksheets are tedious but predictable once you stop treating them like a novel exam and start treating them like a reconciliation problem. They are a reconciliation problem. You take your general ledger, you pull allocation percentages from your chart of accounts, and you plug numbers into forms that have been around since the early nineties. The worksheets have not changed fundamentally in two decades. The pain points are always the same.
What Medicare Cost Report Worksheets Actually Are
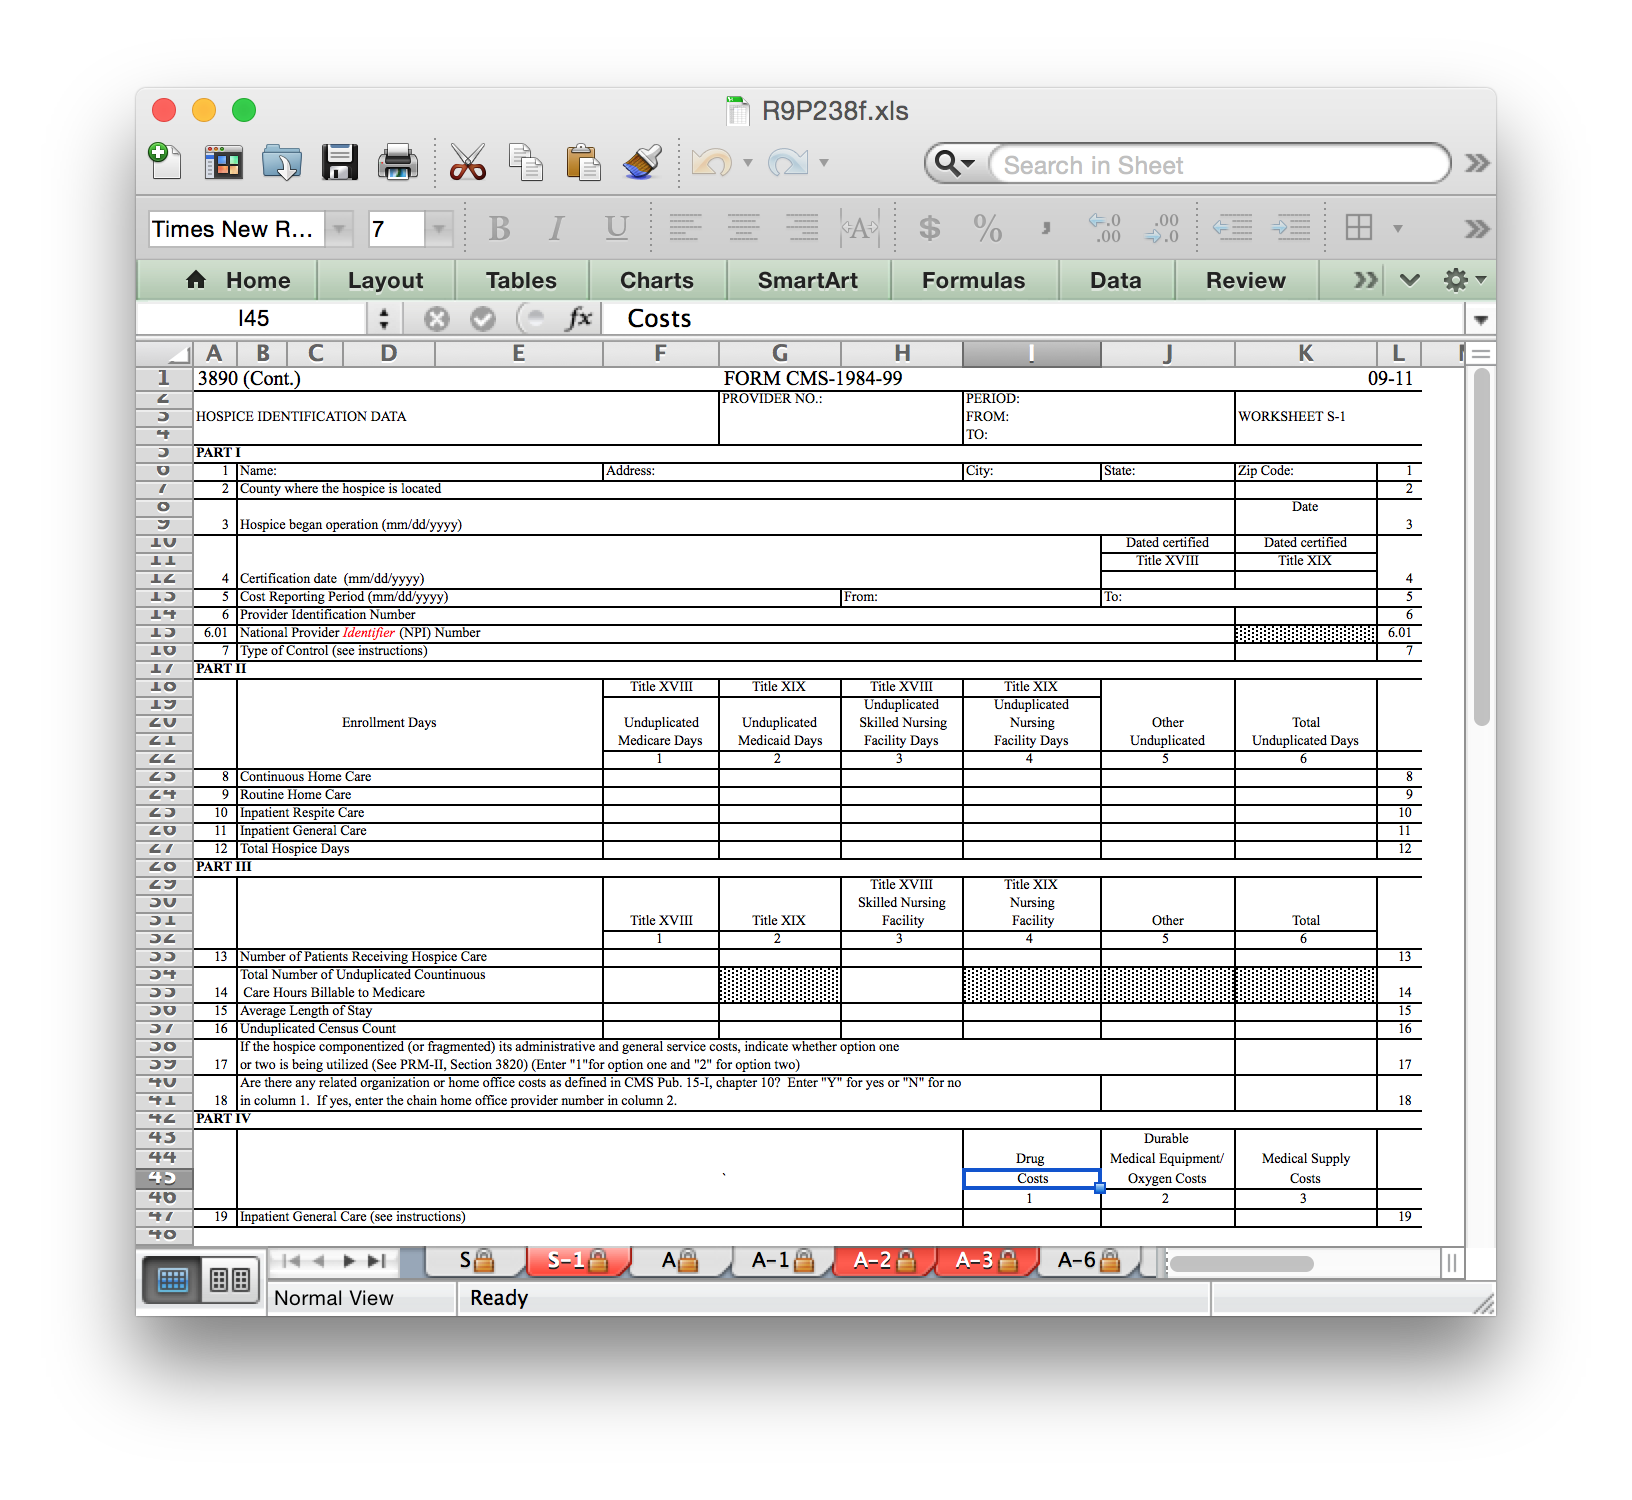
They are the supporting schedules you attach to the Form CMS-2552-10 cost report that your fiscal intermediary or MAC reviews during the audit process. Each worksheet serves a specific function. Worksheet S-3 breaks down non-payroll and payroll cost allocations. Worksheet R-1 is the remittance work sheet for interim payments. Worksheet S-4 handles the Medicare share of indirect costs. Worksheet U-1 covers capital related depreciable assets. There are a lot of them and they cross-reference each other constantly, which means if one cell is off everything downstream gets quietly wrong. The worksheets are publicly available from the CMS website. You download the PDF templates, open them in your accounting or cost reporting software, and fill them in according to the instructions on each form. Some providers use dedicated cost reporting platforms like Medaffiliated CostReports or Accruent that auto-populate fields. Others still do it manually in Excel with spreadsheets that were built in 2014 and nobody remembers how they work. Both approaches are valid. Neither is easy.
The Practical Process
Start with your fiscal year close. Make sure your general ledger is finalized and your trial balance is locked. Do not begin filling out Medicare Cost Report Worksheets until your financial statements are essentially final. I have seen providers send in draft numbers, get audited, then have to redo half the worksheets because an adjusting entry from three months prior shifted the direct patient service percentage. That does not feel like a big deal until the auditor emails you asking why yourWorksheet S-3 percentages changed retroactively. Step one is gathering source data. You need your general ledger by functional cost center, your employee count by department, your square footage schedule, your payroll registers broken down by direct and indirect categories, and any capital asset depreciation schedules. Most errors originate from using wrong allocation bases. The worksheet tells you which basis to use. Stick to it. If the instructions say to allocate based on direct patient service revenue, do not substitute salary percentages just because those numbers are easier to pull. Step two is running your cost center allocations. This is where Worksheet S-3 lives. You map every expense account to a cost center, then apply the appropriate allocation base. Payroll costs go through the payroll worksheet. Non-payroll goes through the non-payroll section. The two streams merge into total costs by department, then get split between Medicare, Medicaid, commercial, and self-pay using your patient service revenue percentages. Get those percentages right or the entire worksheet becomes noise.
Get the Full Details
Step three is calculating the Medicare share. This uses Worksheet R-1 and Worksheet S-4 together. You determine the contract numerator, which is your Medicare allowable cost, then divide it by your total revenue. The resulting percentage is applied across your cost categories to arrive at the Medicare cost share. This number feeds directly into the settlement calculation. A rounding error of two basis points here can mean tens of thousands of dollars depending on your volume. Step four is capital. Worksheet U-1 requires you to list every depreciable capital asset, assign it a category, and apply the MACRS recovery period. CMS has a specific table for this and if you misclassify an asset as depreciable when it is actually excluded, or vice versa, the auditor will catch it. I once spent three weeks correcting a capital worksheet where a vendor had capitalized a $40,000 piece of equipment that should have been expensed under the de minimis safe harbor. The fix was straightforward once I found the error but tracking down which of the forty-seven lines was wrong took far too long.
A Problem I Ran Into and How I Fixed It
During a recent audit on a community hospital cost report, the Medicare fiscal intermediary flagged that our Worksheet S-3 payroll allocations did not match our W-2 totals by nearly $180,000. The discrepancy was not obvious because it was distributed across roughly thirty departments. I traced it back to a single chart of accounts mapping error. Someone had assigned a portion of the employee benefits expense to a cost center labeled Other Operating Expenses instead of the Payroll Benefits pool. The worksheet accepted it silently because the category looked plausible. The workaround was to run a cross-reference query between the GL detail and the cost report data set, filtering for any benefit expense mapped outside the designated benefit cost centers. That isolated the variance in about twenty minutes. We remapped the entries, reran the allocation routines, and resubmitted. The lesson was not that the system was broken. It was that I had stopped questioning why the totals matched too closely in early drafts and only caught it when the auditor asked for the W-2 tie-out.
Things Beginners Miss on Medicare Cost Report Worksheets
One thing most people overlook is the timing of adjustments. If you receive a post-year-end refund or a write-off, it may need to be reflected on the cost report even though it happened after your reporting period closed. CMS expects you to include these if they relate to the cost report year. A late-year bad debt write-off of $200,000 should not sit in a different period and quietly distort your net patient revenue figure. Pull the adjustment and note it clearly on the appropriate worksheet. Another counter-intuitive point is that higher allocation bases do not always produce worse outcomes. Some facilities inflate their Medicare cost share by over-allocating indirect costs toward Medicare relative to other payers. Auditors see this pattern regularly and flag it immediately. The correct approach is to follow the allocation methodology the worksheet prescribes without trying to game the distribution. It usually does not help you and it almost always draws scrutiny. There is also a nuance with self-insured periods. If your organization was self-insured for part of the year and switched to a commercial plan mid-year, the cost report requires you to separate those periods and calculate Medicare costs independently for each. Mixing them inflates or deflates the Medicare share depending on how the costs differ between the two periods. The worksheet has a section for this but most people skip it because they assume the period split is negligible. In a twelve-month report with a six-month transition, it is not negligible.
Common Pitfalls to Avoid
The biggest source of rework is incomplete or inconsistent allocation bases across worksheets. Worksheet S-3 might use direct patient service revenue as its base while Worksheet S-4 pulls from a different denominator. They should align or you need a documented explanation for why they diverge. Auditors will ask for that explanation and if you cannot provide it, they will adjust the numbers themselves, which usually means your settlement goes down. A second pitfall is ignoring the instructions on the latest version of each worksheet. CMS updates the forms periodically and the numbering or layout sometimes shifts. I once used a template from the previous fiscal year and missed a new line item for telehealth expenses that CMS now requires separately allocated. The omission was small but sufficient for the auditor to issue a deficiency finding that required a revised submission within sixty days. Always verify the version date on every worksheet before you start entering data. A third issue is underestimating the time required for the capital section. If your facility has undergone acquisitions, equipment purchases, or depreciation changes during the year, the capital worksheet can easily consume forty to sixty hours of work. Start it early. Do not wait until the last week before the filing deadline to begin mapping assets. You will not regret that advice.
When to Use Software versus Manual Methods
Large health systems with dedicated cost reporting staff typically use platforms like PointCare, Medaffiliated, or HealthGradients. These tools connect to your ERP, auto-populate the worksheets, and perform built-in validation checks. The investment is real but the time savings are measurable. A manual cost report that takes four to six weeks to complete can often be reduced to two or three weeks with automation, assuming the data integration is clean. Smaller hospitals and critical access facilities often complete their cost reports manually or with lighter tools. This is fine if you have a clear process and someone who knows what they are doing. The risk is that the manual route leaves more room for data entry errors and missed cross-references. If you are doing this without software, build a checklist and have a second person review the final worksheet package before submission. One pair of eyes is not enough.
Final Notes on Reality
Medicare Cost Report Worksheets are not difficult if you approach them systematically. They are time-consuming, error-prone in the capital and allocation sections, and unforgiving once submitted. The process rewards preparation and punishes procrastination. Plan your data gathering timeline at least eight weeks before the due date. Leave two weeks for review and revision. The remaining time is for actual worksheet completion. There is no shortcut around the fundamentals. You need clean financial data, accurate allocation bases, and someone who understands what each worksheet is actually measuring. If you lack internal expertise, consider hiring a cost reporting consultant for the initial build or for an audit review. It usually costs less than the penalties and adjustments that come from filing incorrect worksheets.


