What the HRA Actually Is
The Medicare Health Risk Assessment form is a clinical screening tool used by Medicare Advantage plans and some Medicare Parts C organizations. It collects data on a beneficiary's health status, functional limitations, and social determinants of health. The goal is risk adjustment and care gap identification, not diagnosis. You fill it out to generate a Hierarchical Condition Category (HCC) code that affects the plan's reimbursement from CMS. It looks like a standard questionnaire but carries real financial weight. Plans use the data for capitation calculations. That's why getting the responses right matters more than most beneficiaries realize.
Medicare Health Risk Assessment Form 2022
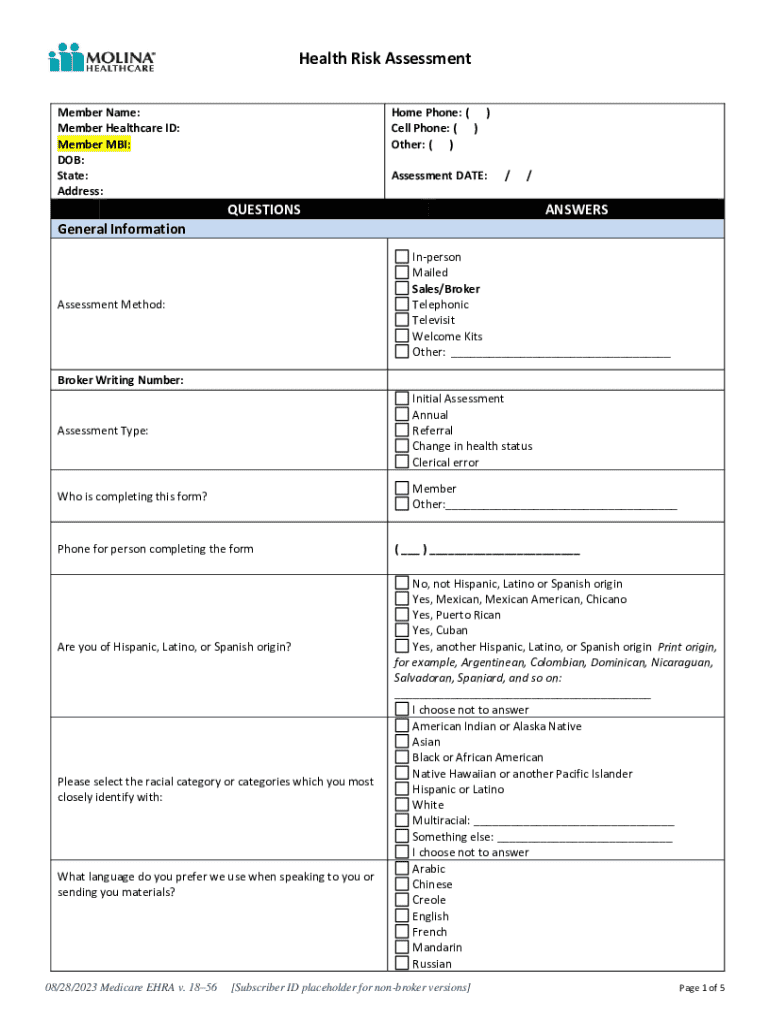
The 2022 version of the HRA reflects a few changes from prior years. The biggest shift was in how the cognitive screening questions are weighted. Previously, a response indicating mild cognitive impairment might not have triggered an HCC flag. In 2022, CMS tightened the scoring criteria so that certain dementia and cognitive disorder responses produce more consistent risk adjustment scores across plans. You can download the form from your plan's member portal or from the MACRA/MACPAC resource pages. Most plans also offer it through electronic platforms like Change Healthcare or Availity. The paper version is still widely distributed through mailings, particularly to beneficiaries who haven't enrolled digitally. Here's what nobody tells you about the form: it's not a one-size-fits-all document. The same HRA template gets used across dozens of plan types, but each plan maps the questions to its own risk adjustment model differently. A question about mobility difficulty might produce an HCC code under one plan's methodology and not under another's. That's because the mapping depends on the plan's contract with CMS and the specific HCC model version they're using.
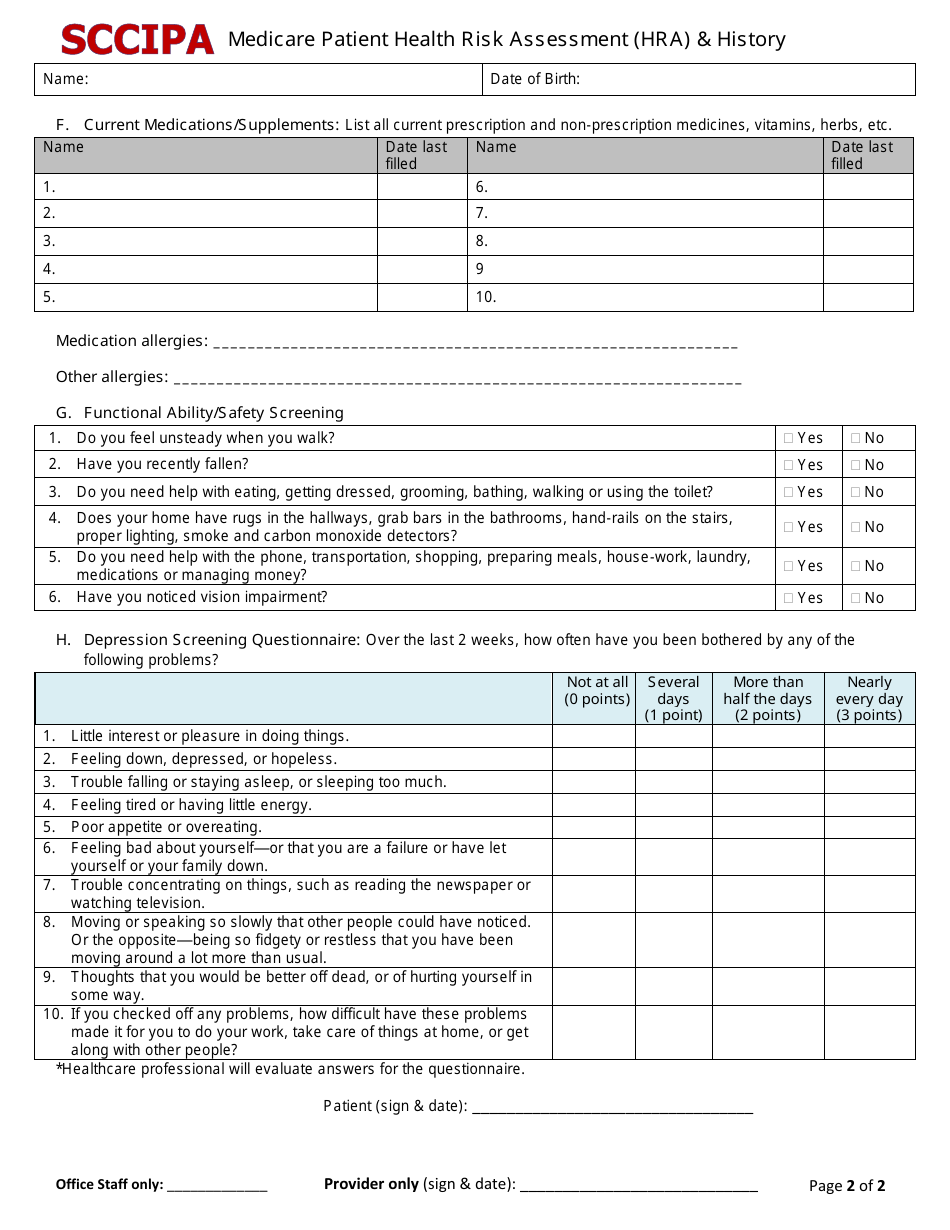
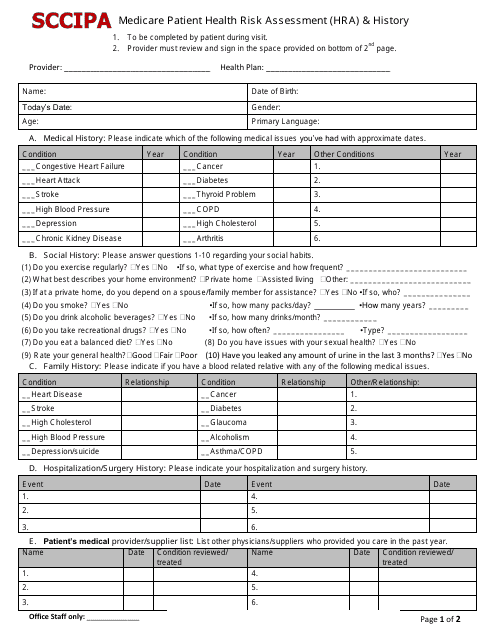
I ran into this problem firsthand when a client completed the HRA for her husband. She checked yes to a question about needing assistance with bathing. The plan submitted the corresponding ICD-10 code and got flagged for audit. CMS questioned whether the documentation supported the severity level. We went back to the source and realized the plan had mapped the answer to an incorrect specificity level in the code set. The workaround was to pull the physician's office notes from the same visit, confirm the functional limitation was documented there, and resubmit with the correct N1 modifier attached to the HCC code. It added two weeks to the process but resolved the audit flag without further review. The form itself is straightforward. It covers things like self-reported diagnoses, medication use, activities of daily living, vision and hearing status, and behavioral health indicators. Some sections ask about tobacco use, fall history, and nutritional status. The data collection usually takes about ten to fifteen minutes for a competent beneficiary. Longer if the person has significant cognitive deficits and needs a caregiver or proxy respondent. One thing that trips up people is the question ordering. Some versions of the form place the cognitive screening items near the end. If the beneficiary gets fatigued or distracted, they skip those sections entirely. That leaves gaps in the HCC capture. I learned to scan the completed form before submission and flag any skipped sections that should have been answered. It's a minor step but it prevents costly omissions down the line.
Get the Full Details

Another nuance worth noting: the HRA does not replace a clinical evaluation. It's a self-reported screening instrument. CMS expects the responses to be confirmed through medical records when the data feeds into risk adjustment. Plans that rely solely on HRA data without supporting documentation tend to get hit with recoupment demands during audit season. The form is the starting point, not the final authority. The 2022 version also includes updated questions around social determinants of health. These cover things like housing stability, food security, and transportation access. While these don't directly generate HCC codes, they feed into the plan's care management strategies and can influence quality rating calculations under Star Ratings. That's why some plans treat these sections with as much importance as the clinical questions. If you're filling this out for yourself or a family member, here's what to keep in mind. Answer every question honestly and completely. Don't leave sections blank. If you need help, have a caregiver or family member read the questions aloud and record the answers. Make sure the proxy respondent is noted on the form. CMS requires documentation of proxy completion, and missing that notation can invalidate the data.
The form doesn't have a strict deadline built into its design. Plans typically send it out during open enrollment or annual enrollment periods. But there's no penalty for late completion beyond the missed opportunity to capture HCC codes for that calendar year. Risk adjustment happens annually based on the data collected during the plan year. If you miss the window, the next opportunity is the following year. Downsides to the HRA process are worth acknowledging. The self-reporting nature introduces bias. Beneficiaries sometimes underreport symptoms because they don't want to be seen as dependent or frail. Others overreport because they assume it'll get them more services. Both behaviors distort the risk score. There's also the issue of literacy. The reading level of the form is roughly sixth grade, but some questions use medical terminology that confuses respondents. A helper is almost always necessary for accurate completion. A practical alternative for plans that want more reliable data is pairing the HRA with an in-person health risk appraisal conducted by a nurse or trained care coordinator. Those evaluations tend to produce fewer missing responses and better documentation trails. They also cost more, which is why most plans stick with the self-administered version. It's a trade-off between accuracy and operational efficiency.
For individual beneficiaries, the key takeaway is that the Medicare Health Risk Assessment Form 2022 is a tool, not a test. It doesn't determine eligibility or benefits directly. It informs how the plan assesses risk and allocates resources. Completing it accurately helps ensure the plan has the data it needs to coordinate care appropriately. Skipping it or rushing through it means leaving money and potentially services on the table for the next year. The form is available through most plan websites and member services departments. If you can't find the 2022 version specifically, contact your plan's member support line. They'll send you the current iteration, which may include minor updates from the prior year. The core structure remains consistent, but the coding mappings shift slightly as CMS updates its risk adjustment model annually.