Why the standard Medicare analysis template doesn't work for most people
I've been running Medicare needs analyses for clients for a while now, and the biggest problem I see isn't the math. It's that most agents use the same generic questionnaire everyone else uses. The questions end up being so broad they produce results nobody can act on. A client tells you they're worried about costs without giving you any actual numbers. You guess. Everyone loses. The difference between a sloppy analysis and one that actually moves a sale is the sequence and specificity of the questions you ask. I learned this the hard way after a situation that still bothers me. I was working with a couple in their late 60s who had both worked in tech and had decent 401k balances. Standard questionnaire said they were solid candidates for Medicare Advantage. I pushed the traditional plan because something felt off during the interview. They hesitated on a couple of unexpected questions about their expected healthcare usage. Turned out one of them had just been diagnosed with early-stage cancer. The standard analysis completely missed it because the forms don't ask about pending or recent diagnoses. Traditional Medicare plus a Medigap policy ended up saving them roughly eighty thousand dollars over five years compared to what the Advantage plan would have cost with all the specialists and treatments involved. That gap wouldn't have existed if the questions were tighter from the start.
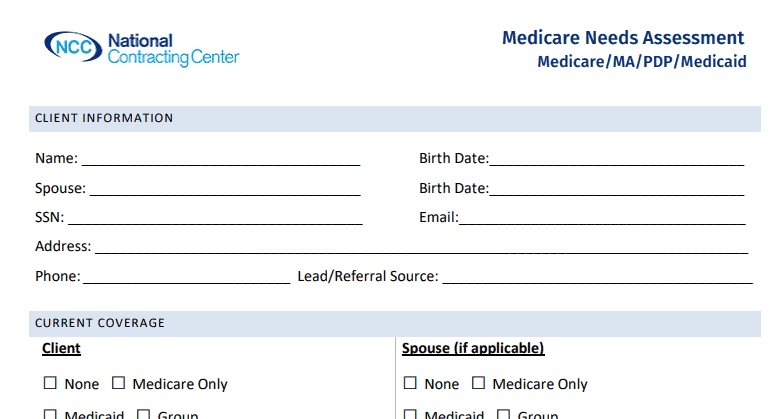
Medicare Needs Analysis Questions That Actually Work
Here's what I've built over years of this work. The questions are grouped by category, but I don't present them that way to clients. I flow from one topic to the next conversationally. Starting with finances because that's what keeps people up at night, then moving into health status, then preferences. Financial foundation questions: What is your current monthly income from all sources including Social Security, pensions, retirement accounts, and any remaining employment? This isn't about how much they make. It's about whether premium costs will crowd out basic living expenses. I've seen people qualify for subsidies they didn't know existed simply because their income profile fit Part D low-income subsidy thresholds. Another question here is whether they own their home or rent, and what their estimated monthly housing cost is. This matters for Medicaid spend-down scenarios in some states.
What are your current monthly healthcare expenses outside of insurance premiums? Prescription costs, dental, vision, hearing aids, medical equipment, frequent over-the-counter purchases. People consistently underestimate this. A typical retiree couple might be spending four to nine hundred dollars a month on out-of-pocket healthcare costs before Medicare even enters the picture. Getting real numbers here changes everything about which plan makes sense. Do you have any existing health savings account, flexible spending account, or settlement money that could offset healthcare costs? These get ignored constantly. An HSA balance can cover years of Medicare premiums and out-of-pocket costs if managed correctly. I had a client with about sixty thousand in an HSA who thought it was irrelevant because he hadn't used it in years. That account alone made traditional Medicare with a supplemental plan viable for him instead of forcing him into Advantage. Health status and usage questions:
Get the Full Details

How many regular healthcare providers do you currently see? List each specialist and the frequency of visits. This is the question most analyses skip. Someone with rheumatoid arthritis seeing a rheumatologist monthly and a primary care doctor quarterly is in a completely different risk category than someone who sees a doctor once a year for a physical. Network restrictions in Medicare Advantage plans become a real problem with multiple specialists. I recommend checking each provider's participation status in any plan you're considering before presenting it. Are you currently taking any prescription medications, and what are the monthly costs? Don't accept vague answers. Get the medication names, dosages, and pharmacy. Formulary coverage varies wildly between Part D plans and between Advantage plans that include drug coverage. A medication that costs twenty dollars a month under one plan can cost two hundred twenty dollars under another. This is where people get blindsided. Do you have any chronic conditions or ongoing health issues that require regular monitoring or treatment? Be direct about this. Conditions like diabetes, heart disease, COPD, kidney disease, and cancer history all shift the calculus. Chronic conditions often mean higher out-of-pocket maximums matter more than lower monthly premiums. The out-of-pocket maximum on Medicare Advantage plans caps your annual spending, but traditional Medicare has no cap without supplemental insurance.
Provider and hospital preference questions: Which hospitals do you prefer or currently use? Most people don't realize that Medicare Advantage plans have narrow hospital networks in many markets. Your preferred hospital might not be in-network. I had a situation where a client's cardiologist was affiliated with a hospital system that wasn't covered by several popular Advantage plans in their area. Switching to one of those plans would have meant either changing doctors or paying significantly more out-of-network. Do you have any doctors you want to keep seeing? Verify their Medicare participation status and network inclusion before you commit to anything. Some specialists don't accept Medicare Advantage at all. They take traditional Medicare plus a Medigap plan. If a client is attached to a specific specialist, this can rule out numerous Advantage options immediately.
Lifestyle and travel questions: How many days per year do you spend outside your home state? If the answer is more than thirty, Medicare Advantage plans are generally a poor choice. Most Advantage plans don't provide adequate coverage outside your service area. Emergency coverage exists everywhere, but routine care and specialist visits are severely limited. Traditional Medicare works nationwide. This single question eliminates half the plans on the market for a significant portion of clients. Do you travel internationally? Medicare doesn't cover any care received outside the United States except in very rare border scenarios. Some Advantage plans offer limited travel benefits, but they're nowhere near comprehensive. International travelers need supplemental coverage or a separate travel health policy regardless of which Medicare path they choose.

Future planning questions: What is your tolerance for predictable versus unpredictable costs? Some people hate surprise bills and would rather pay a higher premium for peace of mind. Others prefer lower premiums and are comfortable managing costs as they come. There's no wrong answer here, but it determines whether a Medigap plan or an Advantage plan with low premiums makes more sense. I've found that people in their early sixties tend to be more risk-tolerant than those approaching sixty-five with existing health issues. Are you currently receiving disability benefits through SSDI? If so, you'll be eligible for Medicare after twenty-four months of disability. The coordination between disability and Medicare can be confusing. Some clients don't realize they have a special enrollment period that isn't time-limited like the general enrollment period. Missing this window can result in delayed coverage and penalties.
How to structure the actual analysis session
Don't rush through these questions. A proper needs analysis takes between forty-five minutes and an hour. I used to try to compress it into twenty minutes because I thought efficiency mattered. It didn't. Rushed sessions produce missed details. Missed details produce wrong recommendations. Wrong recommendations produce complaints and replacements, which destroy your retention metrics. Take notes during the conversation. Don't rely on memory. I use a simple spreadsheet that tracks every answer alongside relevant plan implications. When a client mentions a medication, I immediately note the formulary tier. When they mention a specialist, I flag the network check. This takes an extra ten minutes but prevents embarrassing situations where you recommend a plan and then discover the client's regular doctor isn't covered. Present findings back to the client in plain language. Don't use industry jargon. Instead of saying "your out-of-pocket maximum exposure is limited," say "the most you'd pay in a bad year is three thousand dollars with this plan." Concrete numbers stick. Abstract concepts get forgotten.
Where this approach falls apart
Medicare needs analyses have real limitations. The biggest one is that they're only as good as the information the client provides. Many people don't know their medication costs. They don't know their specialist's network status. They underestimate their healthcare usage because they haven't had serious problems recently. You can ask all the right Medicare Needs Analysis Questions, but if the client is misinformed or evasive, the output will be wrong. I've had to redo analyses three or four times when initial answers turned out to be inaccurate. This happens more often than you'd think. Another limitation is that plan options change every year. What was the best plan in January might not be the best plan in September. Premiums shift. formularies change. Networks expand and contract. Any analysis you produce today has a shelf life of roughly six to eight months before you should revisit it. I schedule follow-ups with clients at the seven-month mark specifically to catch plan changes that might affect their situation. Finally, these analyses can't account for every edge case. I encountered a client last year whose situation involved a combination of Employer Group Waiver Plan eligibility, part-time work at age sixty-six, and a spouse who was already enrolled in Medicare. None of the standard question frameworks addressed this overlap properly. I ended up building a custom analysis that pulled data from multiple sources including the employer benefits department and the local Social Security office. It took three hours of research to produce a recommendation that was essentially correct but never guaranteed until enrollment was complete. There's no shortcut for situations this complex.

If you're working with clients who have employer coverage still active, or who are in situations involving Medicaid dual eligibility, or who have special enrollment periods from other qualifying events, a standard questionnaire isn't sufficient. Those cases require direct consultation with benefits specialists or enrollment counselors who understand the intersection of programs. No amount of well-structured questions will replace that expertise.