Medicare Outpatient Physical Therapy: A Practical Guide for Providers
Medicare pays for outpatient physical therapy under Part B. It is straightforward until it is not. The rules change every year, the therapy caps shift, and the documentation requirements seem designed to trip people up. Here is what you actually need to know to bill this correctly without losing sleep over audits. The key document governing all of this is the Medicare Outpatient Physical Therapy Guidelines. These guidelines cover who qualifies, what services are reimbursable, how the therapy cap works, and what documentation Medicare expects. If you are billing Medicare PT at all, you should have this in front of you and refer to it constantly.
Understanding the Medicare Outpatient Physical Therapy Guidelines
Medicare covers physical therapy on an outpatient basis when it is deemed reasonable and necessary. That phrase matters more than it sounds. Medicare will deny services it considers experimental, unnecessary, or not part of a comprehensive plan of care. Your documentation needs to reflect that plan from day one. Here is how the actual billing structure works. Medicare Part B covers outpatient PT services. There is no separate deductible for PT specifically - it rolls into your standard Part B deductible, which was $240 in 2024. After that, Medicare pays 80% of the Medicare-approved amount for covered services, and the patient is responsible for the remaining 20%. That is the baseline. Everything else is exceptions and specifics. Let me tell you about a specific problem I ran into last year. A clinic was billing Medicare for a patient who had completed their annual therapy goals. The PT department kept scheduling follow-up sessions because the patient wanted to continue. The claims got denied. The issue was not that the patient did not want services - it was that Medicare requires documented medical necessity tied to ongoing goals. Without revised plans of care and updated goals reflecting continued need, those visits were not billable. The workaround was straightforward: the attending physician signed new goals, the PT updated the plan of care, and we started billing again. But the months of lost revenue were already gone. I made sure every provider on that team understood that goal closure means the game changes immediately.
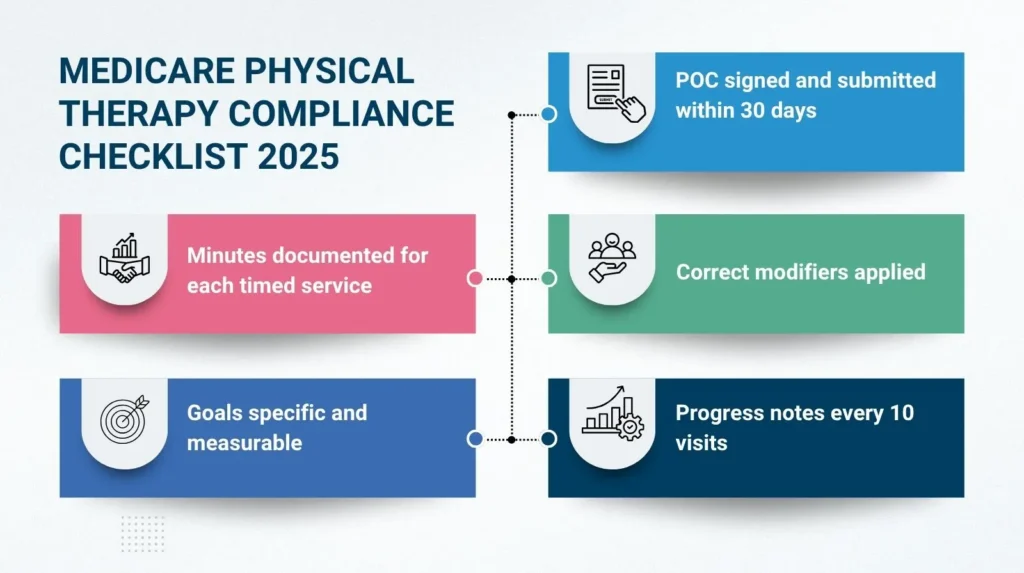
There are two counter-intuitive things about Medicare PT billing that most people miss. The first is the annual therapy cap. For a long time, there was a hard dollar limit on covered therapy services. That limit no longer exists in the same form. What replaced it is the KX modifier threshold. When your therapy charges exceed the combined threshold (which was $2,410 for PT and SLP combined in 2024), you need to add a KX modifier to your claims. This tells Medicare that the services exceed the threshold but are still medically necessary. Without that modifier on claims above the threshold, they get denied automatically. Most billing systems flag this now, but smaller practices running older software might not have this built in. The second thing people get wrong is the skilled versus unskilled distinction. Medicare only covers skilled services. If a patient needs assistance with gait training, manual therapy, or therapeutic exercise that requires a licensed PT, that is skilled. If they just need someone to walk alongside them while they practice basic walking, that is not covered. You can bill for home exercise programs that the patient performs independently, but you cannot bill for supervision-only scenarios. The nuance here is that even when a patient is making good progress, if the services no longer require a therapist's skill, Medicare will not pay. You need to reassess and either modify the plan to justify continued skilled service or discharge with a home program. Documentation requirements under Medicare are not suggestions. Here is what you need on file for each episode of care: an initial evaluation within 30 days of the first treatment, a plan of care signed by the referring physician, progress notes for every visit, a reassessment at least every 30 days, and a plan of care review every 90 days or when there is a significant change in the patient's condition. Missing any of these creates an audit vulnerability. I have seen practices lose thousands because a 90-day plan of care review was not signed and they could not produce it during a recovery audit.
Get the Full Details

Let me give you some practical numbers. The average time spent on documentation for a 30-minute PT session in a busy outpatient clinic is about 5 to 8 minutes per note. If you are seeing six patients a day across four therapists, that is roughly 120 to 160 minutes of documentation time daily just for standard notes. Group therapy notes take longer per patient because you need individualized sections that show each person's participation and response. A typical group note for four patients might take 15 to 20 minutes total. Factor in the initial evaluations which can run 20 to 30 minutes each, and you are looking at a significant portion of clinical time going toward paperwork. The Medicare Outpatient Physical Therapy Guidelines also cover telehealth, which expanded significantly during the pandemic and has remained in effect past my original expectation. Remote PT services are covered when they meet certain conditions. The patient must be in their home or a qualified clinical setting, the service must be appropriate for delivery via telehealth, and you need to use compliant technology. You cannot just call a patient and provide PT advice over the phone and expect payment. The current guidelines list specific CPT codes that are eligible for telehealth billing, and this list changes. Check it annually. Here is another detail that causes problems: incident-to billing. If a PT assistant or other qualified personnel is providing services under the direct supervision of a physician, you may be able to bill at 100% of the Medicare rate instead of the typical 85% rate for assistant therapy. The requirements are strict. The physician must be present in the office suite, the service must be part of the patient's ongoing plan of care, and the physician must have established the plan of care. Miss any of those and you are back to 85%, or worse, facing an overpayment claim. I had a case where a practice billed incident-to for six months while the supervising physician was on vacation. The claims were technically invalid for that period, and the recoupment came to over $8,000. They learned to track physician presence in real time after that.
The frequency limitations are another area worth understanding. Medicare does not set a hard limit on the number of PT visits, but it does expect services to be reasonable and necessary based on the patient's condition. Some Medicare Administrative Contractors (MACs) have specific coverage articles that reference visit frequency benchmarks. For example, one MAC might flag claims if a patient receives more than 40 sessions in a year without clear documentation of why additional sessions are medically necessary. Your documentation needs to justify the intensity and duration of treatment, not just the type of service provided. If you want the official guidelines, you can find them on the Centers for Medicare and Medicaid Services website. Search for the Medicare Learning Network manuals, specifically section 100-04 Chapter 15, which covers physical therapy and related services. That is the primary reference document. You can also consult your local MAC's jurisdiction-specific guidance, since coverage can vary slightly by region. I keep both documents bookmarked and check them whenever a rule change announcement goes out. CMS publishes updates several times per year, and missing one can cost you. The bottom line is that Medicare outpatient PT billing is manageable if you treat the guidelines as a working document rather than something you glance at once a year. The documentation standards are real, the KX modifier threshold is critical once charges exceed it, and the skilled service requirement is the line you cannot cross without justification. Practices that maintain clean records, update plans of care on schedule, and verify telehealth eligibility each year tend to have very few problems with Medicare audits. Those that cut corners on the 90-day reviews are the ones who end up explaining themselves later.
I keep a checklist posted in the staff room covering the six main documentation requirements and the current KX threshold. It takes about 30 seconds to scan and saves hours of retrospective research when questions come up. That is the kind of small system that actually prevents billing errors more reliably than training sessions or policy memos.