Why Most People Skip the Comparison Step (And Regret It)
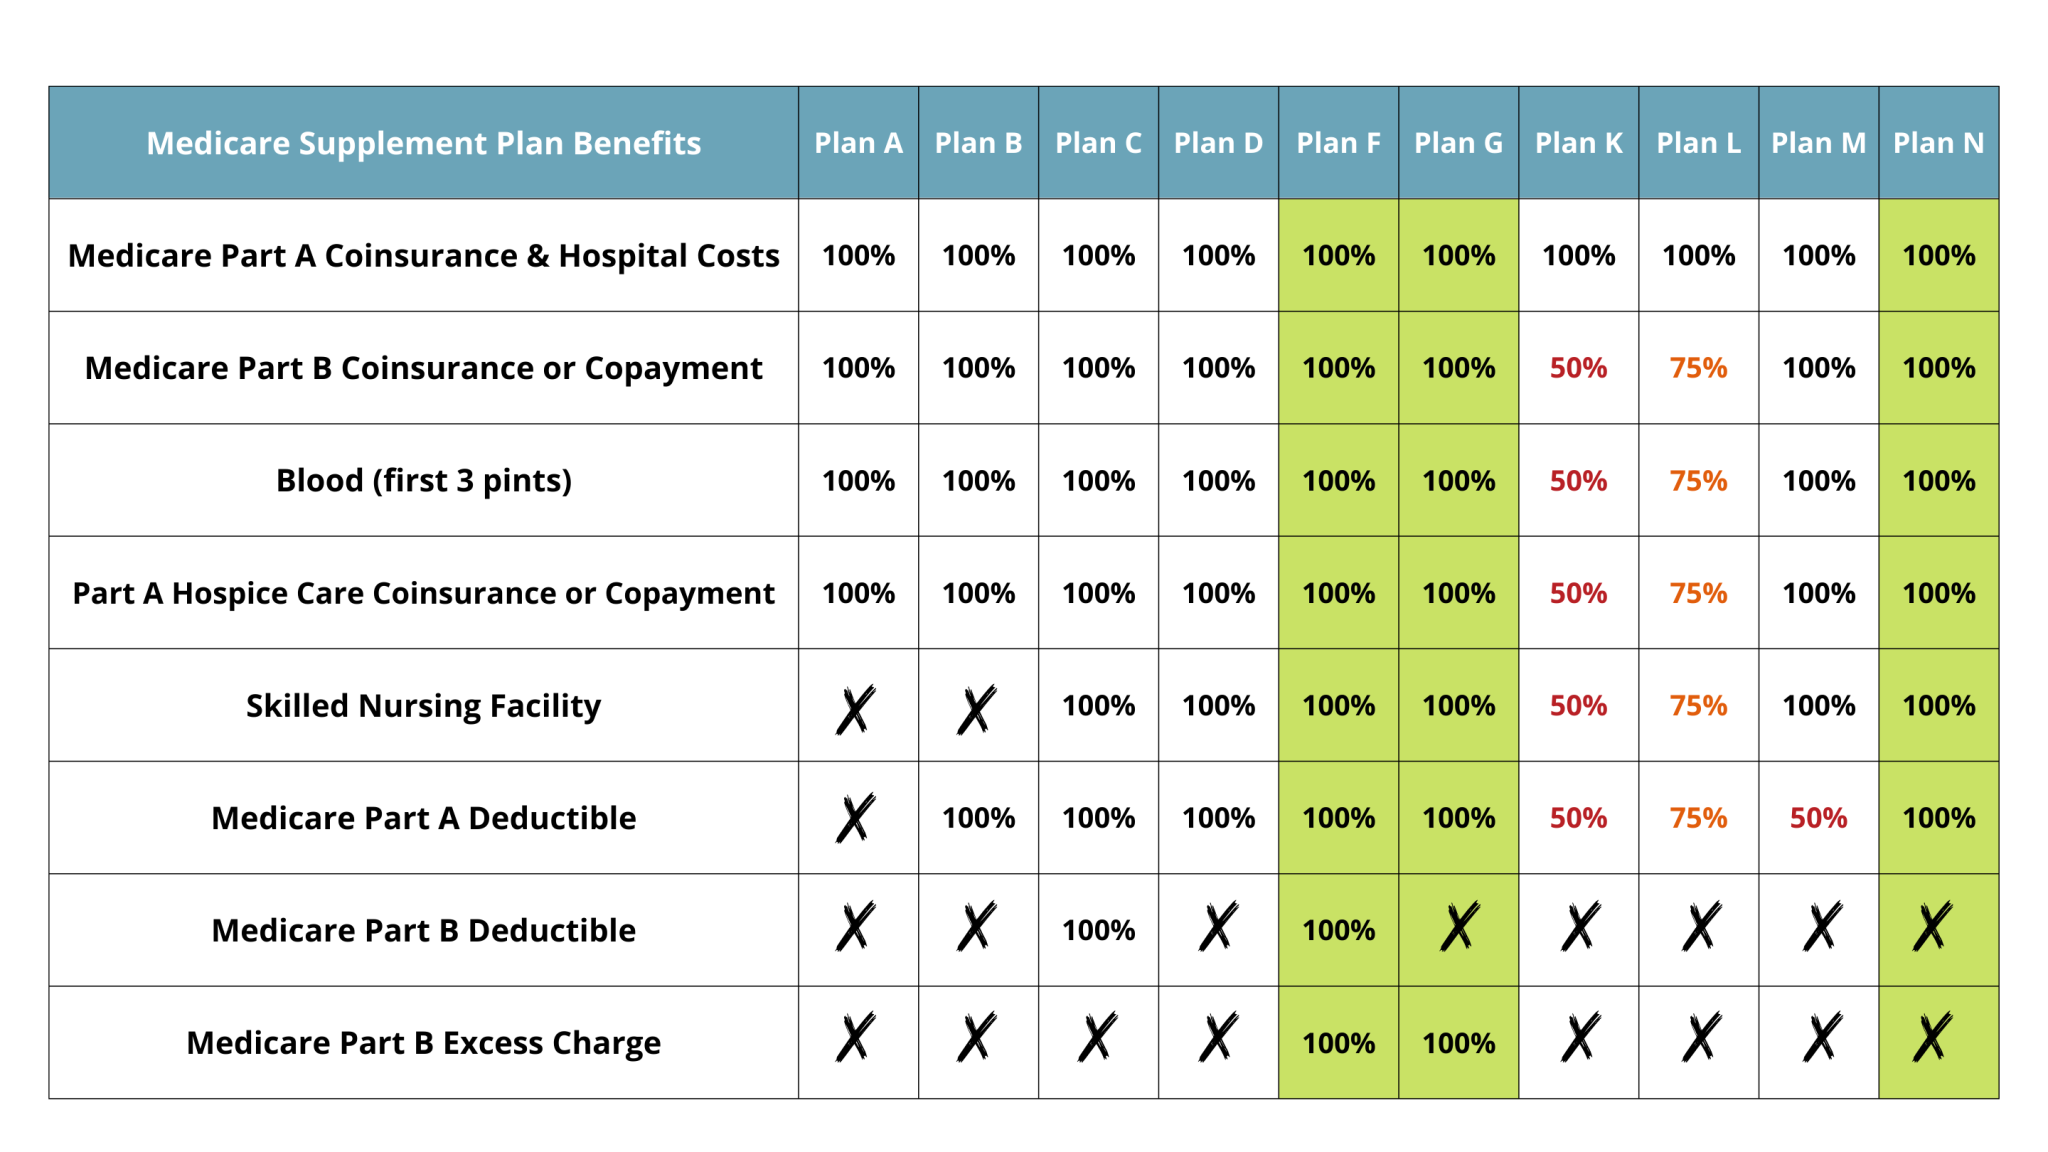
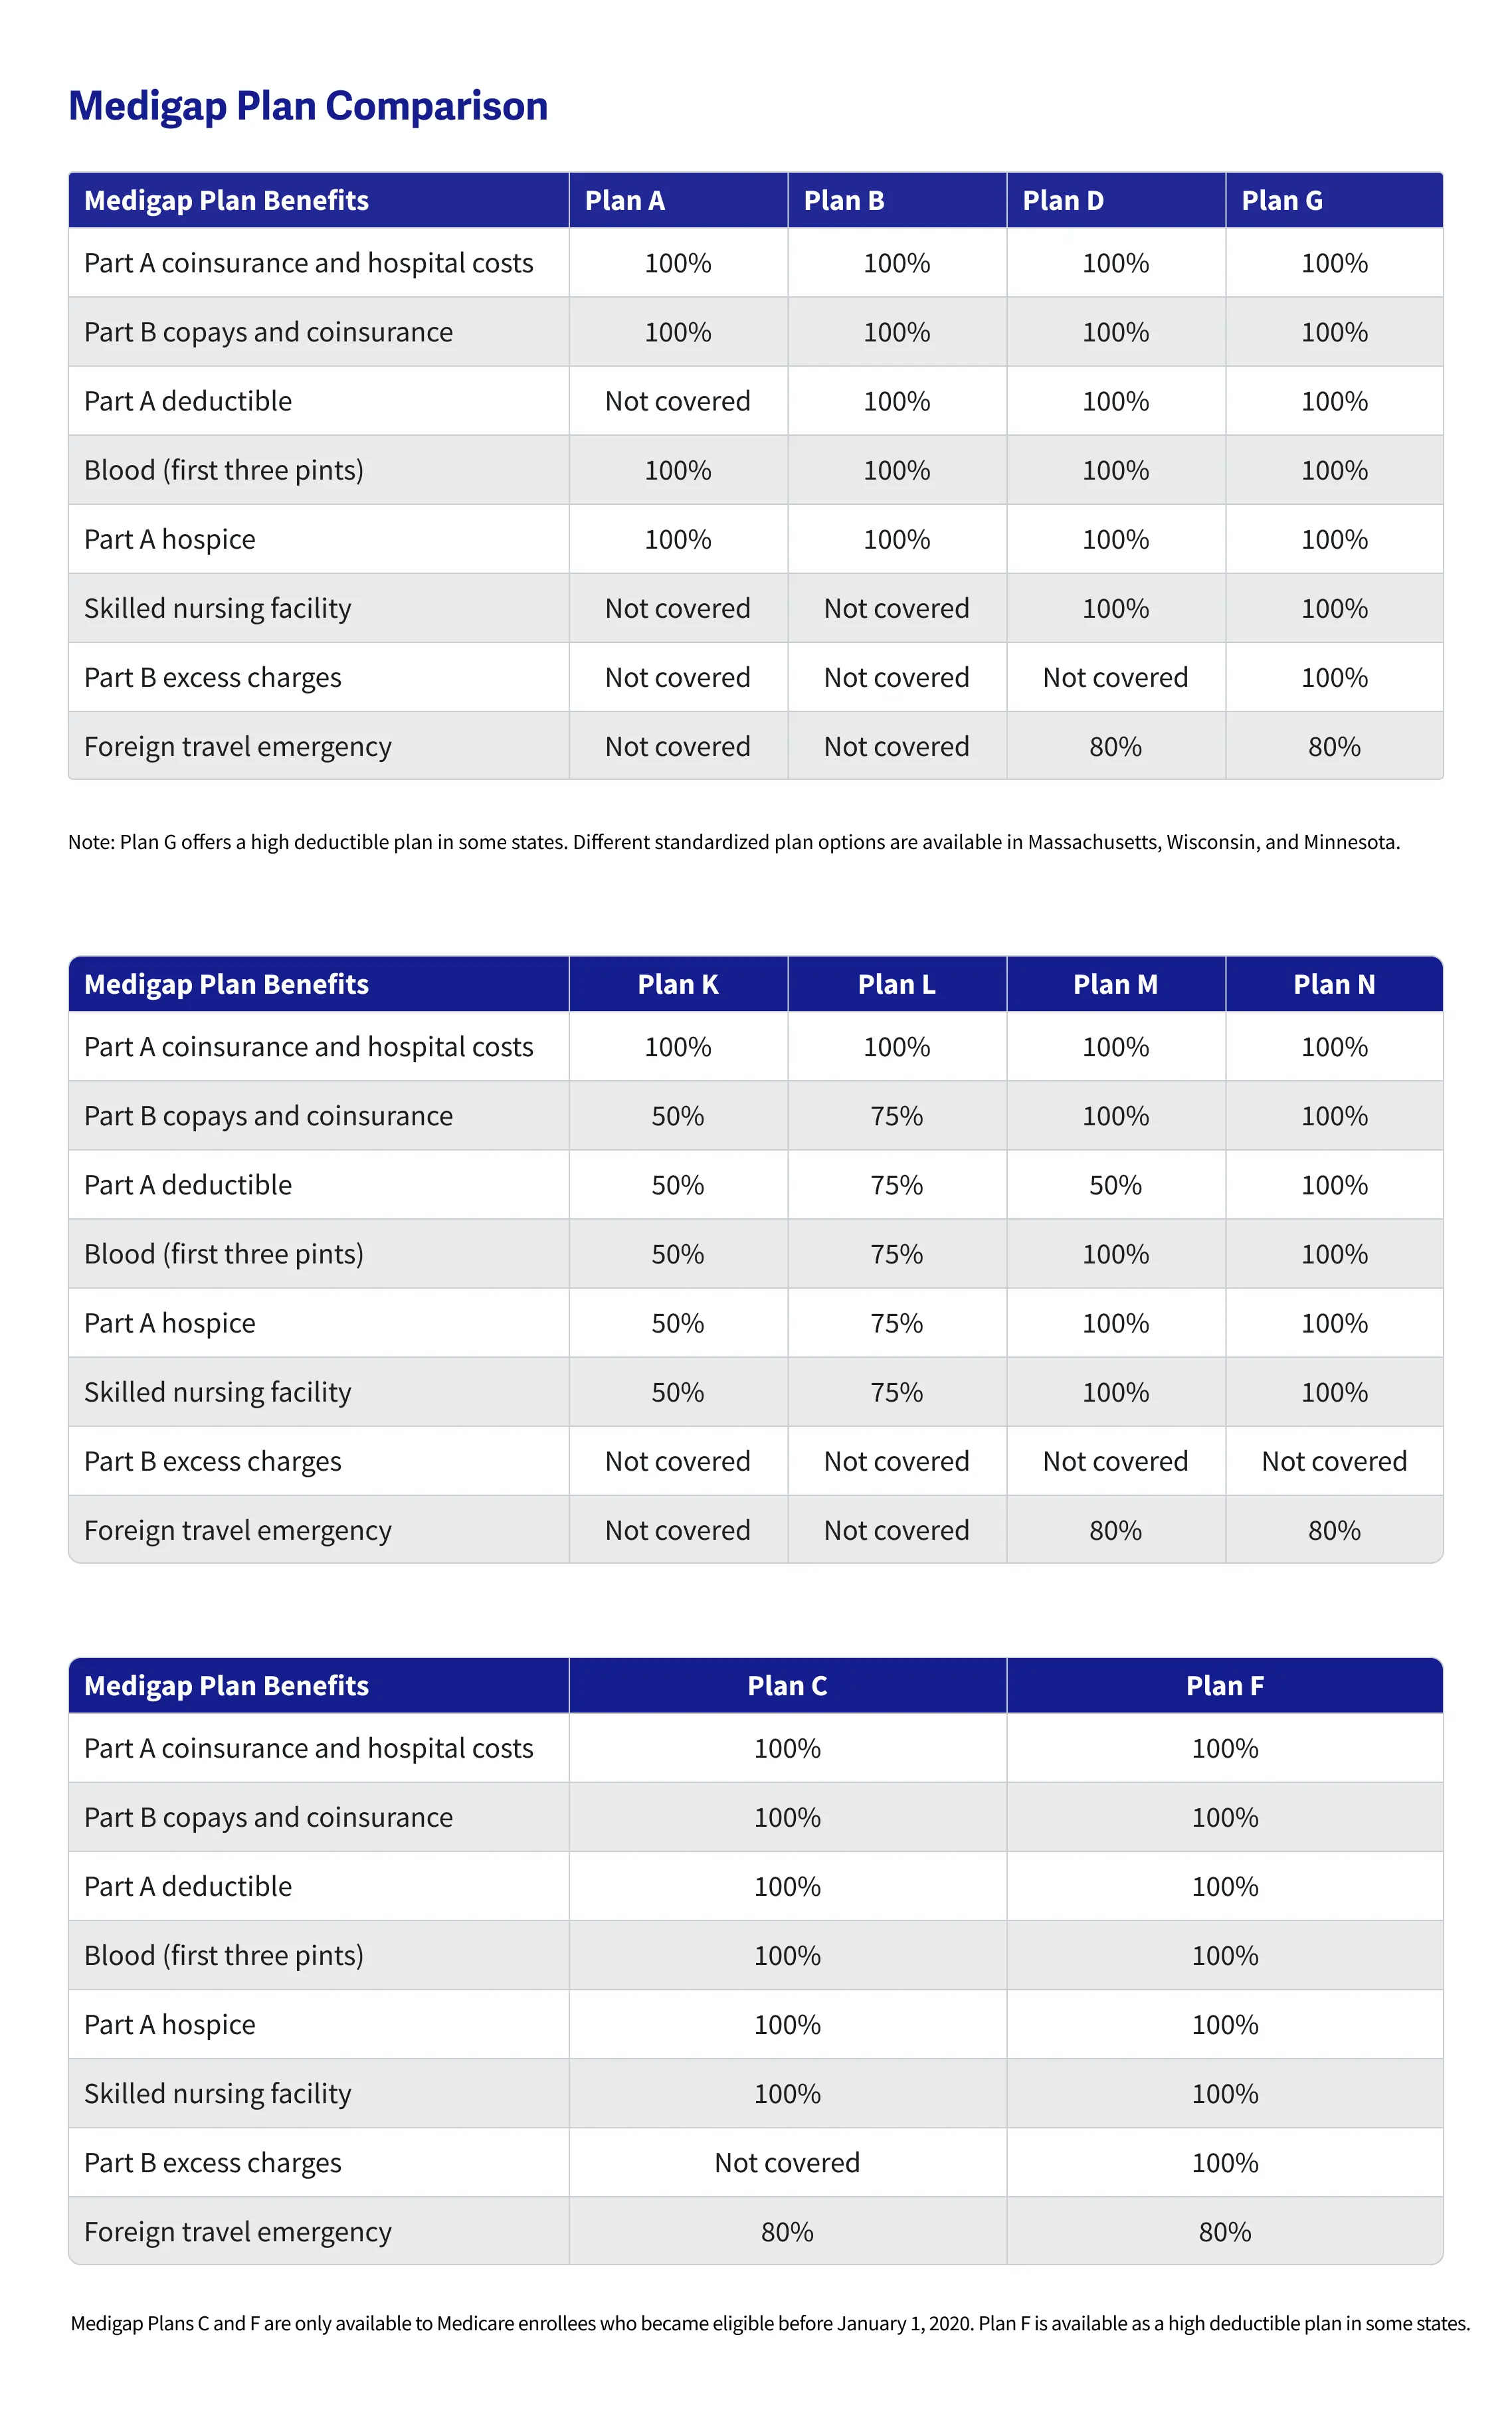
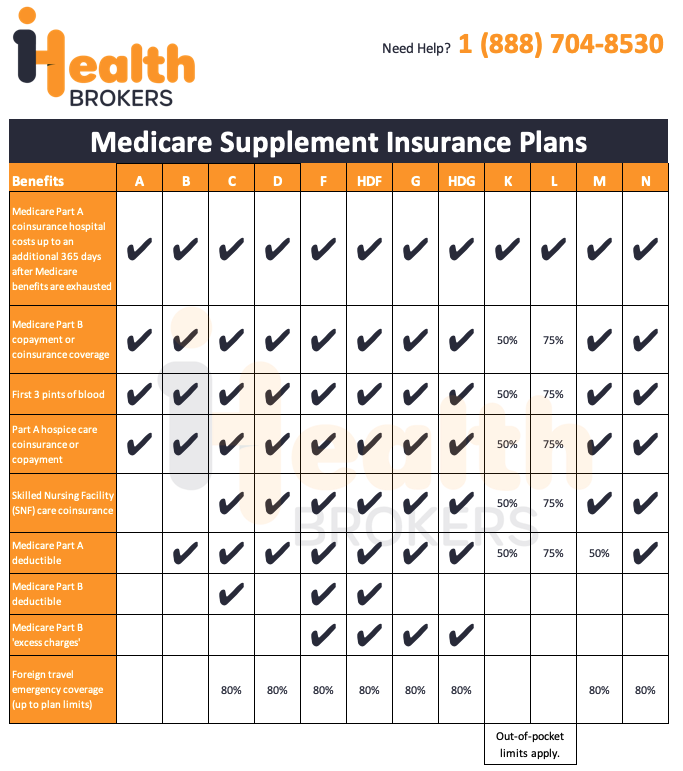
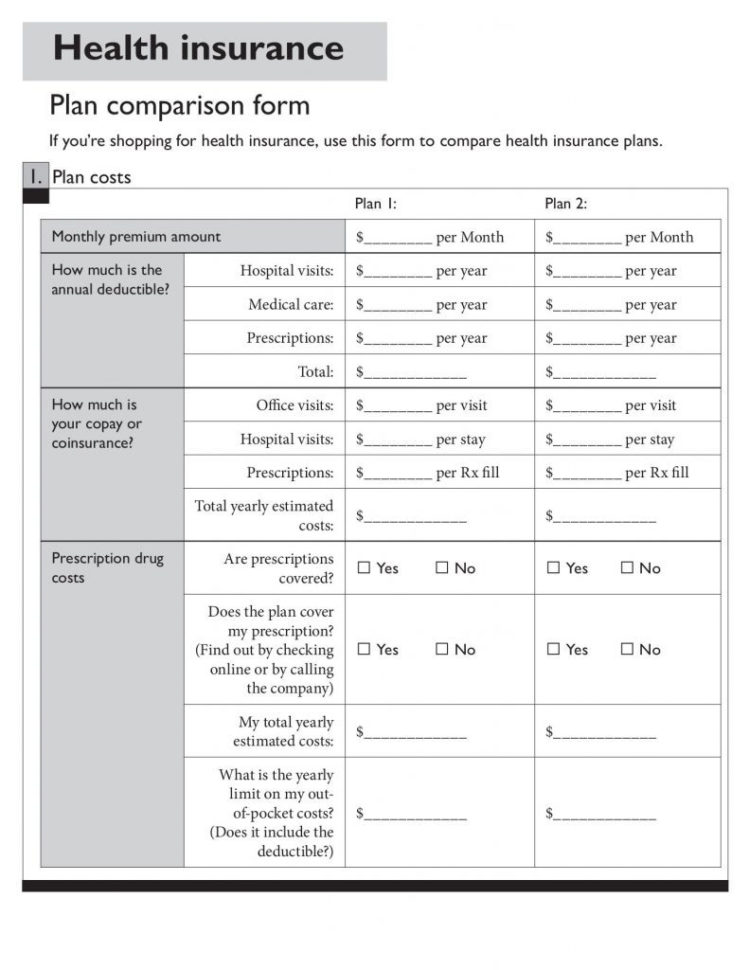
I've watched hundreds of beneficiaries pick a plan off a list, click submit, and never look back until their pharmacy bill arrives in October. The Social Security website has a comparison tool that technically does what it's supposed to do. It also does it in a way that makes almost everyone make the wrong choice. The Medicare Plan Comparison Worksheet is a spreadsheet framework most financial advisors won't tell you about because they want to be the one helping you interpret the government data. You don't need them. You just need to know how the pieces actually fit together before you enter any plan information. Start with a blank spreadsheet. Column A is your current health situation: your estimated annual prescription drugs by tier, your expected doctor visits, any planned procedures, and your income bracket for IRMAA purposes. Put that on one sheet. Create a second sheet where each row is a plan option you're considering. The columns should be: Part B premium, Part B deductible, plan maximum out-of-pocket, Part D deductible (if applicable), and the tiered drug costs under that specific plan's formulary. Then add a column for total estimated annual cost, which is just the sum of all the above based on your own numbers. The critical mistake people make is looking at the monthly premium as the deciding factor. A plan with a $0 monthly premium can easily cost you twice as much over the course of a year once you factor in the higher Part B deductible, the gap in prescription coverage, and the out-of-pocket maximum that doesn't kick in until you've spent $8,000 or more. I had a client in 2023 who chose a $0-premium Medicare Advantage plan because her primary care visits were covered at 100%. She had no idea the plan required prior authorization for her cardiac medication, which she needed every three months. Each authorization took 11 business days to process. By the time she switched plans, she'd missed two refills and been to the emergency room twice. The worksheet would have caught that the moment she pulled the plan's summary of benefits and compared it against her medication list.
Here's the part nobody mentions: Medicare Advantage plans can change their formularies mid-year. The plan that covered your medication at Tier 2 when you enrolled might move it to Tier 3 by July. There is no requirement for them to notify you directly. They send a formulary change notice, but it goes to the address on file and most people don't read those documents. Check the plan's current formulary yourself every time you need a refill. Add a column to your worksheet for "formulary stability risk" if you're on multiple medications. Plans from the same parent company but different regions often have different formularies, so don't assume Plan A in Florida is the same as Plan A in Ohio.
How to Actually Use the Worksheet
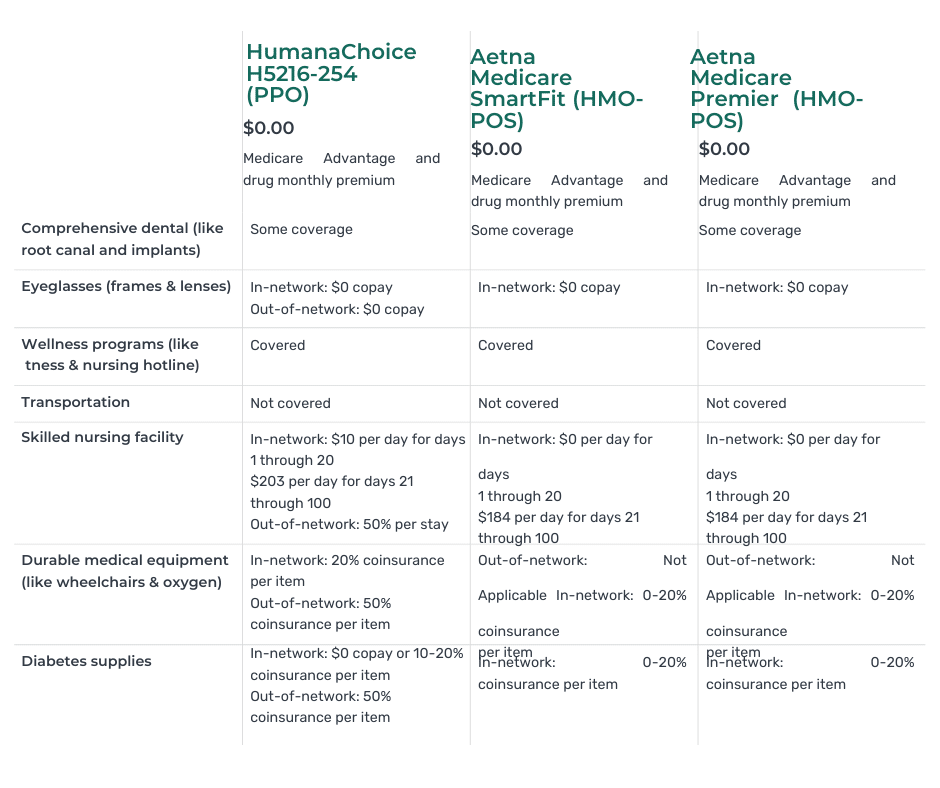
Enter your real numbers, not optimistic ones. If you have a chronic condition, estimate your healthcare usage at the 75th percentile, not the median. You are not a healthy person making a healthy budget. If you go to the specialist quarterly, put four visits. If you take three brand-name drugs, put three brand-name drugs at the cost the plan lists for that tier. The worksheet becomes useful the moment you can see which plan has the lowest total cost across your most likely scenario, not your best-case scenario. There's a technical detail most people miss with the Part D comparison. The government calculator at Medicare.gov assumes you reach the coverage gap and then the catastrophic threshold. That's correct for the average beneficiary. It's wrong for anyone who stays below the gap because their plan has a generous coverage phase or they qualify for Extra Help. If you're near the Income Related Monthly Adjustment Amount (IRMAA) threshold, running the numbers twice—once with IRMAA and once without—will show you whether a slightly more expensive premium plan actually saves you money when you factor in the surcharge. I built this into my own worksheet by adding an IRMAA toggle row that adds the applicable surcharge to whichever plan you're evaluating. The difference between two IRMAA brackets can be $60 to $300 per month on top of your premium, and that changes the math entirely. One more thing that trips people up: the out-of-network penalty in Medicare Advantage plans. Some plans advertise low premiums and then charge you 40% of the allowed amount for seeing anyone outside their network. If you travel frequently or have family doctors in adjacent counties, this isn't a hypothetical. Add a column for "out-of-network cost multiplier" and calculate what your typical annual specialist costs would be under that multiplier. You'll immediately see which cheap-looking plans are actually expensive once you factor in your real geography.
Get the Full Details
Common Pitfalls That Break the Comparison
The worksheet only works if your inputs are accurate. The most common error is pulling premium and deductible numbers from the plan's marketing materials rather than the official Evidence of Coverage document. Brochures sometimes list promotional rates that only apply for the first six months or that require you to enroll by a certain date. The EOC is the legal document. It's longer and drier, but it's what actually governs your coverage. Cross-reference the plan's summary of benefits against the full EOC before you commit to any numbers in your spreadsheet. Another issue is that the CMS Plan Finder tool doesn't always reflect a plan's current network. A hospital system can leave a plan's network at any time during the year. When that happens, the plan must notify you, but the notification may arrive after you've already scheduled a procedure. My workaround was to call the plan's provider services line directly and ask for written confirmation that each of my doctors is still in-network as of the current date. Then I entered that confirmation into the worksheet with a date stamp. If the plan can't confirm it in writing, that's a red flag worth noting regardless of the premium. The worksheet also doesn't account for plan quality ratings well. A plan with a 4-star rating might have better care coordination but worse drug coverage. A 3-star plan might have a broader formulary. Quality ratings are based on outcomes like hospital readmission rates and patient satisfaction surveys, not on whether your specific medication is affordable under that plan. Use the star rating as a filter, not as a deciding factor. I keep my threshold at 3 stars minimum because anything below that tends to indicate systemic problems, but I don't let a 5-star rating override a plan that's clearly cheaper for my specific situation.
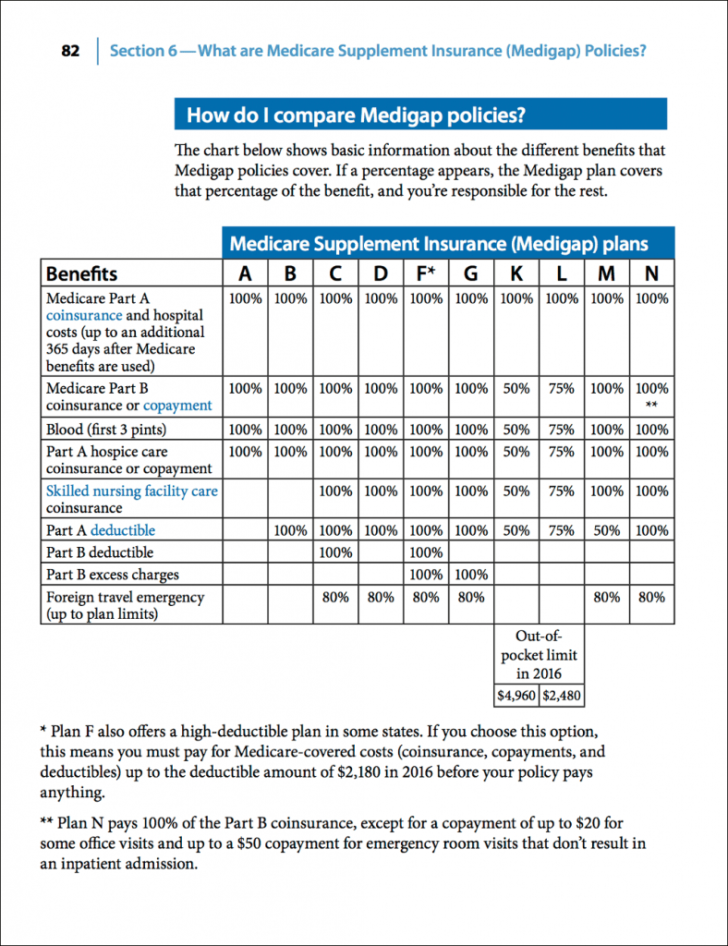
If you're between Medicare Advantage and Original Medicare with a standalone Part D plan, run both configurations through the worksheet separately. The total cost of Original Medicare (Part B premium plus Part B deductible plus Part D premium plus Part D out-of-pocket) is not the same as a Medicare Advantage plan with integrated medical and drug coverage. Sometimes Original Medicare plus a supplemental Medigap policy beats both options. Sometimes it doesn't. The numbers tell you which one, not the other way around. The worksheet itself is static. It captures your estimate for one year. Medicare changes its rules every year, plan costs shift, and your personal health situation may change too. Rebuild the comparison each October during the Annual Enrollment Period. Don't carry over last year's numbers. A plan that was cheapest in 2024 could be the most expensive in 2025 simply because its premium increased by $40 a month or it moved your medication to a higher tier. The process takes about 20 minutes if you have your information organized, and it's the single highest-ROI task you'll do between January and December.