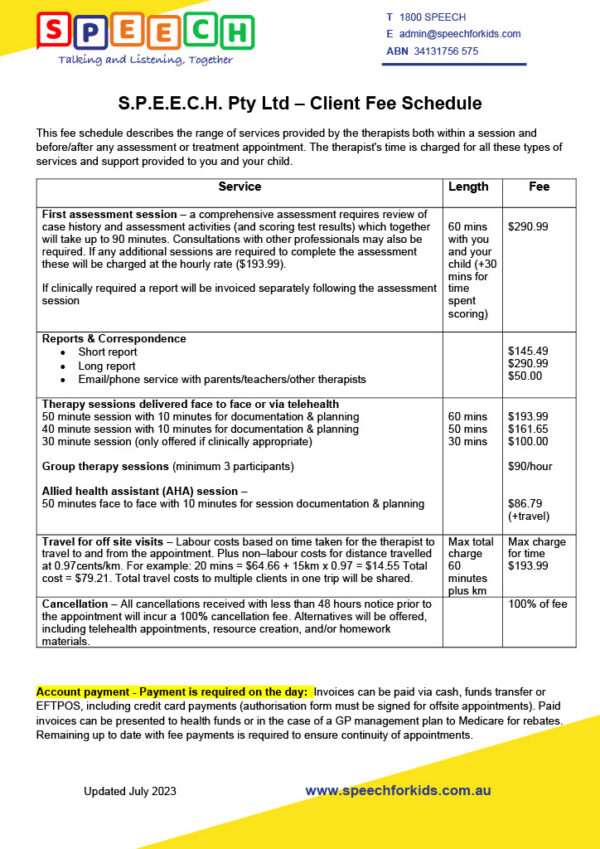
Understanding the Medicare Speech Therapy Fee Schedule
The Medicare Speech Therapy Fee Schedule is what determines how much a speech-language pathologist gets paid when treating a beneficiary covered by Original Medicare. It is part of the broader Physician Fee Schedule, calculated using a national converted value that gets multiplied by locality-specific conversion factors. These factors change every year, so whatever worked in 2024 will not necessarily carry over. Medicare pays for speech therapy under Part B, which means it follows the same outpatient fee schedule structure as doctor visits and diagnostic tests. Each CPT code has a relative value unit attached to it. That RVU gets adjusted by the work component, practice expense component, and malpractice insurance component. Then you apply your geographic practice cost index based on where the service is rendered, and multiply the whole thing by the annual conversion factor. The current conversion factor is roughly $33.01 for 2025, but that number shifts each January. I have watched people miss revenue simply because they did not update their fee calculators after the October announcement. A lot of clinics still pull rates from the beginning-of-year tables and forget they are off by the adjustment amount.
For speech therapy specifically, the common CPT codes are 92507 for therapeutic activities, 92520 for speech language therapy evaluations and treatment, 92521 for auditory processing therapy, and 92610 through 92618 for voice, fluency, and swallowing assessments and treatments. Each has its own RVU breakdown. 92520 is the bread-and-butter code most clinics bill repeatedly, and it carries an RVU that tends to get undervalued relative to the actual time spent with patients who need extensive oral motor and cognitive-linguistic work.
The Threshold Problem Nobody Warns You About
Here is the thing that catches most new clinics off guard. Medicare does not pay for speech therapy the way it pays for most other outpatient services. There is a coverage threshold, not a coinsurance threshold in the traditional sense, and it works differently than you might expect. The Medicare Coverage of Services section of the Common Insurance Modifications (CIM) guide sets a dollar threshold that is updated annually. For 2025, the combined threshold for physical therapy and speech-language pathology services is $2,490. That amount also covers occupational therapy if you are billing all three under the same provider. What happens when you cross it is not simple coinsurance. Once the accumulated billed charges exceed the threshold, Medicare applies a 5% reduction to payment. This is the Medicare Payment Limitation, and it applies to each claim after the threshold is met for that calendar year. It is not an automatic denial. It is a payment cut. Many clinic staff think claims get rejected at that point. They do not. The claim still processes. The remittance just reflects the reduced allowable amount. This confused an entire billing team at a clinic I consulted for back in 2022, and we wasted three weeks chasing denials that were not actually denials. The remittances said 85% payment, and no one had explained why. The workaround is straightforward once you know to expect it. Track cumulative billed charges per beneficiary against the current year threshold in your practice management system. Set an alert at 90% of the threshold so your front desk can flag it before it becomes a surprise. The threshold amount changes every year, so do not set it and forget it. I keep a running spreadsheet of the threshold amounts going back to 2018, and it takes about ten minutes to update each October when CMS publishes the new figure.
Get the Full Details
Common Pitfalls That Drain Revenue
There are a few persistent issues that cause consistent revenue leakage. The first one is modifier confusion. The GA modifier indicates that a waiver of liability statement has been obtained. GZ means the service is likely to be denied as not medically necessary. Using GA when you should be using GZ, or vice versa, will create audit flags and delayed payments. I have seen legitimate claims held for thirty days because the wrong modifier was attached to a therapy service, and the payer questioned whether the patient had actually consented to financial responsibility. The second issue is timing of services versus timing of billing. Medicare expects therapy sessions to be documented on the same day they occur. If a therapist sees a patient on Tuesday but the documentation is completed and billed on Thursday, and there is no contemporaneous note explaining the delay, that can become a compliance issue during an audit. Not a denial reason by itself, but something auditors use to dig deeper into other claims. The third issue is the therapy cap exceptions process. If a patient needs continued therapy beyond the threshold and you want to pursue an exception, you need to document medical necessity with clear functional goals, not just a blanket statement that more sessions are needed. I had a case where a patient with a supraglottic swallowing technique protocol required extensive therapy post-laryngectomy, and the exception got approved quickly because the plan of care included specific measurable outcomes with dates. The exception request that got denied from the same clinic two weeks later was just two paragraphs of generic language. The difference mattered.
Where to Find the Current Rate Tables
The actual fee schedule tables are published by CMS each year in the Federal Register and on their website. You want the outpatient prospector fee schedule spreadsheet, which breaks down each CPT code by its RVU components. The Medicare Administrative Contractor for your region may also publish locality-specific guidance, and those documents sometimes include notes about billing patterns or audit focus areas that the national tables do not cover. I check my MAC's provider updates monthly. Most of the content is noise, but the occasional memo about a change in modifier usage or a new code clarification is worth reading. The exact Medicare Speech Therapy Fee Schedule data lives in the CMS payment tables, and those tables are updated annually around October for the following calendar year. The raw data is available directly from the CMS website in spreadsheet format. Many practices buy software that imports these tables automatically and keeps them current. If you bill a high volume of therapy services under Medicare, the subscription cost pays for itself quickly. If you only see a handful of Medicare patients a week, updating the tables manually each year is manageable and basically free once you know where to look.
What the Fee Schedule Does Not Cover
A few important limitations. Original Medicare does not cover speech therapy if it is provided in a skilled nursing facility during an inpatient stay. That falls under Part A and uses the PPS rate structure instead. Medicare also does not cover therapy services that are primarily for maintenance rather than rehabilitation. The line between maintenance and rehabilitation can be thin, and it is a common source of disputes. If a patient has plateaued and the goals are about maintaining current function without improvement, Medicare may not cover additional sessions regardless of how the CPT code is structured. Medicare Advantage plans are a separate category entirely. They are required to cover at least what Original Medicare covers, but they set their own fee schedules and reimbursement rates. A Medicare Advantage plan may pay more or less than the standard fee schedule for the same service. If your clinic accepts Medicare Advantage, you need a separate contracting process and a separate understanding of what each plan pays. The Medicare Speech Therapy Fee Schedule applies only to Original Medicare, and confusing the two has cost practices significant money when they assumed MA plan rates matched the federal tables. The annual threshold amount is cumulative across all PT and SLP services billed under the same National Provider Identifier. If your clinic has multiple SLPs with different NPIs, each NPI tracks its own threshold independently. This is something that gets overlooked when a new clinician joins a practice and the old threshold balance appears to reset. It does not reset. It resets per NPI. I learned this the hard way when a new hire's patients triggered a threshold alert at the same time as an existing patient's accumulated charges, and we realized the system was tracking two separate thresholds rather than one combined total for the clinic.
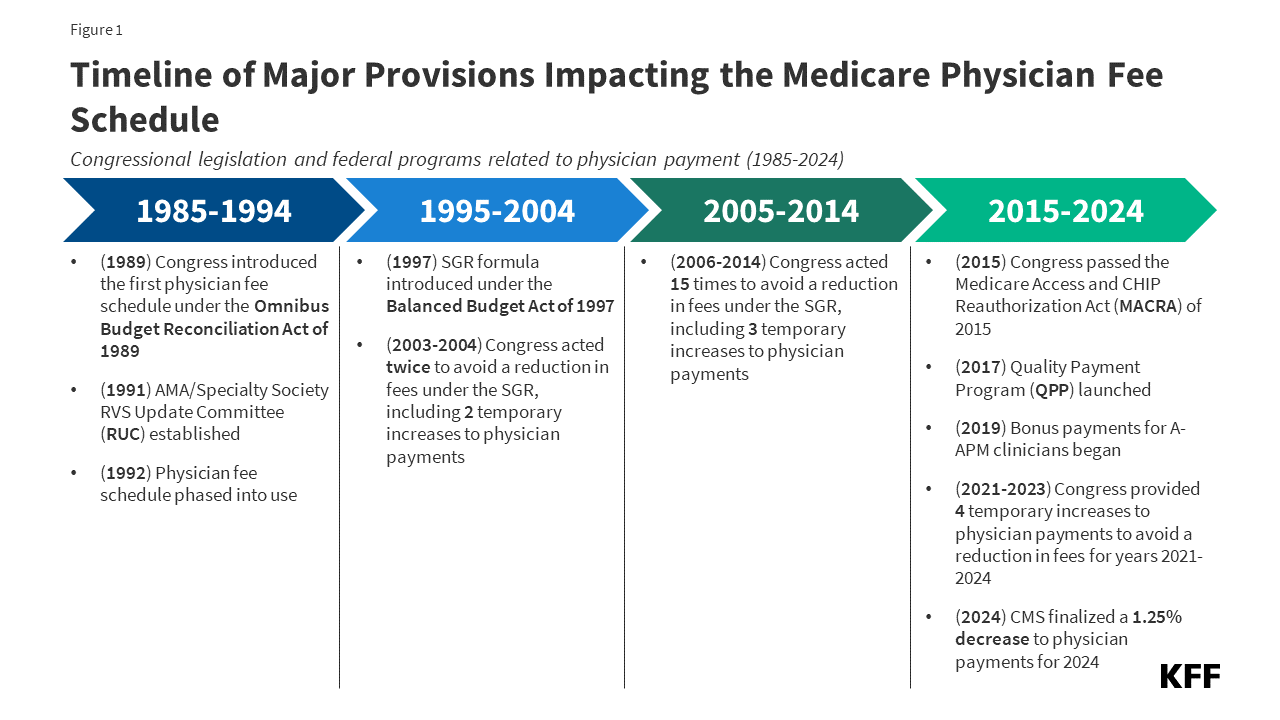
There is no special fee schedule just for speech pathology within Medicare. Speech therapy rates come from the same outpatient physician fee schedule as everything else. The differentiation is purely in the CPT codes themselves and their associated RVUs. If you need rates that are specific to speech therapy procedures, you extract them from the general fee schedule table by filtering for the relevant CPT range. That is the entire structure. It is not complicated in design. It is tedious to maintain because the numbers change annually and the interaction between thresholds, modifiers, and locality adjustments creates enough variables that manual tracking is error-prone. CMS publishes the fee schedule data files around mid-October each year. The effective date is January 1st of the following year. If you are waiting until the new year to update your tables, you have already lost a month of accurate billing. The file format is a plain spreadsheet with columns for CPT code, descriptor, work RVU, practice expense RVU, malpractice RVU, global days indicator, and payment indicator. The locality adjustment factors are in a separate lookup table by ZIP code. You need both to calculate a precise reimbursement amount for any given claim. I use a simple spreadsheet that pulls from both sources and flags any CPT code that appears on the Medicare exclusion list for therapy services, which catches the occasional coding mistake before it becomes a claim rejection.