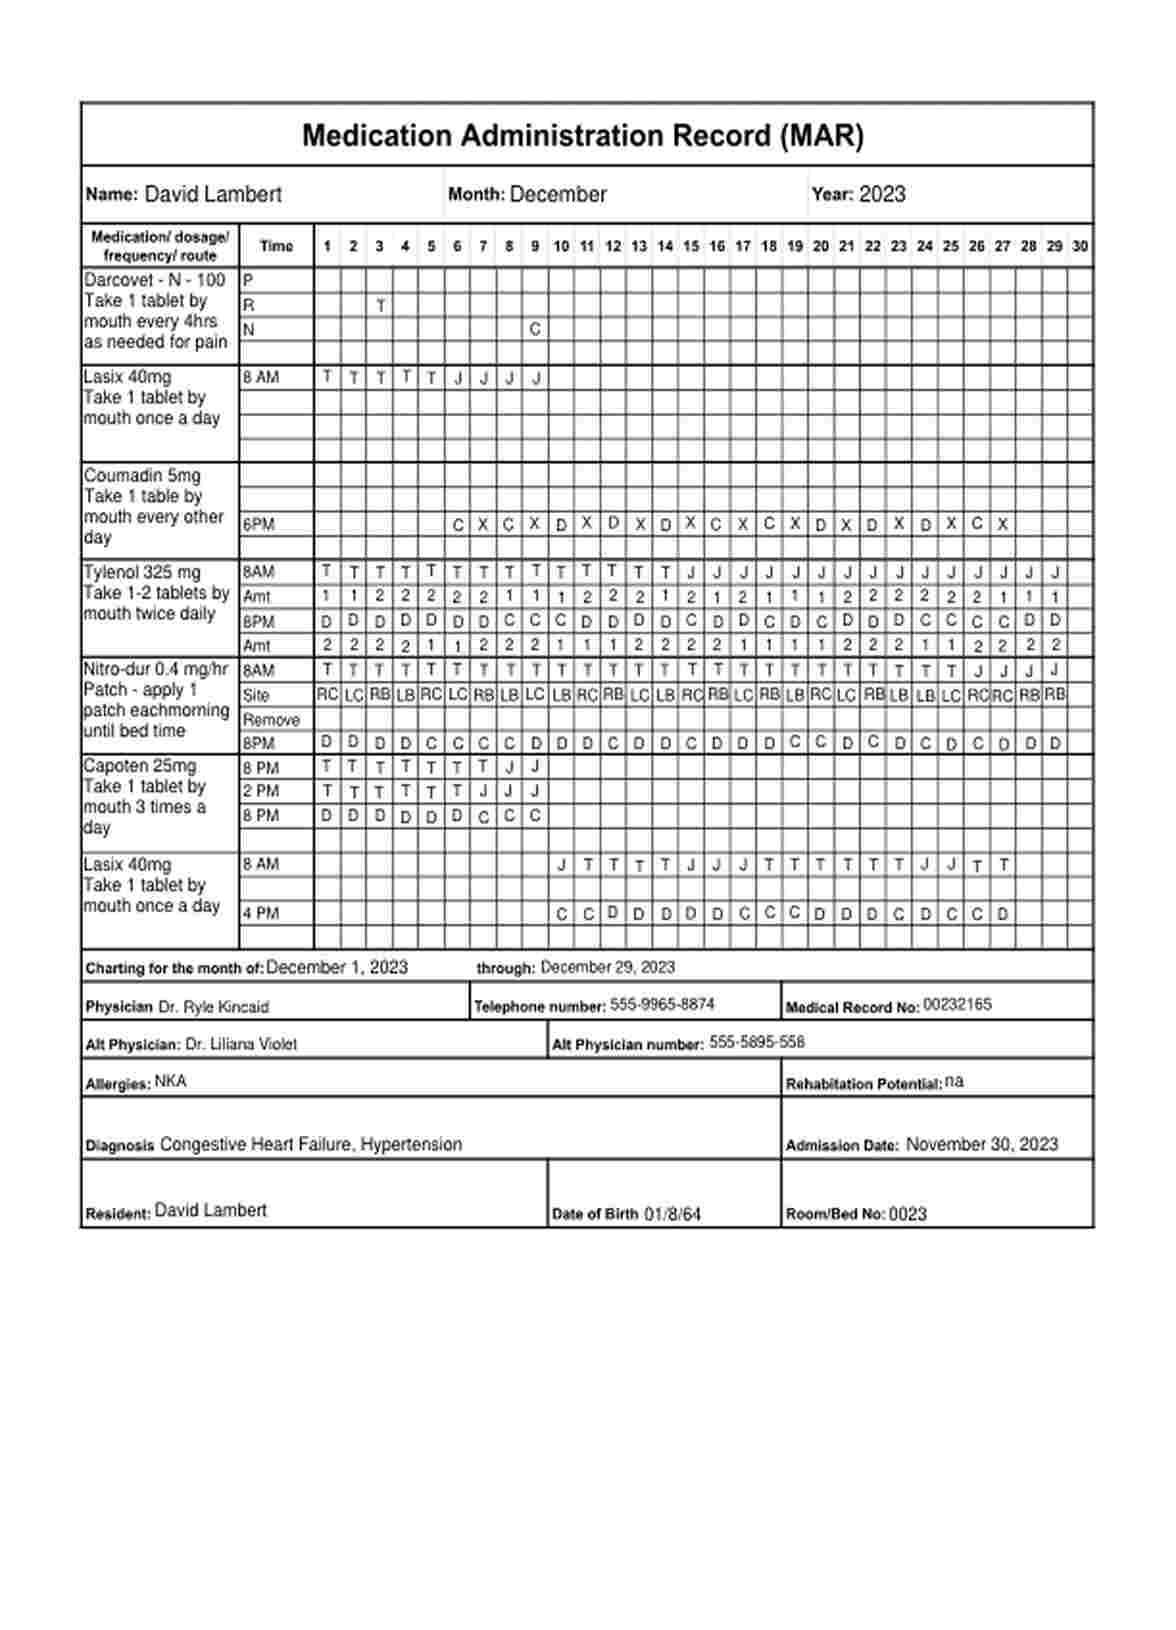
Getting Your MAR Documentation Right Without Losing Your Mind
Medication Administration Record Training is one of those things that sounds straightforward until you actually have to do it during a busy night shift when three residents need their beta-blockers and two of them just woke up confused. I spent about six years working med passes in a long-term care facility before moving into compliance auditing, and the number of documentation errors I've seen would be hilarious if they weren't so dangerous. The core concept is simple: every dose you administer needs a timestamp, your initials, the route, and any relevant observations. That's the bare minimum. The reality of doing this while also managing a resident who suddenly asks for a glass of water, another who needs assistance to the bathroom, and a phone call from a family member demanding updates is what turns MARs into a source of legitimate stress.Why Medication Administration Record Training Matters More Than Most People Realize
The MAR isn't just paperwork. It's the single most important legal document in a healthcare setting when something goes wrong. I audited a facility once where a resident died from an insulin overdose, and the entire investigation hinged on whether the nurse who administered it documented it correctly. She had written the time, her initials, and the dose, but she hadn't logged the blood glucose reading that should have been taken before administration. That single missing data point made it impossible to determine whether protocol was followed, and the facility faced severe regulatory action. When you're doing Medication Administration Record Training, you need to understand that you're building a chain of evidence. Every entry connects to the prescription, the pharmacy label, and the provider's orders. If any link in that chain is broken or unclear, it creates doubt about whether the right medication went to the right person at the right time through the right route in the right dose.The five rights — right patient, right medication, right dose, right route, right time — are drilled into every training program, but nobody tells you that the fifth right, documentation, is just as critical. A perfectly administered dose that isn't documented properly is, from a legal and regulatory standpoint, the same as a dose that wasn't given at all. That's not dramatic phrasing. That's how the law treats it.
The Practical Workflow Nobody Talks About in Training
Here's how it actually works in a busy unit. You pull the MAR binder or open the electronic system. You check the schedule for this specific time block — usually 0900 for morning meds. You scan each medication against the resident's wristband using the barcode system. You confirm the resident's identity by having them state their full name and date of birth. You administer the medication. You immediately document it. The problem is that immediate documentation part. Most systems are designed around the ideal scenario where you have ten minutes between residents to sit down and click through the entries. In practice, you might have three minutes if you're fast, or you might get interrupted by a call light the moment you finish scanning. I developed a workaround that cut my documentation errors from roughly once per shift to almost zero. I kept a small notepad at the med cart and wrote down the timestamps and any observations as I went, then transcribed them into the system during the brief window between medication rounds. It sounds like extra work, and technically it is, but the alternative is trying to remember at the end of the pass whether you gave losartan 50mg at 0845 or 0900, which is a nightmare you don't want to deal with during an audit.The notepad method doesn't work in every facility because some electronic MAR systems lock out late entries or flag them as delinquent. If your system has that feature, you'll need to adapt. Some people use voice memo apps on their phones instead, recording the details immediately after each administration and reviewing them before final transcription. It's less precise than a notepad but faster to use with one hand while holding a pill cup in the other.
Common Pitfalls That Trip Up Even Experienced Staff
The first thing that goes wrong is the "documenting at the bedside versus documenting after the fact" debate. Some managers insist you must document immediately at the resident's side. Others accept documentation within a reasonable timeframe after administration. The regulatory standard is actually quite vague on this, which creates confusion and inconsistency across facilities. What I've found is that documenting at the bedside reduces the chance of forgetting an administration entirely, but it also creates problems when residents are watching you write things down. Some interpret the delay as you being slow or hesitant, which can create anxiety or resistance. Others ask questions mid-donation that you'd rather answer after you've finished the charting. Another common error is the late-entry notation. When you realize you missed documenting a dose after the fact, the correct approach is to make a new entry with the actual time of administration noted clearly and a late-entry annotation. What people often do instead is backdate the entry or simply add it to the existing line, which creates a falsified record. I've seen this happen repeatedly, and it's one of the fastest ways to get flagged during a survey.PRN documentation is where most MAR errors cluster. When a resident receives a medication "as needed," the record must include the indication for administration, not just the dose and time. I audited a facility where a resident had received lorazepam four times in one week for "agitation," but none of the entries documented what the agitation looked like or what non-pharmacological interventions had been tried first. That's a serious documentation gap that suggests the PRN was being used as a convenience rather than a targeted intervention.
Get the Full Details

Advanced Nuances in MAR Compliance
One thing that isn't covered adequately in most training programs is the handling of medication refusals. When a resident declines a medication, the MAR must reflect that refusal with the resident's exact words if possible, the time of refusal, and the notification of the prescribing provider. Simply checking "refused" without additional documentation creates a legal vulnerability. I encountered a specific edge case that took me about three weeks to resolve properly. A resident with advanced dementia refused all oral medications for two consecutive days. The nursing staff documented the refusal each day but didn't notify the provider until the third day because they assumed the resident would eventually accept them. The resident was later diagnosed with a severe urinary tract infection that had gone untreated because the prophylactic antibiotics had been refused and never escalated. The workaround I implemented was a mandatory provider notification trigger set at 24 hours for any refused medication that was flagged as essential. This meant that if a resident skipped a blood pressure medication or an antibiotic for more than one day, the system automatically prompted the charge nurse to contact the provider. It eliminated the assumption-based decision-making that caused the original problem.Electronics and the New Reality of Medication Administration Record Training
Most facilities have moved to electronic MAR systems, and these introduce their own set of challenges. Automated dispensing cabinets like Pyxus or Omnicell integrate with the MAR, but the handshake between systems isn't always seamless. I've seen cases where a medication was scanned and dispensed from the cabinet but the MAR didn't update because the network dropped during the transaction. The nurse had no way of knowing whether the dose was recorded until hours later during a routine audit. Electronic systems also tend to make late entries more visible. Some platforms flag every entry made more than 15 minutes after the scheduled time, which creates noise in the data and makes it harder to distinguish between genuine documentation errors and systemic issues like staffing shortages. When every entry gets a flag, no flag means anything.The barcode verification system itself is another area where training is often insufficient. Staff are taught to scan the resident's wristband and the medication barcode, but they're rarely trained on what to do when the scan fails. A failed scan could mean an expired barcode label, a damaged medication package, a system error, or a legitimate discrepancy between theMAR and the physical medication. Each of these requires a different response, and most facilities don't have clear protocols for the less common scenarios.
What Proper Training Should Actually Cover
A thorough Medication Administration Record Training program should go beyond the basic five rights and cover the specific documentation requirements for each type of medication administration. Oral medications require the resident's identity confirmation and the time of administration. Injectable medications require the site of injection, the needle gauge, and any reaction notes. Topical medications need the body area treated and the amount applied. The training should also address the specific requirements for controlled substances, which often need a second nurse witness and co-signature. I've seen facilities where the second nurse would witness the preparation but not the actual administration, creating a gap in the chain of custody that surveyors flag immediately. Incident reporting is another area that connects directly to MAR documentation. If a medication error occurs — wrong dose, wrong time, wrong resident — the MAR entry must be corrected according to facility policy, and an incident report must be filed. The correction on the MAR should never obscure the original entry. In paper systems this means drawing a single line through the error and initialing it. In electronic systems this means using the formal correction process that maintains the audit trail.I once reviewed a paper MAR where someone had used correction fluid on a medication entry. That's an automatic red flag during any survey. Correction fluid suggests an attempt to hide an error rather than correct it transparently. The proper procedure is always to draw a single line through the mistake, write the correct information nearby, and initial it with the date and time. It looks ugly, but it's defensible. Correction fluid is not.
Limitations and When the MAR System Itself Fails
No documentation system is perfect, and the MAR is no exception. The most significant limitation is the reliance on human memory and attention during high-stress situations. Even the most well-trained nurse will miss a documentation step when managing a resident in distress, coordinating with multiple family members, and dealing with staffing shortages simultaneously. Electronic systems introduce their own failure modes. Network outages, software bugs, hardware malfunctions, and integration errors between dispensing cabinets and MAR systems can all create documentation gaps that no amount of training can prevent. I worked at a facility during a two-day network outage where we had to revert to paper MARs, and the resulting documentation was chaotic, incomplete, and stressful for everyone involved. Another limitation is that the MAR captures what was documented, not necessarily what happened. A perfectly maintained MAR can still conceal errors if the person documenting chose to record inaccurate information deliberately. This is rare but not impossible, and it's one reason why independent audits and spot checks are essential components of any medication safety program.If your facility relies solely on MAR documentation as the primary quality assurance tool, you're missing a critical layer. The MAR tells you what was charted. It doesn't tell you whether the charting reflects reality. Direct observation, medication reconciliation audits, and incident trend analysis are necessary complements to the MAR system.

A Realistic Approach to Improving Your MAR Process
Start by reviewing your current MAR error rate. Most facilities track this metric but few act on it systematically. Pull the last six months of documentation discrepancies from your incident reporting system and categorize them by type — late entries, missing signatures, incomplete PRN justifications, unauthorized corrections, and so on. You'll likely find that 80 percent of your problems cluster around three or four specific error types. Target your training resources at those specific issues rather than trying to improve everything at once. If late entries are your biggest problem, investigate whether the root cause is staffing levels, system usability, or lack of emphasis on timely documentation. The solution will be different depending on the answer. If your MAR system generates excessive late-entry flags, consider whether your documentation windows are realistically aligned with your actual workflow. Some facilities schedule medication passes at rigid intervals that don't account for resident variability — a resident who sleeps in, a resident who needs extensive assistance with bathroom use before taking pills, a resident who has unexpected family visits during med time. Building flexibility into your scheduling can reduce the number of legitimate late entries without compromising accuracy.The single most impactful change I've seen a facility make was implementing a daily MAR review by the charge nurse before the end of each shift. This caught documentation errors while they were still fresh and easily correctable, rather than letting them accumulate until the next shift's review or an external audit. It added approximately 20 minutes to the charge nurse's day, which is a small cost for the improvement in documentation quality.