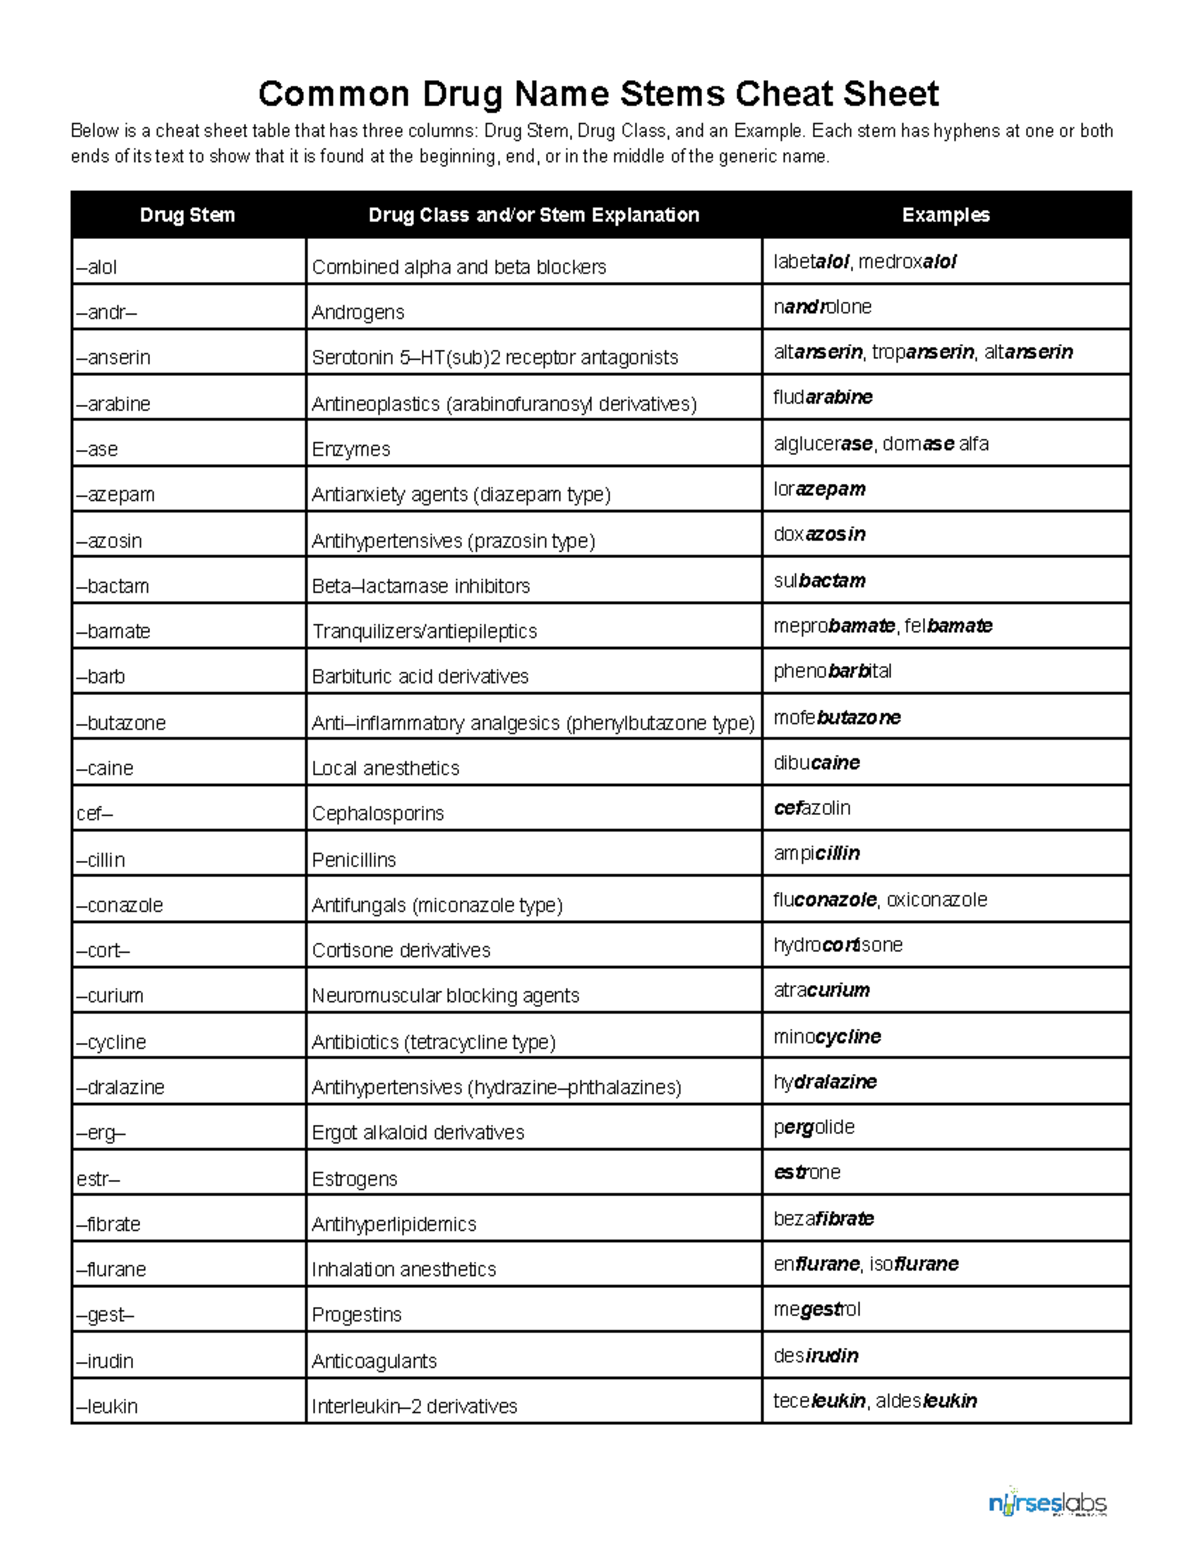
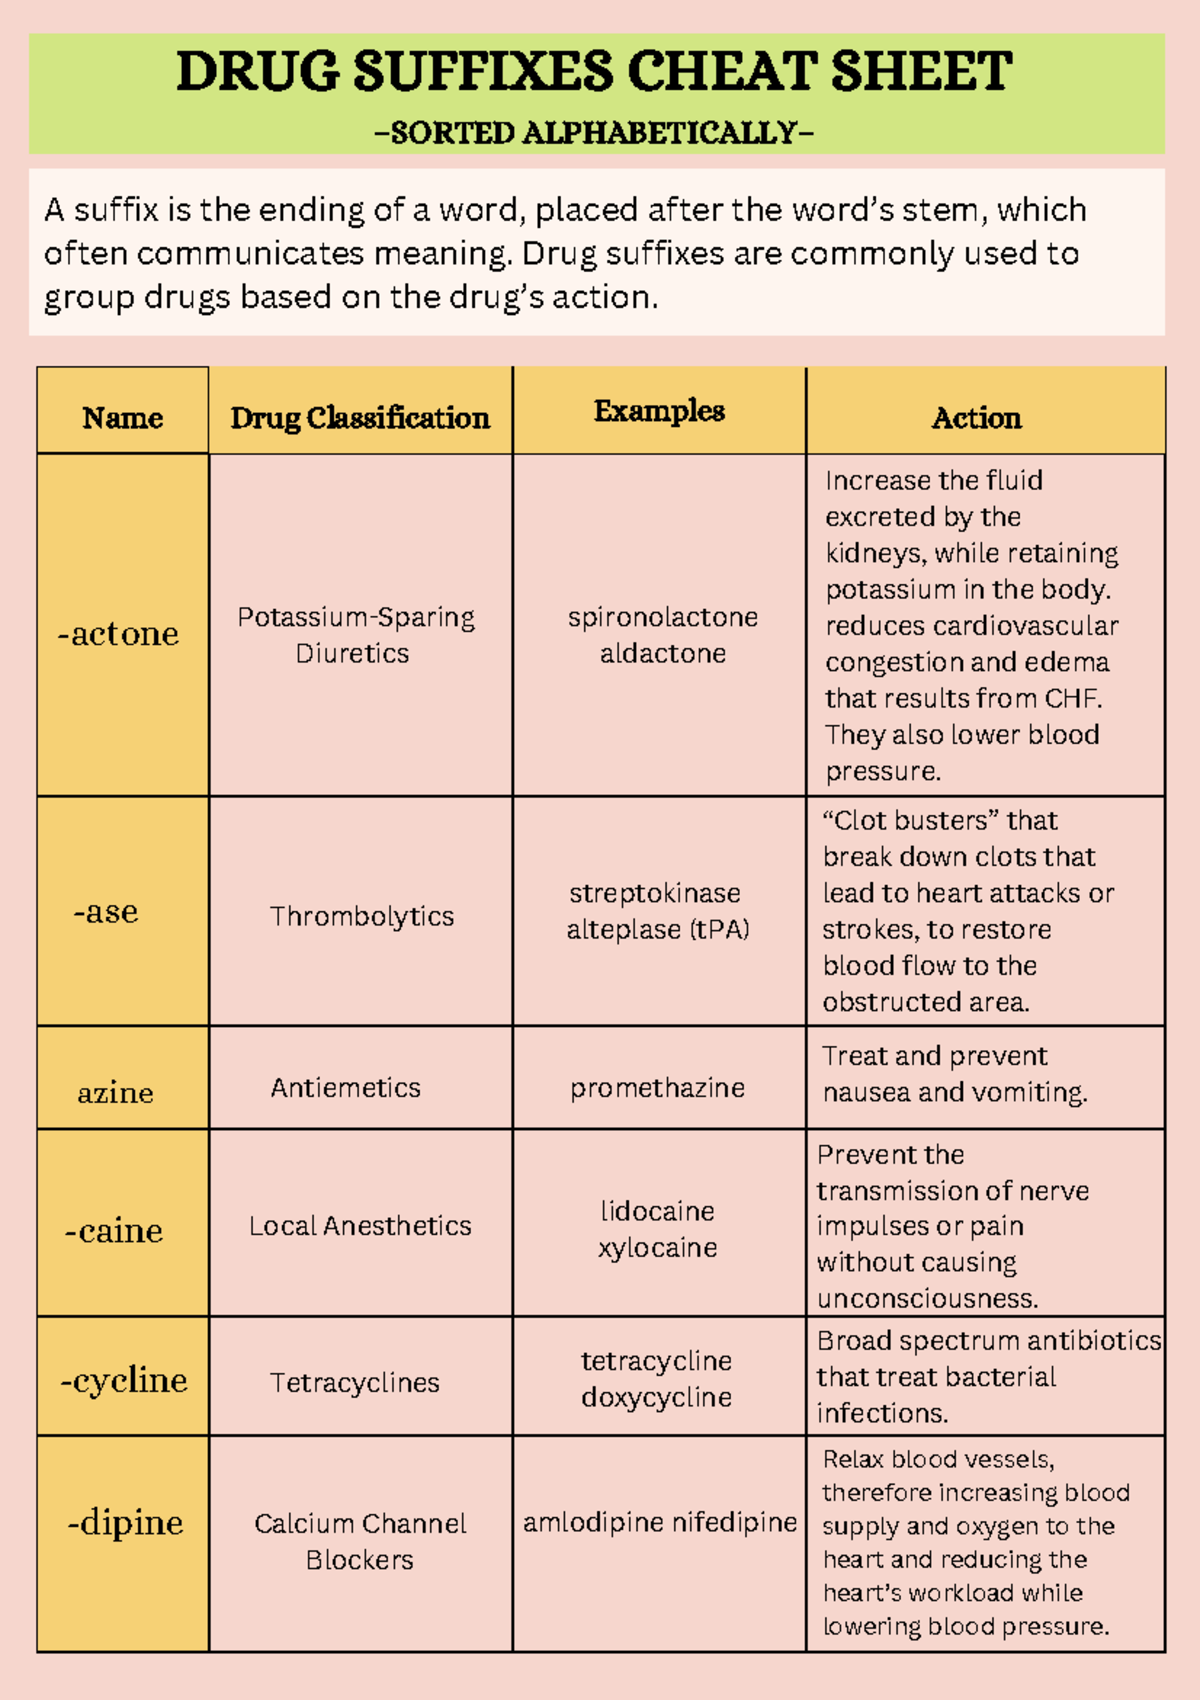
How to Actually Use a Medication Endings Cheat Sheet Without Wasting Your Time
Most people grab a medication endings cheat sheet and memorize it like a vocabulary list. That does not work well in practice. What actually works is understanding why the endings exist in the first place, then learning to use them as shortcuts during patient counseling and exam prep. The endings are not arbitrary. Pharma companies chose them deliberately for branding and regulatory reasons, and that gives them real structure underneath.Medication Endings Cheat Sheet: The Real List
-pril — ACE inhibitors (lisinopril, enalapril, ramipril). They block angiotensin-converting enzyme. Dry cough is the telltale side effect that shows up on rounds. -sartan — ARBs (losartan, valsartan, olmesartan). Same organ system as -pril but different mechanism. Used when the cough from ACE inhibitors is intolerable. Easy to confuse the two classes if you only memorize endings without knowing the pharmacology behind them. -statin — HMG-CoA reductase inhibitors (atorvastatin, rosuvastatin, simvastatin). Lipid-lowering agents. The ending is straightforward but the dosing frequency and drug interactions vary wildly between agents. Atorvastatin and rosuvastatin are the ones you will see most often in practice.
-azole — Antifungals (fluconazole, itraconazole, voriconazole) and SSRIs (fluoxetine, sertraline — wait, those are not -azole, that is a common trap). The -azole ending here exclusively signals antifungal agents. Do not mix this up with the -zepam group below. -pam — Benzodiazepines (diazepam, alprazolam, clonazepam). Short-acting ones like alprazolam have higher abuse potential. Long-acting ones like diazepam have active metabolites that accumulate in elderly patients. This matters clinically more than the ending itself. -zolam — Also benzodiazepines but with a z (zolpidem is different — that is a non-benzodiazepine sleep aid despite the similar ending). The zol- prefix drugs for sleep (zolpidem, zaleplon, eszopiclone) are Z-drugs, not benzodiazepines. This distinction is something I see residents get wrong constantly.
-cillin — Penicillins (amoxicillin, penicillin V, nafcillin). The aminopenicillins like amoxicillin cover gram-negatives better than natural penicillins. Again, the ending tells you the class but the sub-classification matters for prescribing. -cefin / -cef — Cephalosporins (cephalexin, ceftriaxone, cefdinir). Generation matters enormously. First-gen cefalexin covers gram-positives well. Third-gen ceftriaxone has broader gram-negative coverage including Pseudomonas in some cases. A cheat sheet will list the ending but you still need to know which generation you are dealing with. -floxacin — Fluoroquinolones (ciprofloxacin, levofloxacin, moxifloxacin). Black box warnings for tendon rupture and QT prolongation. These are not first-line for anything anymore except specific indications like anthrax or complicated UTIs. You will burn bridges if you prescribe ciprofloxacin for uncomplicated sinusitis.
Get the Full Details

-mycin — Macrolides (azithromycin, clarithromycin, erythromycin) and aminoglycosides (gentamicin, tobramycin). Same ending, completely different drug classes. Macrolides are oral outpatient antibiotics. Aminoglycosides are IV only with nephrotoxicity and ototoxicity concerns. This is one of the most dangerous overlaps in the cheat sheet. -vir — Antivirals (acyclovir, valacyclovir, oseltamivir, ganciclovir). Not all antivirals end in -vir but the ones that do almost always are. Oseltamivir is the outlier people forget because it is Tamiflu and nobody calls it by its generic name. -taxel — Taxane chemotherapy (paclitaxel, docetaxel). Pre-medication with dexamethasone is standard to prevent hypersensitivity reactions. If you miss the pre-med, the reaction can be severe. The ending identifies the class but the protocol around it is what keeps patients safe.
I learned this the hard way early in my career. I was reviewing a discharge list and saw a patient on a -mycin drug for a skin infection. I assumed macrolide because that is what I expected for outpatient coverage. It was actually an aminoglycoside ordered for a resistant organism, and the dose was adjusted for renal function. If I had just Googled the drug without checking the class first, I would have missed the renal dosing entirely. That is why the cheat sheet is a starting point, not an endpoint.How to Study This Efficiently
Do not read the list passively. Write out the endings yourself with at least two example drugs for each. Then test yourself by looking at a random medication name and working backward to the class. This reverse-engineering approach is faster than forward memorization because it mimics how you will actually encounter drugs in clinical practice. Flashcards work if you include the side effect profile and the key clinical pearl on the back. A card that only says "-pril = ACE inhibitor" is not useful. A card that says "-pril = ACE inhibitor, dry cough, hyperkalemia, contraindicated in pregnancy" is. The extra detail takes three seconds more to write and saves you ten minutes of lookup later.Where the Cheat Sheet Breaks Down
The biggest limitation is that not all drugs in a class share the same ending. Levothyroxine is a thyroid hormone replacement but it does not follow any naming convention you can guess. Metformin is a biguanide and again, no pattern. Proton pump inhibitors like omeprazole and pantoprazole share the -prazole ending, but there is no separate -prazole class beyond PPIs — they are all PPIs. Some endings apply to only one therapeutic class while others overlap across multiple classes, which is exactly what happens with -mycin. Another issue is brand names. A patient will tell you they take "Lipitor" not "atorvastatin." The cheat sheet does not help with brand-to-generic translation. Make sure you learn the top 50 brand names alongside the generic suffixes. That is roughly 20 percent of prescriptions written in most outpatient settings.Medication Endings Cheat Sheet Download Reference
I do not host a downloadable file here but the full table I use is simple enough to recreate in any spreadsheet program in about ten minutes. Create columns for: Ending, Drug Class, Example Drugs, Key Side Effects, and Clinical Pearls. Fill it in as you study. Your own version will stick better than any PDF you download because the act of building it is part of the memorization process. If you want a printable version, search for the pharmacy board review materials from the major review courses. They all include a suffix chart. The content is identical across providers because the pharmacology does not change. Pick whichever format you can read without straining your eyes at 11 PM.