Working Through a Medication Management Assessment
Most people think this is just a form you fill out and hand to a doctor. It's not. I've sat at kitchen tables with people who have been on four or five different meds for years and watched them miss dosages daily without any idea they were doing it. The gap between what the prescription label says and what actually happens is usually where everything falls apart. A proper assessment needs to cover several concrete areas. Cognitive ability to understand timing and dosage. Physical capacity to open bottles, pour pills, and manage syringes or inhalers. Vision and dexterity limits that make reading labels impossible. Executive function — the ability to plan, sequence, and initiate the task of medication management without prompts. Environmental factors like lighting, storage setup, and whether the person lives alone or with someone who might be enabling avoidance behaviors. And finally, the actual routine the person has built, which is almost never what the prescription instructions say.
Medication Management Assessment Occupational Therapy
The framework used in practice is typically structured around the Occupational Therapy Practice Framework. You assess the person's occupational profile first. What matters to them. What their goals are. Where they're actually failing. Then you move into performance analysis. You watch them do the task. Not ask about it. Watch it. That distinction changes everything because people will tell you they take their meds correctly and then demonstrate that they put pills in a weekly box, forget to move the current day tab, and don't realize they've been doubling up for three days. I use a modified version of the Myers-Perry Inventory for ADLs alongside direct observation. The inventory gives you a baseline score, but the observation tells you where the real breakdowns are. I've found that combining both gives a much clearer picture than either alone. A client might score fine on the paper tool and still be unable to manage their medications safely at home. The process itself takes roughly 45 to 90 minutes depending on complexity. The first session is usually the assessment. The second session involves implementing interventions and re-checking. If the person has significant cognitive impairment, you'll likely need multiple follow-ups. If it's primarily a physical barrier, one good intervention can resolve it completely.
Here is how I typically structure the hands-on portion. Start with a mock medication setup. Provide several different types of containers — child-resistant caps, blister packs, pill organizers, liquid measuring devices — and ask the person to manage a pretend medication schedule for one week. Watch closely. Note where they hesitate. Note where they make errors. Note whether they catch their own mistakes. The errors that show up here are the same errors showing up in their actual routine at home. Common findings include poor transfer of knowledge from prescription label to actual behavior. People understand the instruction verbally but cannot apply it to the mechanical task of organizing and tracking doses. Also common is over-reliance on caregivers who have quietly taken over the entire process, creating learned helplessness that no assessment will fix until you address it directly. Another issue that comes up frequently is the mismatch between what the pharmacy provides and what the person can actually use. I had a client with severe bilateral hand arthritis and osteoarthritis of the thumbs who received standard child-resistant bottles from the pharmacy. She could not open them without significant pain and occasionally resorted to using pliers, which she then lost. The workaround was straightforward — I wrote a brief letter to the prescriber requesting non-child-resistant containers or a switch to unit-dose packaging through a compounding pharmacy. Within a week, the issue was resolved and her adherence improved noticeably.
Get the Full Details

Interventions That Actually Work
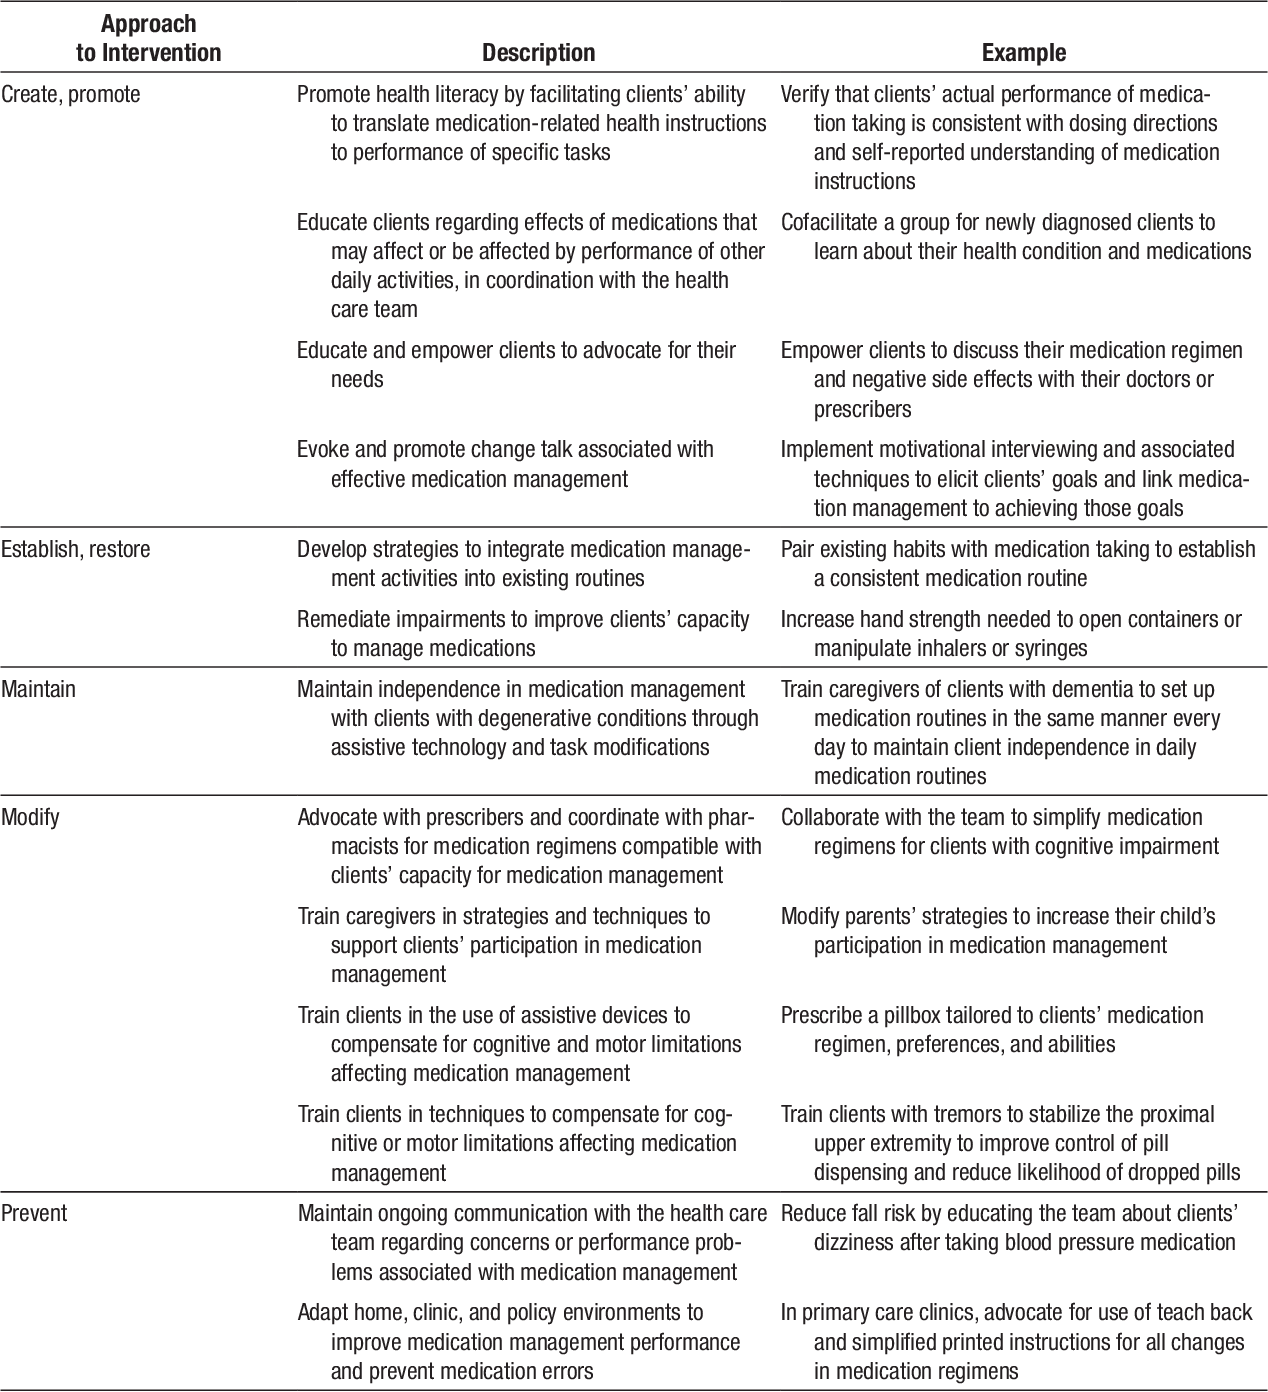
Most recommendations I see online are generic. Adaptive equipment suggestions, reminder apps, pill organizers. Those help when the problem is mild. When the problem is moderate to severe, the interventions need to be more specific and often more systemic. For motor or dexterity limitations, the priority is reducing the physical demand of the task. That means switching to easy-open containers when possible, using a jar opener or adaptive cap tool, and organizing medications by time of day rather than by condition. The latter is a subtle but important distinction. Grouping by condition requires the person to understand which medication treats which problem. Grouping by time only requires them to open the right compartment at the right time. Simpler cognitive load. Fewer errors. For cognitive or executive function issues, the solution is almost always external supports. Smart pill dispensers that lock and only open at the scheduled time. Automated reminders with audible and visual cues. Daily medication charts with checkboxes. The key is matching the support to the specific deficit. If the person forgets they took the medication, a locked dispenser that won't reopen until the next dose is more effective than a checklist they will check anyway regardless of whether they actually took the pill.
Environmental modification is often overlooked. I once assessed a woman who lived in a dark hallway with a medication cabinet on the far end of her kitchen. She had macular degeneration and could barely read the labels. She moved her medications to a box on the counter where she could feel the bottles but not identify them. The fix was moving the entire medication station to the bathroom counter with better lighting, large-print labels, and a visual schedule taped at eye level. Cost: about twelve dollars for the labels and a small LED light. Effectiveness: immediate and sustained.
Pitfalls to Avoid
The biggest mistake I see therapists make is stopping at the identification of the problem without addressing the root cause. Telling someone to "use a pill organizer" when the real issue is that they cannot read the small print or manipulate the small tabs is useless. You have to identify why the organizer fails, not just note that it fails. Another common error is assuming that the person's reported routine is accurate. It never is. I have never had a client say "I take my blood pressure medication every third day" during an interview. They will say "I take it as prescribed" while demonstrating that they take it sporadically. Always verify through observation or caregiver report whenever possible. A third pitfall is underestimating the role of the care environment. If the person lives with a spouse who manages all medications, the assessment should include an interview with that spouse. Sometimes the caregiver is doing an excellent job and the person genuinely has no need to manage their own medications. Sometimes the caregiver has inadvertently created total dependence by taking over the task entirely. Distinguishing between these two scenarios takes a direct conversation with both parties.

For people with advanced dementia or significant cognitive decline, medication management assessment may reveal that independent management is no longer safe or realistic. In those cases, the goal shifts from maintaining independence to ensuring safety through supervised administration. This is a difficult conversation for families. I find it helps to frame it clearly: the question is not whether the person can manage their meds. The question is whether the current system keeps them safe. If it doesn't, the intervention is supervision, not more organizational tools. I also want to be honest about what this assessment does not solve. It will not fix medication non-adherence caused by cost. It will not resolve side effects that the person is quietly enduring because they do not want to burden their doctor. It will not address the delusion or paranoia that leads someone to believe their medications are poison. Those require different interventions — financial counseling, medical review, psychiatric support. The occupational therapy assessment can identify these barriers and refer appropriately, but it is not the solution itself.
Documentation and Communication
The assessment should be documented clearly enough that other providers can understand the findings and the recommendations. Include the specific tasks the person can and cannot perform. Note any adaptive equipment suggested or used. Record the frequency and type of supervision needed. Recommend any environmental modifications. State the expected level of support going forward and what signs would indicate a need to reassess. When communicating with the prescribing physician, focus on functional observations rather than opinions. Instead of writing "the patient is non-compliant," write "the patient was unable to open child-resistant containers without assistance and demonstrated uncertainty about dosing schedule during direct observation." The second statement gives the doctor actionable information. The first gives them a label that leads nowhere. If you are writing this for insurance purposes, be specific about the occupational performance deficit. Reference the activity areas affected — medication self-care, health management, instrumental activities of daily living. State the performance skills that are impaired — motor, process, and communication/social as applicable. This alignment with recognized occupational therapy language makes the documentation stronger and easier for reviewers to evaluate.
Resources
The American Occupational Therapy Association publishes practice guidelines that cover medication management as part of ADL and IADL assessment. These are useful reference points though they tend to be general rather than procedure-specific. For more detailed assessment tools, the Canadian Occupational Performance Measure is widely used in clinical settings and includes medication management as a trackable performance area. For families and caregivers looking for practical support, the nonprofit organization Medication Management Assistance programs exist in many regions. They are not a substitute for a professional assessment but can provide supplemental help with organization, reminders, and basic monitoring. The National Council on Aging also maintains a free resource page with medication safety tools and downloadable organizers. What remains true across every case I have worked on is that the actual behavior around medications is almost always different from the reported behavior. The assessment exists to close that gap. Not by giving people more tools to fail with, but by understanding why the current system is failing and building a replacement that matches the person's actual abilities rather than their intended ones.