
Setting Realistic Medication Goals in OT Practice
Most occupational therapy evaluations for medication management start with a pill organizer and a checklist. That approach misses half the problem. I spent years watching therapists score clients on whether they could sort pills by day, then watch those same clients fail at dosing times because nobody actually observed the full chain of behavior from opening the container to swallowing the tablet. The real work begins when you stop treating medication management as a single skill and start treating it as a sequence of overlapping cognitive and physical tasks.Medication Management Goals Occupational Therapy
When you write goals for this domain, they need to account for executive functioning demands, visual processing limitations, fine motor dexterity issues, and the client's actual daily routine. A goal like "Client will manage medications independently" tells you nothing about what independence looks like for that specific person. Does the client live alone or with a caregiver? Are they on five medications or fifteen? Is there a polypharmacy concern with interactions? I had a client last year, a man in his seventies recovering from a stroke, who could organize his pills flawlessly every Sunday evening. He used a seven-day pillbox and followed a color-coded system. The problem was that he would take the Monday morning dose immediately upon opening the lid, then sit and stare at the rest of the week's compartment for forty-five minutes before realizing he needed to wait. His executive planning was intact enough for the organizational task but impaired enough that the temporal sequencing fell apart under low supervision. We changed the goal from independent management to modified independent management with a visual cueing system, and I had his daughter set alarms on her phone that would text him at his actual dosing times rather than relying on his internal sense of time. The workaround wasn't about improving his cognition. It was about externalizing the timing cue so the cognitive load dropped below his impaired threshold. That distinction matters because it changes how you write the goal and how you measure progress.
The Assessment Phase Most Therapists Skip
Before writing any goal, you need a functional medication interview. This is different from asking a client what medications they take. It's an observation-based assessment where you ask the client to demonstrate their entire medication routine from start to finish while you take notes. You're looking for breakdowns at each step. The steps are: obtaining the medication container, reading the label, opening the container, transferring the medication to the dispensing device or hand, recognizing the correct dose, timing the dose correctly, ingesting the medication, and documenting that the dose was taken. Each step can fail independently. A client with mild aphasia might read the label but misinterpret the dosage instructions because the terminology is confusing. A client with early-stage dementia might take the correct dose but forget they already took it and take another one twenty minutes later. A client with Parkinson's might be able to do everything cognitively but struggle with the fine motor task of opening child-resistant caps. These require completely different interventions.
I've seen too many therapists rely solely on standardized tools like the Modified Barthel Index or the AMPS when evaluating medication management. Those instruments will tell you whether a client can feed themselves or dress independently, but they won't tell you whether the client will accidentally double-dose their blood pressure medication because the bottle labels look identical. For medication-specific assessment, use the Medication Management Inventory or create your own structured observation checklist based on the steps above. Document exactly what the client does at each step, not just whether they succeeded or failed.
Get the Full Details

Writing Goals That Actually Measure Change
SMART goals are table stakes, but the S and M portions are where most OTs cut corners. A specific medication management goal should name the exact behavior, the context, the level of assistance required, and the measurable criterion for success. Here's what that looks like in practice versus what typically gets written. Poor goal: "Client will improve medication management skills." This is useless. It doesn't specify what skill, what improvement, or how you'll know it happened. Better goal: "Client will correctly identify and administer prescribed medications using a weekly pill organizer with minimal verbal cueing across 5 out of 7 days for 2 consecutive weeks." This is specific. It names the tool, the assistance level, and the measurable criterion.
Even better goal includes the baseline. "Client currently requires maximal verbal and physical assistance to open medication containers and select correct doses, taking approximately 45 minutes for a 7-day supply. After 6 weeks of intervention, client will independently prepare a weekly pill organizer and administer doses correctly with intermittent visual cueing on 6 out of 7 days." Now you have a starting point, a timeline, and a clear endpoint. The intervention itself depends entirely on where the breakdown occurred during your assessment. If the problem is cognitive sequencing, you use task analysis and chaining. If the problem is visual labeling confusion, you modify the environment. If the problem is motor access, you recommend adaptive equipment or substitute formulations. The goal writes itself once you know which layer is actually broken.
Common Pitfalls in This Domain
The biggest mistake I see is overestimating what a client can do in a clinic versus at home. A client who successfully sorts pills during a 30-minute session in a quiet office is not necessarily ready for independent management at home. Home environments introduce distractions, poor lighting, conflicting schedules, and emotional stress that don't exist in your clinic. I always try to do at least one home visit or telehealth observation of the actual medication space before finalizing a goal. If that's not possible, I recommend a trial period with a trusted caregiver observing and documenting performance over a full week. Another pitfall is assuming that educational interventions alone solve the problem. Telling a client to "read the label carefully" or "use a pill box" doesn't work if the underlying barrier is vision, cognition, or motor function. I've watched therapists spend three weeks on education-based interventions with a client who couldn't progress because the real issue was uncorrected presbyopia making the tiny print illegible. One referral to an optometrist and a switch to large-print labels solved in a day what three weeks of repetition couldn't touch. There's also the polypharmacy trap. When a client is on more than five medications, the complexity increases exponentially, not linearly. Five medications might mean ten dosing events per day. Add a sixth and you might have twelve, but you also introduce potential interactions, duplicate therapies, and contradictory instructions that no pill organizer can simplify. In these cases, the occupational therapist's role shifts from managing the system to advocating for a pharmaceutical review. Document the complexity, flag the concern in your notes, and recommend a pharmacist consultation. That's often more valuable than any goal you could write.
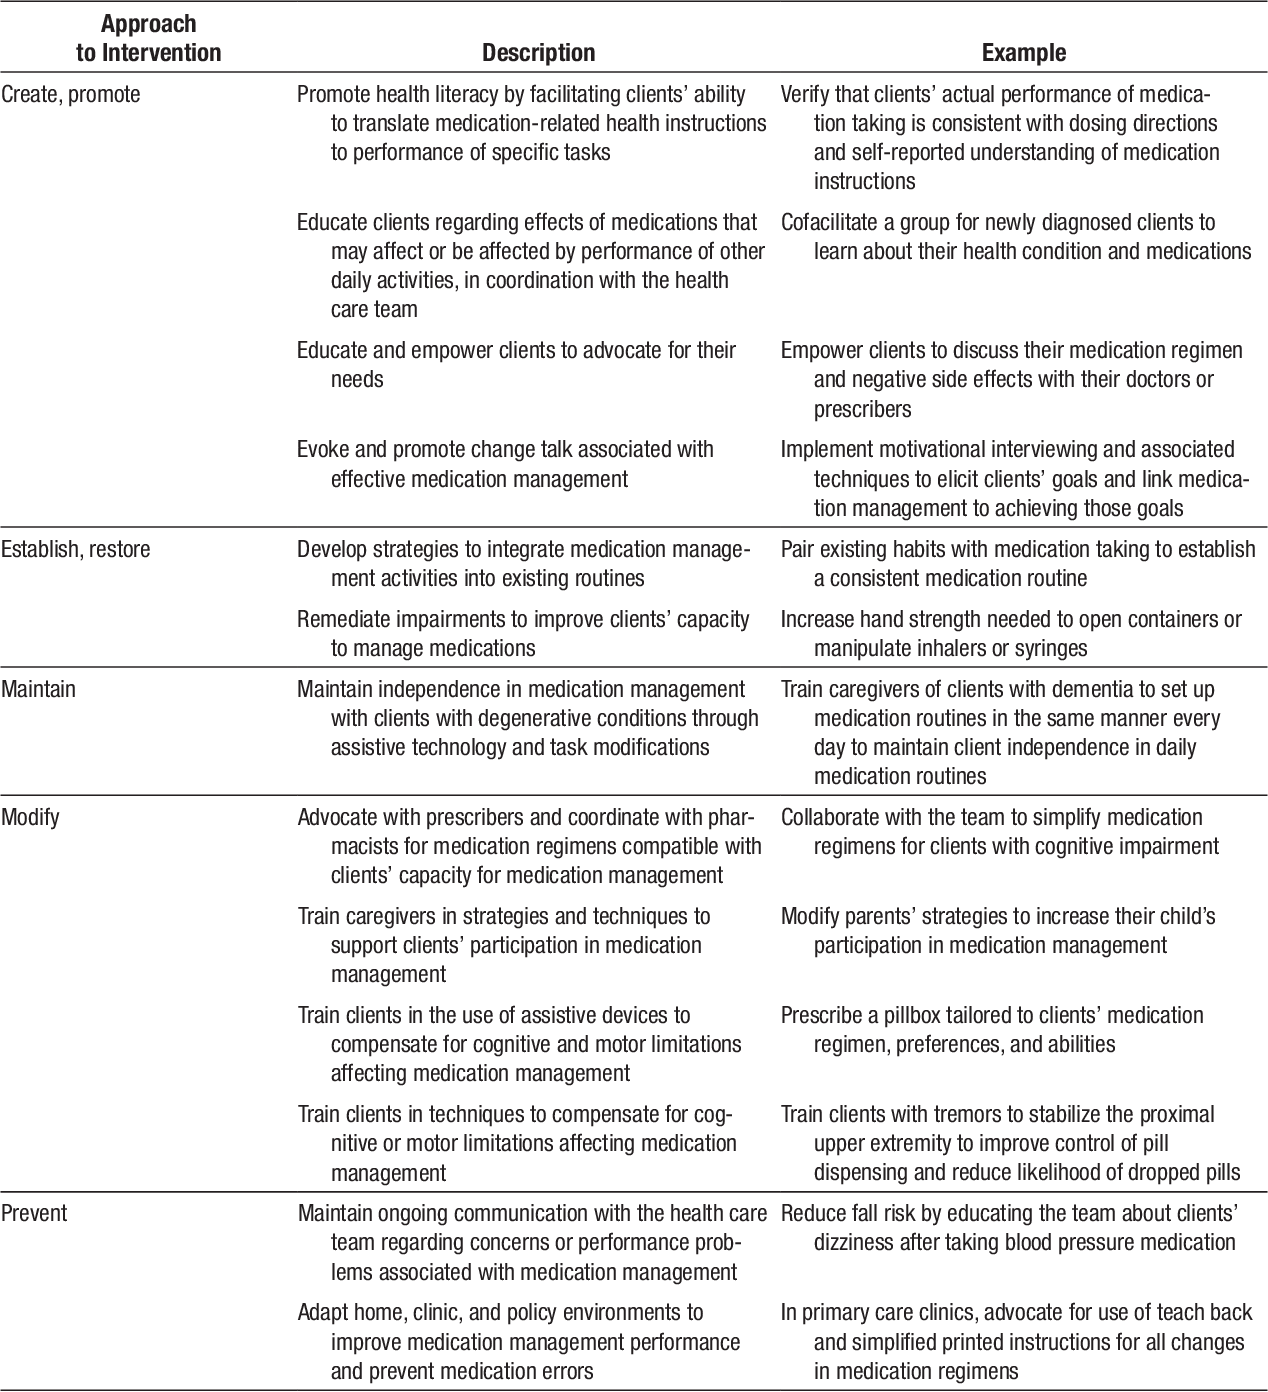
Interventions That Actually Move the Needle
Comprehensive medication reconciliation is probably the single most impactful intervention, and it's the one most OTs are least equipped to do. This involves comparing the client's current medication list against their diagnosis profile, identifying duplicates, checking for drug interactions, and verifying that the dosing schedule matches the client's daily routine. A pharmacist can do the pharmacology portion, but the occupational therapist brings the functional perspective. You know whether the client's morning routine actually allows for a 7 AM dose, or whether the schedule was written by someone who assumes the client wakes up at a consistent time. Environmental modification is the next highest-impact intervention. This includes ensuring adequate lighting at the medication storage area, reducing visual clutter around the dispensing space, using high-contrast labels, and positioning medications at waist height for clients with mobility limitations. I worked with a client who had been failing at medication management for months because his pill bottles were stored in a dark kitchen cabinet that required bending down to open. One relocation to a shelf at eye level with a small LED light strip changed everything. The clinical complexity of his regimen hadn't changed by a single factor, but his ability to manage it improved dramatically because the environmental barriers were removed. Technology-assisted interventions deserve mention but also deserve skepticism. Automated dispensers with alarms and lockouts sound like a perfect solution, but they introduce new failure points. Battery failures, connectivity issues, complex programming requirements, and the stigma of looking like a hospital patient in your own home are real concerns. I recommend these for clients with significant cognitive impairment or a history of dangerous dosing errors, but for most clients, a simple pill organizer plus a phone alarm is sufficient and more sustainable long-term. The technology should reduce cognitive load, not add new complexity.
Documentation and Outcome Measurement
Insurance reviewers and interdisciplinary teams need to see objective data, not narrative hope. Track the number of errors per dosing event, the level of assistance required, the time spent preparing and administering medications, and the client's self-reported confidence level. Reassess every two weeks minimum during active intervention. If you're not seeing measurable improvement within four weeks, the intervention isn't working and you need to pivot, not persist. I keep a simple tracking sheet for each client that logs date, dosing events observed, errors made, type of assistance provided, and total time spent. This generates enough data for strong progress reports without being burdensome to maintain. The pattern of errors is often more informative than the total count. A client who consistently misses the evening dose but nails morning doses needs a different intervention than a client who makes random errors across all time periods. The documentation should also capture the client's own perspective. Medication management is intimately tied to identity and autonomy. A client who resists using a pill organizer or accepting help may have deeper concerns about losing independence that aren't obvious from behavioral observation alone. Spend five minutes asking why they resist the tools you're offering. The answer will guide your next intervention better than any standardized outcome measure.
When Medication Management Goals Won't Work
Sometimes the honest answer is that the client cannot achieve independent medication management regardless of intervention. Advanced dementia, severe intellectual disability, untreated psychiatric conditions, and progressive neurological diseases can make any level of independent management unsafe. In these cases, the goal shifts from independence to supervised management with appropriate safeguards. This is a hard conversation to have with families who expect progress, but it's the ethical obligation. A goal that promises independence the client cannot achieve sets everyone up for failure. Document the specific barriers clearly. Note the cognitive or physical limitations that prevent safe management. Recommend appropriate supervision levels and assistive supports. If family or paid caregivers are available, involve them in the goal-setting process so they understand what they're committing to. A goal of "modified independent management with daily caregiver verification" is a legitimate and realistic outcome, even though it doesn't look like the independence most people imagine. The bottom line is that medication management in occupational therapy is not about pill boxes and reminders. It's about understanding the full chain of behavior, identifying where each individual client breaks down, and matching the intervention to the actual barrier rather than the assumed one. The goals you write should reflect that specificity, and the outcomes you measure should prove whether your assumptions were correct.



