Why Medicine Eor Study Guides Keep Producing Passes That Don't Stick
I spent the better part of three years helping residents prepare for their End-of-Rotation exams, and the pattern was always the same: people would buy or download every available study guide, grind through hundreds of questions, and still freeze when the actual EOR hit them. The problem isn't usually the material. It's the way the material is organized and presented. A Medicine Eor Study Guide is supposed to be a condensed resource that maps directly to the competencies being tested at the end of your clinical rotation. In theory it sounds straightforward. In practice most of what's out there is recycled question banks with minimal explanations and no real connection to how the exam actually unfolds.
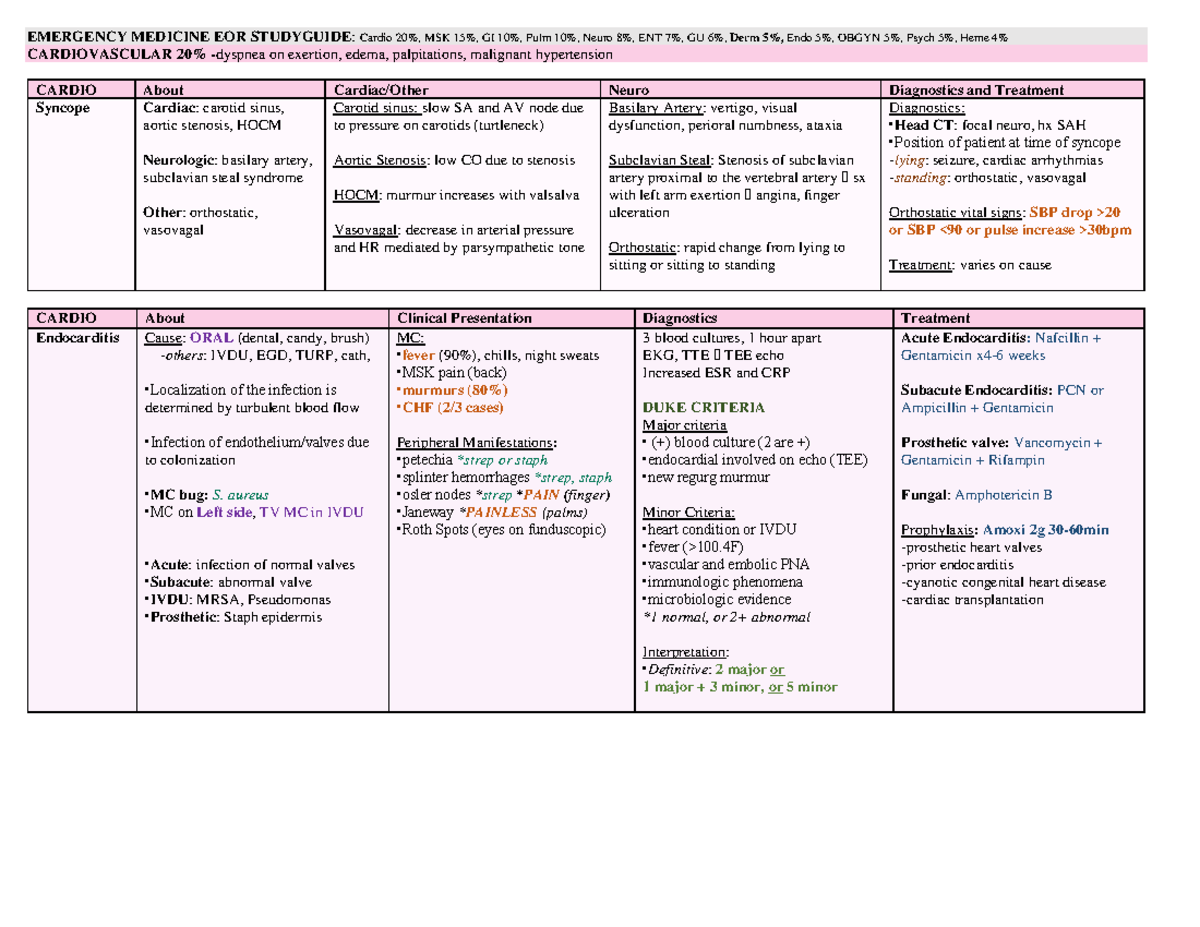
Medicine Eor Study Guide
Here's what I found that actually works, and more importantly what doesn't. The most useful guides structure their content around the ACGME milestones rather than by disease. You'll see a lot of guides organized as "Cardiology section," "Pulmonology section," and so on. That format looks clean but it creates a trap. When the exam presents a clinical vignette that crosses systems, your brain has already been trained to search by organ system instead of by clinical reasoning pathway. I learned this the hard way when a resident in my group scored in the bottom quartile on his internal medicine EOR despite having the highest question completion rate. He'd studied purely by system. The exam threw him a case of a patient with heart failure who also had new-onset atrial fibrillation and acute kidney injury. He knew all three topics individually. He couldn't synthesize them because no guide he used ever forced that exercise. The workaround I ended up building was simple but not obvious: take whichever study guide you're using and reorganize its question explanations around the decision-making sequence. Not the diagnosis. The sequence. What would you check first. What finding changes your next step. Where do you escalate versus observe. I used a spreadsheet for this. Column one had the original question. Column two had the key decision point. Column three had the alternative answer and why it loses. Column four had the clinical context that would flip the answer. It took about six hours to set up for a typical four-week rotation block. After that, reviewing for the EOR took maybe twenty minutes a day because I wasn't relearning content. I was reinforcing pattern recognition.
One thing nobody talks about is the time pressure element. Most EORs give you roughly ninety seconds per question. That means if you're spending more than two minutes on any single item during your prep, you're not training for the actual test. I started timing my residents strictly. Not as a punishment. As a diagnostic tool. When someone consistently exceeded two minutes per question, it almost never meant they didn't know the answer. It usually meant they were second-guessing between two choices because the study guide's explanation hadn't clearly defined the boundary between correct and incorrect. I'd go back to the question and rewrite the explanation in one sentence. That sentence became their anchor for that topic. Another counter-intuitive point: the questions you get wrong matter less than the ones you get right quickly. I track this metric religiously. Speed and accuracy are correlated on these exams, but not in the way people assume. The people who pass with high marks aren't the ones who ace everything slowly. They're the ones who move fast on clear questions and reserve their time for the genuinely ambiguous ones. A study guide that makes you read three paragraphs of explanation per question is actively working against this skill. You want guides where the explanation can be absorbed in under thirty seconds. That forces you to understand the concept, not just memorize the answer. There's a specific edge case that comes up constantly and most guides completely ignore it. Patients on multiple medications. The EOR loves to drop a list of five or six meds into a vignette and then ask about an interaction or an adverse effect. I remember one resident who kept missing these questions because he was studying drug names in isolation. The drugs in the medication list were never the ones he had reviewed. I switched his approach entirely. Instead of memorizing drug lists, I taught him to scan for the class first. Beta blocker. ACE inhibitor. Anticoagulant. Once you identify the class, you immediately know the side effect profile and the interaction risks. The specific drug name becomes secondary. This approach cut his missed questions on pharmacology from an average of seven per practice block down to one or two.
Get the Full Details

Now for the honest downsides. No single Medicine Eor Study Guide is sufficient on its own. The ones that are free or cheap are usually outdated question banks with answers that don't match current guidelines. The ones that are expensive often over-index on rare diseases because those make good exam questions but have almost zero clinical relevance for a resident who will never see them in practice. You will waste time on conditions you'll never encounter. I've seen it happen repeatedly. The guide that covers adrenal crisis in depth while giving you three sentences on heart failure management is not balanced. It's designed to test recall of obscure facts, not clinical judgment. Another limitation: these guides rarely address the meta-skill of reading the question itself. The wording on EOR questions is deliberately constructed. There are tells. Words like "most appropriate next step" versus "best initial test" versus "definitive management." Each phrase points to a different level of intervention. I've watched residents lose points because they answered the question they wanted to see, not the one actually written. No study guide I've encountered teaches you to parse the language systematically. You have to learn that separately, and the best way to do it is to read every explanation backward from the answer choice to the question stem. Ask yourself what specific word in the stem made that answer correct. That habit alone will improve your score more than any amount of content review. If you're short on time, here's the practical sequence I recommend. Pick one comprehensive guide and commit to it. Don't juggle three. Read each explanation once, fully. Then rebuild your own one-sentence version of that explanation. Do this for every question. Spend less time on content you already know well and more time on the topics where your speed drops below one minute per question. Those are your weak spots. The rest is review, not learning.
I keep this all concise because the topic is straightforward once you stop treating the study guide like a textbook and start treating it like a pattern-recognition tool. The EOR isn't testing how much you know. It's testing how quickly and accurately you can apply what you know under conditions that simulate real clinical pressure. Anything that slows down your thinking rather than sharpening it is the wrong kind of resource.