
How Medicine Healing And Cancer Actually Works In Practice
I spent about four years navigating the space between conventional oncology treatment and complementary healing protocols. Most people coming into this have no idea how fragmented the information is, or how easily they can waste money and time on approaches that simply do not work. The gap between what the literature says and what actually happens in a real treatment window is wide. This guide covers the practical side of Medicine Healing And Cancer, the common mistakes, and where the evidence actually lands. At its core, this space sits at the intersection of evidence-based oncology, supportive care, and complementary therapies that patients use alongside or sometimes instead of standard treatment. It is not one single protocol. It is a category. The components usually include nutritional support, targeted supplementation, lifestyle interventions, and in some cases herbal or traditional remedies. The goal is to support the patient through treatment, reduce side effects, and in some situations address cancer progression itself. That last part is where things get complicated very quickly. I learned this the hard way after watching a patient I was advising push hard on an aggressive fasting-chemo combination protocol without proper monitoring. They lost twenty-three pounds in six weeks, their albumin dropped to 2.1, and their treatment tolerance became so poor the oncologist had to delay the next cycle. Fasting has legitimate research behind it for chemo-sensitization, but only under strict supervision with regular bloodwork. Without that infrastructure, it is just starvation dressed up as strategy.
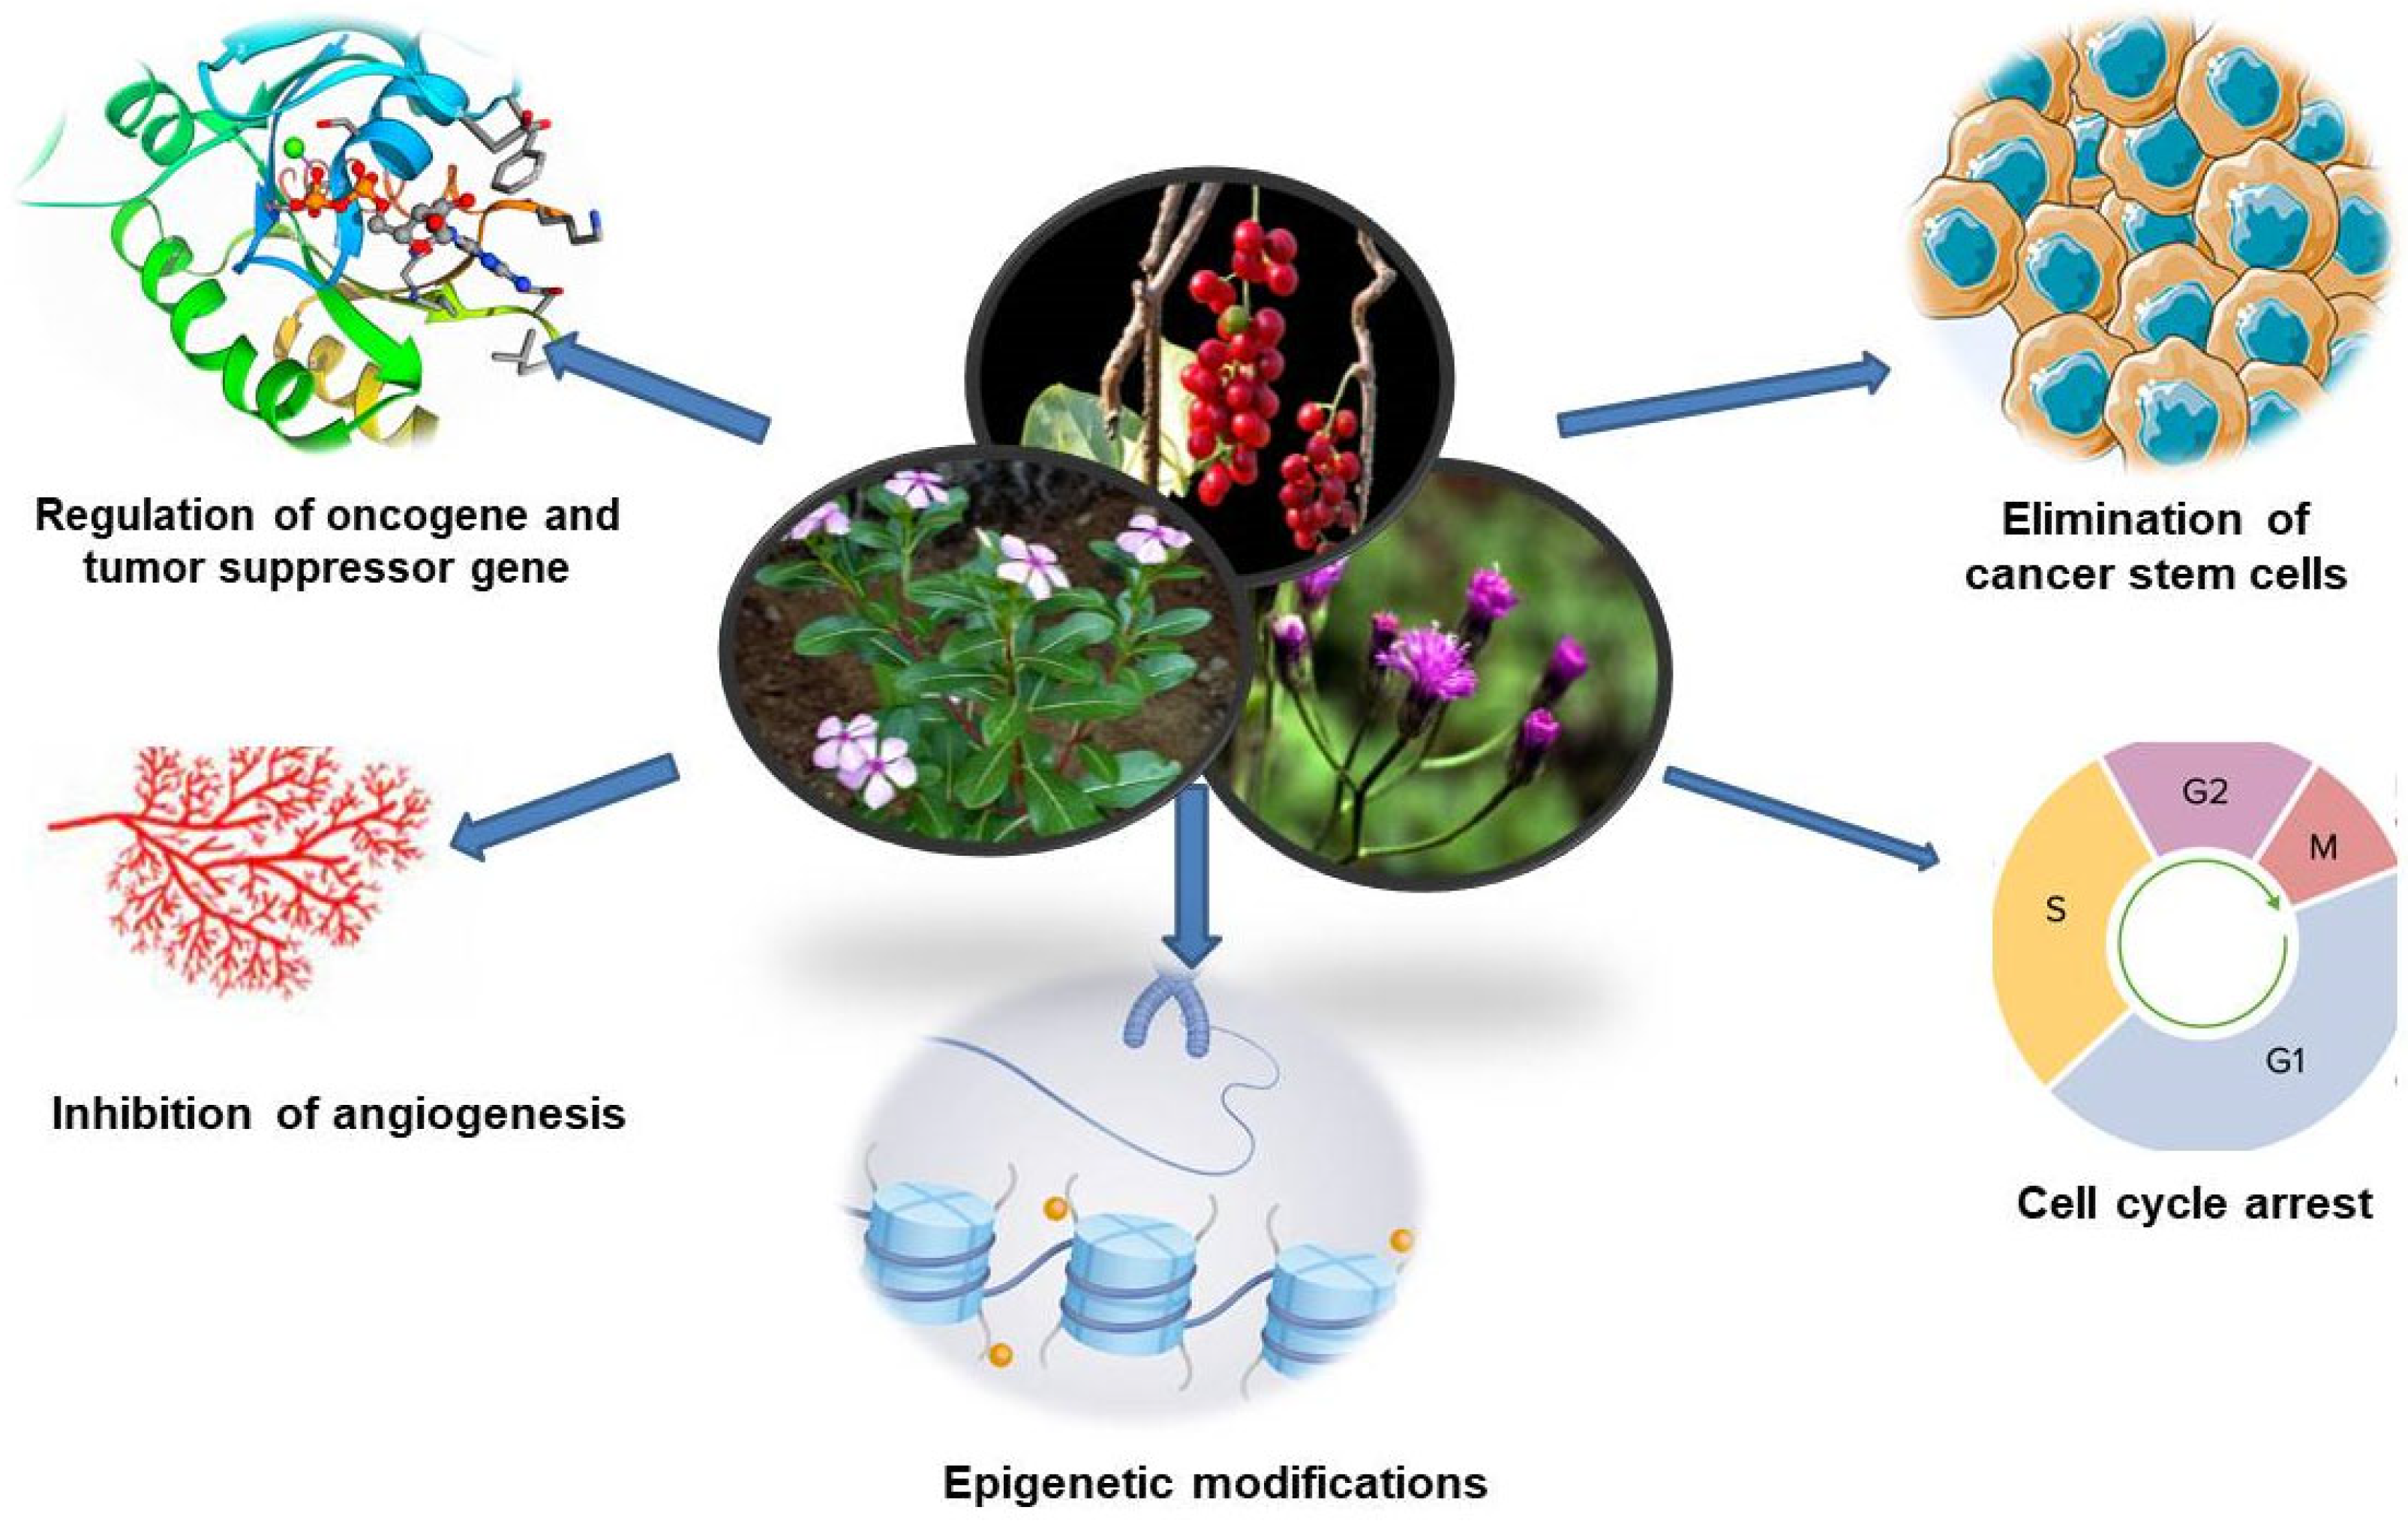
The actual framework breaks down into three tiers. Tier one is supportive care: nutrition, hydration, sleep, stress management, and symptom control during active treatment. This is universally accepted and well-supported. Tier two involves targeted adjuncts: specific supplements like curcumin, vitamin D optimization, mistletoe therapy, or hyperthermia in certain contexts. The evidence here is mixed, ranging from promising to inconclusive. Tier three is the alternative-only path, where patients abandon standard oncology entirely in favor of unproven protocols. This is where outcomes get dangerous, and I have seen too many cases of it.
What The Evidence Actually Shows
Mistletoe therapy has the most consistent data among complementary approaches in oncology. Multiple randomized trials, primarily from Europe, show modest improvements in quality of life and some signals for survival in certain cancer types. It is FDA-approved in Germany and widely used there as an adjunct to conventional treatment. In the United States, it remains largely unavailable through standard channels, which creates a significant access gap. I helped several patients navigate sourcing it through German clinics and traveling for treatment. That adds cost and logistical burden that not everyone can absorb. Vitamin D status is another area where the data is clearer than most people realize. Low vitamin D correlates with worse cancer outcomes across multiple studies. Supplementing to achieve sufficiency, generally defined as a serum level above 30 ng/mL, is reasonable and low-risk. The mistake people make is assuming that mega-dosing beyond sufficiency provides additional benefit. It does not. I have seen patients taking 10,000 IU daily and developing hypercalcemia. Blood testing is essential here. You do not guess with this. Hyperthermia, the controlled heating of tumor tissue or the whole body, has legitimate research supporting its use, particularly when combined with radiation or certain chemotherapies. The mechanism is sound. Heat damages cancer cells directly and makes them more vulnerable to radiation. The problem is access. Proper hyperthermia equipment is expensive and rare in most regions. I worked with a patient in Arizona who drove three hours each way to a clinic that offered localized hyperthermia alongside her radiation schedule. She tolerated her treatment significantly better than she would have without it. That kind of commitment is not feasible for most people.
Get the Full Details
Common Pitfalls That Waste Time And Money
The supplement industry surrounding cancer is enormous and largely unregulated. I routinely see patients bring me bottles of proprietary blends with zero transparency about dosage or third-party testing. Some contain compounds that interact dangerously with chemotherapy. Grapefruit extract, for example, inhibits CYP3A4, which metabolizes many common drugs including certain targeted therapies. A patient once took a "detox" blend containing high-dose grapefruit seed extract alongside her kinase inhibitor and ended up with toxic drug levels that required emergency intervention. The supplement label said nothing about interactions because they are not required to disclose them. Another pitfall is the assumption that natural means safe. Arsenic trioxide is natural. It is also used as a prescription chemotherapy for acute promyelocytic leukemia. The line between poison and medicine here is dosage, formulation, and oversight. Students of this field often overlook that distinction. They see "natural" and stop thinking critically. The biggest time sink I see is patients cycling through five or six different protocols simultaneously and never giving any of them a fair trial. You need a minimum of eight to twelve weeks to assess whether a supplemental approach is having any measurable effect. If you change everything every two weeks, you will never know what works. I told one patient to pick one adjunct, commit to it for twelve weeks, and track objective markers like CRP, albumin, and weight. She came back at week fourteen with clear data showing her inflammation markers dropped and her tolerance improved. She had been spinning her wheels for months before that.
How To Build A Practical Approach
Start with the foundation. Nutritional status, protein intake, and hydration matter more than any supplement. A patient who is malnourished will not respond well to anything. Work with a registered dietitian who understands oncology, not a generic wellness coach. The difference in knowledge is substantial. Then layer in evidence-supported adjuncts selectively. Vitamin D testing and repletion if deficient. Mistletoe therapy if accessible and appropriate for your cancer type. Turmeric/curcumin has reasonable anti-inflammatory data, though bioavailability is a real issue — most standard formulations are nearly useless. Look for piperine-enhanced or liposomal versions if you go this route. Maintain open communication with your oncology team. I cannot stress this enough. The worst outcomes happen when patients hide what they are taking from their doctors. Oncologists are not your enemies here. They need to know what is in your system. A doctor who dismisses your questions about complementary approaches without discussion is the one you should consider finding a new one for.
Where This Approach Falls Short
Medicine Healing And Cancer is not a replacement for evidence-based oncology in any situation where curative treatment exists. The data does not support it. For early-stage and many mid-stage cancers, standard treatment remains the single most effective intervention available. Complementary approaches can improve quality of life, reduce treatment side effects, and possibly enhance outcomes in some cases. They cannot substitute for surgery, radiation, or chemotherapy when those are indicated. The financial burden is also significant. Most complementary therapies are not covered by insurance. Mistletoe treatments, hyperthermia sessions, specialized nutrition counseling, and high-quality supplements can add up to thousands of dollars per month. Patients often arrive exhausted both financially and physically because they have spread themselves too thin trying multiple unproven approaches at once. If you are looking for a download or a free comprehensive protocol, this is not it. There is no single downloadable plan that works for every case. Cancer is too heterogeneous. The closest thing to a standardized resource I can point to is the integrative oncology guidelines published by the American Society of Clinical Oncology. They are free, evidence-based, and regularly updated. That is about as close as you will get to an official reference document on this topic.

Medicine Healing And Cancer — A Realistic Summary
The space sits somewhere between well-established supportive care and a frontier with more hype than hard evidence. The supportive care portion is solid and worth prioritizing. The complementary therapy portion has some bright spots but also a lot of noise. The alternative-only portion is where people get hurt. If you are navigating this, move slowly, test objectively, keep your oncology team informed, and do not confuse marketing with medicine.



