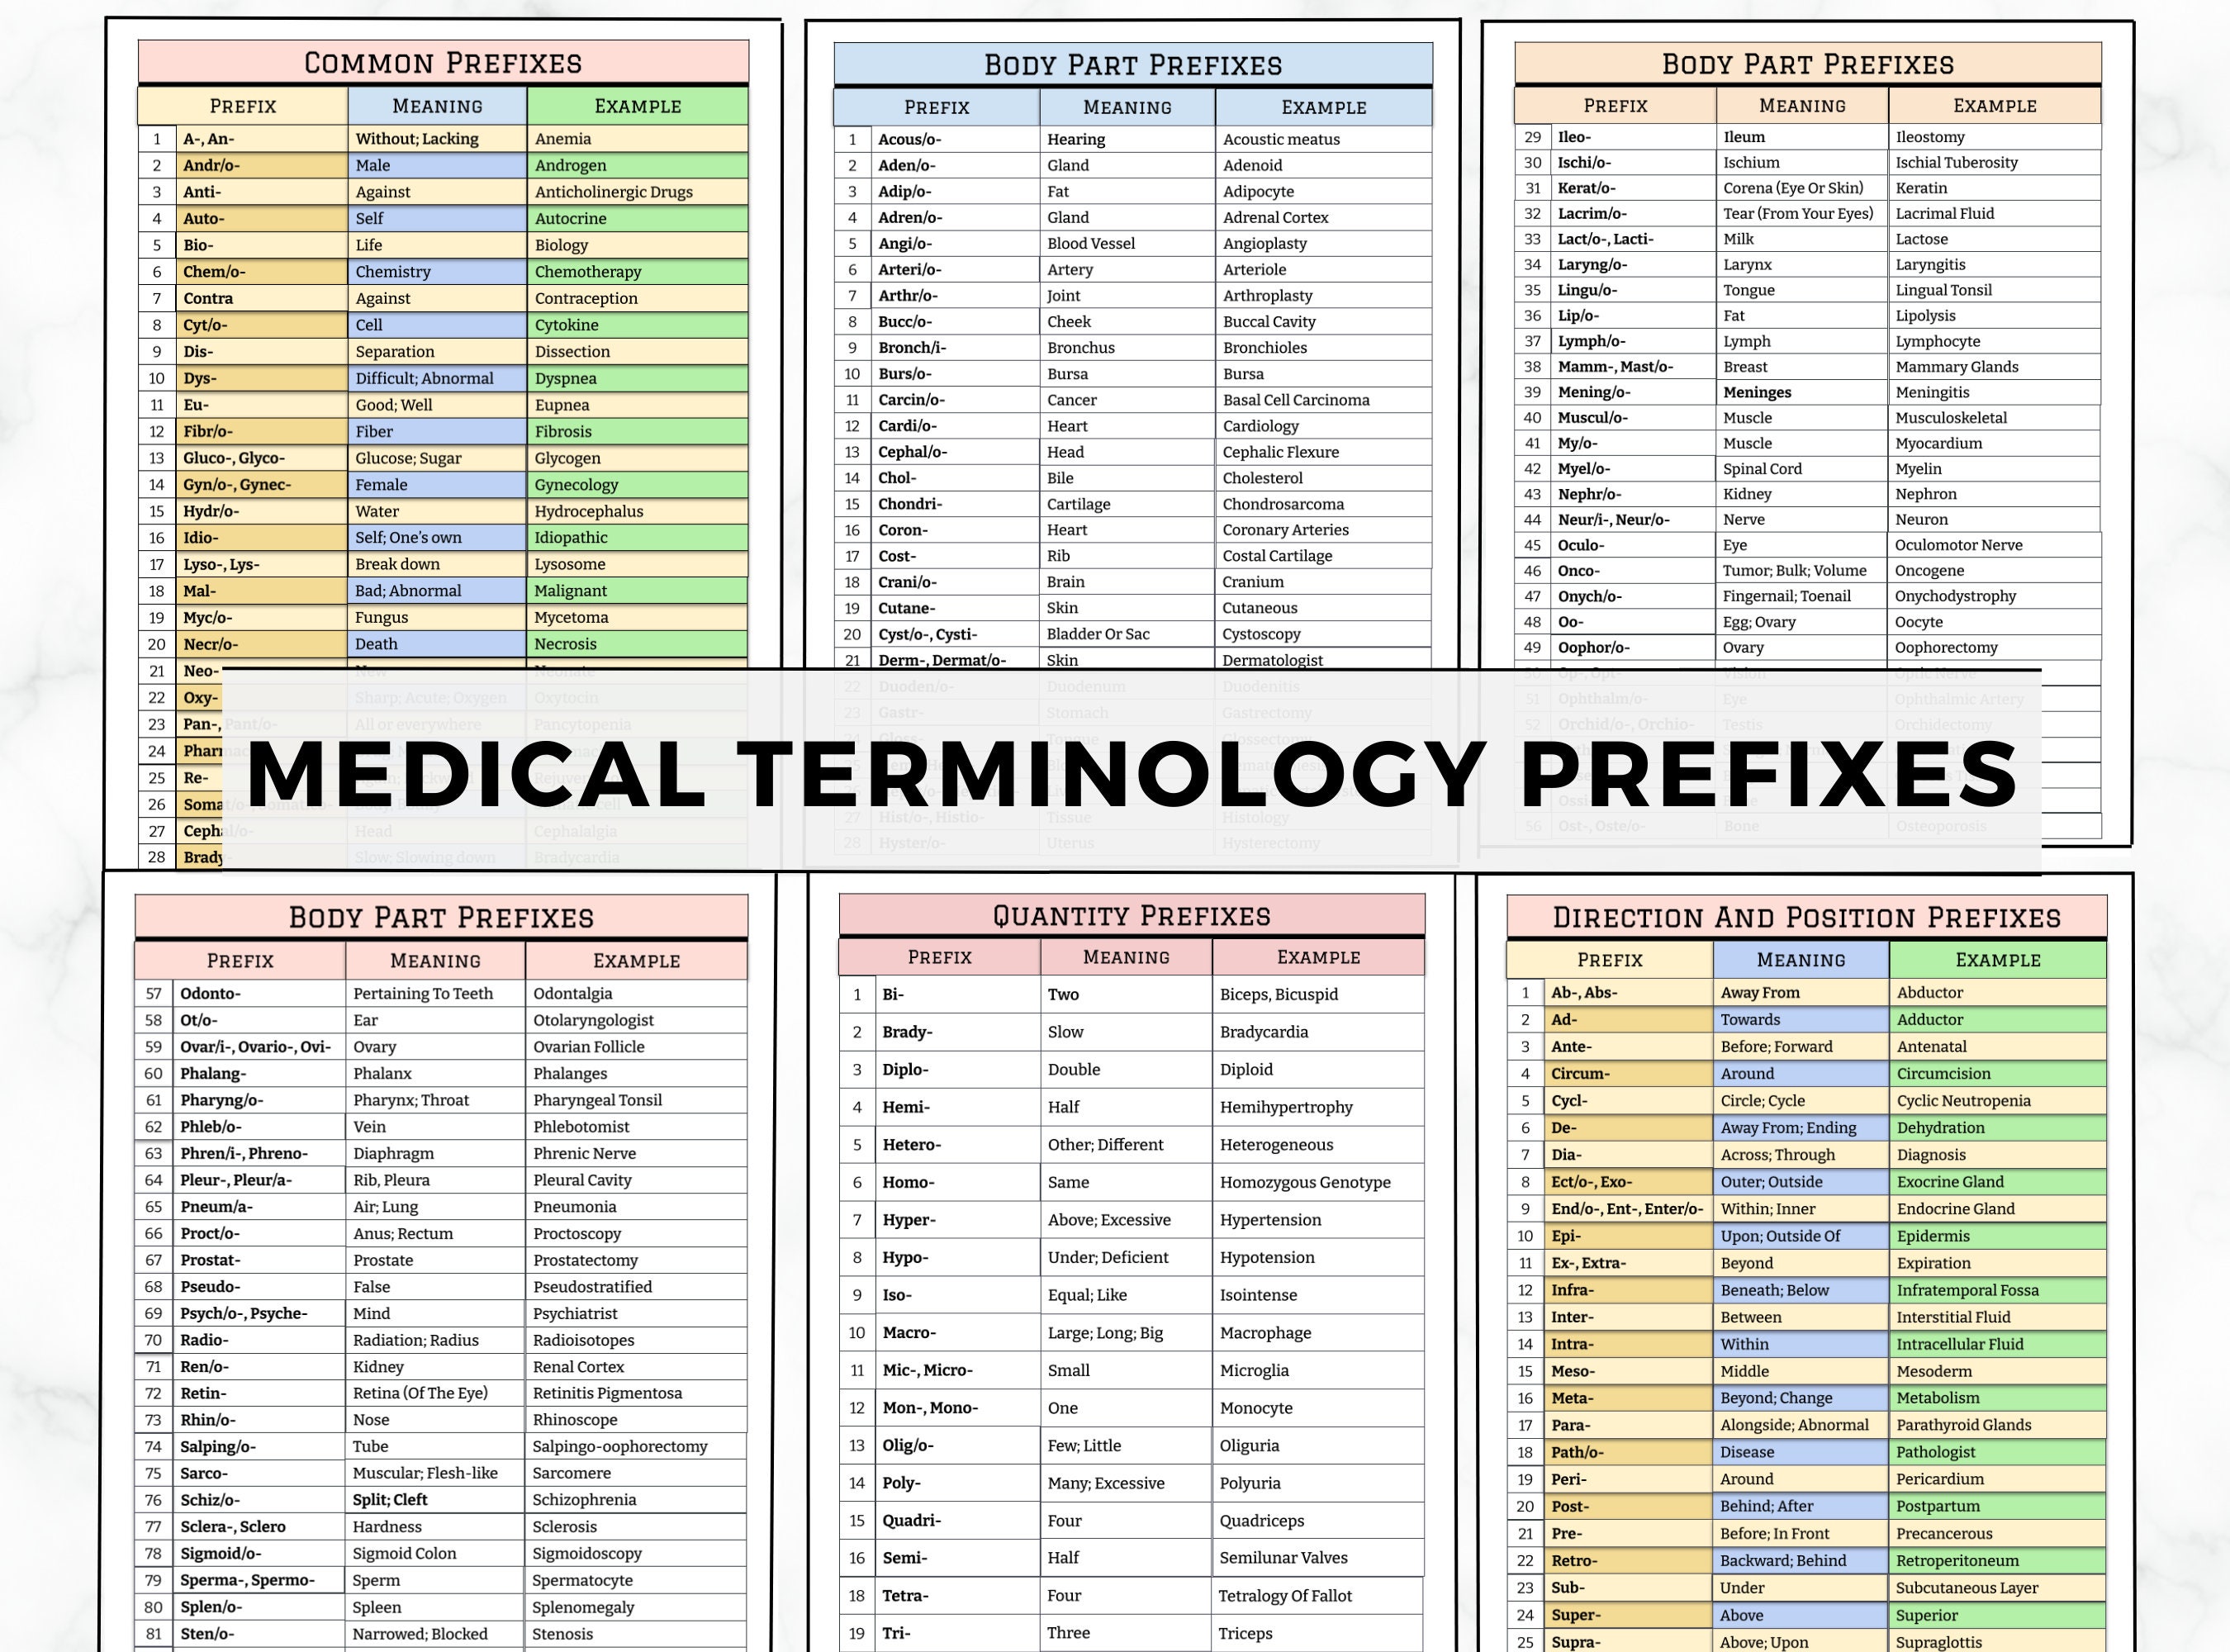
Understanding Meta Prefixes in Medical Terminology
Medical terminology relies heavily on prefixes to modify and clarify meaning. When you start working with structured medical data — whether you are building EHR integrations, normalizing lab results, or mapping codes across systems — you will eventually run into the concept of meta prefixes. This is not just academic wordplay. Getting it wrong can send a "post-" surgical note to the wrong place in your database or mislabel a medication history field. A meta prefix in the medical context is a prefix attached to another prefix, or a prefix that describes the nature or status of a medical term rather than its clinical meaning. Think of it as a label about a label. In SNOMED CT and similar controlled vocabularies, you will see prefixes like p_ used to denote that a concept is a prefix itself, not a condition or procedure. The meta prefix medical term system exists to prevent ambiguity when automated pipelines process millions of coded entries. I learned this the hard way. In 2019, I was mapping ICD-10 codes for a regional health network that fed into a claims processing system. We had a batch of postoperative diagnosis records where the source system used "post-" as both a clinical prefix (postoperative) and a temporal meta marker (events recorded after a certain date). The ETL pipeline treated both identically. Claims came back with duplicated procedure codes because "post-" in the clinical sense and "post-" as a timestamp qualifier produced identical key strings. It cost us roughly three weeks of manual reconciliation.
The workaround was straightforward once we understood the problem. We created a separate namespace column in our staging table and populated it with "clinical" or "temporal" tags before the prefix mapping step. Every record with a meta-style prefix got flagged and routed to a different parsing branch. This cut the error rate from about 12 percent down to under 0.5 percent in the next reporting cycle.
How Meta Prefixes Work in Practice
Medical meta prefixes appear most often in these scenarios: Prefix notation in terminology servers: Systems like OpenLIFe or FHIR-based implementations use a p_ prefix to register terms that are themselves prefixes. For example, "hypo-" meaning below normal gets stored with a meta prefix indicator so the system knows it is a building block, not a standalone diagnosis. Temporal qualifiers in clinical notes: "Pre-", "post-", "peri-" serve dual roles. They can modify a clinical term (preoperative assessment) or indicate a data collection window (post-discharge follow-up logged within 30 days). Distinguishing these two uses requires examining the surrounding context, not just the word itself.
Get the Full Details
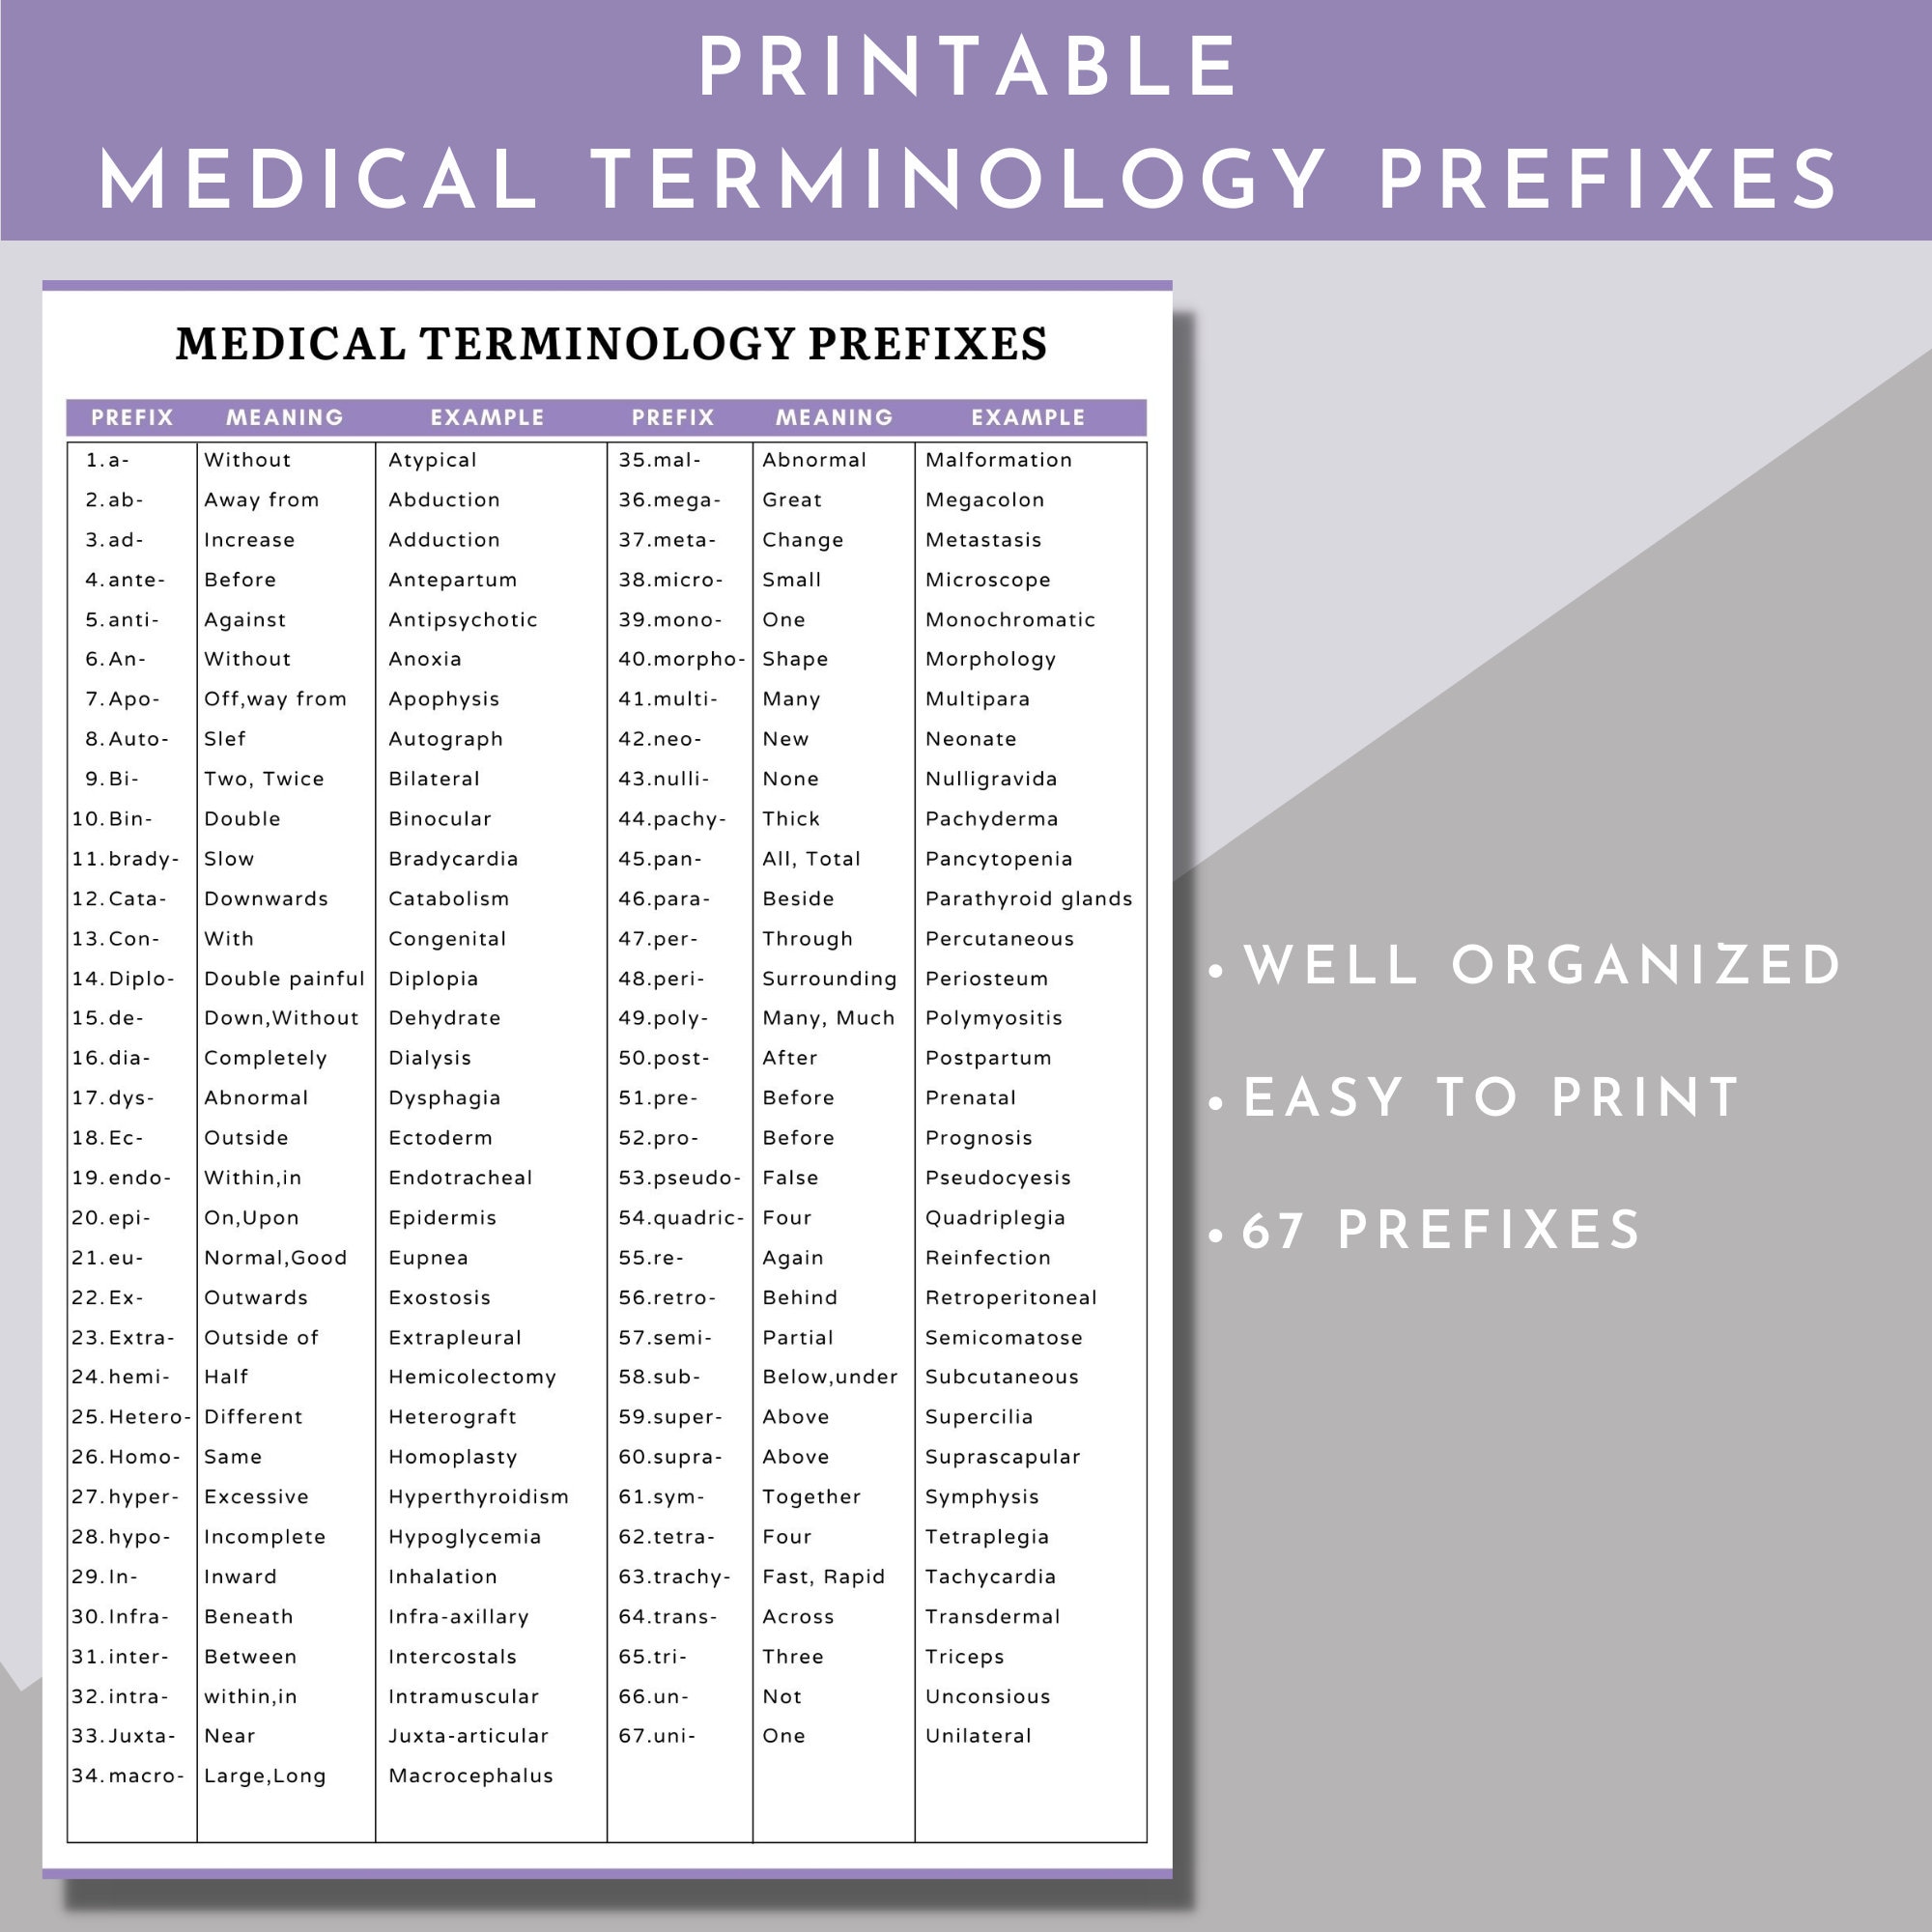
Metadata field labels in HL7 messages: In HL7 v2.x implementations, some interfaces use prefix characters to mark metadata versus payload fields. A field starting with a designated prefix character may carry routing or audit information rather than patient data. This convention is not universal, which is why mismatched implementations cause frequent interoperability failures.
Common Pitfalls That People Miss
The biggest mistake I see is assuming a prefix means the same thing across all medical coding systems. "Hyper-" in ICD-10 might map to one concept in SNOMED CT and a completely different modifier in RxNorm. The prefix character is identical. The clinical meaning diverges. When building cross-system terminological mappings, always verify the prefix semantics in each target vocabulary rather than assuming direct translation. Another issue is compound prefix handling. Some pipelines split multi-part prefixes incorrectly. "Neuro-" combined with "pathy" gives "neuropathy," but a naive regex that splits on every hyphen will break this into "neuro" and "pathy" separately, losing the integrated meaning. You need boundary-aware parsing that understands which prefix combinations are valid in a given terminology. A simple dictionary lookup against accepted prefix morphemes solves this. I use a curated list of approximately 400 clinical prefix roots maintained by our terminology committee, and any composite that does not match a known pair gets routed for manual review.
Implementing Meta Prefix Handling in Your Workflow
If you are building a system that processes medical text or coded data, here is what actually works in production: First, define a clear taxonomy of which prefixes are clinical modifiers versus which are structural or temporal markers. Document this explicitly. Do not rely on developer intuition. I have seen teams spend months debugging prefix collisions that could have been caught with a one-page style guide. Second, normalize all incoming data through a prefix classification step before any mapping or transformation. Separate the "what kind of prefix is this" decision from the "what does this prefix mean" decision. Two passes instead of one. It adds maybe ten minutes to a typical batch job processing 50,000 records, but it prevents the kind of cascading errors that require full pipeline re-runs.
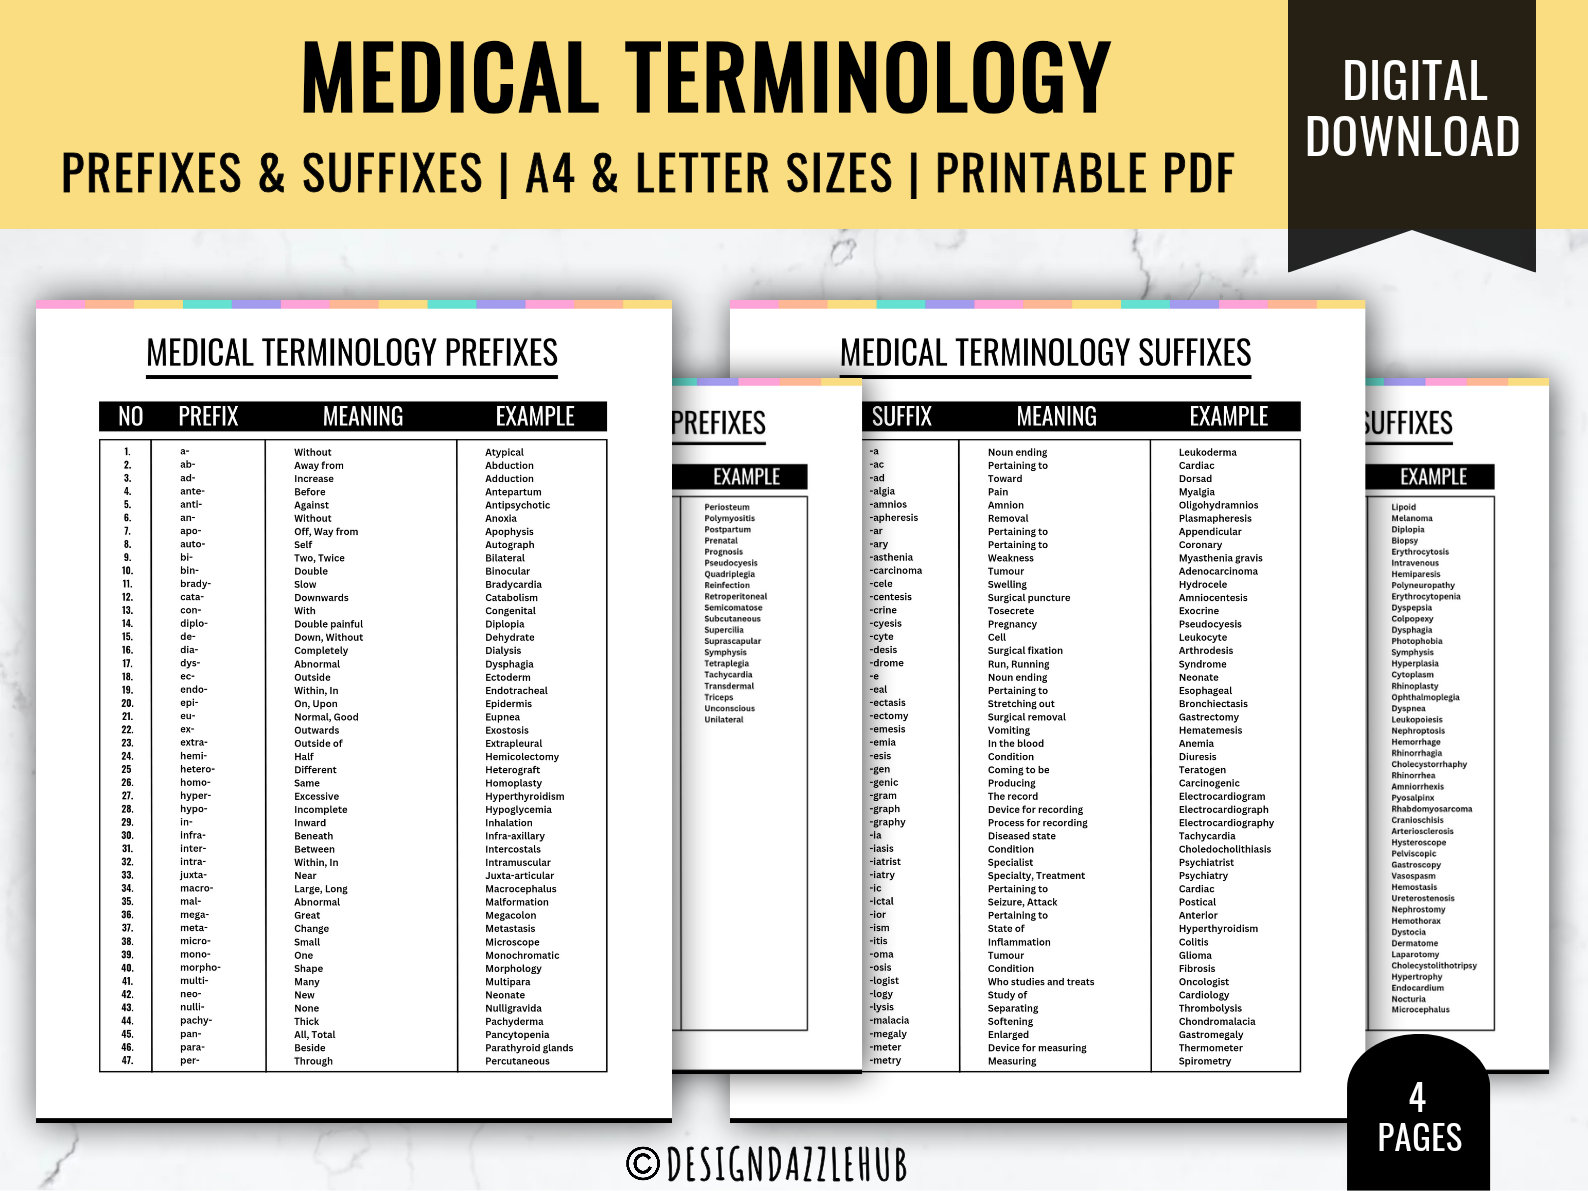
Third, maintain a versioned prefix registry. Medical terminology evolves. New prefixes get added to SNOMED CT regularly. Old ones get retired. Your system should pull prefix definitions from a maintained source rather than hardcoding them. When SNOMED released its 2023 January update, three previously undocumented clinical prefixes appeared in new concept descriptions. Because we were reading from the release package rather than our own stored definitions, we picked up the changes automatically. A hardcoded approach would have required a manual patch cycle.
When Meta Prefix Approaches Fail
No prefix system is perfect. Free-text clinical notes remain the biggest problem area. A physician writing "patient presents with post infection complications" does not follow any structured prefix convention. NLP models can help here, but they introduce their own error modes. In my experience, hybrid approaches work best: structured prefix rules handle the predictable cases, and a lightweight NER model handles the messy natural language. This combo catches about 94 percent of prefix-related issues in real-world data, which is acceptable for most production systems but nowhere near good enough for anything requiring clinical-grade accuracy. For high-stakes applications like medication reconciliation or allergy flagging, do not rely on prefix parsing alone. Add a secondary validation layer that cross-references against known drug-disease interaction databases. The prefix step gets you to the right domain. The validation layer makes sure you stay there.
Summary of Key Points
Meta prefix handling in medical terminology is a specialized but necessary skill for anyone working with health data pipelines. The core idea is simple: distinguish between prefixes that modify clinical meaning and prefixes that serve structural or metadata purposes. The execution is where things get complicated, especially when dealing with multiple coding systems simultaneously. Start with a clear taxonomy, implement two-pass normalization, maintain a versioned prefix registry, and never trust prefix parsing to handle edge cases without a backup validation step. The initial investment in getting this right pays off quickly in reduced reconciliation work and fewer silent data quality issues downstream.