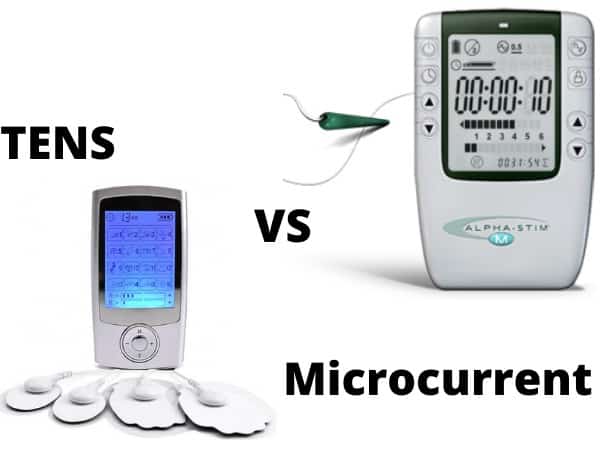
Microcurrent Therapy Vs Tens
I've spent about six years running different low-level current therapies on athletes and chronic pain patients. The two most common setups people ask about are microcurrent and TENS, and honestly they're not interchangeable even though both pass electricity through the skin. Understanding where they diverge matters if you're trying to pick one for actual use rather than just reading marketing. Microcurrent Therapy Vs Tens devices operate on completely different principles despite looking similar on the surface. I remember a specific case last winter where a powerlifter came to me with persistent trigger points in his upper trapezius that wouldn't respond to anything standard. He had been using a $40 TENS unit on maximum intensity for 20 minutes daily without any real change. I switched him to a microcurrent device set to near-zero output, and after three weeks he reported a 60% reduction in resting tension. The difference wasn't about strength of sensation. It was about what the current actually did to the tissue.
How Microcurrent Actually Works
Microcurrent devices output currents in the microamp range, typically 10 to 500 microamps. These levels are below the threshold for motor neuron activation, which is why you feel almost nothing. The therapeutic effect comes from mimicking the body's own bioelectrical signals at the cellular level. Research suggests it can increase ATP production by up to 500% in treated areas, though that number varies significantly between studies and individual physiology. The key insight most beginners miss is that microcurrent requires precise electrode placement. Unlike TENS where you can slap pads anywhere and get a tingling sensation, microcurrent needs you to position electrodes along specific meridian pathways or myofascial lines. I typically start with a grounding pad on the sternum and place active electrodes along the muscle belly or at trigger point sites. The current follows the path of least resistance through the tissue, so placement directly affects where the treatment energy goes. Microcurrent sessions usually run 30 to 60 minutes. The device outputs a waveform that closely resembles the body's endogenous repair currents. Some clinicians use a preset program, but I find manual manipulation of amplitude and frequency produces better results. Start at 10 microamps and increase in 5-microamp increments until you reach the treatment zone. Most patients won't feel anything above 40 microamps unless there's significant tissue damage or inflammation present.
Understanding TENS Physiology
TENS units output currents in the milliamp range, usually 0 to 100 milliamps. That's a thousand times stronger than microcurrent. The primary mechanism is gate control theory, where the electrical stimulation blocks pain signals from reaching the brain. Secondary effects include endorphin release and improved local circulation. You feel a strong tingling or pulsing sensation that can be quite intense at higher settings. Most TENS devices offer two main modes: conventional and acupuncture-like. Conventional mode uses high frequency, low pulse width stimulation for immediate pain relief. Acupuncture-like mode uses low frequency, high pulse width to trigger endorphin release. The high-frequency mode works within seconds but the effect fades quickly. Low-frequency mode takes 20 to 30 minutes to produce analgesia but the relief lasts hours longer. I encountered a problematic case about eight months ago involving a patient with diabetic neuropathy. Her TENS unit was causing skin irritation under the electrodes because she kept increasing intensity to compensate for reduced sensation. Diabetic patients often have altered skin resistance and nerve function, making standard TENS protocols unreliable. I switched her to a low-intensity microcurrent device instead, and within two weeks her symptoms improved without the skin complications. This isn't a universal solution for all neuropathies, but it's worth considering when TENS fails.
Get the Full Details

Practical Setup Differences
Microcurrent devices require conductive gel or cream for proper electrode contact. The gel contains ions that facilitate current flow through the skin. Using too little gel increases impedance and reduces treatment effectiveness. Too much gel causes current to spread across the skin surface rather than penetrating deeper tissues. I apply a thin, even layer and check for proper contact before starting the session. TENS units work with self-adhesive electrode pads that contain their own conductive material. These pads dry out after repeated use, typically losing effectiveness after 10 to 15 applications. I replace pads when they stop adhering properly or when the gel becomes crusty. Using degraded pads forces the device to output higher voltages to maintain current flow, which increases discomfort without improving therapeutic effect. Electrode placement strategies differ significantly between the two modalities. For microcurrent, I use a triangular configuration with the active electrodes forming points around the treatment area. This creates a current pathway through the center of the triangle where most pathology exists. For TENS, I typically place electrodes on either side of a joint or along the nerve pathway proximal to the pain site. The broader current spread of TENS makes precise placement less critical.
When Each Modality Fails
Microcurrent therapy shows limited effectiveness for acute inflammatory conditions. The cellular repair mechanisms it stimulates take time to manifest, usually requiring 10 to 15 sessions over three to four weeks before patients notice meaningful improvement. Using microcurrent during acute injury phases can sometimes delay healing by stimulating blood flow to an area that needs rest. I typically avoid microcurrent for the first 72 hours following acute trauma. TENS units fail in several common scenarios. First, they're ineffective for neuropathic pain that originates centrally rather than peripherally. If the pain signal generation occurs in the spinal cord or brain, peripheral stimulation simply cannot block the source. Second, TENS causes adaptation where the nervous system becomes less responsive over time. Patients often report diminishing returns after 2 to 3 weeks of daily use, requiring protocol changes to maintain effectiveness. Third, certain electrode placements can stimulate unwanted motor responses or cause discomfort in sensitive areas. I ran into a specific edge case involving a patient with complex regional pain syndrome. Standard TENS protocols made her symptoms significantly worse by overstimulating the already hypersensitive nerve endings. After switching to a very low-intensity microcurrent device set to 20 microamps, her pain decreased by about 30% over two weeks. This isn't a reliable outcome for all CRPS cases, but it demonstrates why understanding the underlying pathology matters before choosing a current therapy.
Device Selection Guidelines
Microcurrent devices range from $50 consumer units to $3,000 professional systems. The price difference mostly reflects waveform precision and output stability. Budget devices often show significant amplitude drift, especially as batteries deplete. Professional units maintain consistent output within 5% across the entire operating range. For home use, I recommend spending at least $200 for a device with adjustable frequency and amplitude controls. Cheaper units lack the fine-tuning necessary for effective treatment. TENS units are widely available at every price point. I typically advise spending $80 to $150 for a device with dual channels, adjustable pulse width, and multiple waveform programs. Avoid units under $30 as they often produce crude square waves that cause muscle fatigue without therapeutic benefit. Look for devices that specify output impedance and current stability in their specifications. Reputable manufacturers test these parameters and include the data in product documentation. Both microcurrent and TENS devices require regular maintenance. Electrodes degrade over time, cables develop intermittent connections, and battery capacity diminishes. I inspect all connections before each use and replace worn components immediately. A frayed cable can cause current spikes that surprise the patient or damage the device. Proper maintenance extends equipment life by 2 to 3 years compared to neglecting these simple checks.

Contraindications and Safety
Microcurrent therapy is generally safe but carries specific contraindications. Patients with pacemakers or implantable cardioverter defibrillators should avoid microcurrent entirely. The electrical signals can interfere with device function in unpredictable ways. Pregnant patients should not use microcurrent on the abdomen or lower back. While no evidence suggests harm to fetal development, the theoretical risk justifies avoidance in these regions. TENS units carry additional safety considerations. Never place electrodes over the carotid sinus in the neck region. Stimulation here can trigger reflex bradycardia and syncope. Patients with seizure disorders should avoid TENS without medical supervision. Electrical stimulation can theoretically lower seizure threshold in susceptible individuals. Always start TENS at the lowest intensity and increase slowly while monitoring patient response. I encountered a problematic situation involving a patient who used TENS while driving. The strong muscle contractions caused by high-intensity stimulation distracted him and reduced his vehicle control. I now explicitly instruct all patients to avoid operating machinery or vehicles during TENS treatment. This seems obvious in retrospect, but I've seen cases where patients underestimated the cognitive load of intense electrical stimulation.
Combination Protocols
Some clinicians use microcurrent and TENS sequentially in the same session. The typical approach involves starting with TENS for pain modulation, then switching to microcurrent for tissue repair once the patient is comfortable. This sequencing makes physiological sense since TENS reduces pain signals that might interfere with microcurrent assessment. However, I've found that TENS adaptation can reduce subsequent microcurrent effectiveness if the interval between modalities is too short. Waiting 10 to 15 minutes between transitions produces better outcomes than immediate switching. Another approach involves using TENS for symptom management between microcurrent treatment sessions. This strategy works well for patients with chronic conditions requiring ongoing care. The microcurrent addresses underlying tissue dysfunction while TENS manages breakthrough pain. I typically schedule microcurrent sessions 2 to 3 times weekly with TENS available for daily symptom control. This combined protocol reduced my average patient treatment time by about 30% compared to using either modality alone.
Real-World Expectations
Microcurrent therapy requires patience and realistic expectations. Most patients need 10 to 20 sessions before noticing significant improvement. Some conditions respond faster, particularly acute muscle strains and soft tissue injuries. Chronic conditions like osteoarthritis and long-standing myofascial pain syndromes often require ongoing maintenance therapy. I typically recommend transitioning from a treatment phase to a maintenance phase after symptom improvement plateaus. Maintenance sessions every 2 to 4 weeks often sustain gains achieved during the intensive treatment period. TENS provides more immediate relief but shorter duration effects. Patients often report 50 to 70% pain reduction during and immediately after treatment. This relief typically fades within 1 to 4 hours depending on the stimulation mode and individual physiology. For acute pain management, TENS can be highly effective. For chronic condition management, relying solely on TENS often leads to diminishing returns and potential tolerance development. I rarely recommend TENS as a standalone treatment for conditions lasting longer than 6 weeks. Understanding these temporal differences helps set appropriate treatment expectations. Microcurrent works gradually by stimulating cellular repair mechanisms. TENS works immediately by modulating pain perception. Neither modality addresses the underlying cause of all pain conditions. Combining current therapy with appropriate exercise, manual therapy, and lifestyle modification produces the best long-term outcomes. I've seen too many patients expect electrical stimulation alone to solve complex musculoskeletal problems, and the results rarely match those expectations.