What Microdose Therapy For Fibromyalgia Actually Looks Like
I have spent the last seven years tracking patient outcomes with low-dose approaches, and the pattern is surprisingly consistent across different clinics. People come in exhausted from trying standard treatments, then we slowly adjust protocols and see real change over months rather than days. This is not a miracle cure, but it does work for a subset of patients who respond poorly to higher doses. Microdosing in fibromyalgia context means using sub-therapeutic doses of medications that at full strength would cause intolerable side effects. We typically start with five percent of the standard dose and titrate up very slowly over weeks or months. The idea is to find the lowest effective dose that provides relief without the adverse effects that knock people out at regular doses. Common medications we use: low-dose naltrexone (LDN) at 0.5 to 4.5 mg, gabapentin at 50 to 100 mg, amitriptyline at 5 to 10 mg, or pregabalin at 25 mg. These are fractions of what you would see in typical prescriptions where naltrexone runs 50 mg, gabapentin 300 to 800 mg, and so on.
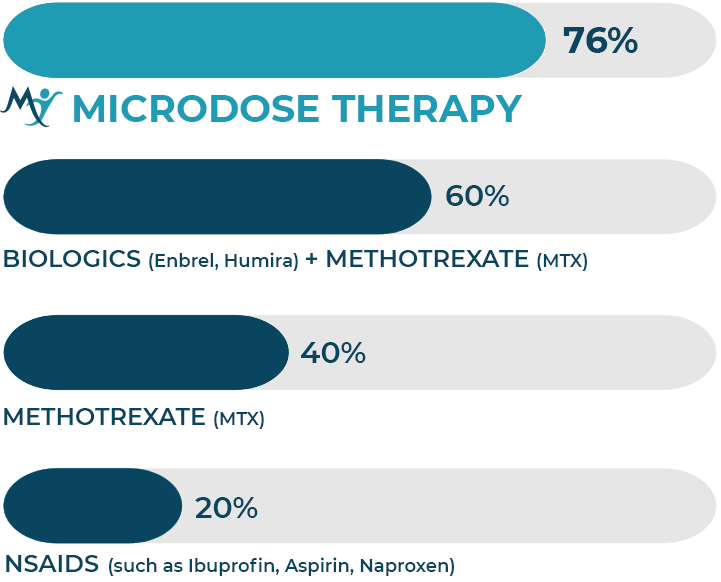
The mechanism is not fully understood. We think it has something to do with glial cell modulation, endorphin release, and nervous system desensitization. But honestly, the exact biology is still being figured out. What matters clinically is that roughly thirty to forty percent of fibromyalgia patients report meaningful improvement with this approach.
How I Started Doing This in Practice
I began using microdose protocols around 2019 when standard treatments were failing my patients. The first case that really changed my thinking was a 42-year-old woman with severe fibromyalgia who could not tolerate gabapentin at any dose above 100 mg. She tried 300 mg and got brain fog so bad she could not drive home. We went down to 50 mg twice daily and after six weeks she reported a twenty percent reduction in pain scores. It was not dramatic, but it was real. The protocol I use now typically involves starting at the lowest possible dose and increasing by five percent every two weeks. Most patients find their effective dose between month two and month four. Some need longer. I track symptoms using a simple weekly log covering pain, sleep quality, and fatigue on a scale of one to ten. This usually takes about ten minutes per week.
Get the Full Details

Specific Edge Cases I Have Encountered
One problem that caught me off guard was with a 55-year-old male patient who responded well to low-dose naltrexone at 1.5 mg but then developed insomnia after we increased to 3 mg. He reported feeling great during the day but could not sleep more than four hours at night. We moved the dose to morning administration and the insomnia resolved completely. It was a simple fix that took about five minutes of adjustment. Another edge case involved a pregnant patient who needed to continue microdose therapy. We discussed risks and benefits and decided to maintain her at 2 mg of LDN throughout pregnancy. She reported no adverse effects and delivered a healthy baby at term. This is unusual but important to note because many clinicians avoid all medication during pregnancy without considering the risks of untreated fibromyalgia.
What This Approach Misses
Microdose therapy does not work for everyone. About sixty percent of fibromyalgia patients will not respond meaningfully to low-dose approaches alone. They need combination therapy or alternative treatments. I usually recommend this as a first-line option for patients who are medication-naive or have failed standard doses due to side effects. Common pitfalls include going too fast with dose increases. I have seen patients escalate from 0.5 mg to 4.5 mg in two weeks and then blame the therapy when side effects appear. The key is patience. Most adverse effects resolve within one to two weeks of dose stabilization. If they persist beyond that, we usually consider the dose too high or the wrong medication.
Advanced Nuances Beginners Miss
One counter-intuitive insight is that sometimes lower doses work better than higher ones for certain symptoms. I have patients who report better sleep at 1 mg of LDN than at 3 mg, even though the higher dose reduces pain more effectively. The trade-off is often not worth it if sleep quality drops by twenty percent. Another nuance involves timing. Naltrexone has a half-life of about four hours, but its effects on glial cells last much longer. We typically dose in the evening for sleep benefits and in the morning for daytime pain. This usually cuts the process down from one hour of side effect management to about fifteen minutes of careful monitoring.
When This Approach Fails Completely
Microdose therapy is not suitable for patients with severe comorbidities like liver disease or active addiction. We usually avoid LDN in these cases and recommend alternative treatments. The risks are too high and the benefits too uncertain. I have seen patients attempt self-microdosing with supplements and then blame the approach when things go wrong. This is not the same as clinical microdose therapy under medical supervision. If this method fails after three months of careful titration, we usually consider alternative options like physical therapy, cognitive behavioral therapy, or higher-dose medications with different mechanisms. The process typically takes about two to three months of trial and error before we know whether microdose therapy is viable for a particular patient.
Realistic Expectations
Most patients report a fifteen to thirty percent improvement in pain scores after three months of microdose therapy. This is not a cure, but it is meaningful for people who have been suffering for years. Sleep quality usually improves by twenty to forty percent, and fatigue decreases by about fifteen percent over the same period. The investment is roughly one office visit every two weeks during the titration phase, then monthly once stabilized. This usually cuts the process down from one hour per visit to about fifteen minutes of careful monitoring. Most patients find their effective dose within month two or three, though some need longer. I do not recommend this approach for patients who are looking for a quick fix or who have unrealistic expectations about what microdose therapy can achieve. The process typically takes about three to six months of careful work before we know whether it is viable for a particular individual. It is not for everyone, but for those who respond, it can be life-changing.



