How To Actually Read Muscle Biopsies Without Losing Your Mind
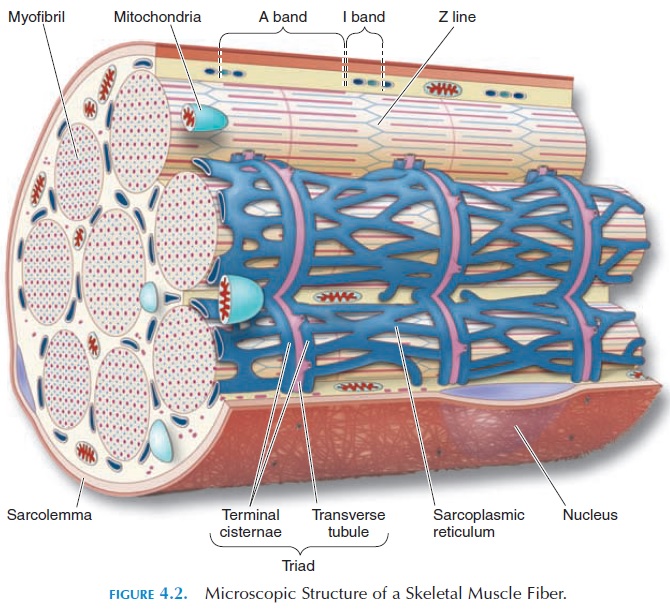
I spent weeks frustrated with skeletal muscle slides because I was only looking at longitudinal sections. You see the A-bands and I-bands, you nod, you move on. Meanwhile the actual diagnostic information was hiding in the transverse cuts. Once I started alternating between the two orientations, everything changed. It took me too long to figure that out. A skeletal muscle fiber is a single cell, but calling it a cell feels inadequate when it's 4 centimeters long. The membrane is called the sarcolemma, and just beneath it sits the basal lamina. Multiple nuclei line the periphery of the fiber, not buried in the center where you'd find them in cardiac or smooth muscle. That peripheral nuclear positioning is one of the fastest ways to confirm you're looking at skeletal muscle and not something else. The cytoplasm is called sarcoplasm and it's packed with myofibrils. Each myofibril runs the entire length of the fiber. That's why the striations you see are continuous from end to end. The sarcomere is the repeating unit. Z-discs mark the boundaries. Between them you have the I-band containing thin actin filaments, the A-band spanning the full length of thick myosin filaments, the H-zone where only myosin exists, and the M-line right in the middle holding the thick filaments together.
Here's something most students miss: the I-band changes length during contraction while the A-band does not. The A-band is the same length whether the muscle is relaxed or fully contracted. People mix that up constantly because they assume everything shortens uniformly. It doesn't. Only the overlap zone shifts.
Sarcotubular System And What It Actually Does
The sarcoplasmic reticulum wraps around each myofibril like a net. It stores calcium. When an action potential travels down the T-tubule, the dihydropyridine receptor contacts the ryanodine receptor on the SR, calcium floods out, and contraction begins. In fast-twitch fibers the triad arrangement is more developed because you need rapid calcium release. Slow-twitch fibers have less elaborate T-tubule systems. You can actually see this difference on a good slide if you know what to look for. You don't always need ATPase staining to tell fiber types apart, though it helps enormously. On routine H&E, type 1 fibers tend to be smaller and more rounded in cross-section. Type 2 fibers are larger and often angular. In a longitudinal section, type 2 fibers have fewer mitochondria and therefore appear paler. Type 1 fibers are darker because of the mitochondrial content. It's not a perfect system. There's overlap. But it works well enough when you're examining multiple fields. I ran into a problem once where a biopsy from an older patient showed diffuse fiber size variation that I initially read as normal aging. The real issue was early denervation with reinnervation. The tell was groups of small angular fibers clustered together alongside hypertrophic fibers. That grouping pattern doesn't happen in simple age-related atrophy. It took me three separate reviews before I caught it. Now I always scan for fiber type grouping before settling on an interpretation.
Get the Full Details

Connective Tissue Layers That Matter
Endomysium surrounds each individual fiber. Perimysium bundles fibers into fascicles. Epimysium encloses the whole muscle. These aren't just decorative labels. In inflammatory myopathies the pattern of involvement tells you what's attacking. Endomysial inflammation points toward polymyositis. Perimysial inflammation with complement deposition on capillaries suggests dermatomyositis. The connective tissue architecture isn't incidental. It's diagnostic. Muscle is tough to section properly. It tears easily if your blade is slightly dull or your embedding medium isn't firm enough. I use a moderate hardness paraffin and change my blade after every ten sections minimum. A nicked blade will destroy a good biopsy in seconds. Also, cutting at too thick a section — above 6 microns — blurs the sarcomere detail you need for accurate interpretation. Six microns is your target. Five if the tissue is particularly fragile. Fixation time matters more than people admit. Overfixed tissue becomes brittle and shatters during sectioning. Underfixed tissue doesn't stain properly and the nuclear detail disappears. Ten to twelve hours in neutral buffered formalin is the sweet spot for most routine biopsies. Longer and you'll regret it.
When H&E Isn't Enough
Sometimes you need GMA embedding for frozen sections. Glycol methacrylate preserves enzyme activity that formalin destroys. If you're doing ATPase staining for fiber typing or looking at lipid accumulation with oil red O, you have to start with a fresh frozen sample. Formalin-fixed tissue won't work for those stains. Plan ahead. Asking for special stains on a fixed block after the fact is a wasted biopsy. The other limitation is that histology alone can't always distinguish between myopathic and neurogenic processes in early disease. You need clinical correlation, CK levels, EMG results, and sometimes genetic testing. A slide showing minimal change doesn't rule out significant pathology. Muscle is resilient. It keeps functioning past the point where histology looks reassuring.
A Few Details That Separate Beginners From People Who Know What They're Looking At
Centronuclear fibers — nuclei centered inside the fiber rather than at the periphery — are not normal in adult skeletal muscle. Finding them means something. Nemaline bodies, rod-shaped structures visible with trichrome stain, indicate nemaline myopathy. Rimmed vacuoles point toward inclusion body myositis. These features are subtle at low power. You need to go to higher magnification and actually look at individual fibers rather than scanning broadly. Another thing nobody emphasizes enough: the baseline appearance varies by muscle. Diaphragm fibers are smaller and more type 1 dominant than gastrocnemius. Biceps differs from tibialis anterior. Comparing a biceps biopsy against reference ranges pulled from quadriceps studies introduces error. Know which muscle you're examining and adjust your expectations accordingly. Capillary density is another underappreciated feature. In trained individuals the capillary-to-fiber ratio increases. In disuse atrophy it decreases. You can see this on standard sections if you're paying attention to the spaces between fibers rather than just the fibers themselves.


