Walking Through a Bone Section Under the Microscope
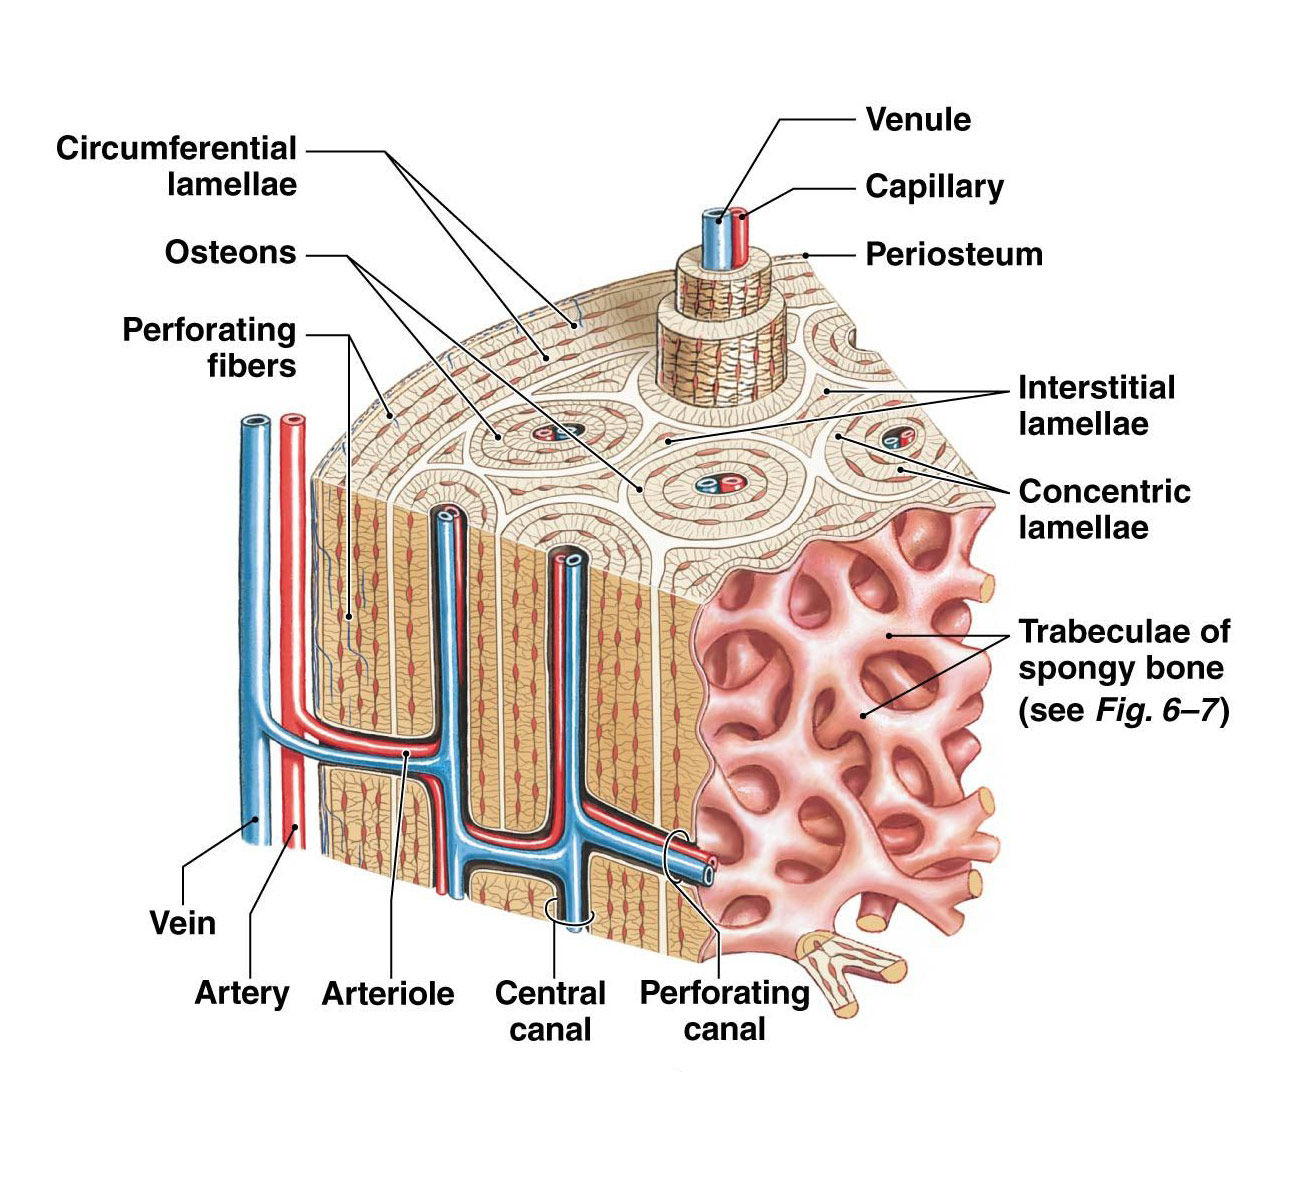
I spent a decade running bone histology in a pathology lab, mostly decalcified ground sections for orthopedic research. You punch out a 5-millimeter ring from a femur, embed it in methyl methacrylate, and cut at 3 microns. Most of those sections look like a cracked pavement from above. The structure is boring until you actually need to measure something, then every little detail matters. The Microscopic Structure Of Compact Bone you see on a slide is not random. It is organized into repeating units called osteons, each one a cylinder running more or less parallel to the long axis of the bone. An osteon consists of concentric layers of mineralized matrix called lamellae, with a central canal in the middle that contains capillaries and nerve fibers. The canals are roughly 50 to 100 micrometers in diameter, which means you need a decent objective just to see the contents clearly.
What You Actually See When Sectioning Compactly
Each osteon contains osteocytes trapped inside small spaces called lacunae, which sit between the lamellae like raisins in a cake. From each lacuna, tiny channels called canaliculi radiate outward, forming a network that connects neighboring cells. These canaliculi are about 0.1 to 0.5 micrometers wide, far below the resolution of light microscopy unless you stain specifically for them. In a standard hematoxylin and eosin stain on a ground section, you mostly see the lacunae as dark spots and the lamellae as faint concentric rings. The canaliculi network only becomes visible with special preparations or under higher magnification. Between the complete osteons, you find remnants of older, partially resorbed osteons called interstitial lamellae. They fill the gaps and look like puzzle pieces that do not quite fit. At the periphery of the bone, just beneath the periosteum on the outside and surrounding the medullary cavity on the inside, you find circumferential lamellae that wrap around the entire shaft. These are continuous sheets rather than discrete osteons, and they provide additional structural support without the same vascular organization. Connecting the Haversian canals of adjacent osteons are perpendicular channels called Volkmann's canals, also known as perforating canals. They run transversely or obliquely through the compact bone, allowing blood vessels and nerves to pass from the periosteal surface into the deeper osteonal systems. Without Volkmann's canals, the central canals would be isolated dead ends, and the bone tissue would starve. In cross-section, these canals appear as irregular spaces scattered between osteons, often carrying larger vessels than the central canals themselves.
How It Actually Works in Practice
The osteonal structure is not merely decorative. It provides a balance between strength and metabolic activity that allows bone to remodel continuously throughout life. Each osteon represents a unit of remodeling, where osteoclasts first create a cutting cone that resorbs old matrix, followed by osteoblasts that lay down new lamellae in a sealing cone. The entire process takes about 3 to 6 months in human cortical bone, and the resulting osteon can be identified decades later as a permanent record of past mechanical stress and repair. One thing beginners consistently miss is that osteons are not perfectly cylindrical. They can be tortuous, branching, and overlapping, especially in regions of high mechanical stress like the femoral shaft. When you section through such a region at an angle, you do not see clean circular osteons but rather elongated or irregular profiles that can confuse even experienced readers. The degree of tortuosity varies with age, loading history, and pathological conditions, so you need to consider the anatomical context when interpreting any single section. I once spent two weeks trying to quantify osteon density in a set of femoral sections from elderly donors, only to realize that my sectioning angle was systematically biased because I was cutting strictly perpendicular to what I assumed was the long axis. The femur is not straight, and the osteons curve along the shaft, so my measurements were consistently overestimating the true cross-sectional osteon count by about 15 to 20 percent. I ended up resectioning at multiple angles and averaging the results, which added about a week to the project but produced data I could actually publish. If you are doing similar work, measure the local curvature of the bone surface before you commit to a single sectioning plane.
Get the Full Details

Where This Approach Fails and What to Do Instead
The traditional histological approach to studying compact bone has significant limitations, especially when you need three-dimensional information or when the bone is heavily osteoporotic. Decalcification during processing can distort the lamellar architecture, and ground section preparation destroys the cellular details that are visible in undecalcified plastic sections. If you need to see osteocyte viability or lacunar morphology, you should use undecalcified sections cut with a diamond saw and stained with toluidine blue or fluorescent labels, which usually preserves cellular detail but requires special equipment and takes about twice as long to process. Micro-computed tomography, or micro-CT, has largely replaced traditional histology for many applications because it provides three-dimensional structural information non-destructively. You can reconstruct the entire osteonal network from a single sample and measure parameters like osteon size, density, and orientation with sub-micrometer resolution. However, micro-CT cannot visualize cellular details or distinguish between viable and dead osteocytes, and the equipment costs about 500,000 to 2 million dollars depending on the model. If you need both structural and cellular information, you should combine micro-CT with traditional histology, using the CT data to guide your sectioning and the histology to validate your findings. This combined approach usually takes about 2 to 3 weeks per sample but produces data that neither method can generate alone. The biggest bottleneck in compact bone histology is not the staining or the microscopy but the sample preparation, which usually accounts for 70 to 80 percent of the total processing time. Fixation in 10 percent neutral buffered formalin for 2 to 4 weeks is standard, but thicker samples require longer fixation times, and over-fixation can make the tissue brittle and difficult to section. Decalcification in 14 percent EDTA at pH 7.4 takes about 4 to 8 weeks for adult human cortical bone, during which time the sample must be kept agitated and the solution changed weekly to maintain efficiency. If you are processing a large batch of samples, plan for at least 12 weeks from fixation to finished section, and do not attempt to accelerate the process with stronger acids or higher temperatures, which will damage the matrix architecture beyond recognition.
Another common pitfall is assuming that osteon density is a reliable indicator of bone health without considering the anatomical location and the patient's age. Osteon density decreases with age in the human femur, dropping from about 45 to 55 osteons per square millimeter in young adults to 25 to 35 in elderly individuals, but this decrease is not uniform across the cross-section. The outer third of the cortex retains higher osteon density than the inner third, and pathological conditions like osteoporosis affect the two regions differently. If you are comparing groups, always section at standardized anatomical levels and report the exact location, because variability in sampling can introduce errors larger than any true biological difference you are trying to detect. The most painful lesson I learned is that bone is anisotropic, meaning its mechanical properties vary with direction, and this anisotropy is reflected in the osteonal architecture. Osteons are oriented preferentially along the principal stress axes, so in the femoral shaft they run nearly parallel to the long axis, but in the femoral neck they curve to resist bending and torsional loads. If you are studying bone mechanics, you cannot assume that a single cross-section represents the entire structural organization, and you should section at multiple orientations and correlate the histological findings with mechanical testing data. This integrated approach usually takes about 4 to 6 weeks per specimen but produces insights that neither approach can generate alone. I wish someone had told me this before I wasted three months on a project that produced data I could not interpret correctly.