What Actually Happens When You Cross 40
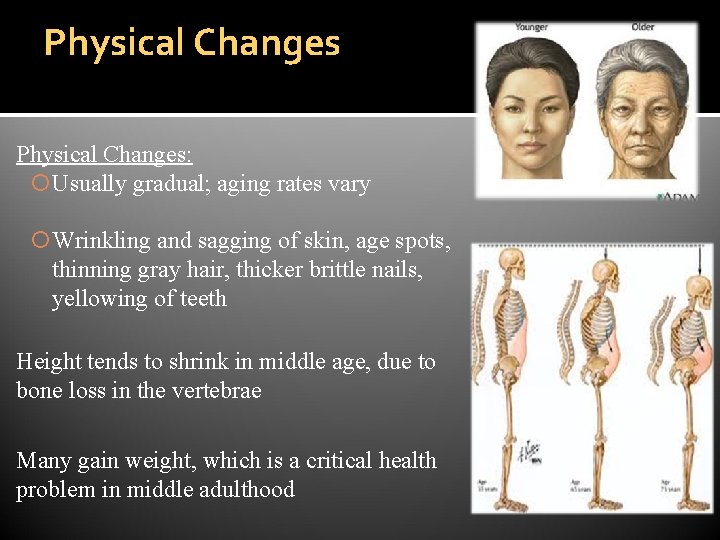
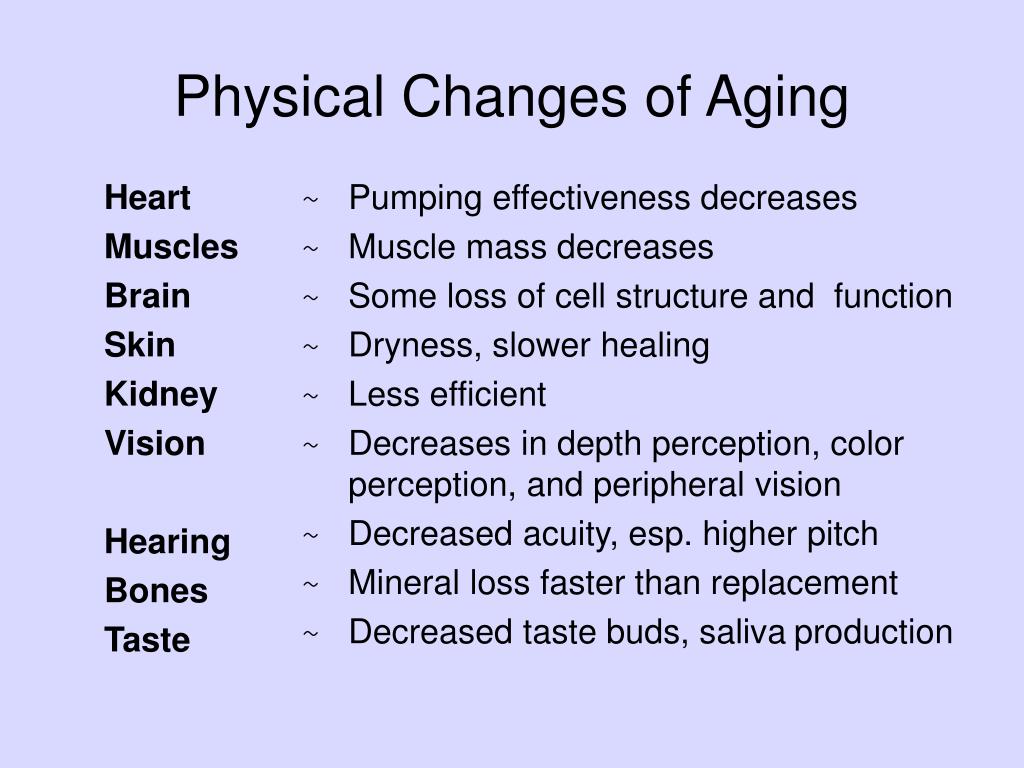
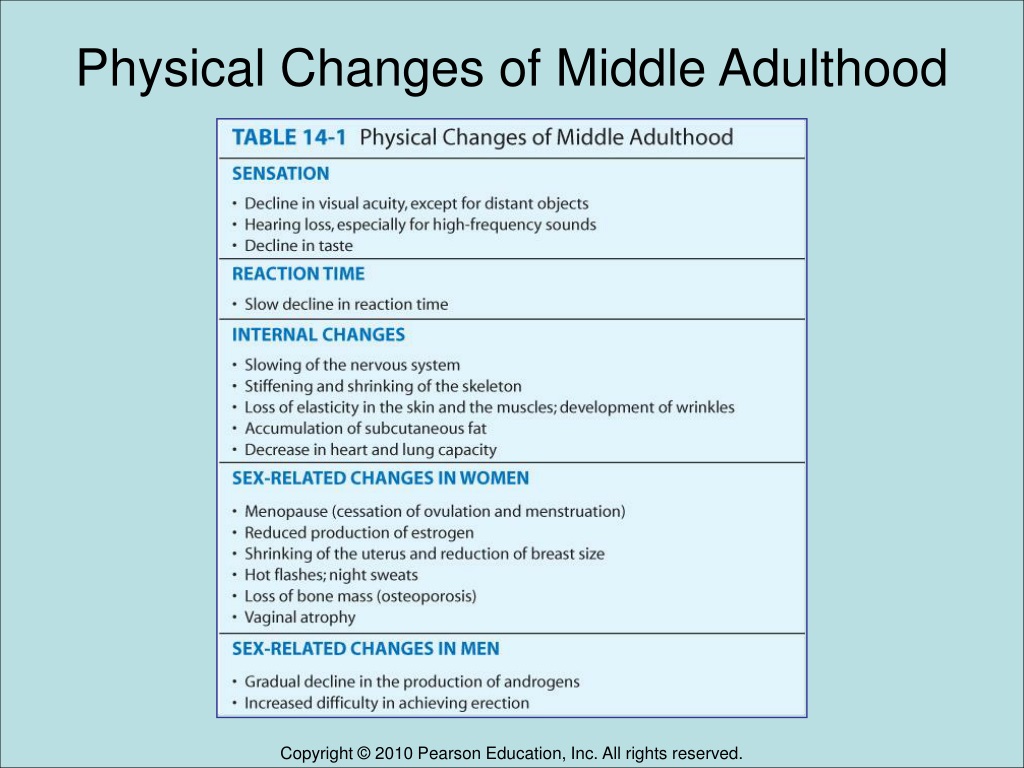
It is not a single event. It is a series of small adjustments that add up over several years, and most people notice them too late to do anything about the early stages. The term covers a cluster of hormonal, metabolic, and structural shifts that hit men and women differently but overlap in ways most general articles skip. For women, the perimenopausal window typically begins between 40 and 44, and estrogen fluctuations cause sleep disruption, joint stiffness, and a redistribution of fat from the hips toward the visceral area. For men, testosterone declines roughly one percent per year after 30, which means a 45-year-old man has already lost about 15 percent of his peak free testosterone without necessarily feeling dramatically different. The insidious part is how slowly it happens. Your body adapts day by day until one morning you realize your recovery from a workout takes three days instead of one. I learned this the hard way in my late forties. I kept training at the same volume I had managed at 35, and my resting heart rate climbed from 58 to 72 over six months. No amount of stretching or foam rolling fixed it. The fix was simple but counter to everything I had been told: I dropped the volume by forty percent and shifted from heavy compound lifts to moderate load work with longer rest intervals. Within eight weeks my resting heart rate dropped back to 61. The training habit stayed the same. The stimulus just needed recalibration for a body that no longer recovered on youth metabolism alone.
The Metabolic Shift Nobody Talks About
Basal metabolic rate drops about five to seven percent between ages 40 and 60, but that number understates the problem. The real issue is the decline in non-exercise activity thermogenesis, commonly called NEAT. Most people unknowingly move less throughout the day as they age, and that silent reduction accounts for more weight gain than any gym session can undo. A sedentary office worker in their forties might burn 200 to 400 fewer calories per day from reduced fidgeting, standing, and general movement without noticing. The scale creeps up a pound or two every six months, and the math is not dramatic in isolation but compounds relentlessly. Hunger signals also change. Leptin resistance increases with age, meaning the hormone that tells your brain you are full becomes less effective. You can eat the same amount as you did at thirty and still feel hungry two hours later. This is not a willpower problem. It is a hormonal one, and the workaround is protein-first meal sequencing. Eating 30 to 40 grams of protein before carbohydrates blunts the hunger spike and reduces overall calorie intake by roughly 15 to 20 percent without calorie counting. I track this with a simple food scale app, and it has been the single most effective dietary intervention I have used.
Sleep Architecture Degrades
Deep sleep, the stage responsible for growth hormone release and tissue repair, decreases substantially after 40. Many people in this age bracket rarely reach stage N3 sleep at all. The result is waking up unfresh even after eight hours in bed. Alcohol is a major culprit because it fragments REM sleep and suppresses deep sleep, and its impact worsens with age. A single glass of wine at 30 might leave you fine. At 45, the same glass can reduce deep sleep by up to 30 percent. The most practical intervention is temperature control. Keeping the bedroom between 65 and 67 degrees Fahrenheit aligns with the body's natural core temperature drop during sleep onset. Combine that with consistent sleep and wake times, and most people see measurable improvement in sleep quality within two weeks. Morning sunlight exposure for ten to fifteen minutes also helps reset circadian rhythm, especially if you work indoors all day.
Get the Full Details
Muscle Loss and Joint Wear
Sarcopenia, the progressive loss of skeletal muscle mass, accelerates after 40 if resistance training stops. The average person loses about one percent of muscle mass per year after 40, which translates to roughly ten percent over a decade. This is not reversible with cardio alone. Strength training is the only proven method to halt and partially reverse it, but the approach must change. Heavy maximal lifting that worked in your thirties becomes a joint liability. Moderate loads between 60 and 75 percent of your one-rep max, taken to controlled failure with slower eccentrics, produce similar hypertrophic stimulus with significantly less wear on tendons and ligaments. Joint stiffness is another issue that gets dismissed as normal aging when it is often just deconditioning. Cartilage relies on movement for nutrient distribution because it has no blood supply. If you stop moving through full ranges of motion, the cartilage degrades faster. Daily mobility work for the hips, shoulders, and ankles takes about twelve minutes and prevents the kind of stiffness that leads to chronic pain decades later.
Cardiovascular Risk Increases Asymmetrically
Arterial stiffness increases with age, and blood pressure trends upward even in people who never smoked and maintain a healthy weight. This is partly due to collagen cross-linking in the vessel walls, a process accelerated by sustained high blood sugar and chronic inflammation. The standard advice to "just exercise more" misses the nuance. Zone 2 cardiovascular training, performed at a pace where you can hold a conversation but with slight effort, improves endothelial function and arterial compliance in ways that higher-intensity work does not match. Thirty minutes three to four times per week at a heart rate of 120 to 140 beats per minute produces measurable improvements in vascular health within eight to twelve weeks. Blood work is essential because many of these changes are invisible until they become problems. A standard lipid panel and fasting glucose test should be supplemented with HbA1c, hs-CRP for inflammation, and a full thyroid panel. These cost roughly $150 to $300 out of pocket without insurance and provide data that a annual physical exam rarely covers thoroughly enough to catch early metabolic shifts.
What Does Not Work
Supplements marketed for middle age vitality are largely unproven. Testosterone boosters sold over the counter contain ingredients with minimal clinical evidence and can interact with medications. DHEA supplementation without medical supervision carries risks including hormonal imbalance and liver strain. The only supplement with consistent evidence for this age group is vitamin D if you are deficient, which affects roughly 40 percent of adults over 40 in northern latitudes. Creatine monohydrate at five grams daily has solid evidence for preserving muscle mass and cognitive function, but it is not a miracle compound and works best alongside resistance training. The biggest mistake people make is treating symptoms in isolation. Fatigue, weight gain, poor sleep, and brain fog each get addressed separately with different solutions when they are often connected through the same underlying mechanism: hormonal shift and reduced recovery capacity. Fixing sleep and adjusting training volume usually improves three of those four symptoms simultaneously. Trying to supplement or diet your way out of each one individually wastes time and money. Monitoring progress matters more than most people expect. Taking monthly photos, tracking resting heart rate, and logging strength numbers creates a data trail that reveals trends well before the mirror does. Without objective tracking, it is easy to convince yourself nothing is changing when subtle improvements are happening or to miss a negative trend until it becomes obvious.