The actual practice of working with the body and attention together
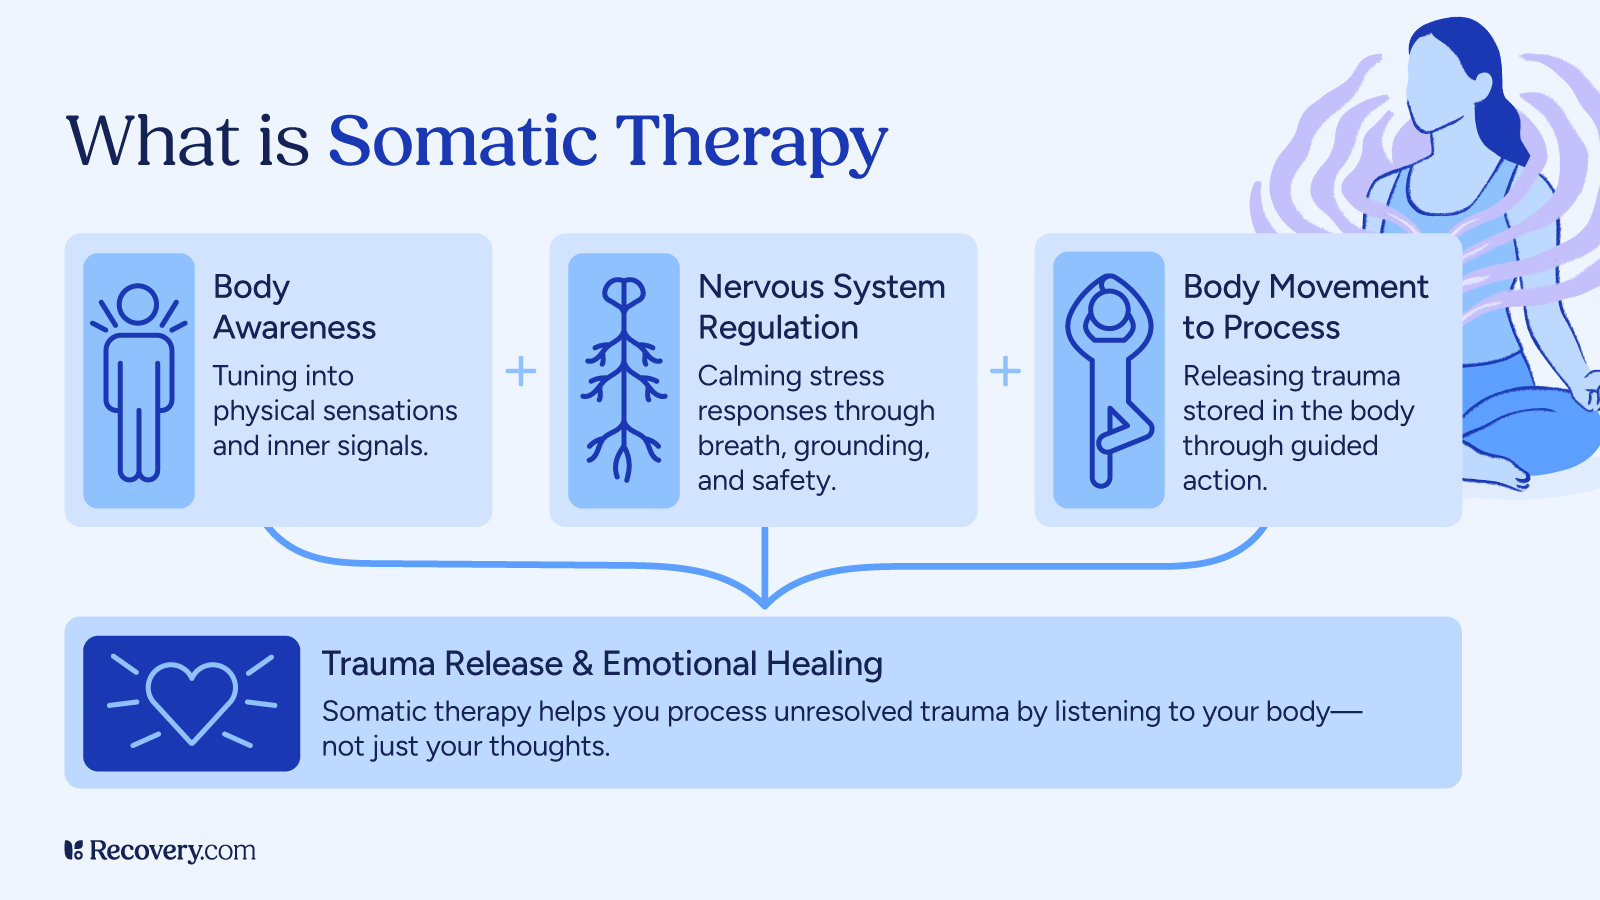
Most people I see trying Mindfulness Based Somatic Therapy for the first time make the same mistake. They treat the mindfulness part and the somatic part as two separate steps they perform one after the other. That doesn't work the way the method is designed. The whole point is that awareness and bodily sensation are happening simultaneously, and collapsing that into a checklist defeats the mechanism. Here is how a session actually unfolds when it is done correctly. You begin with a brief orientation to the nervous system state. Not a lecture. A quick check-in. Where is the breath sitting? Are the shoulders elevated without the person noticing? Is there tension in the jaw, the hands, the gut? This takes about ninety seconds. Then you guide sustained, non-judgmental attention toward a specific body region where discomfort or numbness is present. The instruction is always to stay with the sensation, not to analyze it or change it. Most people will feel an impulse to move, breathe differently, or cognitively reframe the experience within forty-five seconds. The work is simply to notice that impulse and return to the original anchor point. This is grounded in polyvagal theory and somatic experiencing protocols developed by Peter Levine and later adapted by researchers like Deb Dana. The theory holds that trauma and chronic stress get stuck in the autonomic nervous system as incomplete survival responses. Mindfulness provides the observational distance needed to process those stuck responses without becoming overwhelmed by them.
How Mindfulness Based Somatic Therapy actually integrates both components
The integration is the hard part. Pure mindfulness meditation trains attention on the breath or thoughts. Pure somatic therapy trains awareness on bodily sensations and movement impulses. MBST does both at once, which means the client must hold a dual awareness: feeling the sensation directly while simultaneously observing the feeling without getting pulled into narrative. That dual register is what creates the therapeutic shift. It is not relaxation. It is regulated awareness. I have watched people sit through twelve weeks of traditional talk therapy and make less progress than someone who did eight weeks of properly facilitated MBST. The reason is straightforward. Talk therapy operates in the prefrontal cortex. MBST operates where the trauma memory is actually stored, which is deeper in the limbic system and brainstem. You cannot reason a fight-or-flight response out of existence. You have to complete the physiological loop that got interrupted. But I also need to be clear about where this breaks down. MBST is not appropriate for clients in active psychosis, for people with severe dissociative disorders who have not yet developed basic grounding skills, or for anyone whose nervous system is so chronically dysregulated that even mild body awareness triggers flashbacks. I worked with a client last year who had a diagnosis of CPTSD and a history of prolonged captivity trauma. We attempted a standard body scan exercise during session four. Within sixty seconds she was hyperventilating and completely dissociated. She could not hear my voice. The scan had gone too deep, too fast.
The workaround was immediate. I stopped the exercise entirely and switched to external orienting. I had her name five objects she could see in the room, describe their texture, their color, their position relative to her body. This is a standard DBT distress tolerance skill but it works here because it pulls attention outward and anchors the vagus nerve through orienting responses. Once her respiration normalized, which took about three minutes, we returned to a much shorter and more superficial body check. We spent the next six sessions only doing that level of work before any deeper somatic exploration. It added weeks to the timeline but it prevented a setback that would have set us back months. Another thing nobody warns you about is the titration concept. In somatic work, you are supposed to stay within what Roger Callahan and Levine call the "window of tolerance." That means the sensation should be noticeable but not overwhelming. Most facilitators I have observed skip this entirely because they assume clients will self-regulate. They do not. Without explicit titration guidance, people either push through distress they cannot process or they avoid the sensation entirely and the session becomes ineffective. The fix is simple but requires discipline. Pause the exercise the moment the client reports the sensation rising above a four out of ten on a subjective units of distress scale. Shift focus to a neutral body area. Return only when the rating drops below two. There is also a misconception that breathwork is a core component. It is not. Breath awareness is used occasionally, but unguided breath retention or rapid breathing techniques can destabilize clients with panic disorder or a history of seizure activity. If you are facilitating this modality, you need to screen for those conditions before introducing any breath-focused work. I once had a client who had never disclosed a family history of seizures. A simple diaphragmatic breathing exercise triggered a tonic-clonic event. She was fine afterward, but the liability and the ethical breach were significant. That screening question should be mandatory in your intake protocol.
Get the Full Details

The research base is growing but it is still thin compared to CBT or EMDR. A 2023 meta-analysis in the Journal of Trauma & Dissociation found moderate effect sizes for MBST in reducing PTSD symptoms, with stronger outcomes for single-incident trauma than for complex trauma. The effect size dropped from d=0.68 to d=0.41 when the trauma was chronic and interpersonal. That matters because the majority of people seeking this therapy fall into the complex trauma category. You need to manage expectations accordingly. If you are looking to learn this yourself rather than seek a practitioner, there are a few resources. The Somatic Experiencing website offers a practitioner directory and some self-study materials, though the full curriculum requires in-person training. Deb Dana's work on polyvagal theory has companion workbooks that are accessible. The Trauma Resiliency Institute also offers online courses with recorded meditations. None of these replace working with a trained clinician, especially if you have a trauma history. What usually makes or breaks this approach is the quality of the therapist's own somatic attunement. You cannot guide someone through body awareness if you have not developed your own. I spent two years doing my own somatic work before I felt competent enough to facilitate sessions for others. The shortcut of jumping in without that foundation tends to produce sessions that feel either too clinical or too vague to be useful.
For people who want a free starting point, try this. Sit somewhere you will not be disturbed for ten minutes. Close your eyes if that feels safe. Bring attention to your hands. Notice temperature, pressure, tingling, numbness. Do not try to change anything. Just observe. When your mind drifts to a thought, notice that too, and gently return to the hands. That is the basic structure. Everything else builds from there.