The Way People Actually Use This Test in Real Clinics
The Mini Mental State Exam is a 30-point paper-and-pencil screen for cognitive impairment. Folks use it everywhere from memory clinics to primary care offices to pre-op clearance. It takes roughly 5 to 10 minutes if the patient is cooperative and the examiner knows what they're doing. The scoring is straightforward, but the trick is knowing how to administer it without accidentally biasing the result. I used to think the MMSE was just something you read off a sheet and move on. Then I spent a couple years actually doing them in a busy geriatric clinic. A lot of things changed in that time. Let's talk about how the test actually works when you are in the room with someone who might not understand what is happening.
Mini Mental State Exam: What It Measures and How to Administer It
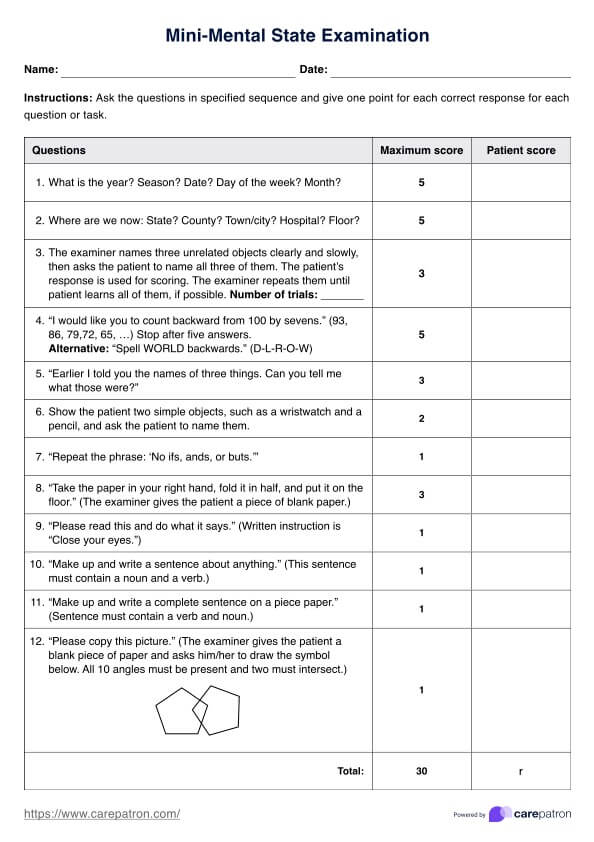
The exam covers orientation, registration, attention and calculation, recall, language, and visuospatial skills. The maximum score is 30. A score below 24 generally suggests some degree of cognitive impairment, though the cutoff shifts depending on education level and other factors. Here is the order most people follow: Orientational questions come first. Ask the person their age, the current year, season, month, date, day of week, where you are, and which floor or room you are in. This usually accounts for about 10 points total across the different categories.
Registration is simple. Name three unrelated objects. Have them repeat all three. Record whether they get all three correct on the first try. This is a very small part of the overall score, but it tells you something about immediate memory holding capacity. Attention and calculation is where things start getting tricky. The classic version asks the person to count backward from 100 by sevens. If that frustrates the patient or they struggle with math for other reasons, you can substitute spelling "WORLD" backward. Both versions are valid. Just pick one and stick with it for consistency. Recall comes next. Ask them to repeat the three objects from the registration phase. If they did not learn them properly during registration because they were distracted, the recall score will be low even though their memory may be fine. This is a common testing artifact people miss.
Get the Full Details

Language and visuospatial items include naming two common objects, following a three-stage verbal command, reading and following a written command, writing a sentence, and copying a intersecting pentagon. The clock-drawing variation sometimes replaces the pentagon copy. The whole thing should feel conversational, not like an interrogation. I have seen examiners rush through these steps in under three minutes, which ruins the validity. You want to move at a pace that lets the patient engage with each item without feeling pressured. There is one thing that always comes up that textbooks do not really address clearly.
A Specific Problem I Ran Into and How I Fixed It
Early in my practice I was administering the MMSE to a 78-year-old man who scored 23. I flagged him for further evaluation, but then I looked more closely at his errors. He missed points on the attention section because he could not hear well, and he missed a language item because the command "Take this paper in your left hand and fold it in half" was confusing when he had mild arthritis that made folding difficult. His actual cognitive function was probably normal. The workaround was to adjust the administration. I repeated instructions more slowly. For the hearing issue, I moved closer and reduced background noise. For the motor component, I accepted a rough fold rather than a precise one. His adjusted score came back at 27, which was consistent with his baseline. This kind of recalibration happens more often than people expect, especially with elderly patients who have sensory or motor comorbidities. I started making notes on the form about any accommodations I gave during administration. That way if someone else reviews the score later, they know the context.
Counter-Intuitive Things About Scoring
Most beginners treat the MMSE as a blunt screening tool. It is not that simple. One thing people get wrong is the education adjustment. A cutoff of 24 is standard for someone with at least a high school education. But for someone with an eighth-grade education or less, a cutoff of 20 or 21 is more appropriate. Using the same cutoff for everyone inflates false positives in the less-educated population. I saw this repeatedly. Patients would score in the 22-to-23 range and look impaired, but when you adjusted for education they were actually within normal limits. Another thing is that the MMSE is heavily skewed toward language and orientation. It does not assess executive function very well. Someone with early frontal lobe pathology might score perfectly fine on a standard MMSE despite having significant functional impairment. If you suspect executive dysfunction, the MMSE alone will not catch it. You need something like the Trail Making Test or the Executive Interview.
Also, depression can lower MMSE scores by a few points without any actual neurodegenerative process. Pseudodementia is a real thing. A depressed elderly patient may struggle with attention and concentration, which tanks their score, but their underlying cognition is intact. Screening for depression should happen alongside the cognitive screen, not after. There is also a floor effect to consider. In moderate to severe dementia, the MMSE loses sensitivity because patients are already scoring so low that small changes do not show up. The Mini-Cog or the Addenbrooke's Cognitive Examination work better in those populations for tracking progression.
Where to Get a Copy
The original MMSE was developed by Marshal Folstein and colleagues at Johns Hopkins in 1975. The test itself is copyrighted and requires a license for commercial use. If you are using it in a clinical setting for patient care, you need to obtain it through the official publisher. The Psychological Assessment Resources website sells the official form and training materials. For academic or research purposes, there may be different licensing options. Check with your institution's research compliance office before distributing copies to participants. Using an unlicensed version in a published study can cause problems. In many community health settings and non-clinical screenings, you can find free versions online that are adapted for educational use, but those are not the official instrument and may not have the same psychometric properties validated in the literature.
Practical Tips That Actually Matter
First, establish rapport before starting. I spend about two minutes on casual conversation. This reduces anxiety and gives me a baseline sense of how the person communicates under normal conditions. Second, always ask about sensory deficits at the beginning. Hearing aids should be in place. Glasses should be available. If a patient cannot see or hear properly, the score is useless and you should reschedule. Third, do not help the patient during the test. If they make an error, move on. Correcting them or prompting them contaminates the result. The MMSE is supposed to measure what the person can do independently.

Fourth, document everything. Not just the score. Note the setting, the patient's alertness, any distractions, accommodations given, and the patient's own comments about their memory or confusion. Those qualitative observations are often more useful than the number on the page. Fifth, remember the MMSE is a screener, not a diagnosis. A low score does not mean dementia. It means you need to investigate further with labs, imaging, and possibly neuropsychological testing. I have seen patients with B12 deficiency, hypothyroidism, normal pressure hydrocephalus, and medication side effects all present with low MMSE scores that resolved once the underlying cause was treated. There are newer tools that some clinicians prefer now. The MoCA is more sensitive to mild cognitive impairment and picks up executive dysfunction better. The SLUMS test is another option that has a built-in education adjustment. Depending on your patient population, one of these might be more appropriate than the MMSE.
The MMSE remains widely used because it is brief, familiar to most clinicians, and quick to score. It has real limitations, but it is still a reasonable first step when you are concerned about cognitive change and need a structured way to document it.


