Scoring the Mini Mental State Examination Without Going Crazy
The MMSE is a 30-point screening tool. It tests orientation, registration, attention and calculation, recall, language, and visuospatial ability. Most people know the basics. What they don't always understand is how to actually administer it consistently, or why the online versions keep creating more problems than they solve. I've been administering this for over a decade across different settings. The test itself is straightforward when you know what you're doing. The real difficulty comes from the edge cases that pop up in actual practice.
Mini Mental State Examination Mmse Online
There are dozens of websites offering free MMSE downloads and online scoring. Some are legitimate. Most are not. I'll get to how to spot the difference and how to use them properly. But first, let's talk about what the test actually measures and how to administer it in a way that produces usable data instead of a number that looks good on paper but means nothing clinically. The standard administration takes about ten to fifteen minutes. A trained examiner should read each item verbatim, score according to the official rubric, and record responses in real time. The original 1975 version by Folstein is in the public domain, which is why you'll find it everywhere. However, the public domain status doesn't mean any version you find online is accurate. I've seen modified versions with altered scoring that shift the interpretation entirely. Always verify against a primary source.
How to Administer It Correctly
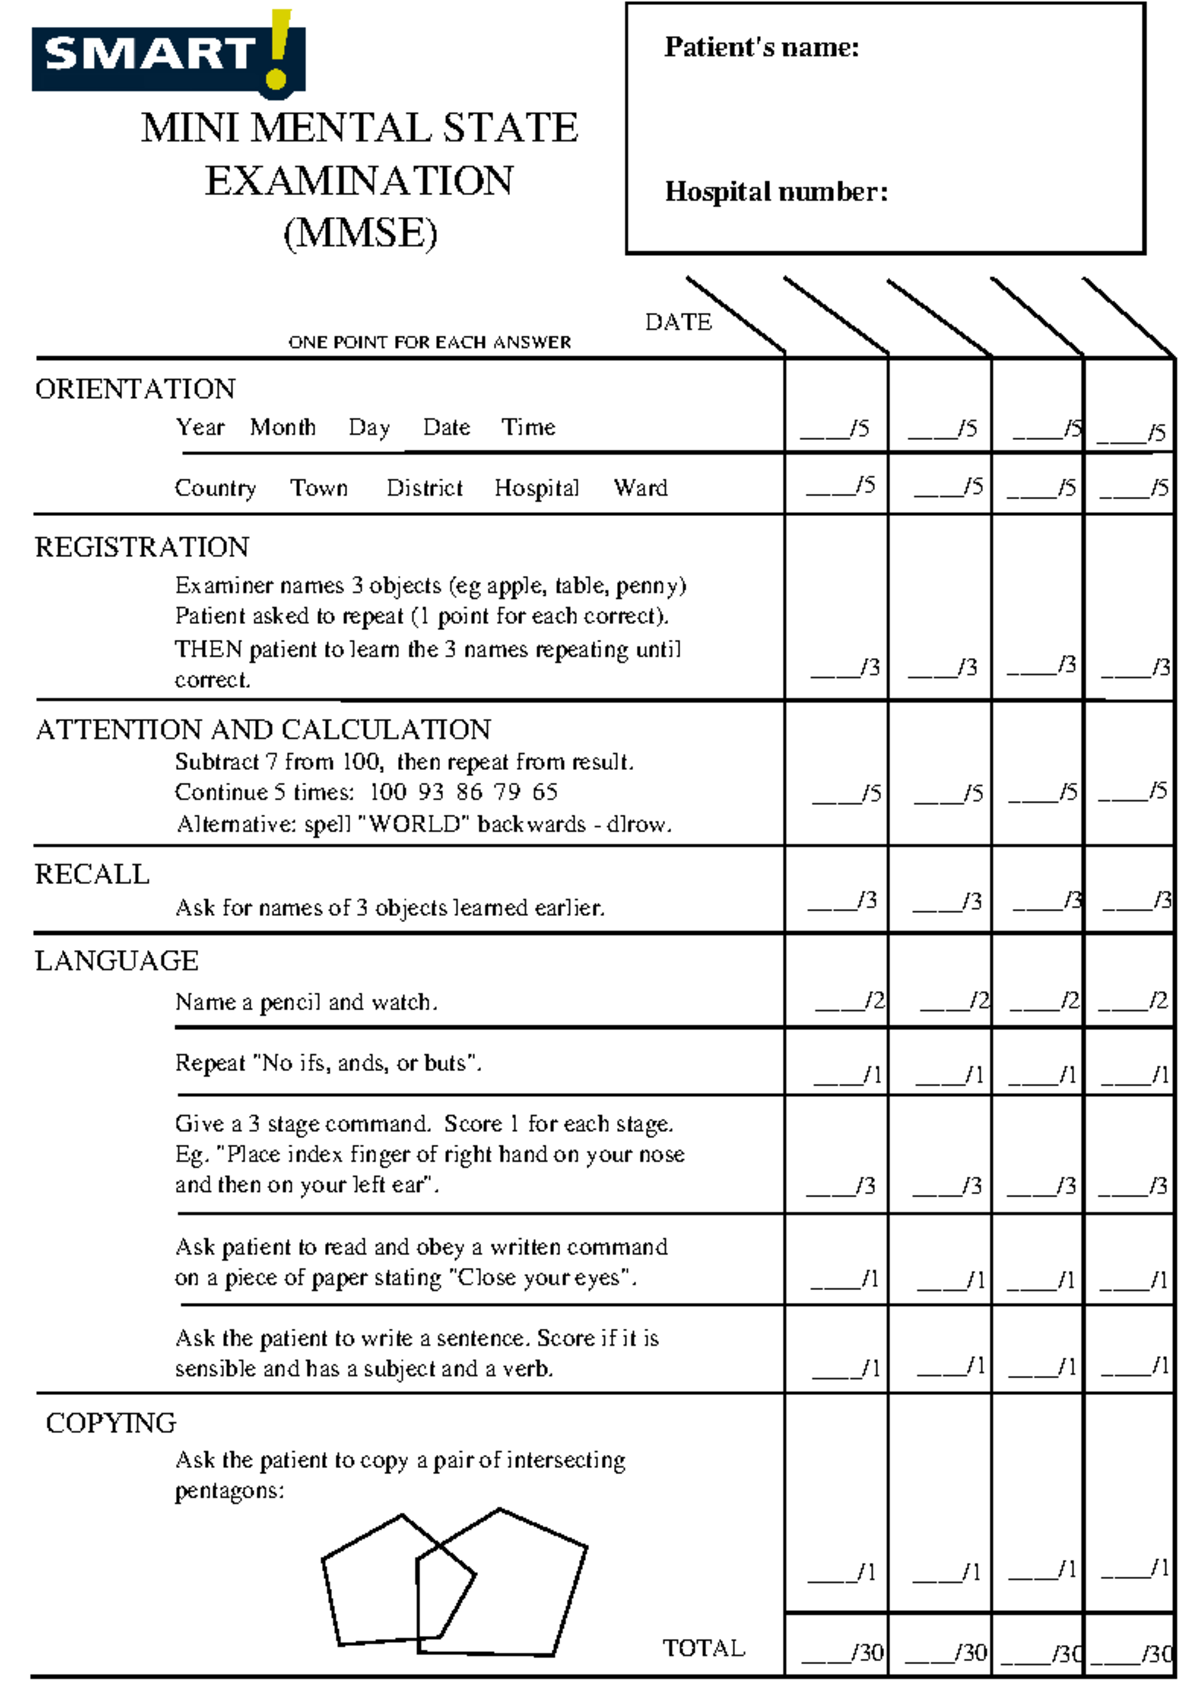
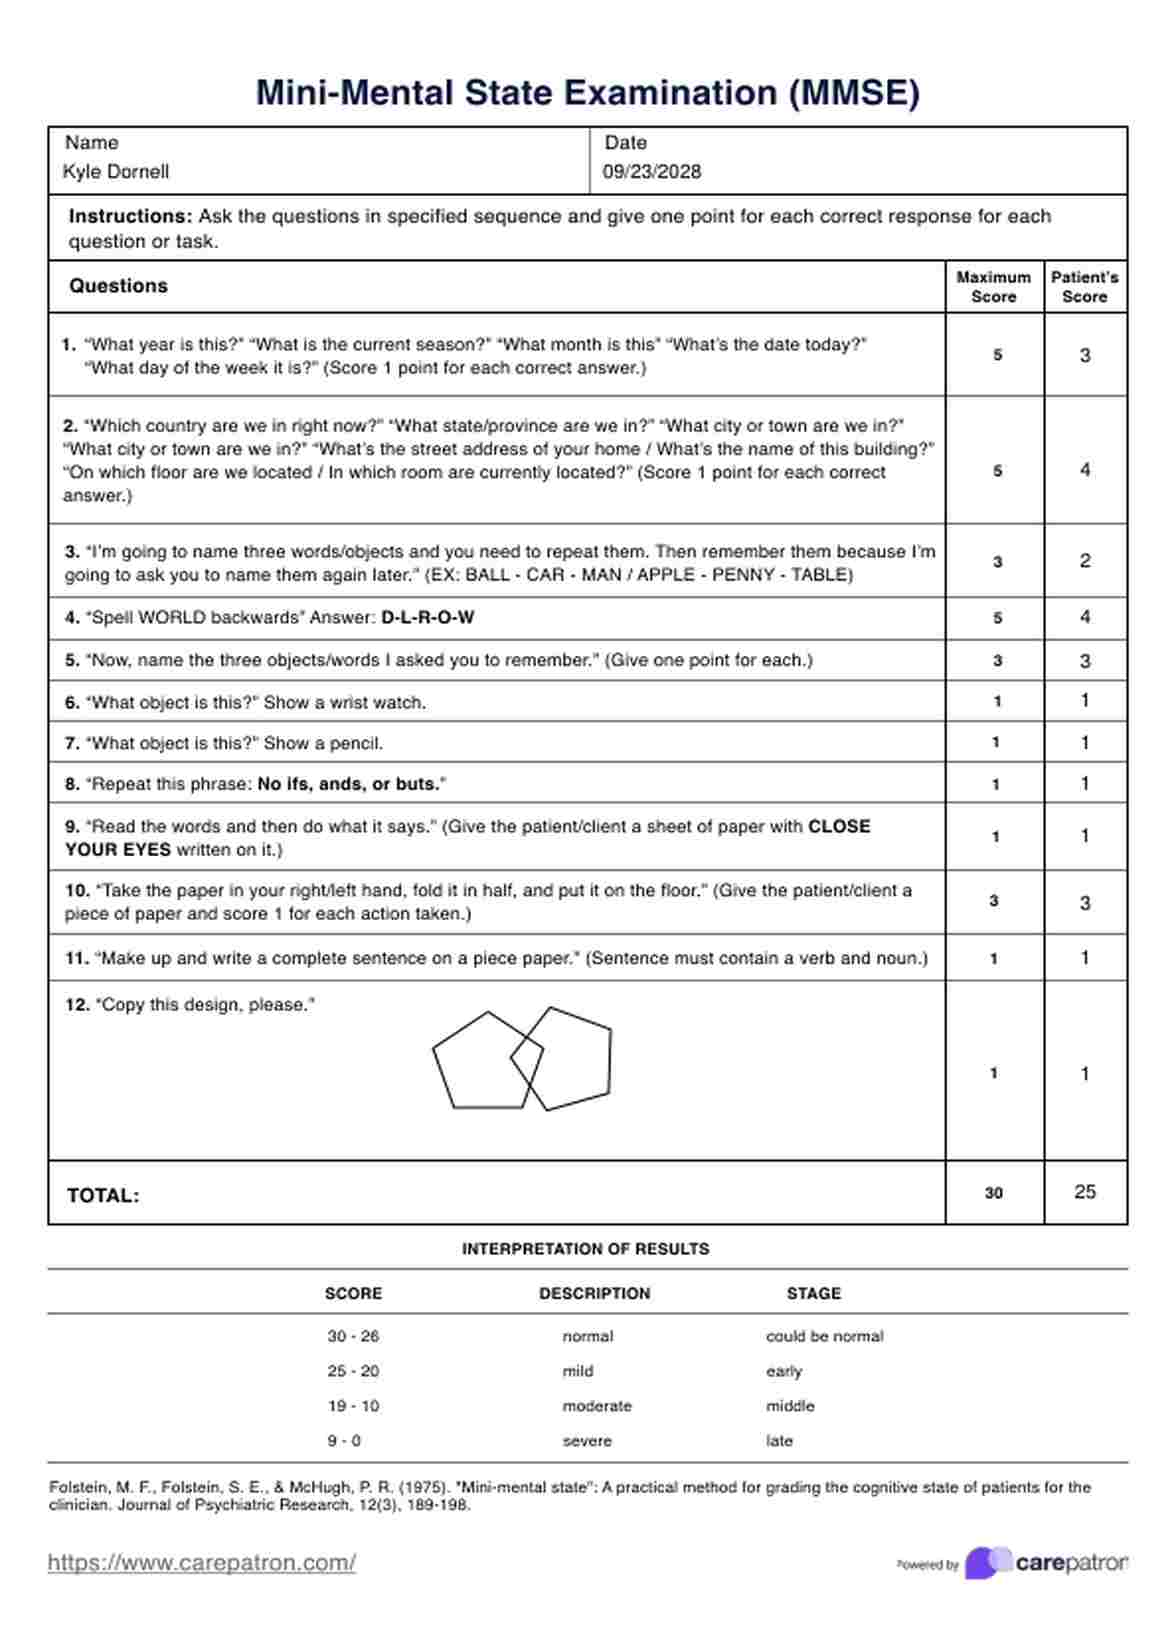
Start with orientation. Ask for the year, season, month, date, and day of the week. Then proceed to registration: name three objects clearly and ask the patient to repeat them. Immediately test attention and calculation using serial sevens. Subtract seven from 100, then keep subtracting seven until they reach zero or make six consecutive errors. This part is where most examiners lose accuracy. The scoring criteria matter here. A response of "93" gets one point. "86" gets another. If the patient hesitates or asks for clarification, note it but continue scoring only the final answer given. Recall comes next. After a distraction period, ask the patient to remember the three objects from registration. Then move to language tasks: name a watch and a pencil, follow a three-stage command, read and obey a written command, write a sentence, and copy a intersecting pentagon. Each item has a specific scoring rubric. The pentagon drawing alone accounts for one point, but the accuracy matters more than completion. An examiner recently asked me to review a case where the patient scored full marks on the drawing but had severe aphasia on the language items. The composite score looked fine. The clinical picture was completely missed.
Get the Full Details

A Specific Problem I Encountered
About three years ago, I was using an online MMSE platform with a caregiver who reported difficulty with serial sevens. The digital interface auto-advanced after thirty seconds per question regardless of whether the patient had finished. The automated scoring system registered incomplete responses as incorrect, which artificially lowered the score by four points compared to in-person administration. This particular patient had mild cognitive impairment with preserved calculation ability. The platform error created a false positive for dementia-level impairment. The workaround was simple but tedious: I switched to a paper-based administration for that patient and documented the platform limitation in the clinical notes. For future cases, I flagged the tool in our internal database as unreliable for patients with attention or processing speed deficits. This isn't a rare issue. Many free online versions lack proper response timing controls and force completion patterns that don't reflect real clinical conditions.
What Beginners Get Wrong
The biggest mistake I see is treating the MMSE as a standalone diagnostic instrument. It is a screening tool. A score below twenty-four typically warrants further evaluation, but the cutoff is not universal. Educational level, age, and cultural background all affect baseline performance. A person with eight years of formal education scoring twenty-two is not equivalent to someone with sixteen years of education scoring twenty-two. This is why education-corrected norms exist in published literature, and why ignoring them produces inaccurate classifications. Another common error is the handling of "don't know" responses. Some examiners accept a patient's statement that they don't know and award zero points without attempting prompting strategies. The official administration allows gentle prompting for orientation items. A patient who initially says "I don't know" but then recalls the correct answer after one prompt should still receive the point. The test measures cognitive function, not confidence. This distinction matters for borderline cases where scores cluster around the cutoff thresholds.
Limitations You Need to Accept
The MMSE has well-documented floor and ceiling effects. Patients with moderate to severe dementia often score in the five to ten range, making it nearly impossible to track subtle changes over time. Conversely, highly educated individuals with early neurodegenerative changes can score twenty-eight or higher and still be declining cognitively. The test simply isn't sensitive enough for either end of the spectrum. If you're monitoring disease progression in established dementia or screening for very early cognitive change, the Montreal Cognitive Assessment (MoCA) provides better discrimination with its inclusion of executive function and visuospatial tasks weighted more heavily. Online versions introduce additional limitations. They cannot assess nonverbal responses reliably. They cannot observe subtle signs of apraxia, neglect, or anosognosia that contribute to clinical interpretation. They cannot adjust administration in real time for patients who are hard of hearing, visually impaired, or anxious. A paper-based MMSE administered by a trained professional will almost always yield more clinically meaningful data than an online version completed independently by a patient or caregiver.

How to Choose a Legitimate Online Resource
Look for sources that cite the original Folstein publication and provide the complete 30-item instrument with verbatim administration instructions. Reputable medical organizations like the Alzheimer's Association and major university medical centers host versions that match the standard scoring. Avoid platforms that summarize or paraphrase questions, alter the point structure, or omit items entirely. Some free versions skip the clock-drawing component or replace it with a simpler task, which changes the total possible score and invalidates standard interpretation. If you need to use an online version for remote screening, be transparent about the limitations in your documentation. Note that the administration was not conducted in person, that certain behavioral observations were unavailable, and that any score obtained should be confirmed with in-person evaluation before clinical decisions are made. This protects both the patient and the examiner.
Scoring Quick Reference
Orientation: ten points maximum. Registration: three points. Attention and calculation: five points. Recall: three points. Language: eight points. Visuospatial: one point. Total: thirty points. Scores between twenty-four and thirty are generally considered normal for elderly populations. Below twenty-four suggests cognitive impairment. Below ten indicates severe impairment. These ranges are guidelines, not absolute boundaries, and should always be interpreted alongside clinical context and patient history. The test itself is not proprietary. Anyone can administer it. The responsibility for proper administration, accurate scoring, and appropriate clinical interpretation rests entirely with the examiner. An online tool is only as useful as the person using it.