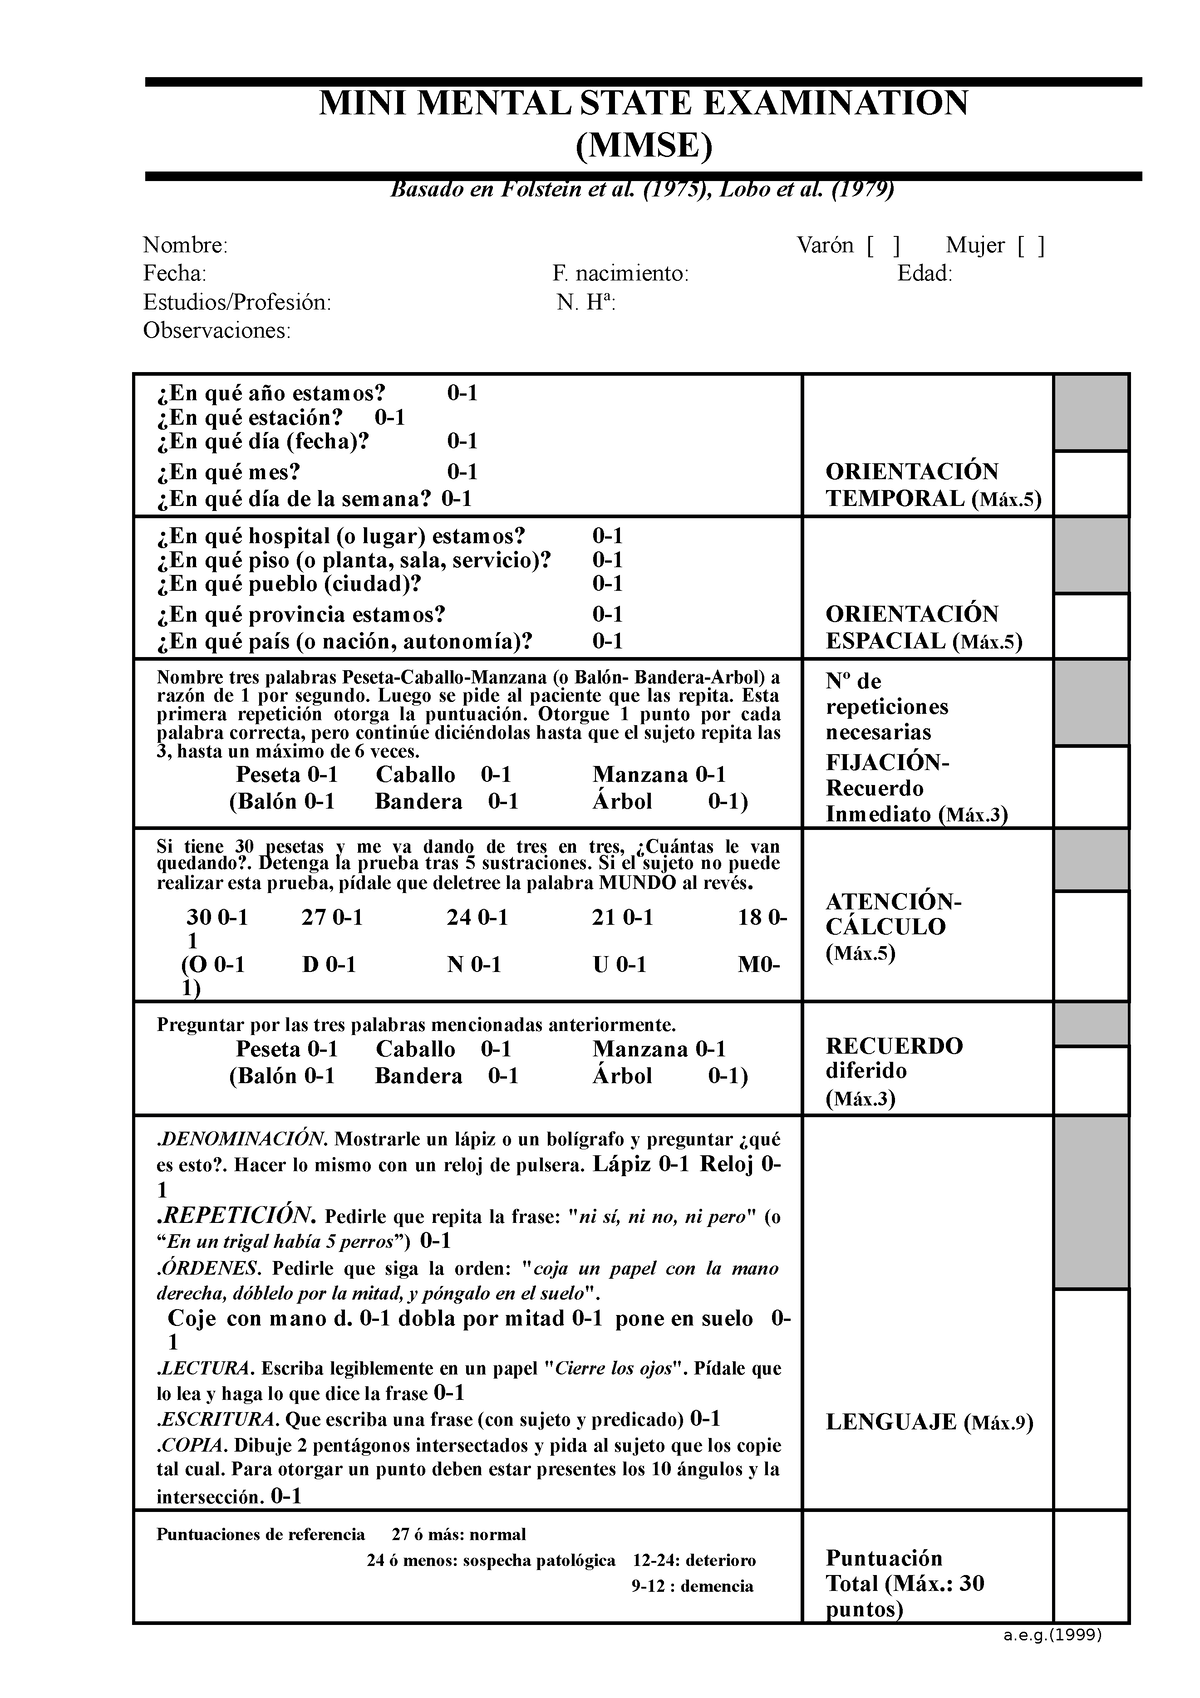
Using the Mini Mental Status Exam in Spanish
The MMSE is one of those standardized tools you see everywhere in clinical settings. When your patient population speaks Spanish as their primary language, the English version becomes unreliable. Word recognition tasks fall apart when someone understands your instructions but genuinely doesn't know what "paper" or "backward" means in English. That's where the Spanish-adapted version comes in. The adapted version preserves the original 100-item structure, though it's been reworded for Spanish-speaking respondents. The domains remain the same: orientation, registration, attention and calculation, recall, language, and visuospatial skills. But the tasks shift significantly. Instead of repeating "no paper," you ask patients to repeat phrases like "cierra los ojos" or "toma este papel." The calculation section usually keeps the same monetary math problems but can be framed differently depending on the adaptation you use. I've administered this in both hospital and outpatient settings. One practical issue I ran into early on is that many Spanish-speaking patients respond politely even when they don't understand. They'll nod and say "sí" through questions that are clearly confusing them. You need to watch for that specifically. In one case, a patient scored a solid 24 on the first run, which is borderline normal. I went back and realized half her "correct" answers were just polite nods. She was actually orienting poorly and struggling with the recall task. Dropping her score to a 17 after proper administration changed the entire clinical picture. It took about twenty minutes total instead of the ten I'd originally allocated.
Scoring thresholds matter here too. The standard cutoff of 24 or below indicating possible impairment carries over, but education level and acculturation affect performance noticeably. A patient with less formal schooling who grew up speaking only Spanish tends to score lower on the calculation and naming subtasks regardless of cognitive status. I've seen educated bilingual patients score just fine while recently arrived immigrants with the same baseline cognition struggle on the exact same items. Here's what most people miss when they start using this version. The clock drawing task translates without modification, but the three-point naming item uses different objects in some adaptations. Some versions use "reloj, moneda, faro" instead of the original English items. Make sure your scoring sheet matches your administered version exactly. Mismatched keys are the most common scoring error I see, and it wastes everyone's time correcting it later. Retest reliability is solid for the Spanish version. Test-retest correlations in the 0.85 to 0.90 range appear across studies, which tracks with the original MMSE's psychometrics. Sensitivity drops slightly compared to instruments like the MoCA, particularly for detecting mild cognitive impairment in the 22 to 24 range. That's worth noting if you're using this as a screening tool rather than a comprehensive assessment.
Potential downsides. The Spanish MMSE doesn't account for vision or hearing deficits well. If your patient has untreated cataracts or hearing loss, their scores will reflect that barrier rather than cognition. I've had patients consistently score in the impaired range only to discover later they couldn't hear the verbal instructions clearly. Budget ten extra minutes at the start for a basic sensory check before you begin. Also, the ceiling effect is real. Patients scoring 28 or 29 aren't necessarily cognitively pristine; they just did well on the easier items. The test lacks the discrimination needed at the high end. If you need something more sensitive for Mild Cognitive Impairment detection, the Spanish MoCA is a better option. It adds more demanding executive and memory tasks that catch problems the MMSE misses. The trade-off is time and training. The MMSE in Spanish takes roughly 10 to 15 minutes for a trained administrator. The Spanish MoCA runs 15 to 20 minutes and requires more familiarity with the scoring nuances. Administration tips that actually help. Read each item slowly and clearly. Pause between commands. Don't rush through the orientation questions because they feel routine. I've caught errors by slowing down on the month sequencing task where patients sometimes blend numbers together without realizing it. For the recall portion, don't give hints or cues. The point is unaided retrieval. Write down exactly what they say, verbatim, so you can score accurately afterward.
Get the Full Details

Documentation should note the version used, the patient's preferred language, and any accommodations made. Did you repeat instructions? Did they respond primarily through a family interpreter or independently? Those details change how you interpret the final score. The Spanish MMSE isn't perfect, but it's widely available and reasonably cost-effective for initial screening. Just be honest about what it can and can't tell you, and don't let a borderline score sit in a chart unexamined. That 24 that looked suspiciously high after ten minutes of rushed administration usually tells you something worth investigating further.