Why the MNA still matters despite being around since 1994
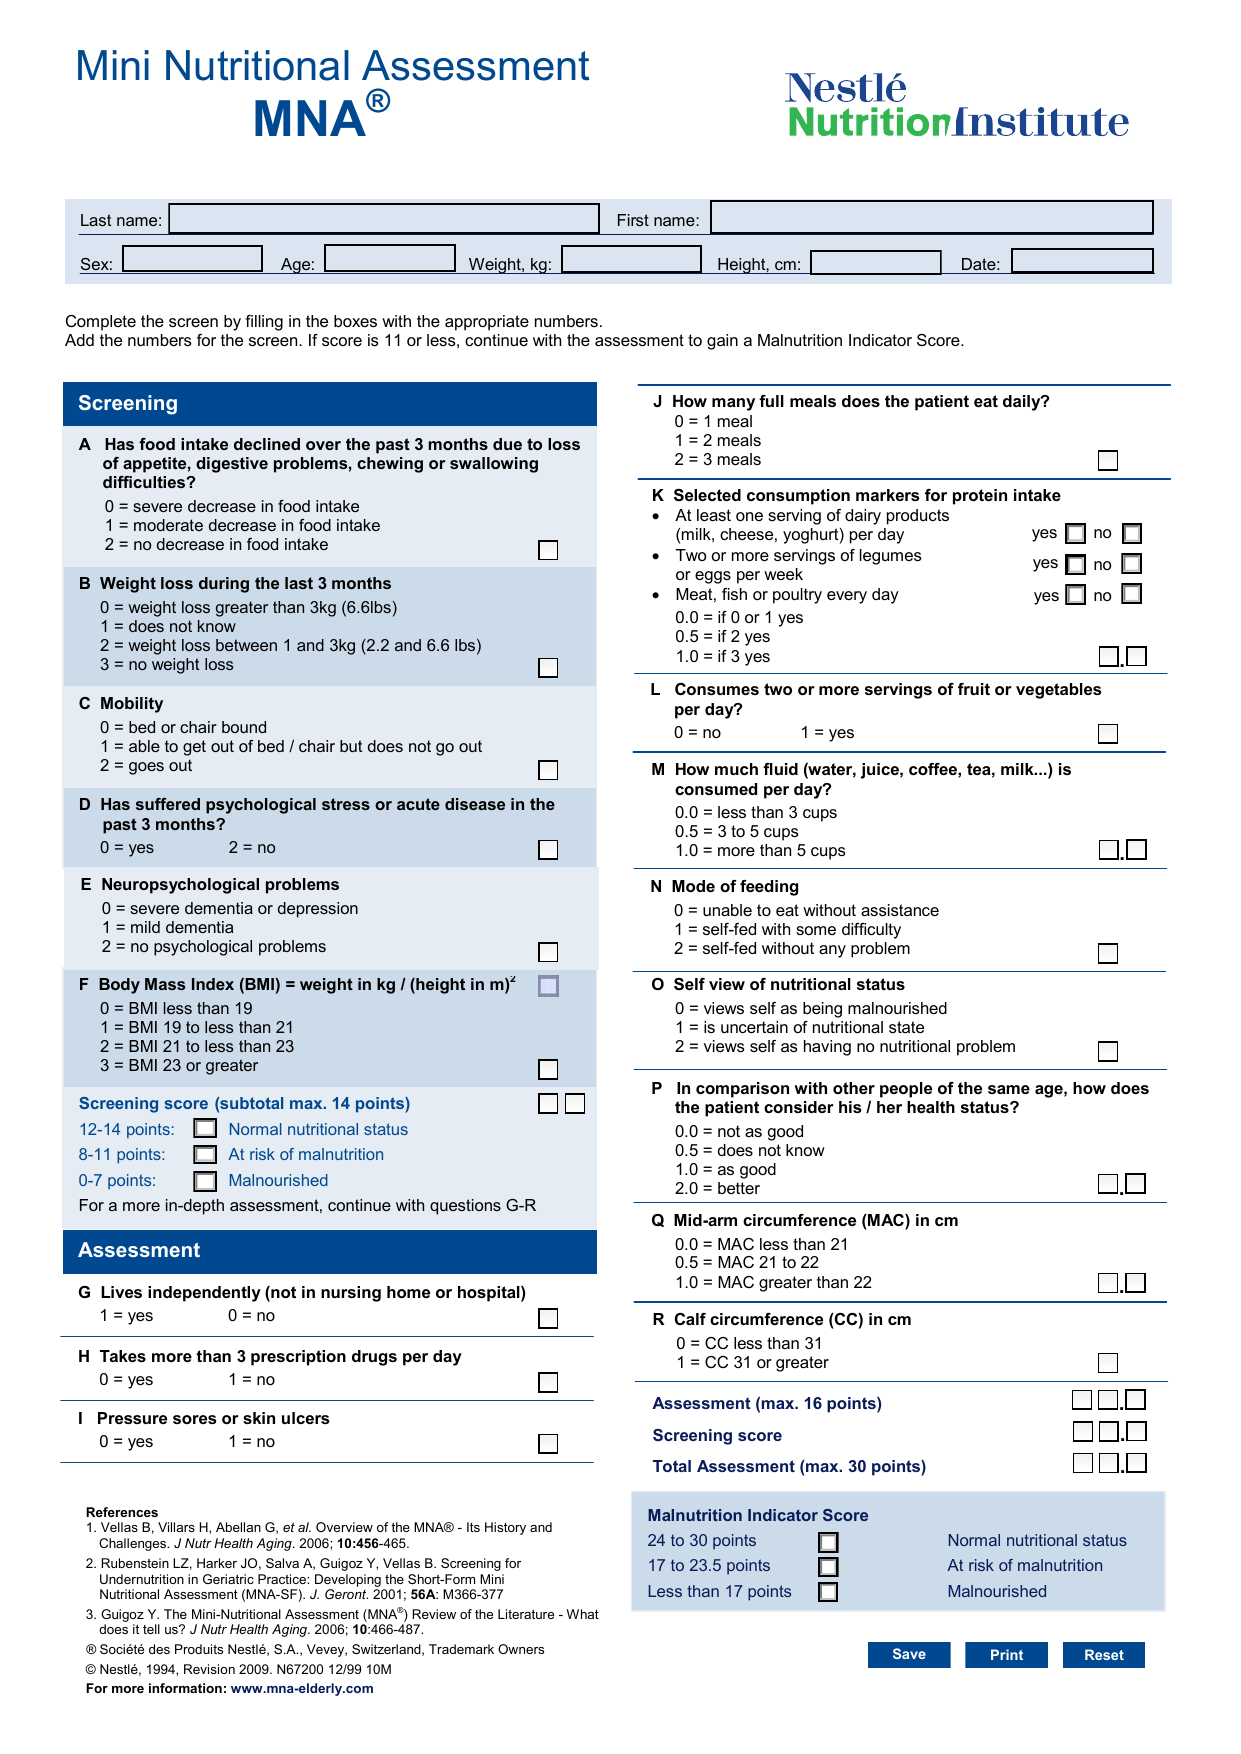
The Mini Nutritional Assessment was developed by Michel Scherbo and colleagues at Nestlé Research Center to fill a gap that existed at the time. Nobody had a brief, validated tool that actually worked for older adults in both community and clinical settings. Most screening instruments were either too long or designed for hospitalised patients with acute illnesses. The MNA was different because it captured things beyond just weight loss. It looks at mobility, neurological problems, psychological stress, and independence with medications alongside nutrition. I've been running this tool in geriatric wards and outpatient clinics for years. It's still the most commonly used nutritional screening instrument in Europe for people over 65. Not because it's perfect, but because it's fast, it's free, and it has more outcome data behind it than almost any other tool in its category. Validation studies show it predicts mortality, length of hospital stay, and functional decline with reasonable accuracy.
Mini Nutritional Assessment: how the scoring actually works
The full version has 18 items split into two sections. Section A covers anthropometric data, general lifestyle, medication use, and mobility. That's about six minutes for a trained person. Section B is the actual scoring part with questions on weight loss, overall feeding assessment, mobility, psychological stress or acute disease, neuropsychological problems, and body mass index. The maximum score is 30 points. People who score 24 to 30 are considered well nourished. Scores between 17 and 23.5 indicate risk of malnutrition. Anything below 17 means the person is malnourished. There's also a short form, the MNA-SF, with only six items. It takes roughly two minutes and is what most clinicians actually use in busy practice. You start with BMI, then weight loss over the past three months, mobility, psychological stress or acute disease in the past three months, delirium, and appétite. The cut-offs are slightly different. A score of 12 to 14 is normal. Seven to eleven signals risk. Six or below means malnutrition. The short form validates well against the full version. Correlation coefficients in published studies range from about 0.87 to 0.94 depending on the population. Here's something most people don't realise when they first administer it. The weight loss question is worth four points on the full MNA and three on the short form, but it's also the most unreliable item. People forget how much they weighed six months ago. Family caregivers often don't know either. I've seen people confidently report zero weight loss when they had clearly lost eight kilograms. The workaround I use is to cross-reference with clinic notes or pharmacy records whenever possible, or to ask specifically about whether their clothes have become noticeably looser. That tends to produce more honest answers than asking directly about kilograms.
What happens when you actually use it in a real clinic
The tool assumes the person can answer questions or has a reliable caregiver available. That assumption breaks down quickly in advanced dementia. I ran into this repeatedly in a memory clinic where about a third of patients scored as malnourished on initial screening but couldn't complete the interview because of cognitive impairment. The tool doesn't account for this properly. When I encountered this, I started using the caregiver-reported version and paired it with skinfold measurements taken by the nursing staff. Body mass index alone became useless in these cases because fluid overload and muscle wasting mask each other. Adding a mid-arm circumference measurement and checking for sacral pressure sores gave me a much clearer picture than the MNA score alone ever would. Another edge case that comes up constantly involves amputees. The standard MNA scoring uses BMI calculated from total body weight. If someone has had a below-knee amputation, their weight is significantly lower than it would be with both legs present. The published correction factors aren't built into the tool itself. I calculate an estimated pre-amputation weight and use that for BMI interpretation. Without doing this, you systematically overstate nutritional risk in amputee patients. The feeding assessment question is also worth noting. It asks whether the person feeds themselves independently, with help, or not at all. This sounds straightforward but it conflates physical inability with voluntary restriction. An elderly woman with severe arthritis in her hands might struggle to hold a fork, which the score interprets as feeding dependence. She's not malnourished because she won't eat. She's malnourished because she physically cannot manage cutlery. The intervention is different in each case. Adaptive utensils versus appetite stimulants versus texture-modified food. The MNA doesn't distinguish between these, and that's a real limitation.
Get the Full Details
Common mistakes people make when using the MNA
One frequent error is applying the same interpretation to people with chronic kidney disease on dialysis. These patients often have elevated BMI from fluid retention and altered body composition that the standard scoring misreads as adequate nutrition. I've seen dialysis patients with clear protein-energy wasting given a "normal" MNA score solely because their dry weight calculation got complicated by oedema. In these cases, I supplement with serum albumin trends and the Subjective Global Assessment instead, because the MNA simply isn't designed for that population. Another mistake is treating the cutoff scores as hard diagnostic boundaries. They aren't. A score of 17 on the full MNA places someone in the malnutrition category, but that single point doesn't carry the same clinical weight as a score of 12 would. The tool gives you a risk category, not a definitive diagnosis. Clinical judgment still matters. A person who scores 17 but eats three proper meals a day, maintains activity, and has stable weight month to month doesn't need the same aggressive nutritional intervention as someone scoring 17 who is eating virtually nothing and losing strength. The MNA also doesn't screen for micronutrient deficiencies. It's entirely focused on energy, protein, and overall intake patterns. If you're looking for vitamin D deficiency, B12 issues, or iron deficiency, you need blood work. The tool won't tell you. I've seen facilities rely too heavily on MNA scores and skip basic laboratory panels, which is a serious oversight. The MNA and a comprehensive metabolic panel should be used together, not interchangeably.
Where the Mini Nutritional Assessment falls short
The tool was designed for community-dwelling and institutionalised older adults. It performs poorly in younger populations with chronic illness. A 45-year-old with Crohn's disease who has lost significant weight won't necessarily score poorly if their BMI hasn't dropped below the threshold yet. The MNA is fundamentally age-biased in its design. The weight loss question uses a three-month window, which may miss slower, chronic wasting in younger patients. Similarly, the mobility questions assume age-related decline rather than disease-specific disability. There's also the issue of cultural adaptation. The original tool was developed and validated primarily in European and North American settings. Food frequency questions reference items that don't exist in many cuisines. In my experience with refugee health clinics, translating the feeding assessment question and the general food intake question required substantial localisation. What counts as adequate intake in one culture may not translate to another. The scoring itself hasn't been validated for many cultural groups, which means the cutoff points may not apply equally. The MNA-SF omits several items from the full version, including the section on neuropsychological problems and the dietary quality assessment. This makes it faster but less sensitive to certain types of risk. Depression alone can cause malnutrition without obvious weight loss in the first few months. The full MNA catches this through the psychological stress and neuropsychological questions. The short form misses it entirely unless delirium is present. If you're using the short form in a geriatric psychiatry unit, you're underestimating nutritional risk.
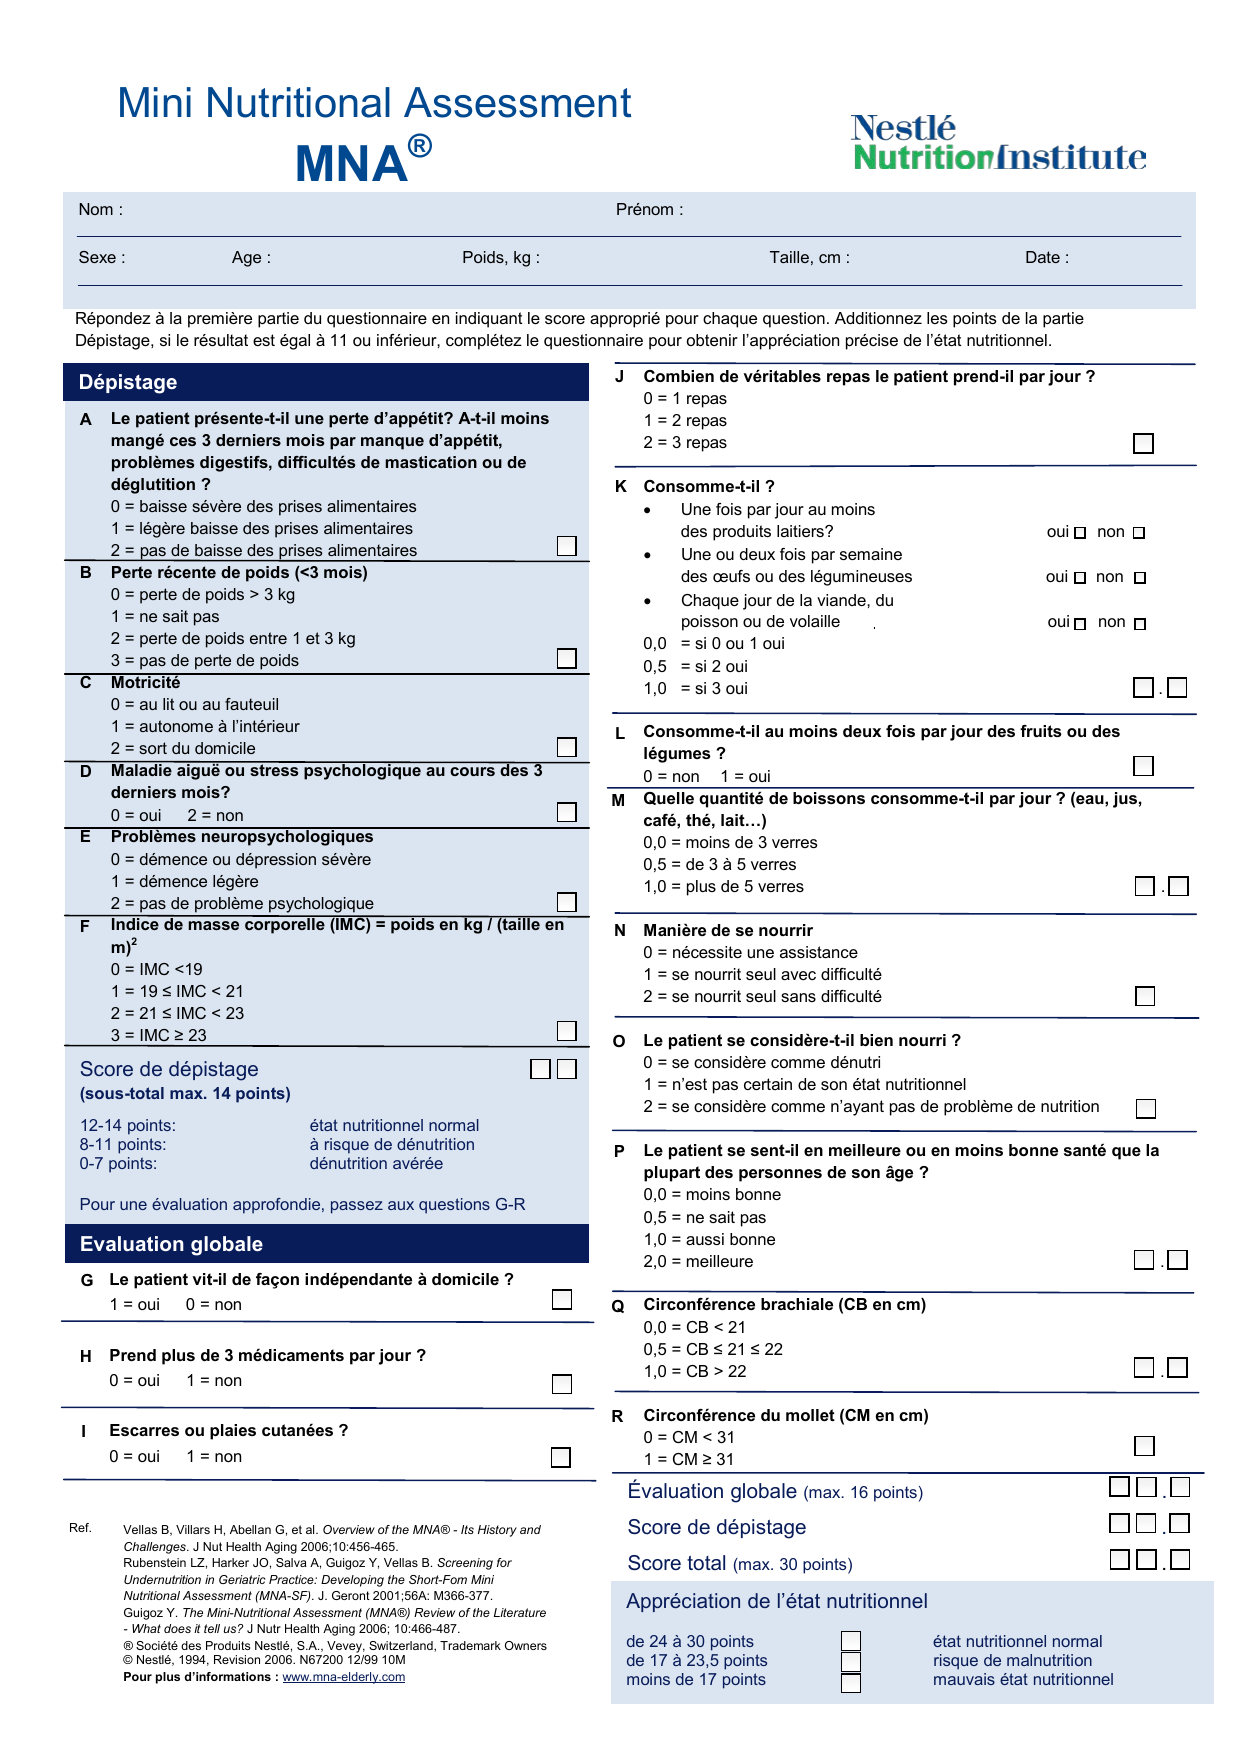
For those looking for the actual questionnaire, the full version and the short form are freely available from the MNA® Foundation website. There is no copyright fee for clinical use. Some institutions purchase printed booklets or integrated digital versions through third-party vendors, but the underlying tool is public domain for professional use. The scoring tables and cut-off values are the same everywhere regardless of where you obtain the form. The bottom line is that the Mini Nutritional Assessment remains one of the better tools available for its intended purpose. It's not a comprehensive nutritional diagnosis instrument. It's a screening tool. Used correctly, it identifies people who need a deeper assessment. Used as a standalone diagnostic, it produces both false positives and false negatives that can lead to inappropriate interventions. Know what it does and doesn't do, pair it with clinical judgment and laboratory data when necessary, and don't let the score replace observation.




