What the MMPI Actually Measures
The Minnesota Multiphasic Personality Inventory is one of the most widely used psychological assessment tools in clinical practice, but it gets misunderstood constantly. It is not a test that tells you who you are. It is a standardized instrument designed to identify psychiatric conditions and personality structure based on responses to around 500 true-or-false statements. The current version, MMPI-3, has 340 items and replaces some of the older scales while keeping the core structure intact. The original MMPI was developed in the late 1930s at the University of Minnesota by Starke R. Hathaway and J. Charnley McKinley. They used an empirical criterion-keying method, which means they did not start with theory. They gave items to two groups: people diagnosed with various psychiatric conditions and a normative community sample. Items that differentiated the groups were kept. Items that did not were dropped. This is why the scale feels oddly structured compared to other personality tests you might encounter.
Accessing the Minnesota Multiphasic Personality Inventory
The MMPI is not something you download from a random website and hand to someone. It is a controlled instrument administered and scored by qualified professionals. The official publisher is Pearson, and you need a Level C or higher qualification to purchase it, depending on which version you want. That qualification generally means you hold a graduate degree in psychology, counseling, or a related field and have completed specific assessment coursework. I have seen people try to find free PDFs online, and the versions circulating there are either outdated, incomplete, or illegally distributed. More importantly, they are useless without proper training because scoring requires standardized procedures and clinical interpretation. If you are looking to administer the test legitimately, you go through Pearson's Assessment portal, verify your credentials, and order the kit or access the online version through Q-global, which is Pearson's digital administration platform. The cost runs roughly $100 to $200 depending on the version and whether you buy paper or electronic administration. Scoring and interpretation reports come as part of the package.
How Scoring Actually Works in Practice
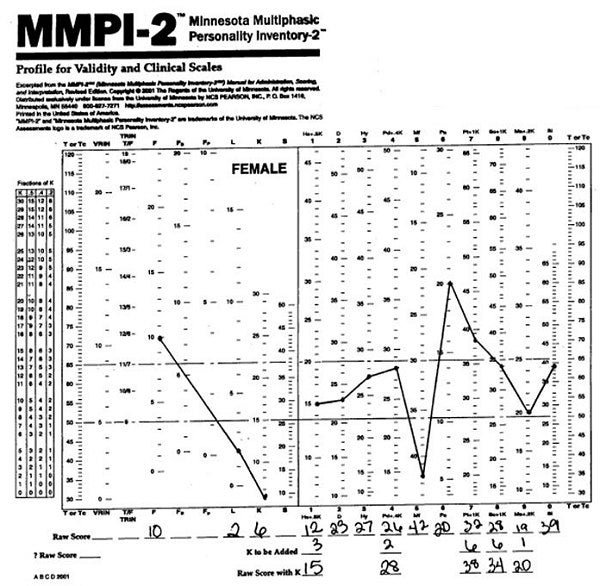
Scoring the MMPI is not as simple as counting correct answers. The instrument includes several validity scales built in specifically to detect response bias. F-scale measures rare or unusual responding. K-scale measures defensiveness or attempt to present oneself favorably. L-scale measures naive self-presentation. If you ignore these scales, you are not doing clinical work; you are just generating numbers that mean nothing. I once had a case where a client scored remarkably normal across every clinical scale, which on the surface looked like a clean result. But the F-scale was elevated and the VRIN (Variable Response Inconsistency) scale was off the chart. The raw profile said healthy. The validity indices said the person was basically flipping coins or randomly endorsing items. Without that context, a naive interpreter would have walked away confident in a totally false normal reading. That is the kind of edge case that does not show up in training manuals until you actually sit with real data. The workaround in cases like that is straightforward: flag the invalid profile, do not interpret clinical scales, and note the reason in the report. You document the specific validity violations and either re-administer under closer supervision or explain the limitation to the referring clinician. There is no creative interpretation that saves a contaminated profile. The moment VRIN and IRIN (Interitem Inconsistency) are both elevated, the data is compromised regardless of how clean the rest of the scores look.
Get the Full Details

Common Misconceptions That Waste Time
People frequently assume the MMPI reads like a Myers-Briggs type indicator. It does not. Myers-Briggs sorts people into categories. The MMPI produces continuous T-scores on multiple scales that indicate degree of endorsement for particular psychological tendencies. A T-score of 65 is clinically significant. A T-score of 75 is more pronounced. These are not labels; they are points on a continuum relative to a normative sample. Another mistake is treating the clinical scales as standalone diagnoses. Scale 2 is depression, yes. But elevation on Scale 2 without consideration of surrounding scales can mean many different things. A person with a high Scale 8 (schizophrenia) and a high Scale 4 (psychopathic deviate) might also elevate Scale 2 because they are in distress, not because they meet criteria for a depressive disorder. The pattern matters more than any single scale. You look at codetypes, which are two-digit combinations representing the two highest clinical scales. A 2-7 codetype describes something entirely different from a 7-2 codetype even though both involve the same scales. The restructured clinical scales (RC scales) in the MMPI-2-RF and MMPI-3 address some of the overlap problems in the original nine scales. The original Hs, D, Hy, Pd, Mf, Pa, Pt, Sc, and Ms scales share substantial variance because they were developed independently before anyone knew how much they correlated. The RC scales separate unique variance from shared variance. Using RC scores alongside the original clinical scales gives you a clearer picture without discarding decades of normative data tied to the older metrics.
Limitations Nobody Wants to Advertise
The MMPI has real limitations that any competent examiner has to live with. It is length. Administering the full MMPI-3 takes 60 to 90 minutes for most people. Fatigue sets in, and fatigue changes response patterns. I have seen valid profiles degrade noticeably after the 300-item mark when someone has already been taking cognitive tests for two hours straight. In those situations, the MMPI-2-RF at 185 items is a better choice if you need a shorter alternative, though you trade some depth for efficiency. Cultural bias is another persistent issue. The normative samples, especially for the original MMPI and MMPI-2, leaned heavily white and middle-class. The MMPI-3 made adjustments, but no version is fully culture-neutral. Elevated scores can reflect cultural difference rather than pathology, particularly in minority populations or immigrants. I have encountered situations where a client from a different cultural background endorsed items about religious or spiritual experiences in ways the scoring program flagged as unusual, inflating the Scales score without meaning psychosis. The fix is not to ignore the elevation but to consider cultural context before interpreting it as clinical significance. Response bias can work in both directions. Some clients try to look bad, which is rare but happens in forensic settings where there may be secondary gain in appearing severely disturbed. The Fb-scale and Fp-scale were added to catch this. Other clients, especially in employment screening contexts, try extremely hard to look normal, depressing their clinical scores. The K-correction attempts to account for this, but it does not fix everything. When you suspect intentional faking, you need to triangulate with other assessment methods rather than rely solely on MMPI results.
When the MMPI Is the Right Tool and When It Is Not
The MMPI is appropriate when you need a comprehensive clinical portrait, particularly for diagnostic clarification, treatment planning, or forensic evaluation where response style is a concern. It is less appropriate for quick screening, routine employee selection without clinical context, or any situation where 60 minutes of focused responding is impractical. For those cases, instruments like the PHQ-9 for depression screening or the BDI for broader mood assessment are faster and cheaper, even if they lack the validity protections and breadth of the MMPI. Understanding the difference between what this instrument does and what people assume it does will save you from misusing it. The scores are useful but only when you respect the validity framework and the statistical grounding behind them. That is the actual practical takeaway from years of administering and interpreting these profiles.