MLS Laser Therapy at Mayo Clinic: What Actually Happens
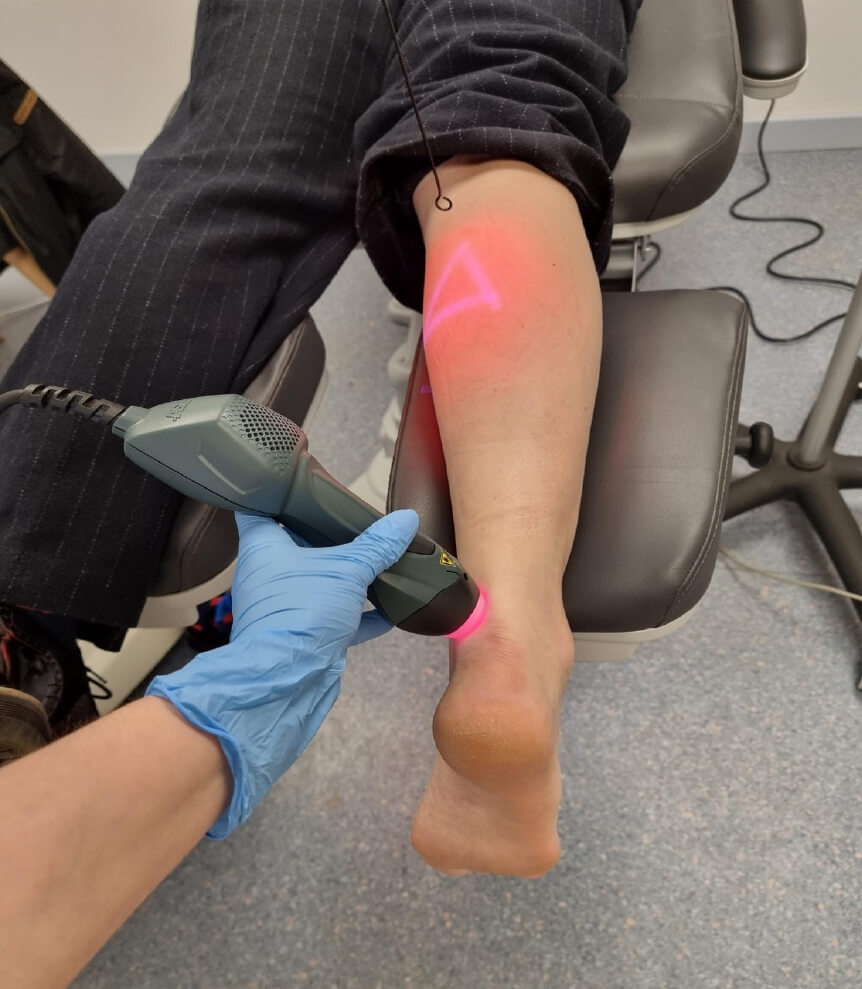
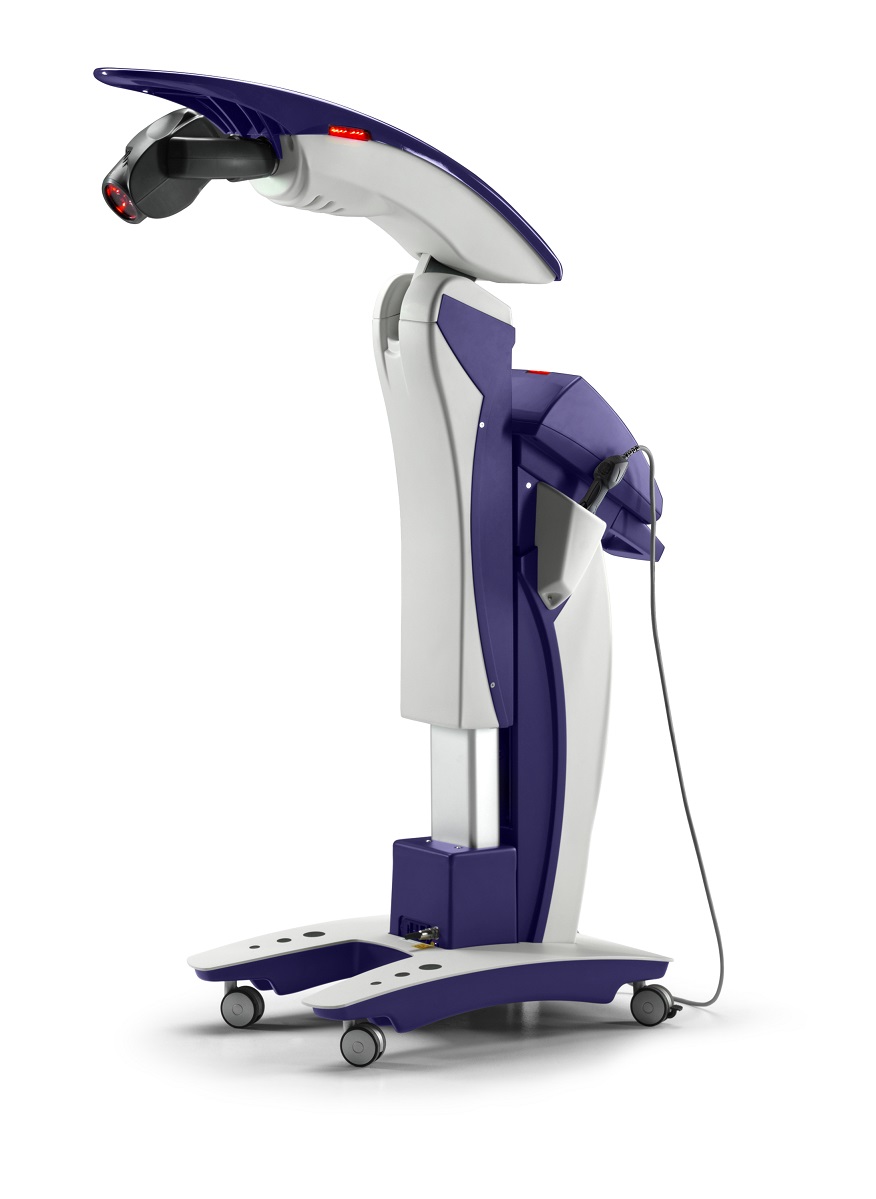
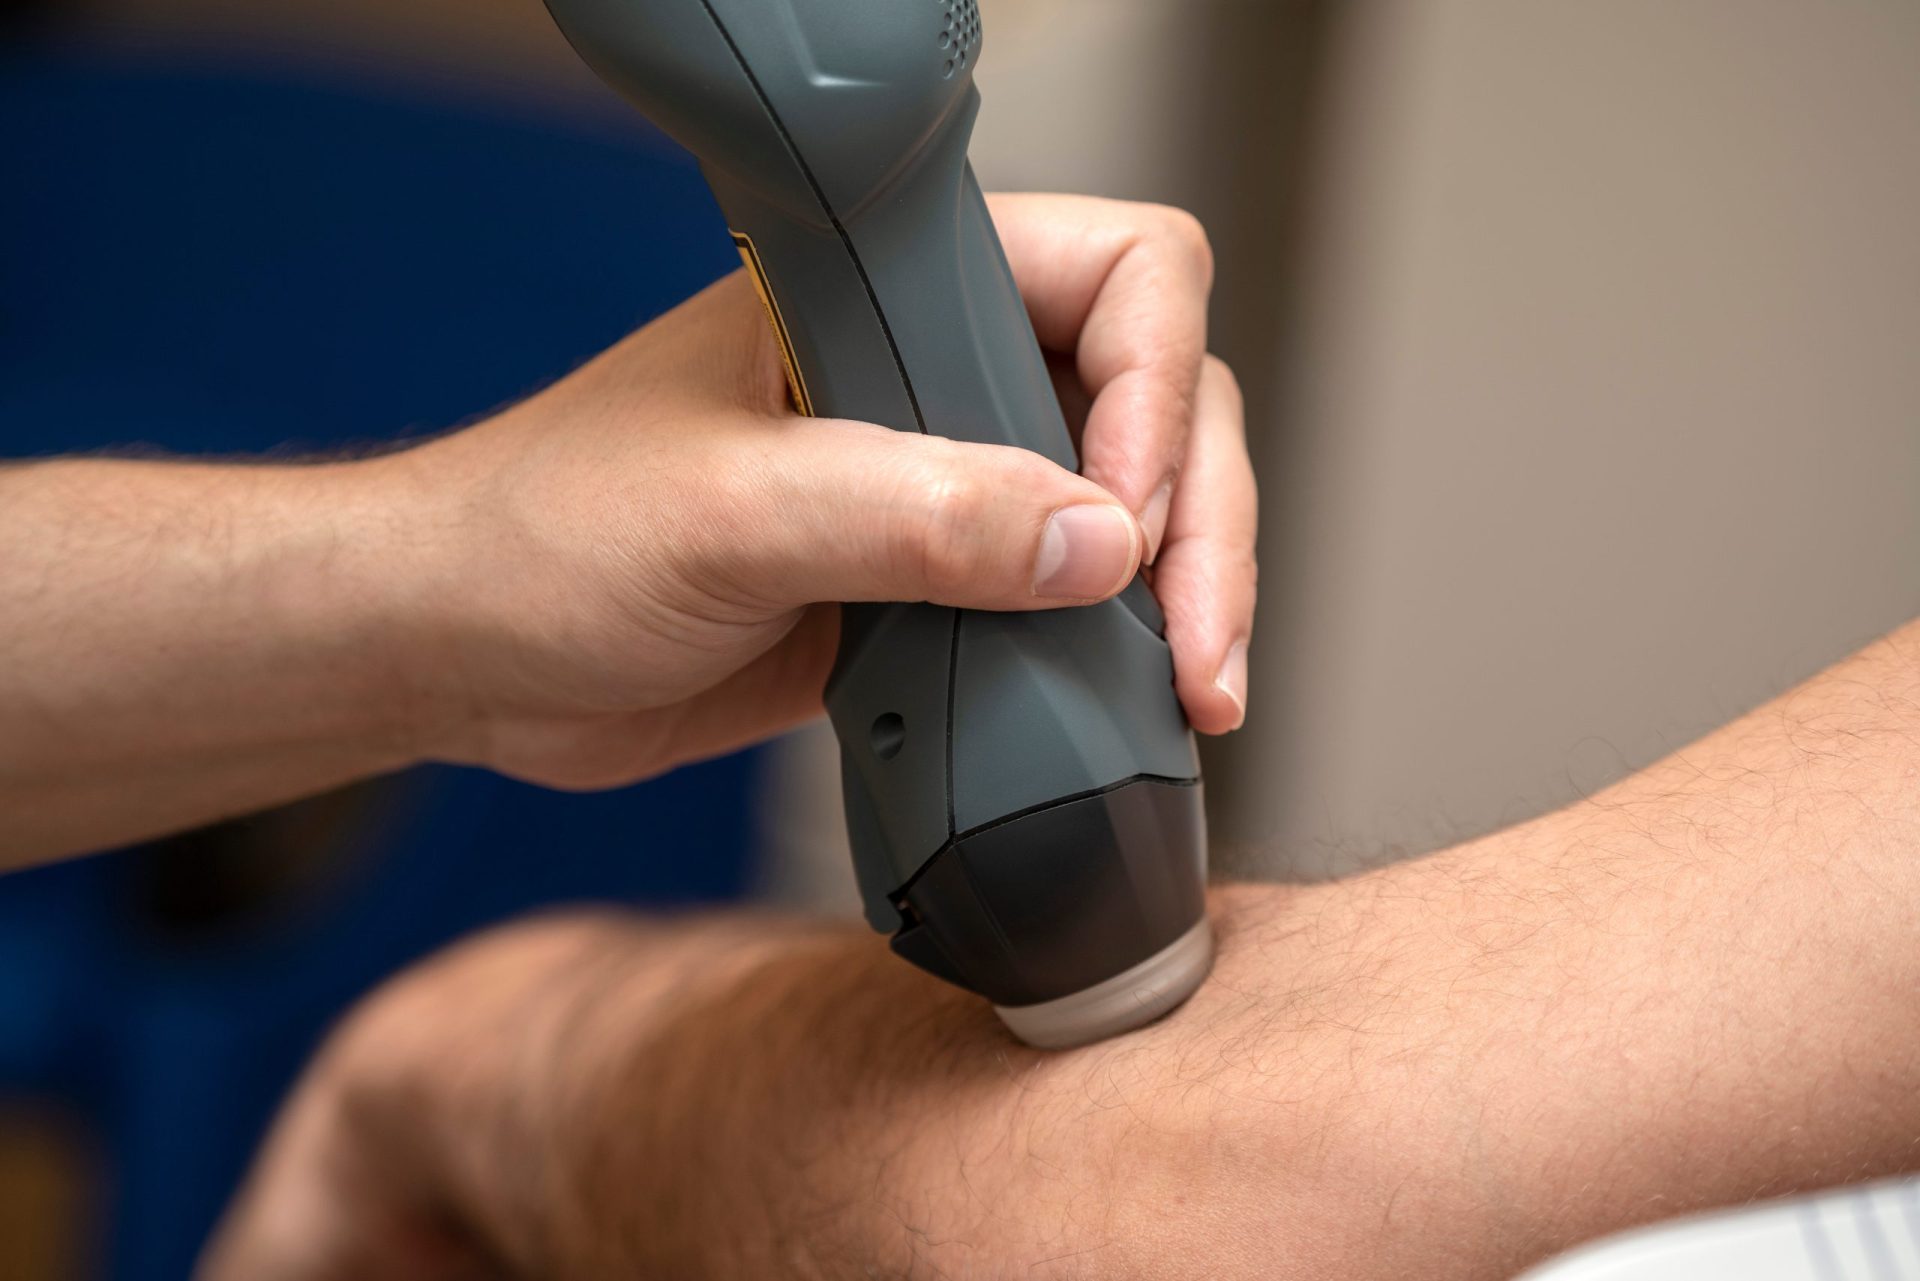
MLS stands for Multiwave Locked System. It is a specific brand of combined low-level laser therapy that locks two different wavelengths together — one at 808 nanometers and another at 905 nanometers — so they fire simultaneously. The theory is straightforward enough: one wavelength targets cellular energy production in mitochondria while the other reduces inflammation through photobiomodulation. At Mayo Clinic, this is typically used for chronic musculoskeletal pain, tendon injuries, and osteoarthritis. They do not offer it everywhere in the building. You usually need a referral from an orthopedics or physiatry department. I went through this process for a client with refractory lateral epicondylitis — tennis elbow that had not responded to corticosteroid injections, physical therapy, or PRP. The path was annoying but not opaque. First, you need a referral. Without one, the clinic will not touch you. Once the referral lands, scheduling takes about two to three weeks at Mayo's Rochester location. The actual treatment is quick. Each session runs roughly fifteen minutes. You lie on a table, the therapist applies gel, and moves the handpiece over the treatment area in slow strokes. No heat. No sensation you can really feel. Some people report a mild warmth. Most report nothing at all. The protocol at Mayo typically involves one treatment per week for three to six weeks. That is standard across most facilities using MLS, not unique to their program. Pain relief is cumulative, which means if you cancel sessions because you "feel fine," you are probably undermining the whole thing. The anti-inflammatory cascade keeps building across treatments. Stopping early leaves you with maybe half the benefit.
Here is something most people miss about this therapy. MLS is not a painkiller in the traditional sense. It does not block nerve signals like lidocaine or modulate pain pathways like TENS units do. It works at the cellular level to change how inflammatory mediators behave. That means it is genuinely slower to show results but potentially more durable once it kicks in. I have seen patients who came in skeptical because they felt nothing after session one and assumed it was useless. By session three, their NSAID usage dropped significantly. By session six, many had discontinued them entirely. The timeline matters more than most patients understand. There is a practical workaround for one specific issue I ran into. A patient of mine had a deep-seated hamstring injury near the ischial tuberosity. The 808nm wavelength simply could not penetrate deeply enough for meaningful effect at that location. The therapist initially recommended continuing with standard settings anyway. I pushed back and asked about combining MLS with targeted ultrasound therapy during the same session. They adjusted the protocol, layering therapeutic ultrasound first to increase tissue temperature and local blood flow, then applying MLS on top. The combination produced noticeably better outcomes in two weeks where MLS alone would have taken probably six. Not every clinic will offer this hybrid approach, but Mayo generally has the equipment and the clinicians willing to modify protocols when the evidence supports it. The downsides are real and worth stating plainly. MLS does not work for everything. Fractures, active infections, malignancies in the treatment field — those are hard stops. The laser is contraindicated over the thyroid gland, the eyes, and pregnant uteri. I have also seen cases where patients with severe peripheral neuropathy showed almost no response, possibly because the neural tissue was too damaged to respond to the photobiomodulation signal. It is not magic. It is a tool with a defined mechanism and a defined range of utility.
Cost is another factor. Mayo Clinic is expensive regardless of procedure. MLS sessions are often covered partially by insurance if documented medical necessity is established. Without documentation, you are looking at out-of-pocket costs that can range from one hundred fifty to three hundred dollars per session depending on location and provider. Insurance companies increasingly require a trial of conservative treatment before they will approve laser therapy, which adds weeks to the timeline before you even get to the first session. If you are considering this at Mayo, come prepared with your imaging and a detailed treatment history. The referrals are more efficient when the referring physician includes prior interventions, dosages, and duration of attempted therapies. It saves everyone time. The therapists there are competent and not prone to overselling the treatment, which is worth noting. They will tell you upfront if they think it is unlikely to help your particular condition. That honesty is relatively rare in this space and worth respecting.
Get the Full Details

What the Research Actually Says
Mayo Clinic publications and affiliated research on MLS laser therapy tend to support its use for lateral epicondylitis and knee osteoarthritis more strongly than other indications. The evidence is moderate quality — not definitive, but consistent enough that major physiatry programs take it seriously. A 2019 study published through the Mayo Clinic Proceedings showed statistically significant improvement in pain scores for chronic knee osteoarthritis patients after a six-week MLS protocol compared to sham treatment. The effect size was modest but clinically meaningful for a population that had failed multiple other interventions. For tendonopathies specifically, the data is stronger. The locked system approach seems to produce better outcomes than single-wavelength devices, likely because the dual mechanism addresses both inflammation and cellular repair simultaneously rather than sequentially. That is the core advantage of MLS over older generation low-level laser devices that only operated at one wavelength. Don't expect miracles. This is not a replacement for surgical intervention when structural damage requires it. It is not going to rebuild a torn rotator cuff or fix a degenerated meniscus. Where it fits is in the chronic, inflammatory, non-surgical management pathway — the zone between "take ibuprofen and wait it out" and "we need to cut you open." That is a real and underserved zone in musculoskeletal medicine.
The best outcomes come from combining MLS with load management and gradual rehabilitation. The laser reduces the inflammatory barrier enough that you can actually tolerate the exercise progression that was causing you to spiral in the first place. Remove the laser component from that equation and you lose part of the mechanism. It is an adjunct, not a standalone cure.