
How the MMPI-3 Interpretation Worksheet Actually Works
The MMPI-3 came out in 2020 and replaced both the MMPI-2 and MMPI-2-RF. That means a lot of older interpretation sheets are now obsolete, and people are scrambling to figure out how the new scoring structure maps onto a worksheet they can actually use. I spent about three months building out a workflow for this after my first time administering it, so I can tell you what works and what doesn't. First, a quick note on the instrument itself. The MMPI-3 has 335 true/false items. It generates 16 Validity Scales, 12 Clinical Scales (the restructured ones from the MMPI-2-RF carry over), 8 Supplemental Scales, 4 Content Scales, and 6 Personality Psychopathology Five scales. That is a lot of numbers to juggle, and raw T-scores alone won't tell you much without a structured approach.
MMPI 3 Interpretation Worksheet Setup
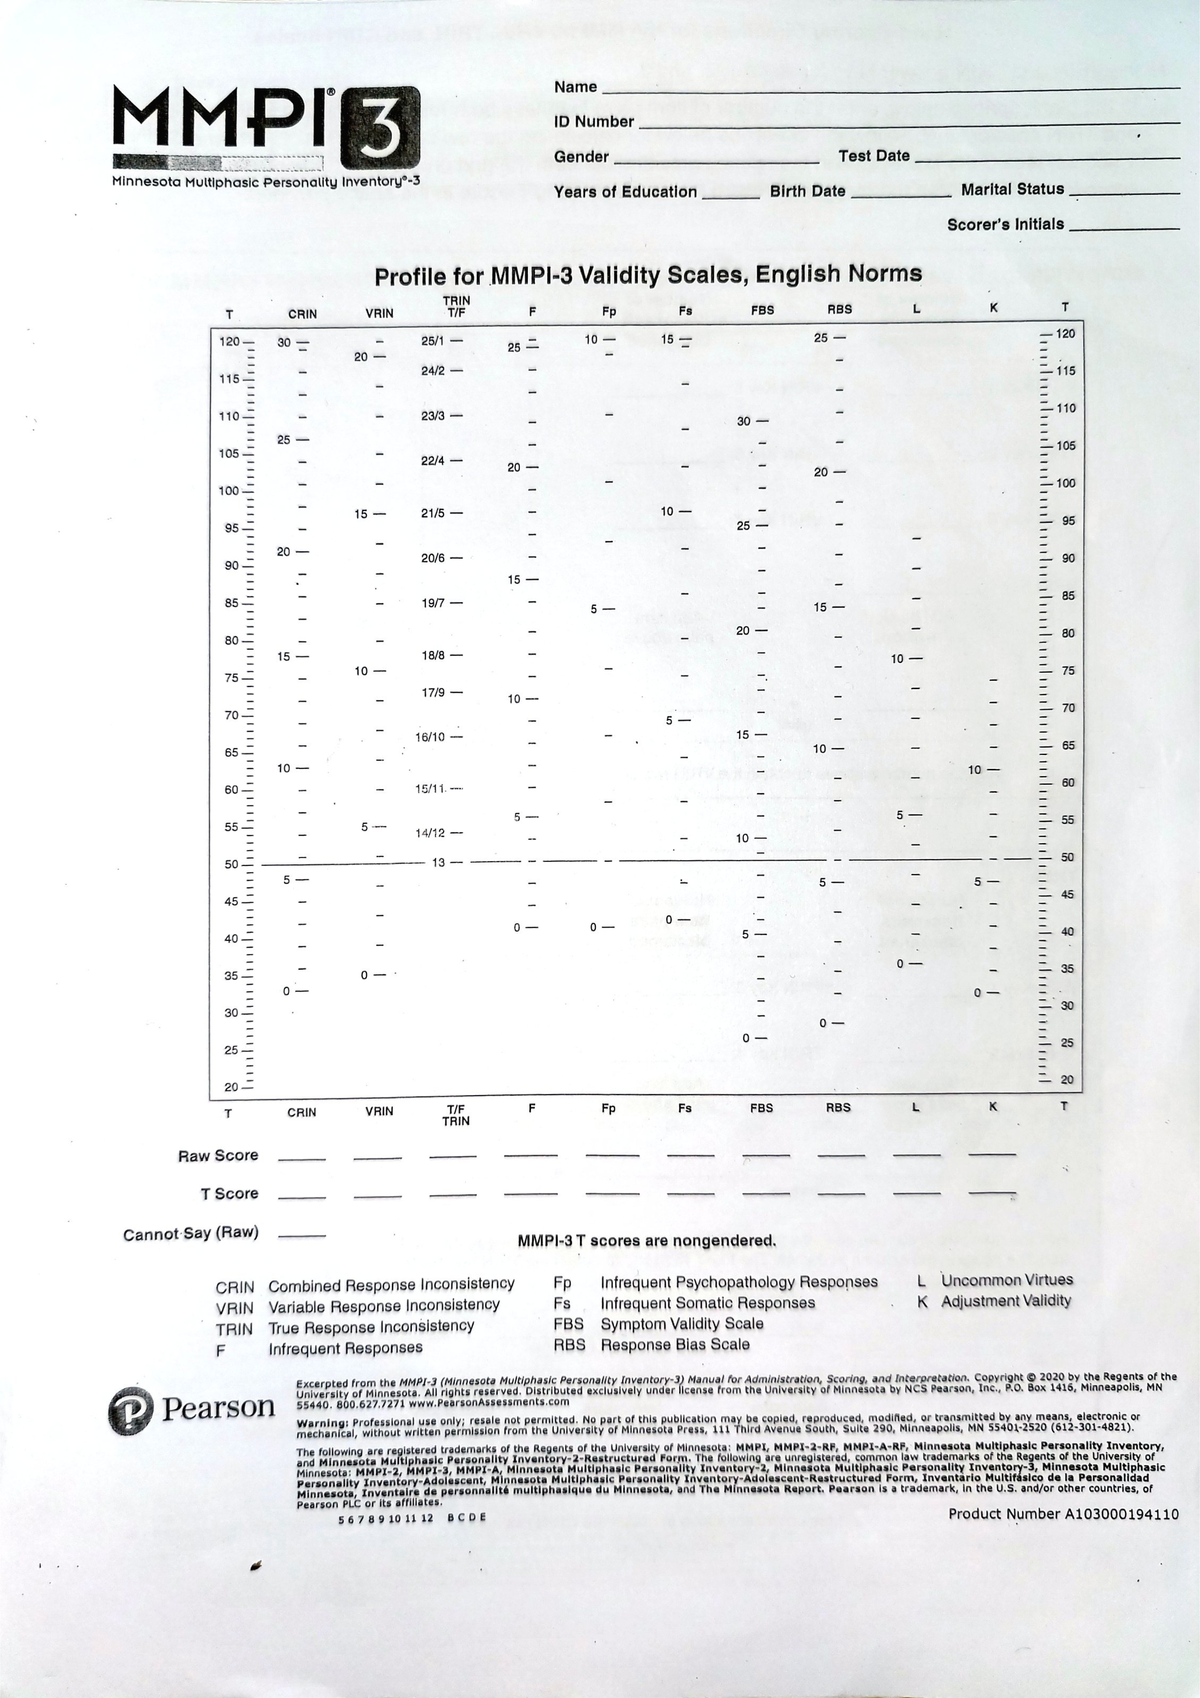
I keep a single Excel workbook with four tabs: one for validity analysis, one for clinical scale scoring, one for supplemental and content scales, and one for narrative notes. The validity tab is the most important and the one most people skip past too quickly. If the validity scales don't check out, everything below them is unreliable, period. Here is the basic structure I use: Validity Tab
The MMPI-3 has shifted some validity indicators from the MMPI-2. The F, Fp, and FBS scales still matter, but they have different base rates now. I track V-Scale 1 (Response Set), V-Scale 2 (Infrequent Somatic Responses), V-Scale 3 (Infrequent Psychological Responses), V-Scale 4 (Rare Endorsements),VRIN-r, and TRIN-r. The T-score cutoffs are slightly different from the MMPI-2-RF. VRIN-r above 80 and TRIN-r outside the 40-to-60 range usually flag a problematic response pattern. I also flag when F is elevated relative to Fp, which can indicate over-reporting, or when Fp is elevated without a corresponding F elevation, which sometimes points toward malingering rather than genuine distress. Clinical Tab The 12 clinical scales use the same numbering as the MMPI-2-RF. I calculate T-scores from the raw scores, flag anything at or above 65, and then look at the code type. Two-point or three-point code types are where the interpretation gets real. A 2-7 code type, for example, tells you something very different than a 7-2, even though the same two scales are elevated. Direction matters. I always note which scale is higher and by how many points.
Get the Full Details
Supplemental and Content Tab The supplemental scales like MAC-R, REI, and PK still have their place. The content scales (SC, PSY-5) give you descriptive detail that the clinical scales alone don't capture. I cross-reference content scale elevations with the clinical profile to see if there is convergence or divergence. Divergence is where the interesting cases live. I ran into a specific problem about six months in that took me a while to figure out. A client came in with an otherwise clean validity profile, T-scores in the normal range across VRIN-r and TRIN-r, but their F scale was at 72 and their Fp was at 68. On paper, this looked borderline. The old MMPI-2 rules would have flagged this immediately as over-response inflation. On the MMPI-3, the base rates for F and Fp are lower because the item pool changed. I initially misread this as a valid profile with mild exaggeration. What actually happened was the client had genuine severe psychopathology, and the F elevation was real, not feigned. The workaround was to pull the RC scales and the PSY-5 scales and check for convergence. When those clinical indicators also lit up in the same direction, I knew this wasn't malingering. I documented the discrepancy and noted it in the report rather than dismissing the elevated F. That case taught me to never rely on a single validity indicator in isolation.
Another thing nobody tells you about the MMPI-3 interpretation worksheet is that the norming sample changed. The MMPI-3 was normed on a more demographically representative sample than the MMPI-2. This affects T-score interpretation at the margins. A T-score of 63 on the MMPI-3 might be clinically meaningful in a way that a T-score of 63 on the MMPI-2 was not, simply because the distribution shifted slightly. I adjust my threshold for flagging borderline elevations upward to about 64 or 65 depending on the scale and the context of the referral question. This is not in the manual explicitly. It is something you pick up by comparing old MMPI-2 profiles with new MMPI-3 profiles from the same types of clients. For downloading or building your own worksheet, the scoring software from the publisher generates raw score reports that you can copy into your spreadsheet. I use the Q-global scoring system and then export the results. There is no official standalone worksheet from the publisher, so most clinicians build their own or adapt an MMPI-2-RF template. The mapping between MMPI-2-RF and MMPI-3 is roughly one-to-one for most scales, but a few supplemental scales were dropped and a couple of new ones were added, so you cannot just reuse an old sheet without checking which scales are present in the output. The whole process from score output to a finished narrative typically takes me about 45 minutes to an hour for a straightforward profile. Complex profiles with multiple code types and validity concerns can take two to three hours. The worksheet itself is what keeps me from re-scoring or second-guessing myself halfway through the narrative section.


