What Mod I Physical Therapy Actually Covers
Mod I Physical Therapy is a first-semester foundational module found in most accredited physical therapy degree programs. It covers the core principles of musculoskeletal assessment, basic neurology, and introductory patient management. Most students breeze through the lectures but hit a wall during clinical reasoning sessions because the material bridges two disciplines without fully committing to either. I remember struggling with this when I was studying for my board prep. The module expects you to already be fluent in anatomy terminology and then suddenly apply it to clinical decision-making within the same week. That transition is rough if you haven't done any self-directed reading ahead of time.
Mod I Physical Therapy: How It Actually Works
The module is structured around three pillars: biomechanics, tissue healing timelines, and initial patient screening. Biomechanics alone takes up about a third of the contact hours. You learn joint arthrokinematics, muscle leverage, and how to perform basic goniometric measurements. Tissue healing timelines cover the inflammatory, proliferative, and remodeling phases across different tissue types. The screening portion teaches you red flag identification and when to refer rather than treat. Most programs don't give you a single textbook for this. You end up piecing together material from Magee's Orthopedic Physical Assessment, Kisner and Colby's Therapeutic Exercise, and a few chapters from O'Sullivan's Rehabilitation Nursing. That fragmentation is by design but it means you have to build your own study system early or fall behind fast.
How to Study for It Without Losing Your Mind
Don't just read the material. Active recall is the only thing that sticks. I used to sit in the library and close the book, then try to draw out the brachial plexus from memory, label every branch, and explain what each nerve innervates. If I got stuck, I'd open the book and mark exactly where my gap was. That took about twenty minutes per topic and saved me hours of rereading passages I thought I understood. The clinical reasoning part is where most people tank. You'll get case studies that seem straightforward but have hidden complications. For example, a patient presents with shoulder pain and limited abduction. The easy answer is adhesive capsulitis. But if you don't check cervical radiculopathy first, you're sending them down the wrong treatment path. I learned this the hard way during a simulated clinical rotation when I missed a positive Spurling test and recommended aggressive stretching for someone who actually needed cervical traction and nerve gliding instead. My workaround was simple: I started every case study by listing differential diagnoses before looking at the treatment options. I wrote them down in order of likelihood. This forced me to actually think through the assessment rather than jump straight to interventions. It added about five minutes to each problem but dramatically improved my accuracy.
Get the Full Details

What Most Students Miss
The biggest gap I see is how little emphasis is placed on documentation. Programs focus heavily on assessment skills but barely touch on how to write a SOAP note that would survive a payer audit. I spent weeks learning special tests and almost nothing on how to justify medical necessity in writing. That oversight cost me during my first clinical rotation when my supervising PT reviewed my notes and pointed out that every entry was missing objective measurable data. Phrases like "patient responded well" are worthless in documentation. You need numbers, ranges, and specific outcome measures. Another thing nobody talks about is the weight of statistics and research methodology in this module. You need to understand basic study design, p-values, confidence intervals, and how to critically appraise a journal article. Most students wing it and then struggle when they reach evidence-based practice modules later in the program. Spend a weekend going through basic biostatistics resources and you'll save yourself a lot of pain.
Where This Module Falls Short
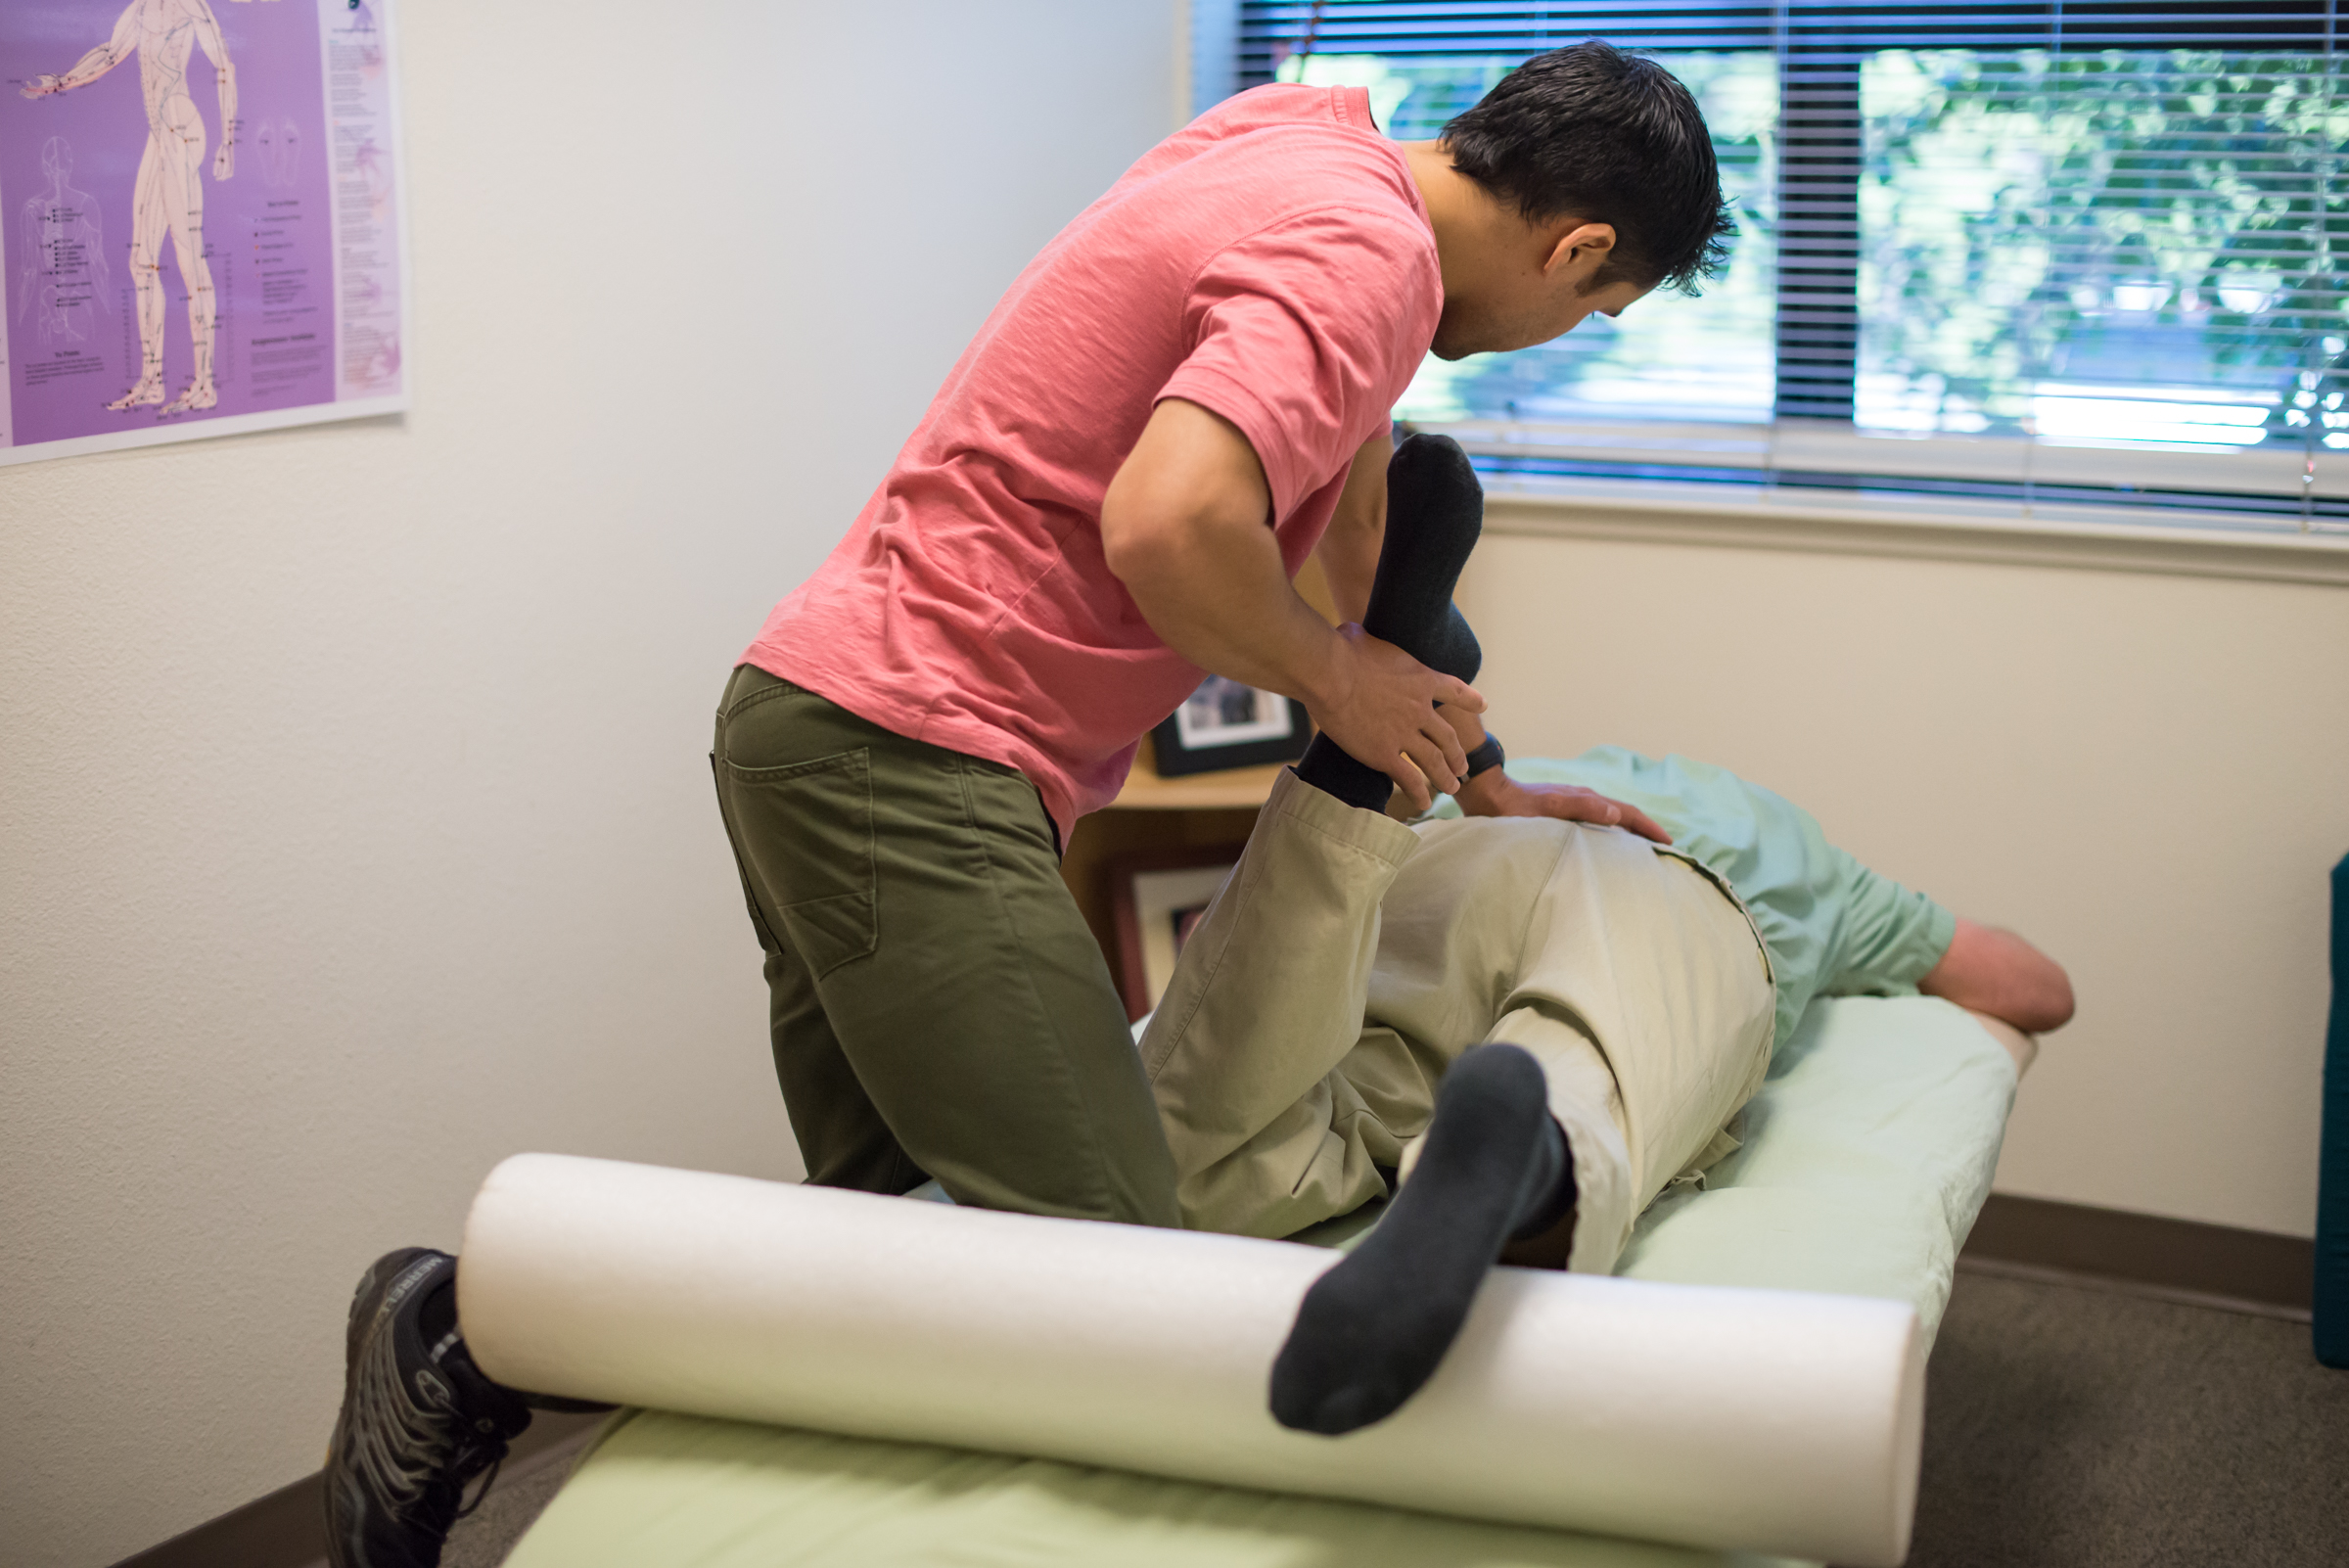
The biggest limitation of Mod I Physical Therapy in most programs is that it treats assessment and treatment as separate units when they're not. In real clinical practice, you're assessing and intervening simultaneously. A manual therapy technique you use can also serve as a diagnostic tool. The module structure doesn't really reflect that integration. Also, the timeline pressure is unrealistic. You're expected to absorb an enormous volume of material in twelve to fourteen weeks while also managing clinical practicum hours. Many programs schedule exams back to back during the last two weeks, which turns the module into a memorization sprint rather than a genuine learning experience. This is a systemic issue, not something you can fix on your own, but being aware of it helps you pace your studying better. If your program is heavy on lecture and light on hands-on practice, supplement with virtual simulation platforms or peer assessment sessions. Practice goniometry on each other until it becomes automatic. You won't have the muscle memory during clinical rotations if you're still figuring out where the lateral epicondyle is.
Resources That Actually Help
PhysicalTherapy.com has a decent section on biomechanics review. Board Vitals for PT helps with question practice, though some of the clinical scenarios lean too heavily toward pathology and not enough toward differential diagnosis. YouTube channels like Physiotutors cover specific assessment techniques with reasonable detail, but cross-reference everything because not every video follows current evidence standards. The most useful resource I found was creating my own flashcard deck using Anki. Spaced repetition makes a real difference for the anatomy and terminology sections that make up the bulk of this module. I put about four hundred cards together covering muscles, nerves, vascular structures, and common special tests. It took two weeks to build but paid off over the entire semester.