How to Actually Use the MOH-SOT Without Driving Yourself Insane
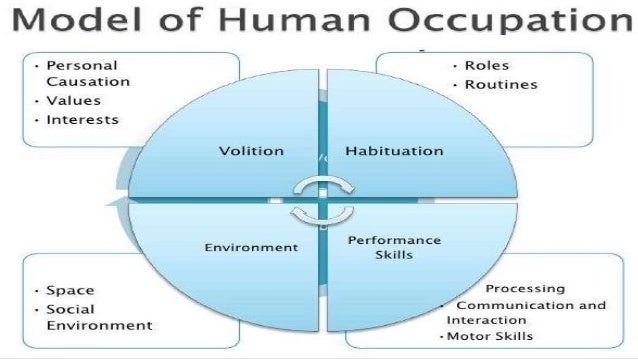
Most people think the Model Of Human Occupation Screening Tool is a quick checklist you hand a patient and walk away from. That's wrong. It's structured enough that it takes about 20 to 30 minutes per administration, and if you rush through it, you're just generating noise. I've seen it happen. The tool is built on Gary Kielhofner's Model of Human Occupation framework, and it measures four domains: volition, habituation, performance capacity, and environment. Each domain feeds into how a client actually shows up for daily occupation, and the screening is supposed to tell you where the breakdown is. Here's the practical reality. You can find the current version, the MOH-SOT-2, through the publisher or your university library's clinical databases. Some institutions have it sitting behind a paywall or a membership gate, which is standard for therapy assessment tools. If you're a student or working at a clinic without a subscription, check with your department first. The cost isn't trivial, and you don't want to spend money only to find out your organization already has a license.
Model Of Human Occupation Screening Tool Administration
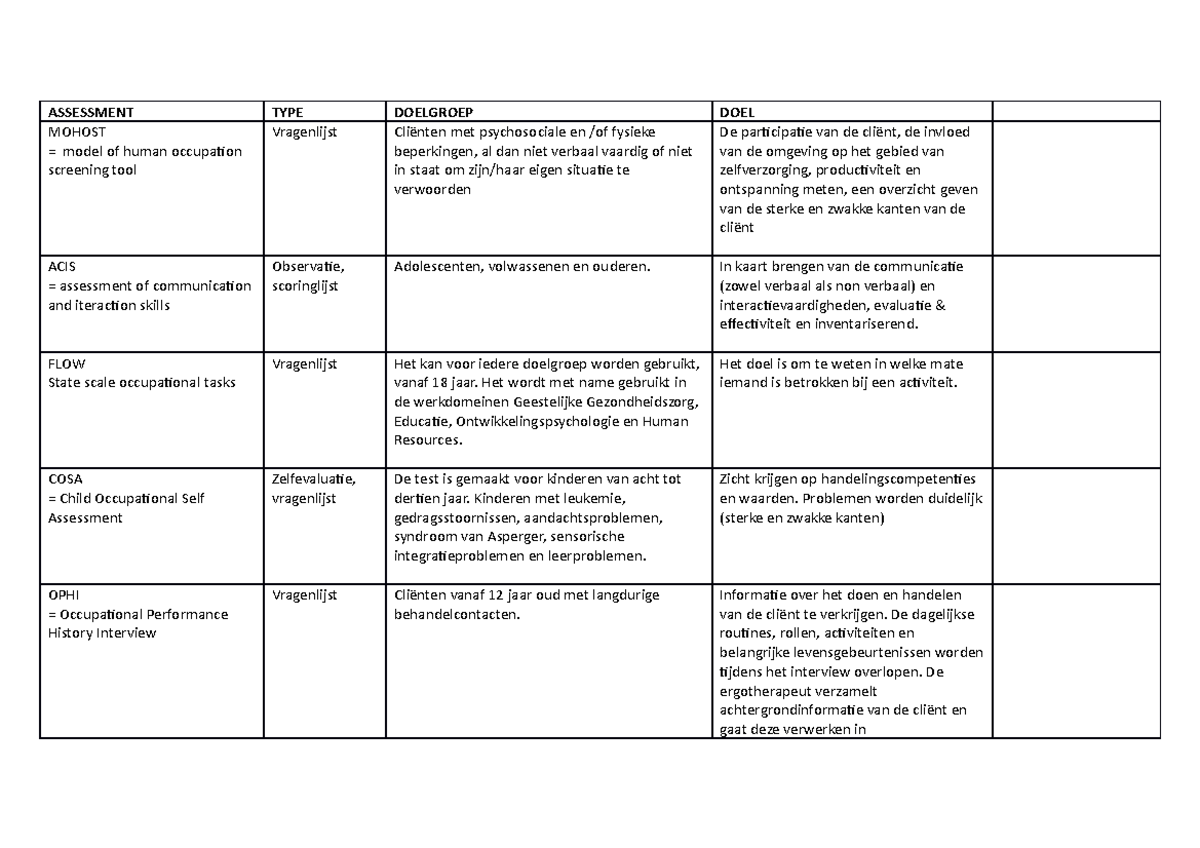
The screening itself is semi-structured. You're interviewing the client, not just handing them a paper. You ask questions that probe their motivation, their routines, their past skills, and the physical and social spaces they move through. The client responds, you score each item, and the output gives you a profile across the four domains. It's not a diagnostic instrument. It's a screening tool, which means its purpose is direction, not certainty. I remember working with a client who had traumatic brain injury and mild aphasia. The MOH-SOT assumes reasonable verbal self-report ability. This person couldn't reliably describe their own routines or volitional patterns. I tried pushing through anyway, which was a mistake. The scores came back looking flat across every domain, which read like global impairment, but that wasn't the picture. What actually happened was the language barrier was flattening the data. The workaround was to supplement the screening with collateral interviews — family members, previous therapists — and then interpret the MOH-SOT results as a lower bound rather than a ceiling. The tool wasn't failing. I was applying it outside its intended population without adjusting my interpretation. The domains break down like this. Volition covers what a person wants and values, their causal self-perceptions, and their interests. Habituation covers roles, routines, and habits that organize behavior. Performance capacity is about the actual sensory, cognitive, and motor abilities someone brings to a task. Environment covers the physical and social context that either enables or blocks action. These aren't isolated. A breakdown in one shows up in another. That's why the screening is designed to look at the system, not just a single deficit.
One thing beginners miss is that the tool doesn't measure severity. It identifies patterns. If you're looking for something that grades impairment level, this isn't it. You need a different instrument for that. The MOH-SOT will tell you where the occupational problem likely sits — motivation, routine, capability, or environment — but it won't quantify how bad it is. Pair it with a measure like the Functional Independence Measure or the Berg Balance Scale depending on your clinical picture. Another nuance. The performance capacity domain is frequently underweighted in analysis. Clinicians tend to focus on volition and habituation because those produce more interesting interview material. But performance capacity is often the bottleneck. A client can have strong volition and solid routines and still fail to execute because of unaddressed sensory or motor limitations. When I review MOH-SOT profiles that look contradictory — high volition, low performance capacity — I don't assume the client is noncompliant. I assume I need to dig deeper into the performance capacity section with objective measures, because the screening alone won't show me the full story. The scoring itself uses a Likert-type format for most items. You assign values based on client response, and the totals generate a profile graph. Some sites offer a scoring key or calculator if you buy the manual. Others expect you to tally manually. Neither is particularly time-consuming once you've done it three or four times. After that, the scoring becomes almost automatic. The real time sink is the interview, not the math.
Get the Full Details
There are situations where this tool just doesn't work. Severe cognitive impairment, acute psychiatric episodes, lack of insight, language barriers without translation support. In those cases, forcing the MOH-SOT through produces unreliable data. I'd rather spend the extra time on a collateral-informed assessment or a different standardized tool than to submit a screen that looks clean on paper but is clinically meaningless. The tool is valid when it's used appropriately. That phrase matters more than people usually admit. If you're studying for certification or preparing for clinical rotation, start with the manual before you touch the screen. Read the rationale behind each domain. Understand why Kielhofner structured it this way. The tool makes more sense when you know the theory, not less. Running it blind will teach you how to calculate scores but not how to interpret them. That's the difference between someone who knows the MOH-SOT and someone who understands what it actually tells you.