The Practical Differences Between Hybridoma and Serum-Derived Reagents
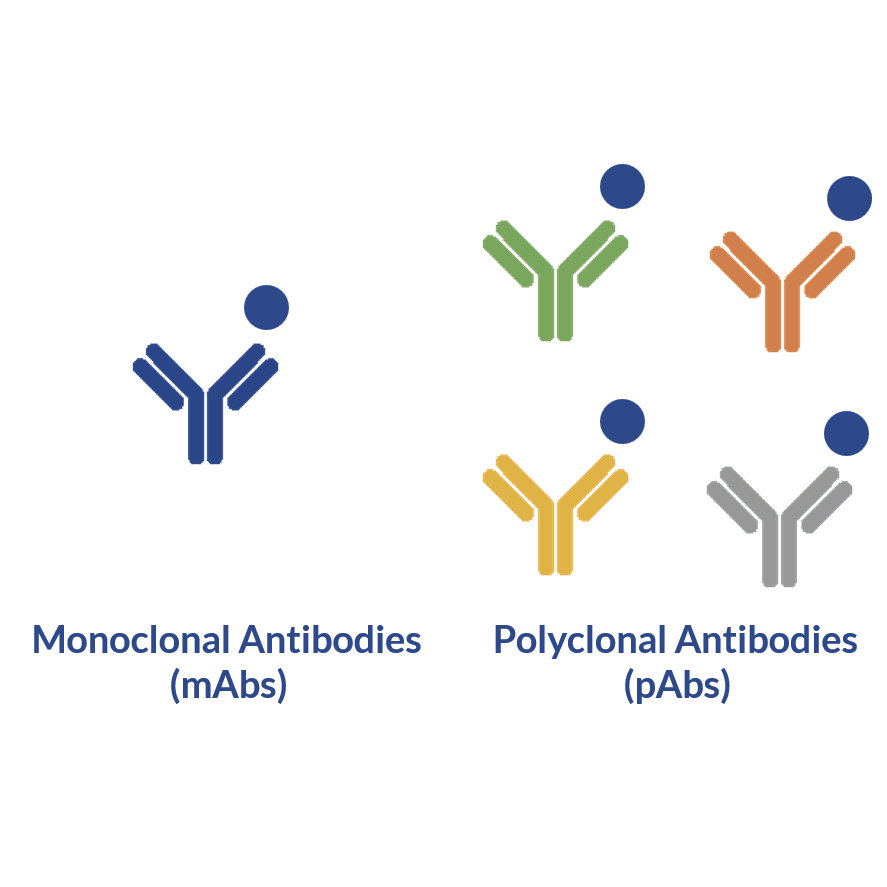
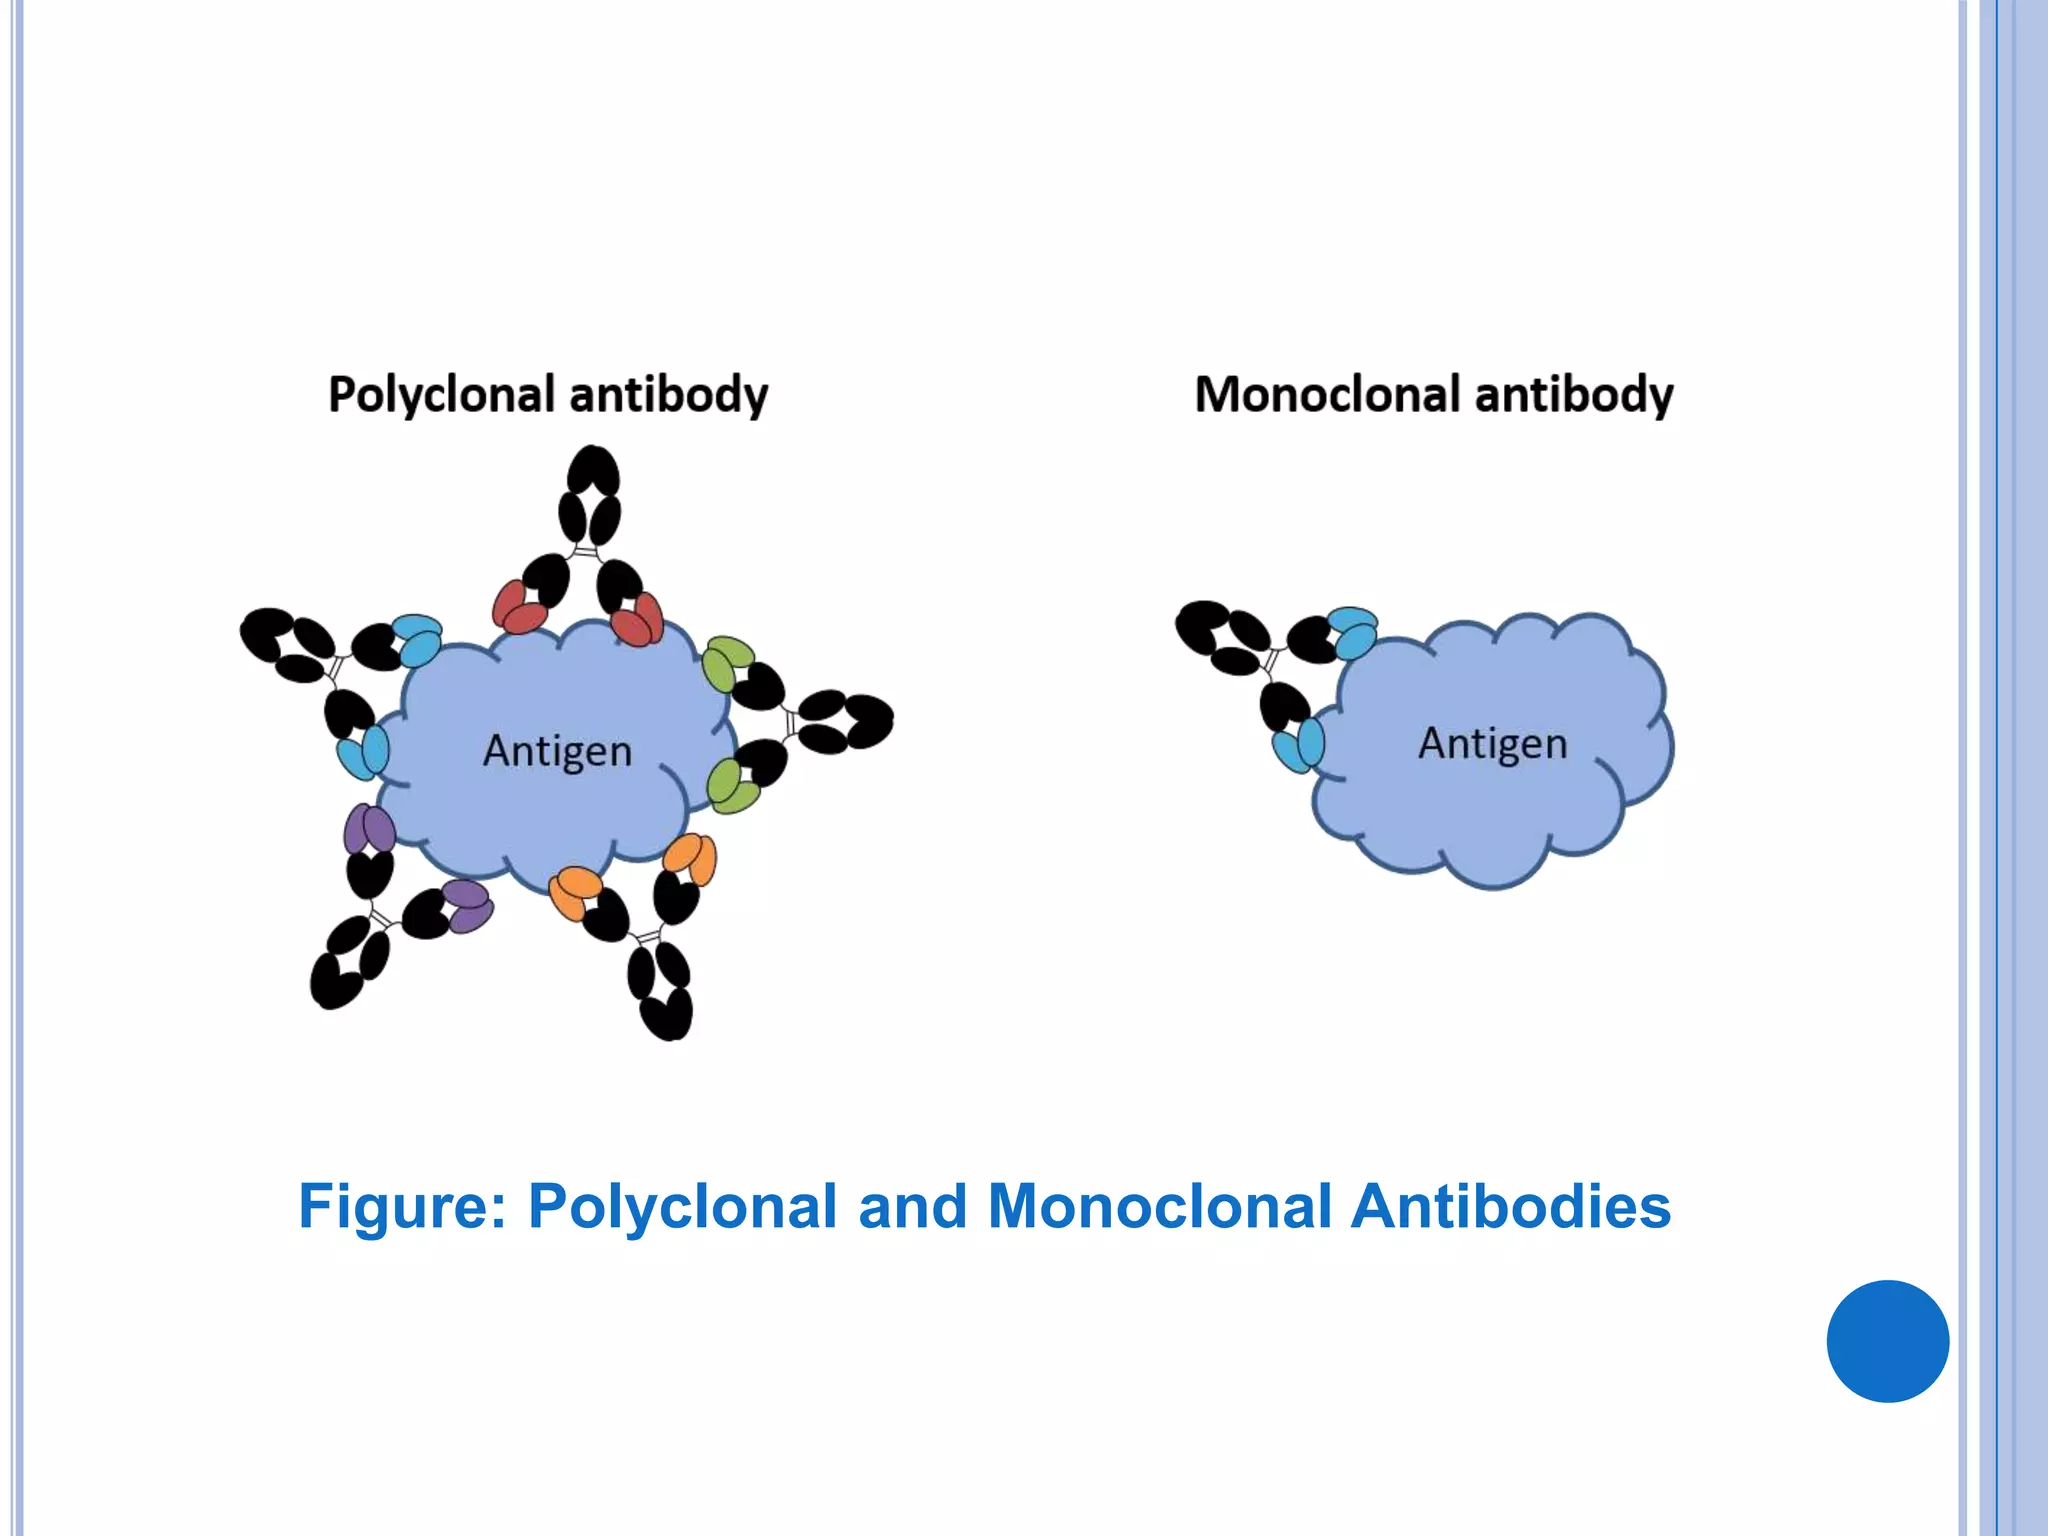
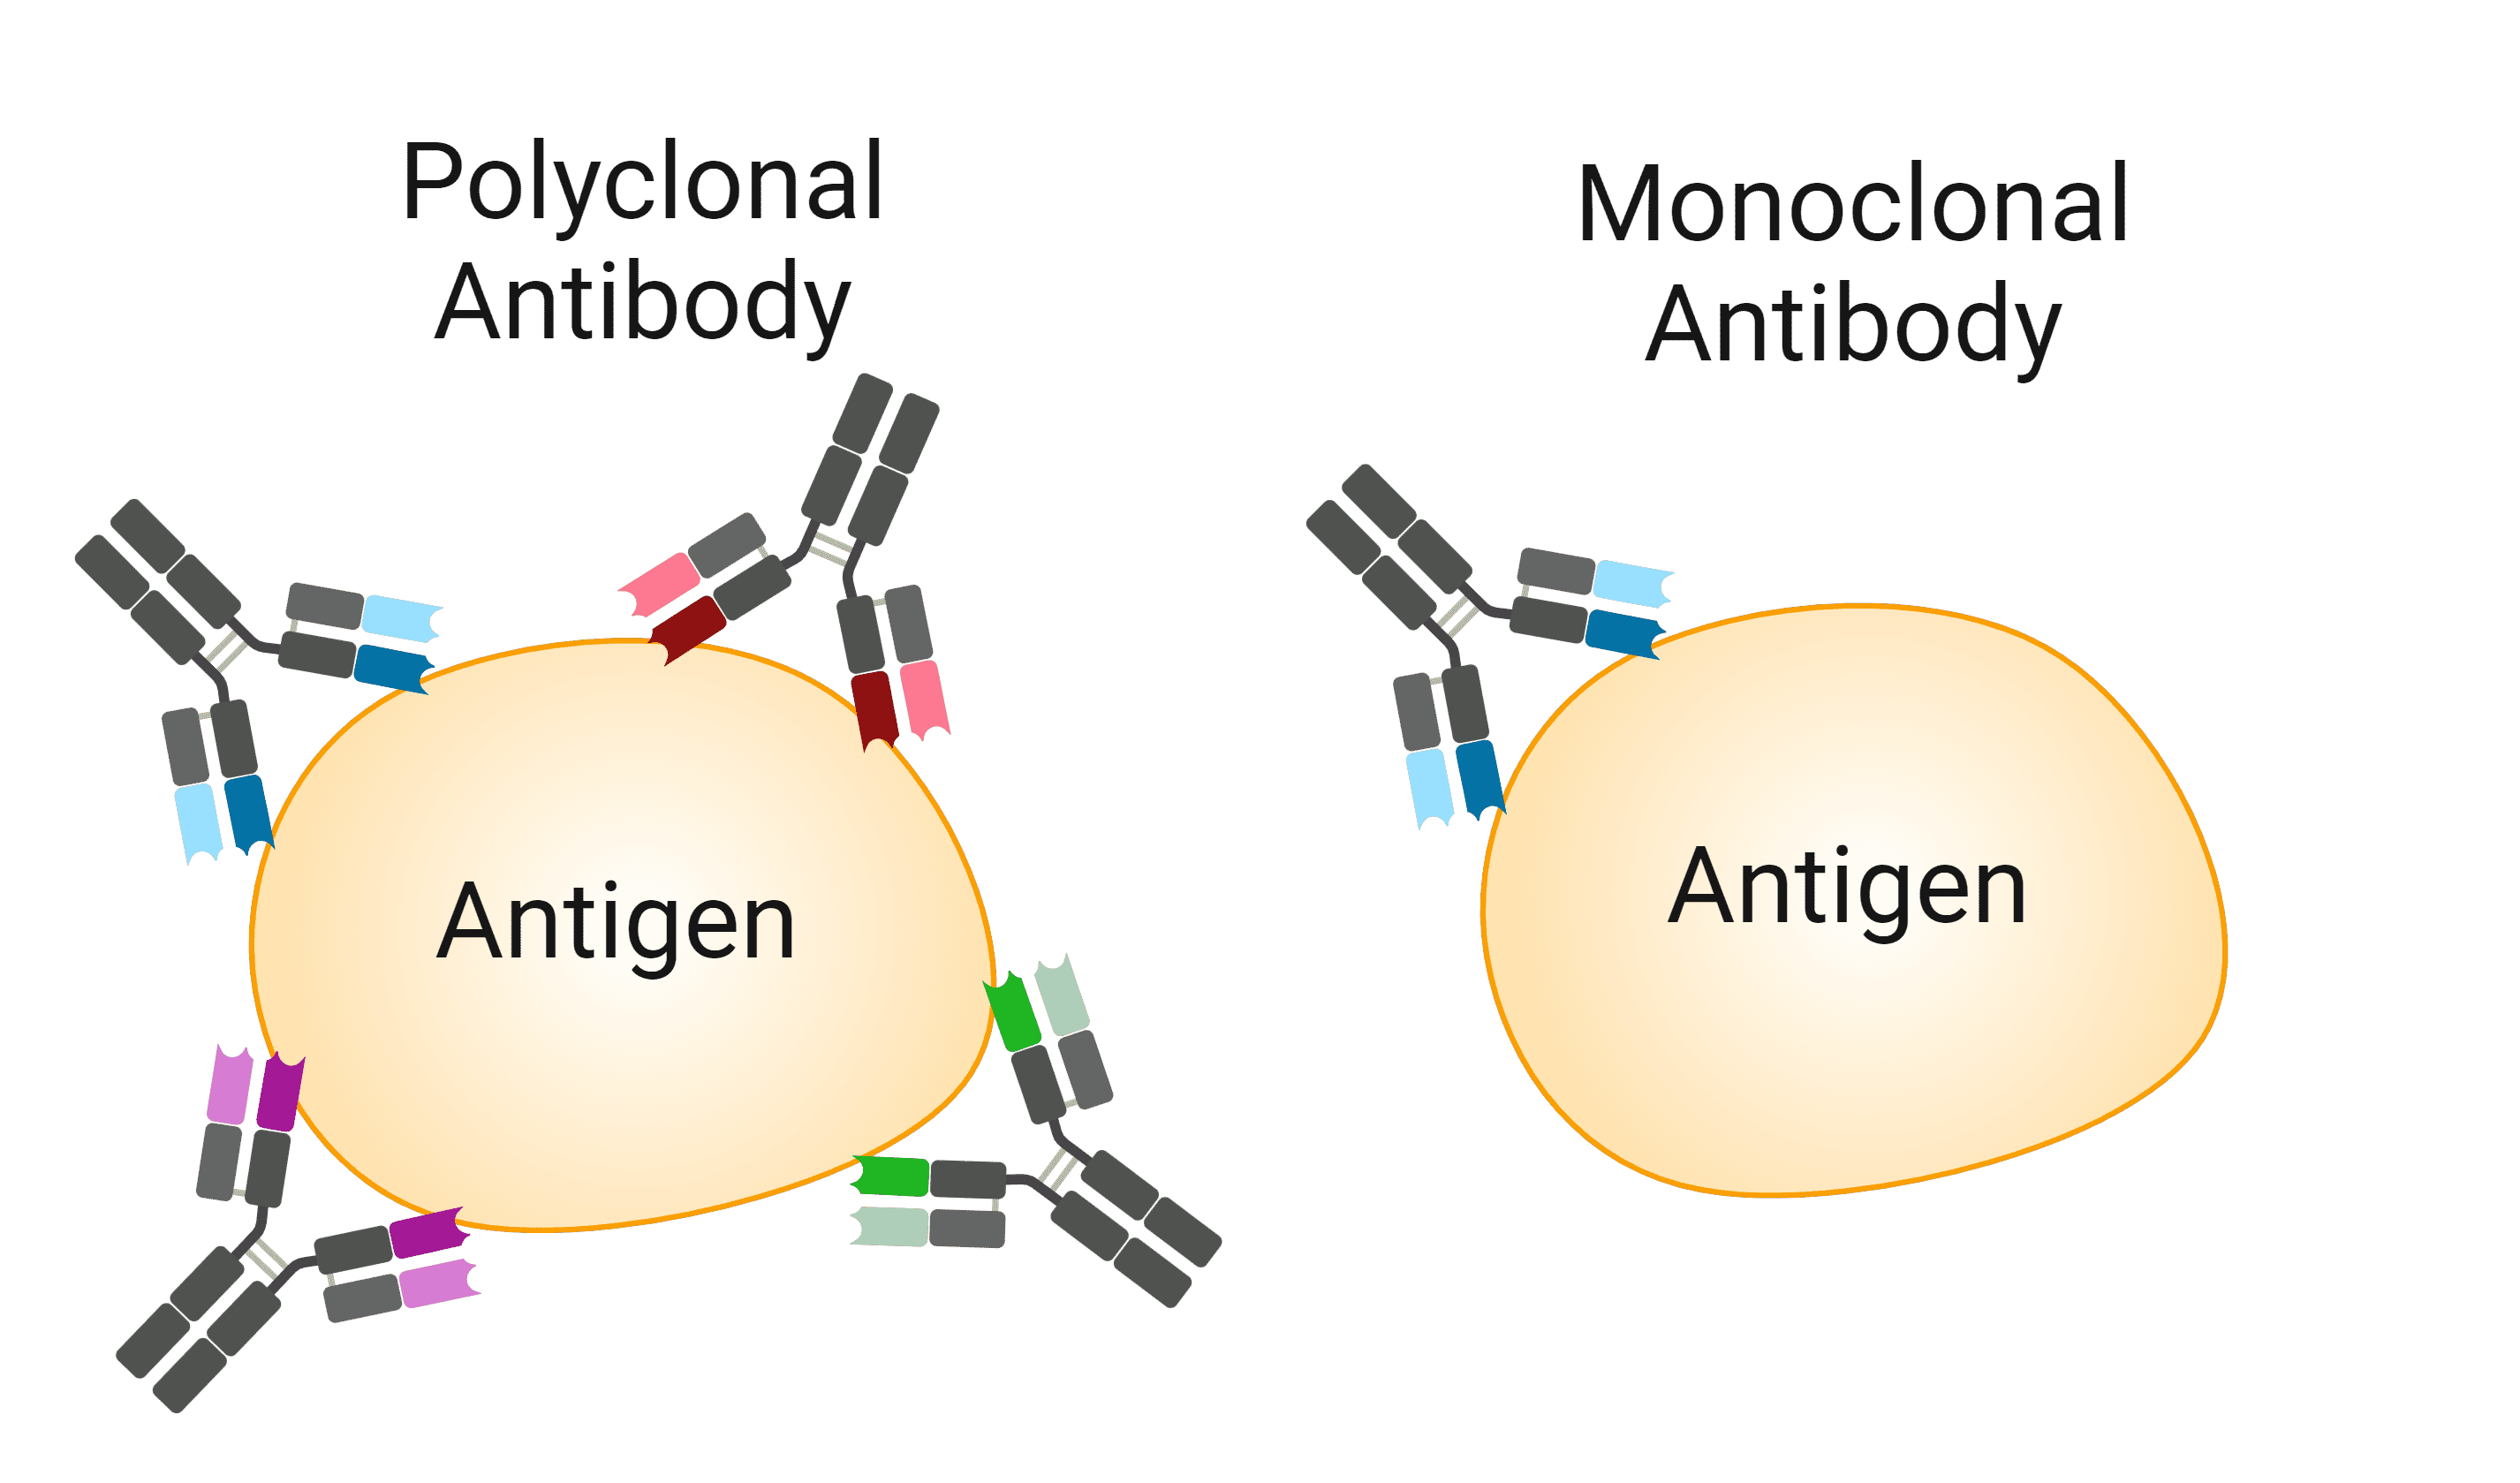
I spent years running immunoblots and ELISAs before I really understood why my results kept becoming inconsistent. The issue usually came down to one thing: I wasn't thinking carefully enough about what kind of antibody I was using. Monoclonal And Polyclonal Antibodies serve different purposes, and confusing them is one of the fastest ways to waste months of work. Polyclonal antibodies are exactly what they sound like. You inject an animal with your antigen, wait for the immune response, and harvest the serum. That serum contains thousands of different antibodies, each targeting a slightly different epitope on your protein of interest. They bind broadly. They're generally easier and cheaper to produce, and they often give stronger signals in detection assays because multiple binding events amplify the readout. But that same breadth means batch-to-batch variability. The antibody from one rabbit won't look exactly like the antibody from the next rabbit, even if you immunize them with the identical protein prep. Monoclonal antibodies come from a single B-cell clone. You fuse that B-cell with a myeloma cell, create a hybridoma, and that hybridoma becomes an immortal line producing one specific antibody against one specific epitope. The result is extremely consistent across batches. Once you have the hybridoma stored in liquid nitrogen, you can pull it out five years later and get the exact same reagent. That reproducibility matters enormously when you're submitting data to reviewers or trying to replicate a colleague's experiment.
Choosing Between Monoclonal And Polyclonal Antibodies for Your Application
Here is the part most people gloss over. Monoclonals are not automatically better. They have real weaknesses that make them unsuitable for certain applications, and I learned this the hard way during a project where I switched from a polyclonal to a monoclonal without adjusting my protocol. I was doing immunohistochemistry on frozen tissue sections. My polyclonal was working beautifully at a 1:2000 dilution, giving crisp membrane staining. I switched to a monoclonal against the same target because I needed batch consistency across a long-term study. Same dilution, same protocol, same tissue. The signal dropped to almost nothing. What I had failed to account for is that the monoclonal recognized an epitope that was partially masked by the formalin fixation process, while the polyclonal had other clones in its mixture that recognized denatured or conformational epitopes still accessible after fixation. I ended up having to test three different monoclonals before finding one that worked, and that cost me roughly six weeks of stalled experiments. That experience taught me something important. If your application involves native, folded protein and you need strong signal amplification, polyclonals often outperform monoclonals. Western blots are a different story. Denatured proteins expose linear epitopes, and monoclonals tend to perform very well here, especially when you need specificity. Cross-reactivity is a genuine risk with polyclonals because some of the antibodies in the mixture will bind to unrelated proteins that share sequence homology with your target. I once had a polyclonal that gave a clean band at the expected molecular weight and then three strong bands at completely different sizes. The manufacturer hadn't fully adsorbed the serum against related family members, and those cross-reacting antibodies were the ones causing the extra bands.
For quantitative work like ELISA or flow cytometry, monoclonals are usually the safer choice. The consistent affinity and specificity mean your standard curve actually means something. Polyclonals can work fine here too, but you need to validate each new batch, which adds time and cost. If you're buying off the shelf from a commercial vendor, they typically test and certify each polyclonal lot, but even then, the inherent variability means you should never assume a new lot will perform identically to the old one without running a side-by-side comparison first. Production timelines matter more than people realize. A polyclonal can be ready in about eight to twelve weeks from immunization to purified product. A monoclonal requires hybridoma generation, cloning, screening, and scale-up, which typically takes four to six months before you have a usable batch. If you're on a tight deadline, that difference can be decisive. However, once the monoclonal is established, you never have to go through that process again. The hybridoma is a permanent resource. Cost is another practical consideration. Polyclonals usually run between three and eight hundred dollars for a purified 0.1 mg vial. Monoclonals are more expensive upfront, often ranging from five to fifteen hundred dollars for the same quantity, because of the longer development process and the need for extensive screening. But if you need the same antibody for three years of ongoing experiments, the monoclonal becomes cheaper per experiment because you eliminate the variability cost and the need for repeated validation.
Get the Full Details
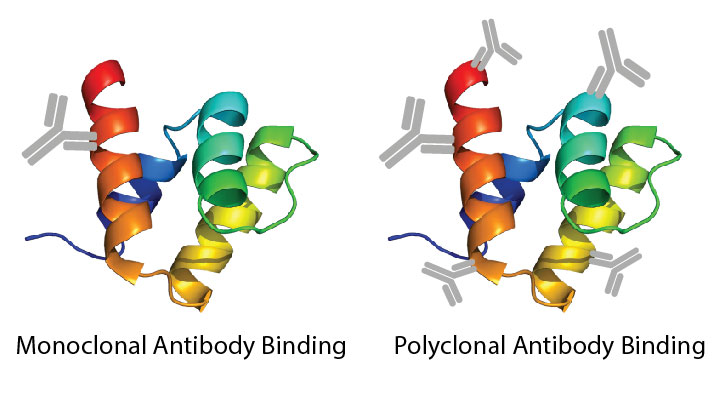
There is a middle ground worth mentioning. Chimeric antibodies and recombinant single-chain fragments give you monoclonal-style specificity with some of the flexibility of polyclonals. These are engineered in vitro rather than produced in animals, and they avoid the immunological variability entirely. The downside is that they require more specialized expertise to develop and are significantly more expensive to produce at scale. When I'm advising junior researchers now, I tell them to start with the application, not the antibody type. Ask what epitope your method preserves, how much batch consistency you actually need, what your timeline looks like, and whether your target protein has family members that could cause cross-reactivity. Then pick the reagent that fits those constraints. Starting with whichever one sounds more rigorous in a textbook will cost you time and money in practice.