What I Actually Use When I Need to Keep Up With Drug Mechanisms
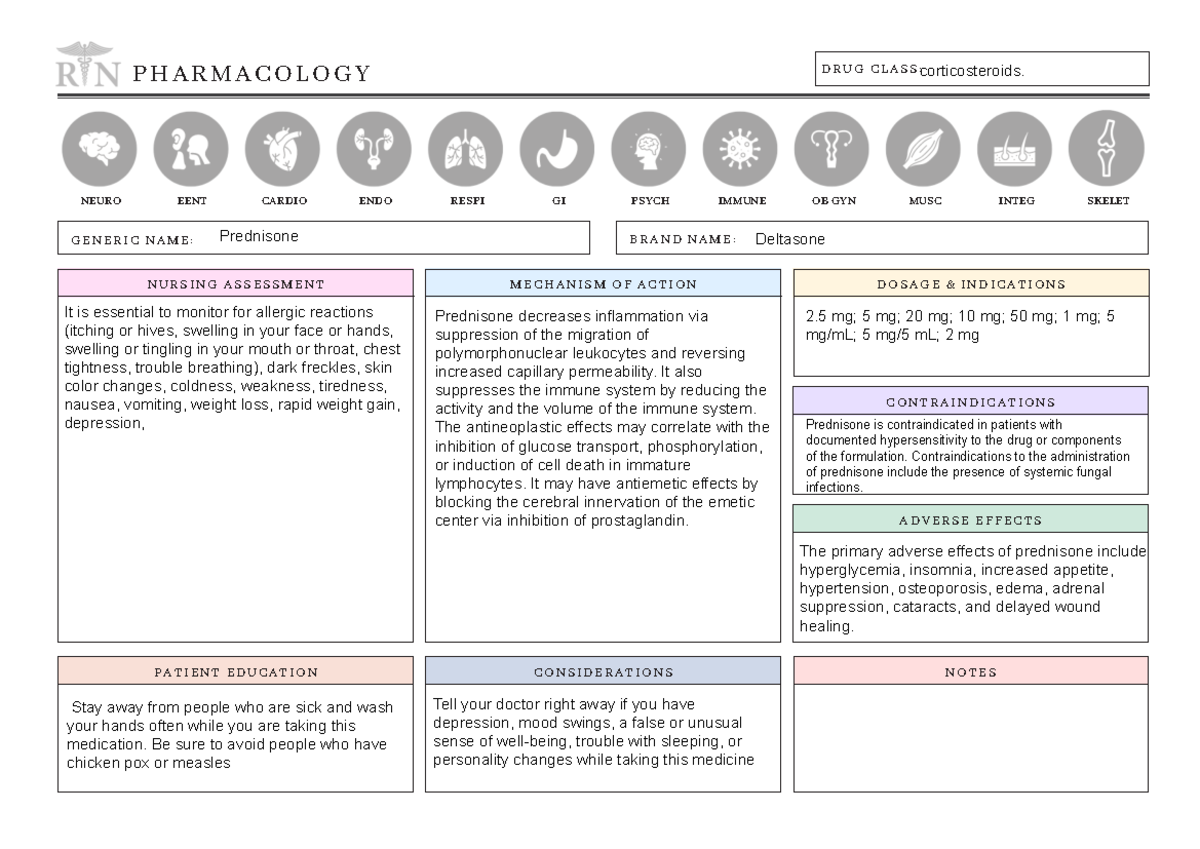
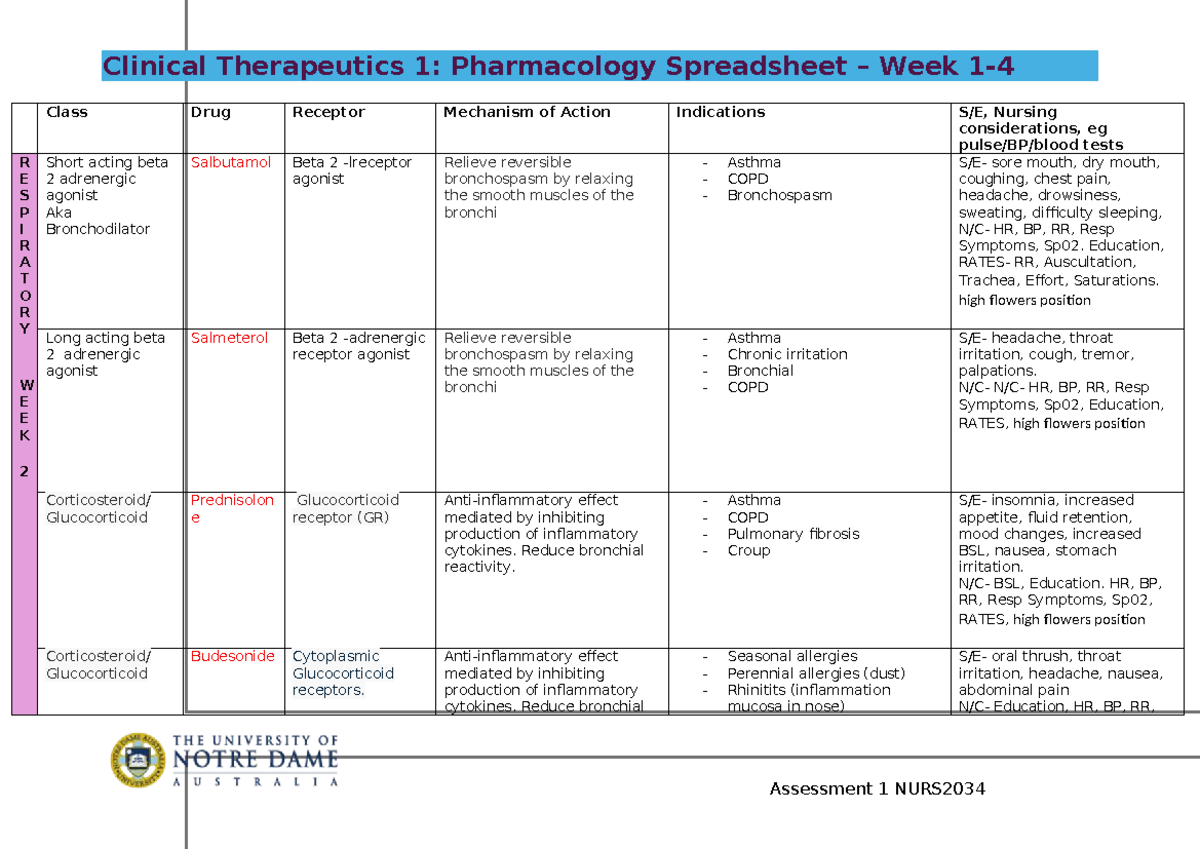
I stopped trying to memorize entire pharmacology textbooks back in my second year of residency prep. The sheer volume is impossible, and most of what you'd cram gets lost within weeks anyway. Instead, I settled on a system built around Monthly Pharmacology Examples — a curated approach where each month focuses on a specific drug class, key mechanisms, and clinical applications tied together with real case scenarios. It sounds simple, but the execution matters more than the concept. The format varies depending on who produces them, but the useful ones share a few traits. You get a focused drug class — say, ACE inhibitors one month, direct oral anticoagulants the next. Each resource breaks down mechanism of action, pharmacokinetics, common adverse effects, and at least one clinical vignette that forces you to apply the knowledge rather than just recognize it. The best versions also include dose adjustments for renal impairment, which is where most students get tripped up on actual board exams. I found that the monthly cadence actually works better than binge-studying a whole class at once. Spaced repetition isn't just a buzzword here. When you review ACE inhibitors in October and then encounter them again while studying ARBs in November, your brain makes a stronger connection between the two because the time gap forces retrieval practice. That's the core mechanic behind why this system sticks.
Where I've Run Into Problems
Not every Monthly Pharmacology Examples resource is worth your time. I wasted about three weeks on a set that claimed to cover cardiovascular drugs but mostly repeated the same metoprolol case study with minor modifications. Red flags I watch for now: resources that don't list their sources, ones that haven't been updated since 2019, and anything that presents drug interactions as bullet points without explaining the underlying mechanism. If a resource tells you warfarin interacts with antibiotics but doesn't explain that it's primarily through CYP2C9 inhibition and vitamin K disruption, it's not teaching you — it's giving you something to parrot. I also learned the hard way that some Monthly Pharmacology Examples sets conflate half-lives across different formulations. A sustained-release formulation of a drug can have a dramatically different pharmacokinetic profile than the immediate-release version, and several free resources I found glossed over this distinction entirely. When I was prepping for Step 2, this came back to bite me on a question about digoxin toxicity timing — the answer depended on whether the formulation was IV or oral extended-release, and the study set I'd been relying on never mentioned both.
How to Build Your Own if You Can't Find Good Ones
If the available Monthly Pharmacology Examples aren't matching what you need, making your own takes about 90 minutes per drug class and pays off for the rest of your career. Here's what my process looks like. Step one: Pick your drug class and pull the Top 50 drug list from the current edition of the drug formulary your program uses. Don't use an outdated reference — I learned that the 2020 edition still listed certain SSRI dosing recommendations that changed in 2021, and I nearly built a study set around obsolete information. Step two: For each drug, write three things on separate index cards or in a structured note. The mechanism — one sentence, no fluff. The key side effect — the one that shows up on exams, not the rare case report from a dermatology journal. And a clinical scenario — a brief patient presentation that requires you to choose the right drug and justify it. I keep the scenarios real enough that they match what you'd see in clinical rotations. Something like a 67-year-old with atrial fibrillation, CHF, and stage 3 CKD needing anticoagulation. That single scenario touches on drug selection, renal dosing, and monitoring parameters.
Get the Full Details

Step three: Cross-reference everything against at least two sources. If one says a drug is primarily renally excreted and another says hepatic, figure out which is correct before you commit it to memory. I used Good Pharma and the FDA labels for this during residency prep, though some people prefer the clinical pharmacology database. Either way, two-source verification catches the kind of errors that slip into free study materials. Step four: Put your cards or notes into Anki or a similar spaced repetition tool. Don't skip this step. I used to think I understood a drug class until I tried recalling it under timed conditions, and that's when the gaps became obvious. The act of forcing retrieval, not just recognition, is what moves information from short-term to long-term memory. This usually cuts the process down from 2 hours to about 15 minutes per drug class once you've built your initial set, though setting up the first set takes longer because you're creating content from scratch.
What Most People Miss About Pharmacology Retention
The counter-intuitive part about studying pharmacology effectively is that grouping drugs by chemical structure is almost always the wrong approach for clinical purposes. You'll find resources that organize benzodiazepines by their chemical class — diazepam with the long-acting ones, lorazepam with the intermediate — but that's useful for organic chemistry, not for choosing a sedative for a patient with liver cirrhosis. The clinically relevant grouping is by half-life and metabolism pathway. Lorazepam, oxazepam, and temazepam are grouped together as LOT drugs precisely because they bypass Phase I metabolism, which is the detail that actually matters when you're prescribing for an elderly patient with compromised liver function. Another thing that catches people off guard: understanding drug interactions at the receptor level matters more than memorizing interaction lists. When you know that macrolide antibiotics inhibit CYP3A4, you can predict interactions with statins, calcium channel blockers, and immunosuppressants without having to look each one up. The interaction list approach breaks down the moment you encounter a drug your source material never covered. The mechanism approach works for every drug you'll ever prescribe, including the ones invented after your textbook was published.
Where This System Falls Short
Monthly Pharmacology Examples won't make you an expert. They'll make you competent for exams and safe for initial clinical practice, but there are gaps you'll only fill through actual patient exposure. I knew the mechanism of heparin-induced thrombocytopenia backwards and forwards from my study sets, but I had no real sense of how quickly platelet counts could drop until I saw a case in the hospital where the Heparin appeared harmless on paper but caused a catastrophic event in practice. No study set replicates that visceral understanding. The system also assumes you have access to current, accurate source material. If you're using outdated pharmacy references or AI-generated content without verification, you're building your knowledge on shifting ground. I've seen too many students trust whatever pops up in a search and then get confused when their knowledge conflicts with what attending physicians actually do in clinical practice. Pharmacy databases and official FDA labeling are your baseline — everything else is supplementary. Finally, pharmacology is cumulative. The monthly structure helps with organization, but you will forget things from earlier months if you don't maintain a review cadence. I kept a weekly review habit where I'd cycle through one set from each of the previous three months, and that alone prevented most of the decay that would otherwise happen. Without that maintenance layer, the monthly system becomes a series of isolated facts rather than an integrated knowledge base.