How to Actually Use a Monthly Pharmacology Worksheet Without Losing Your Mind
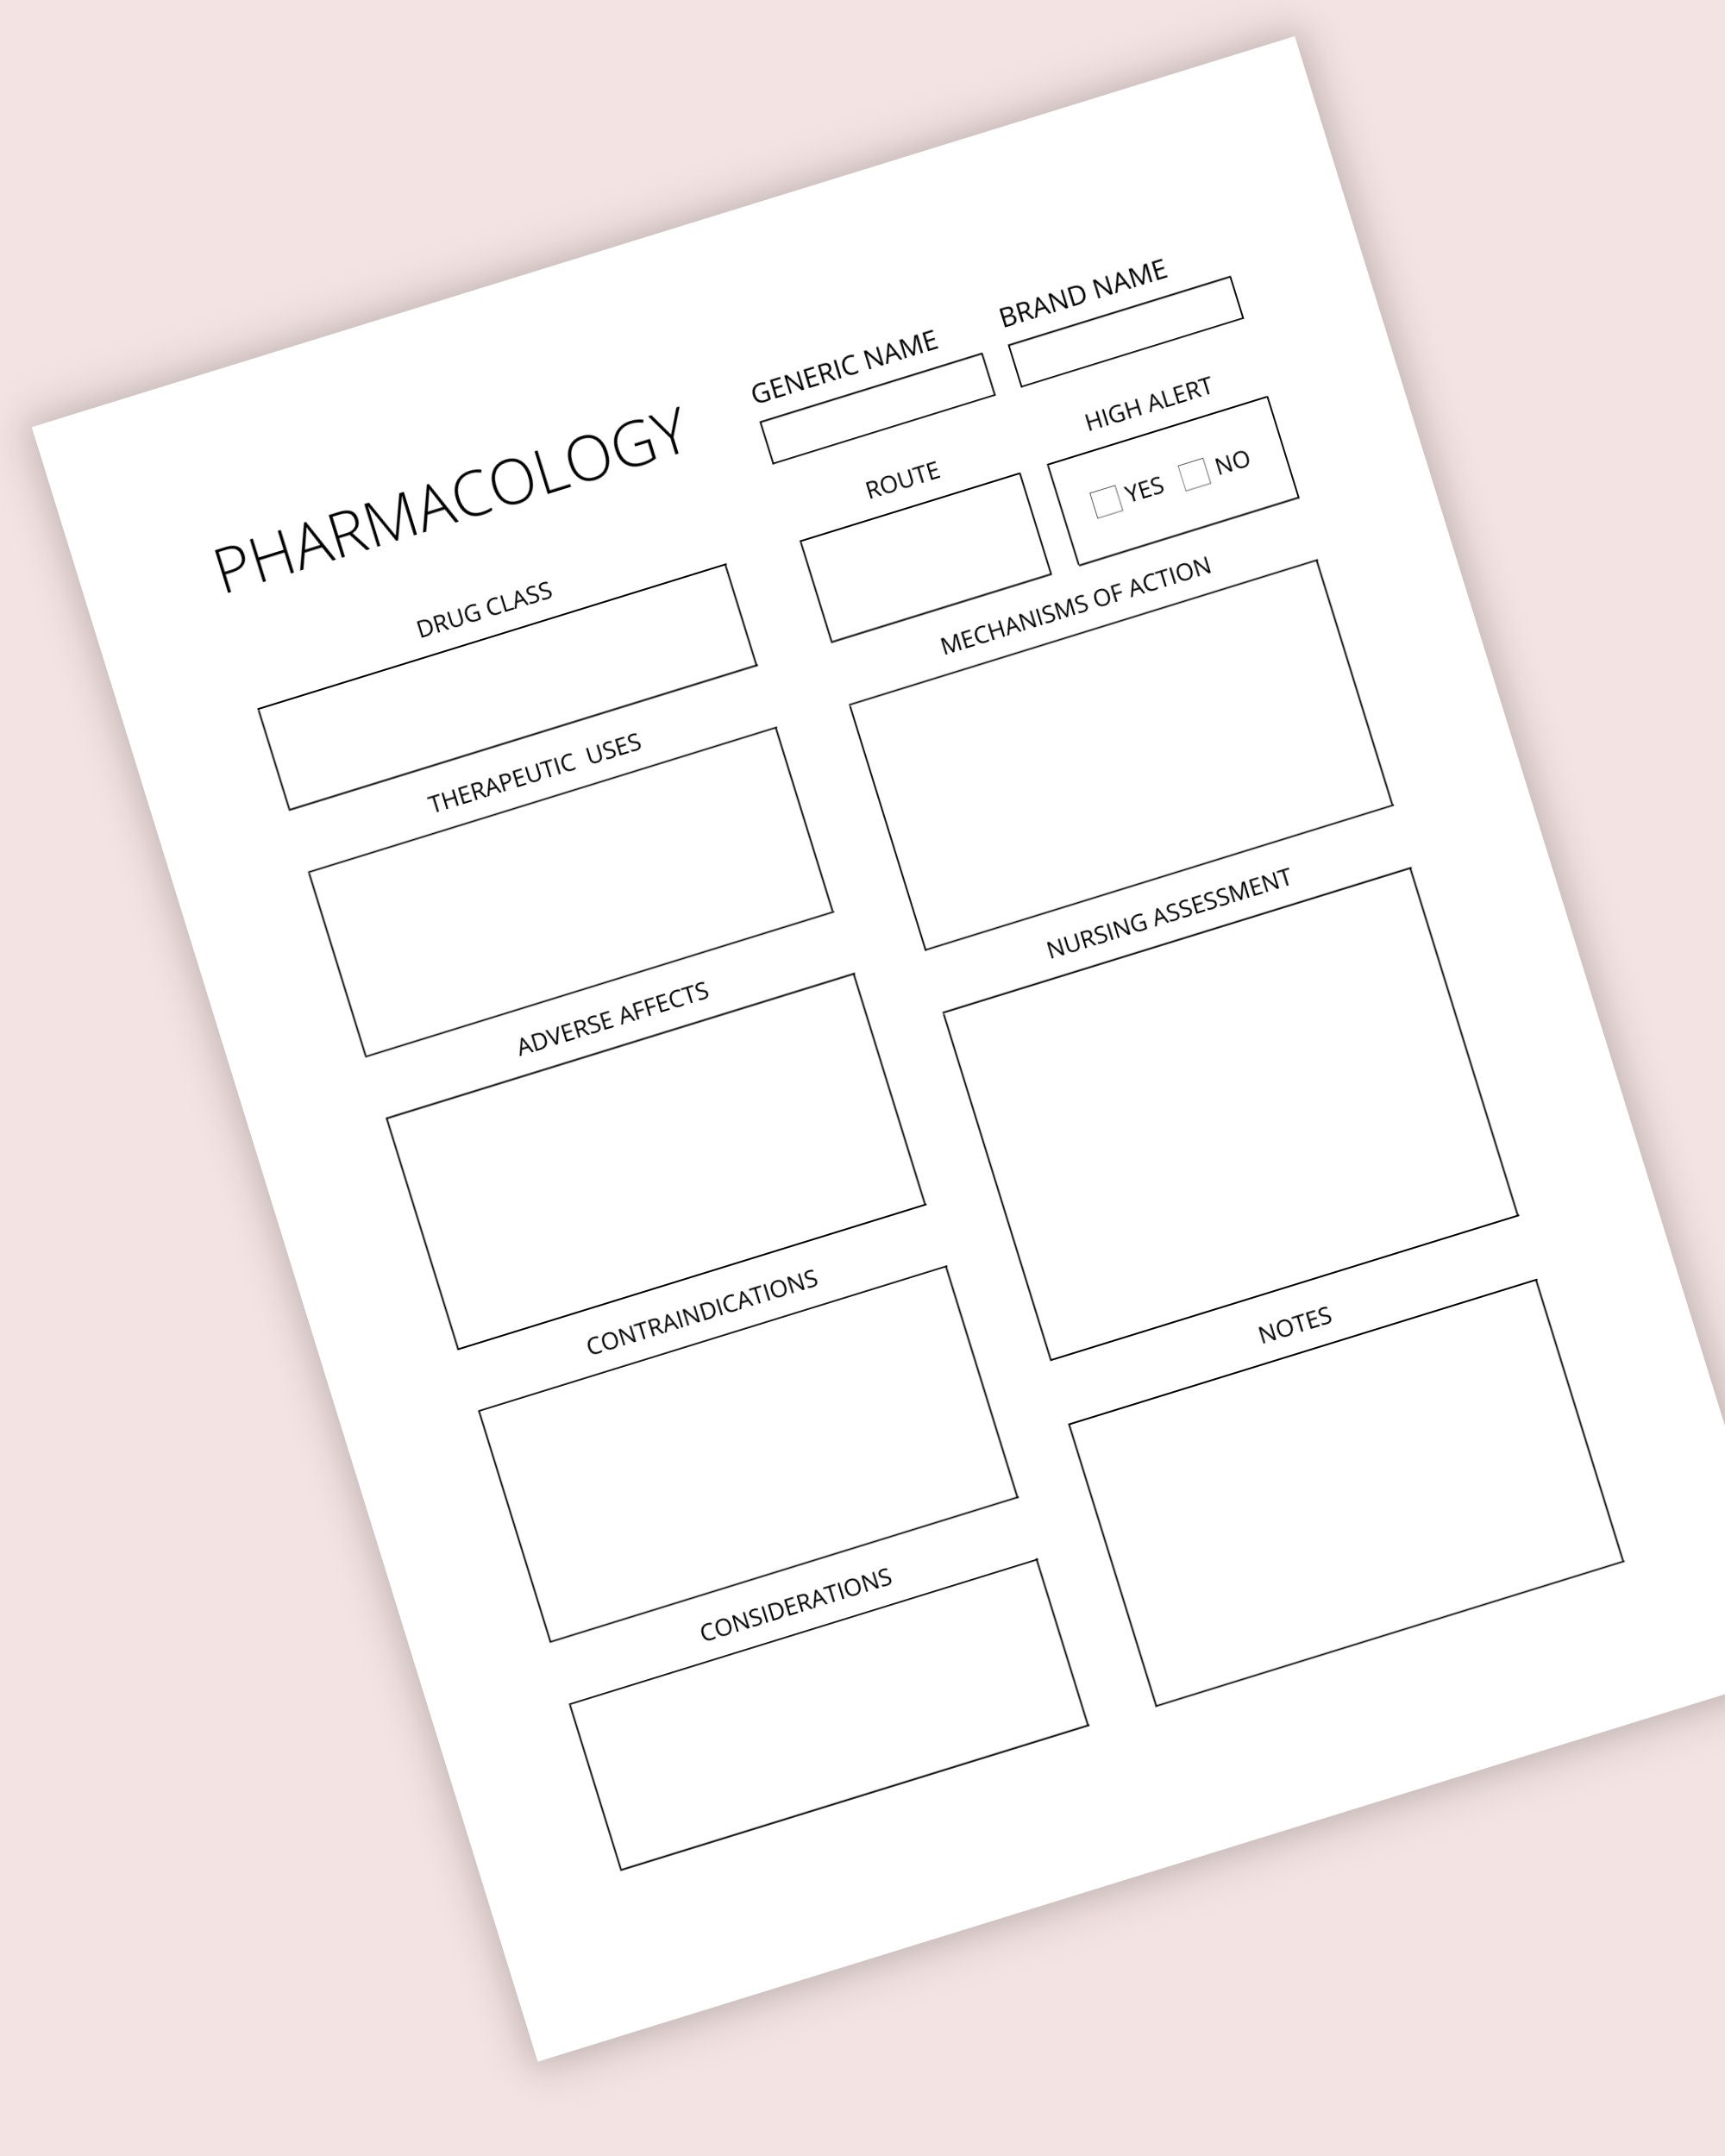
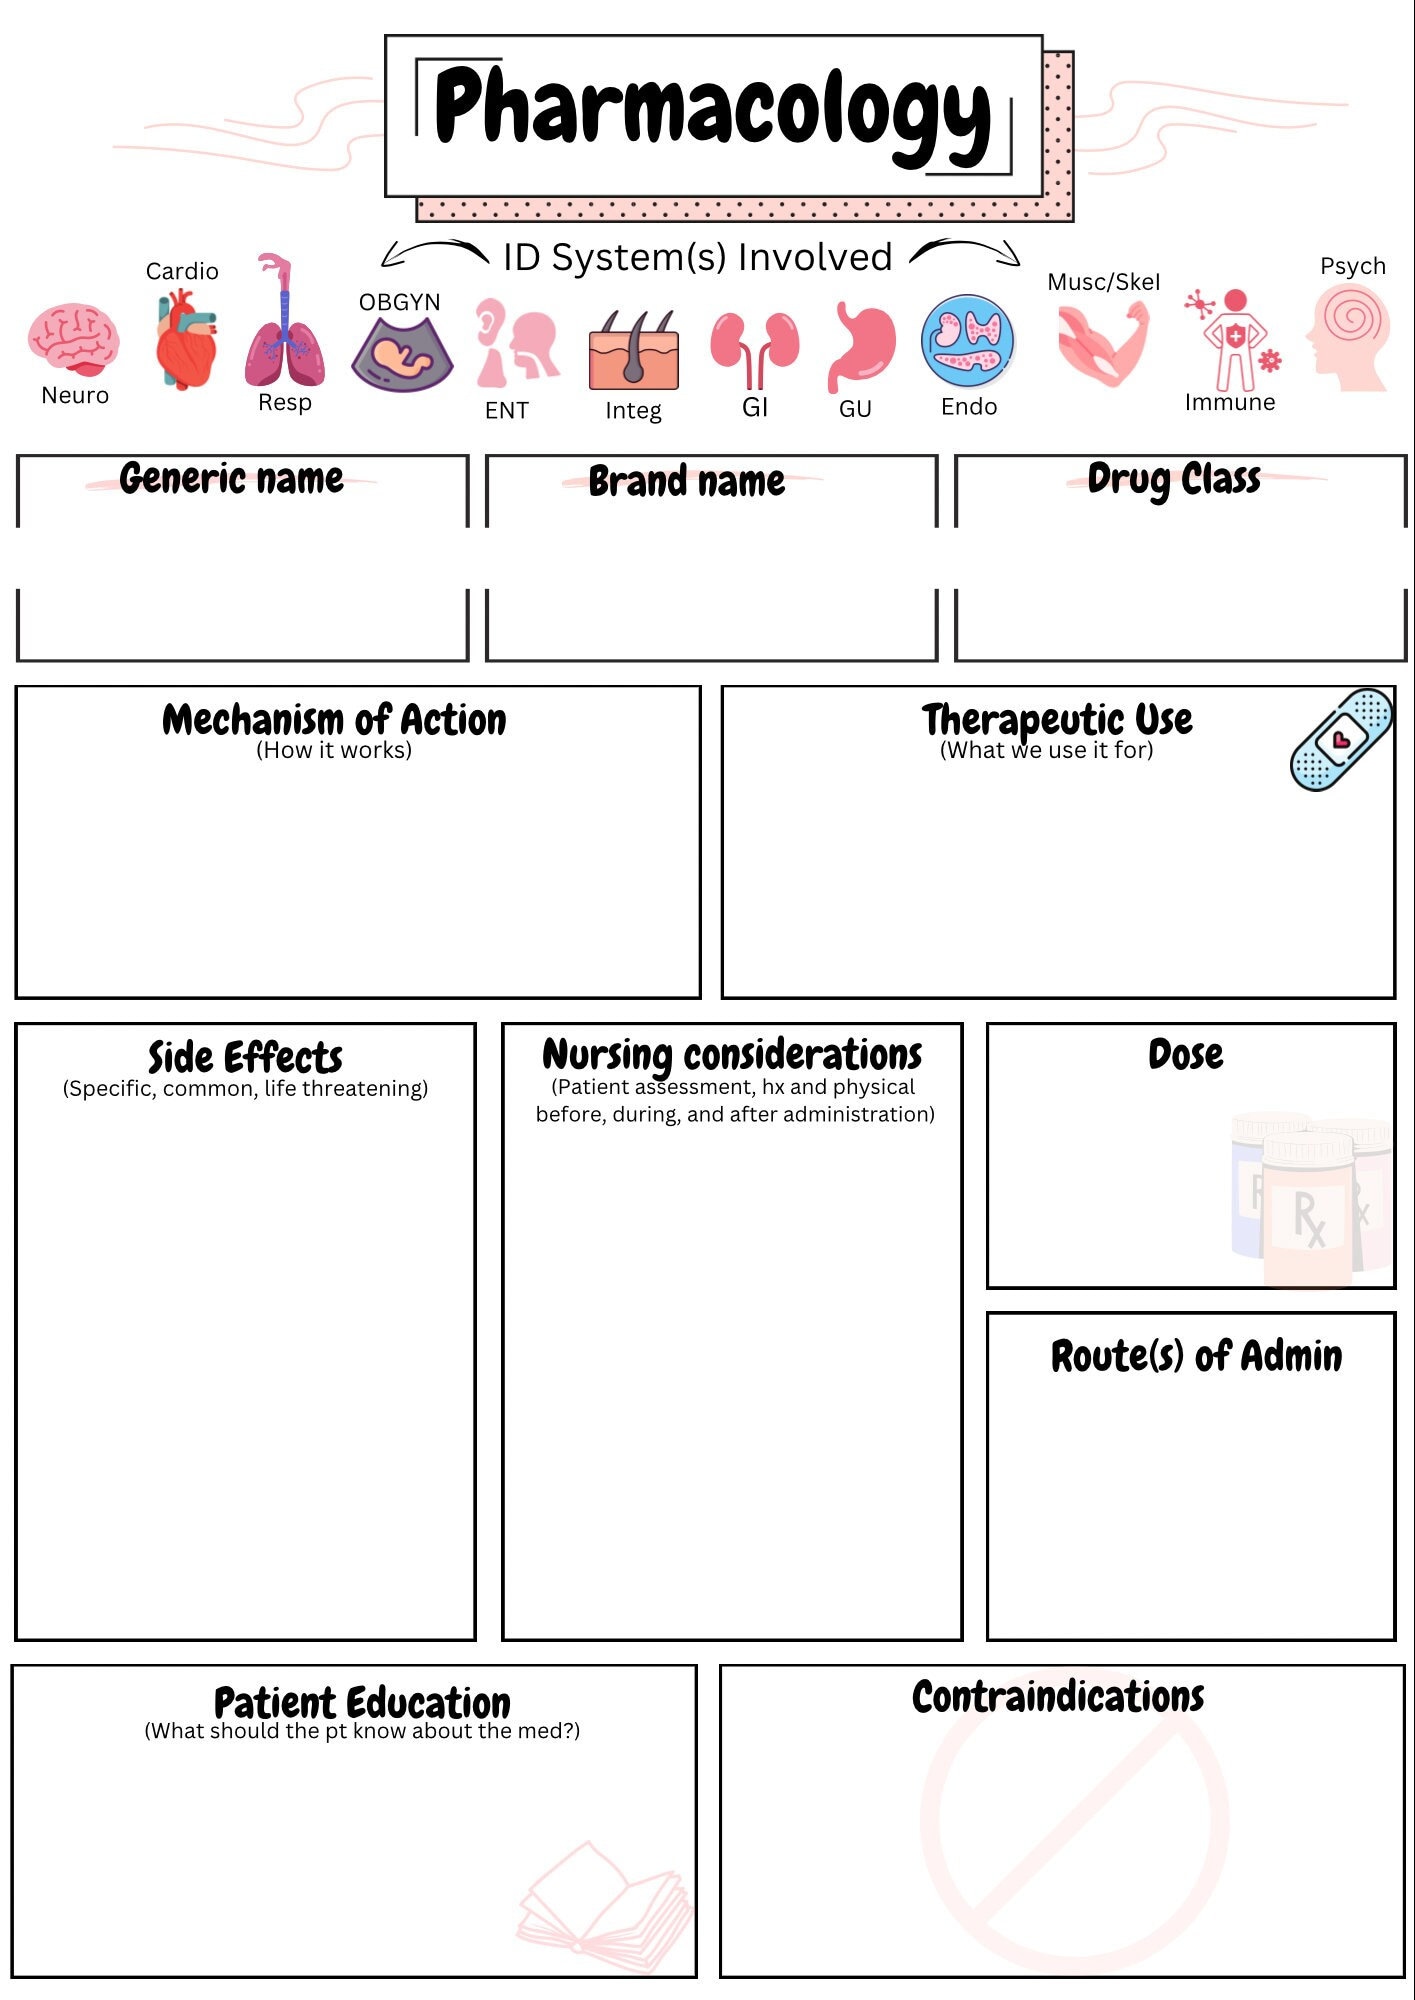
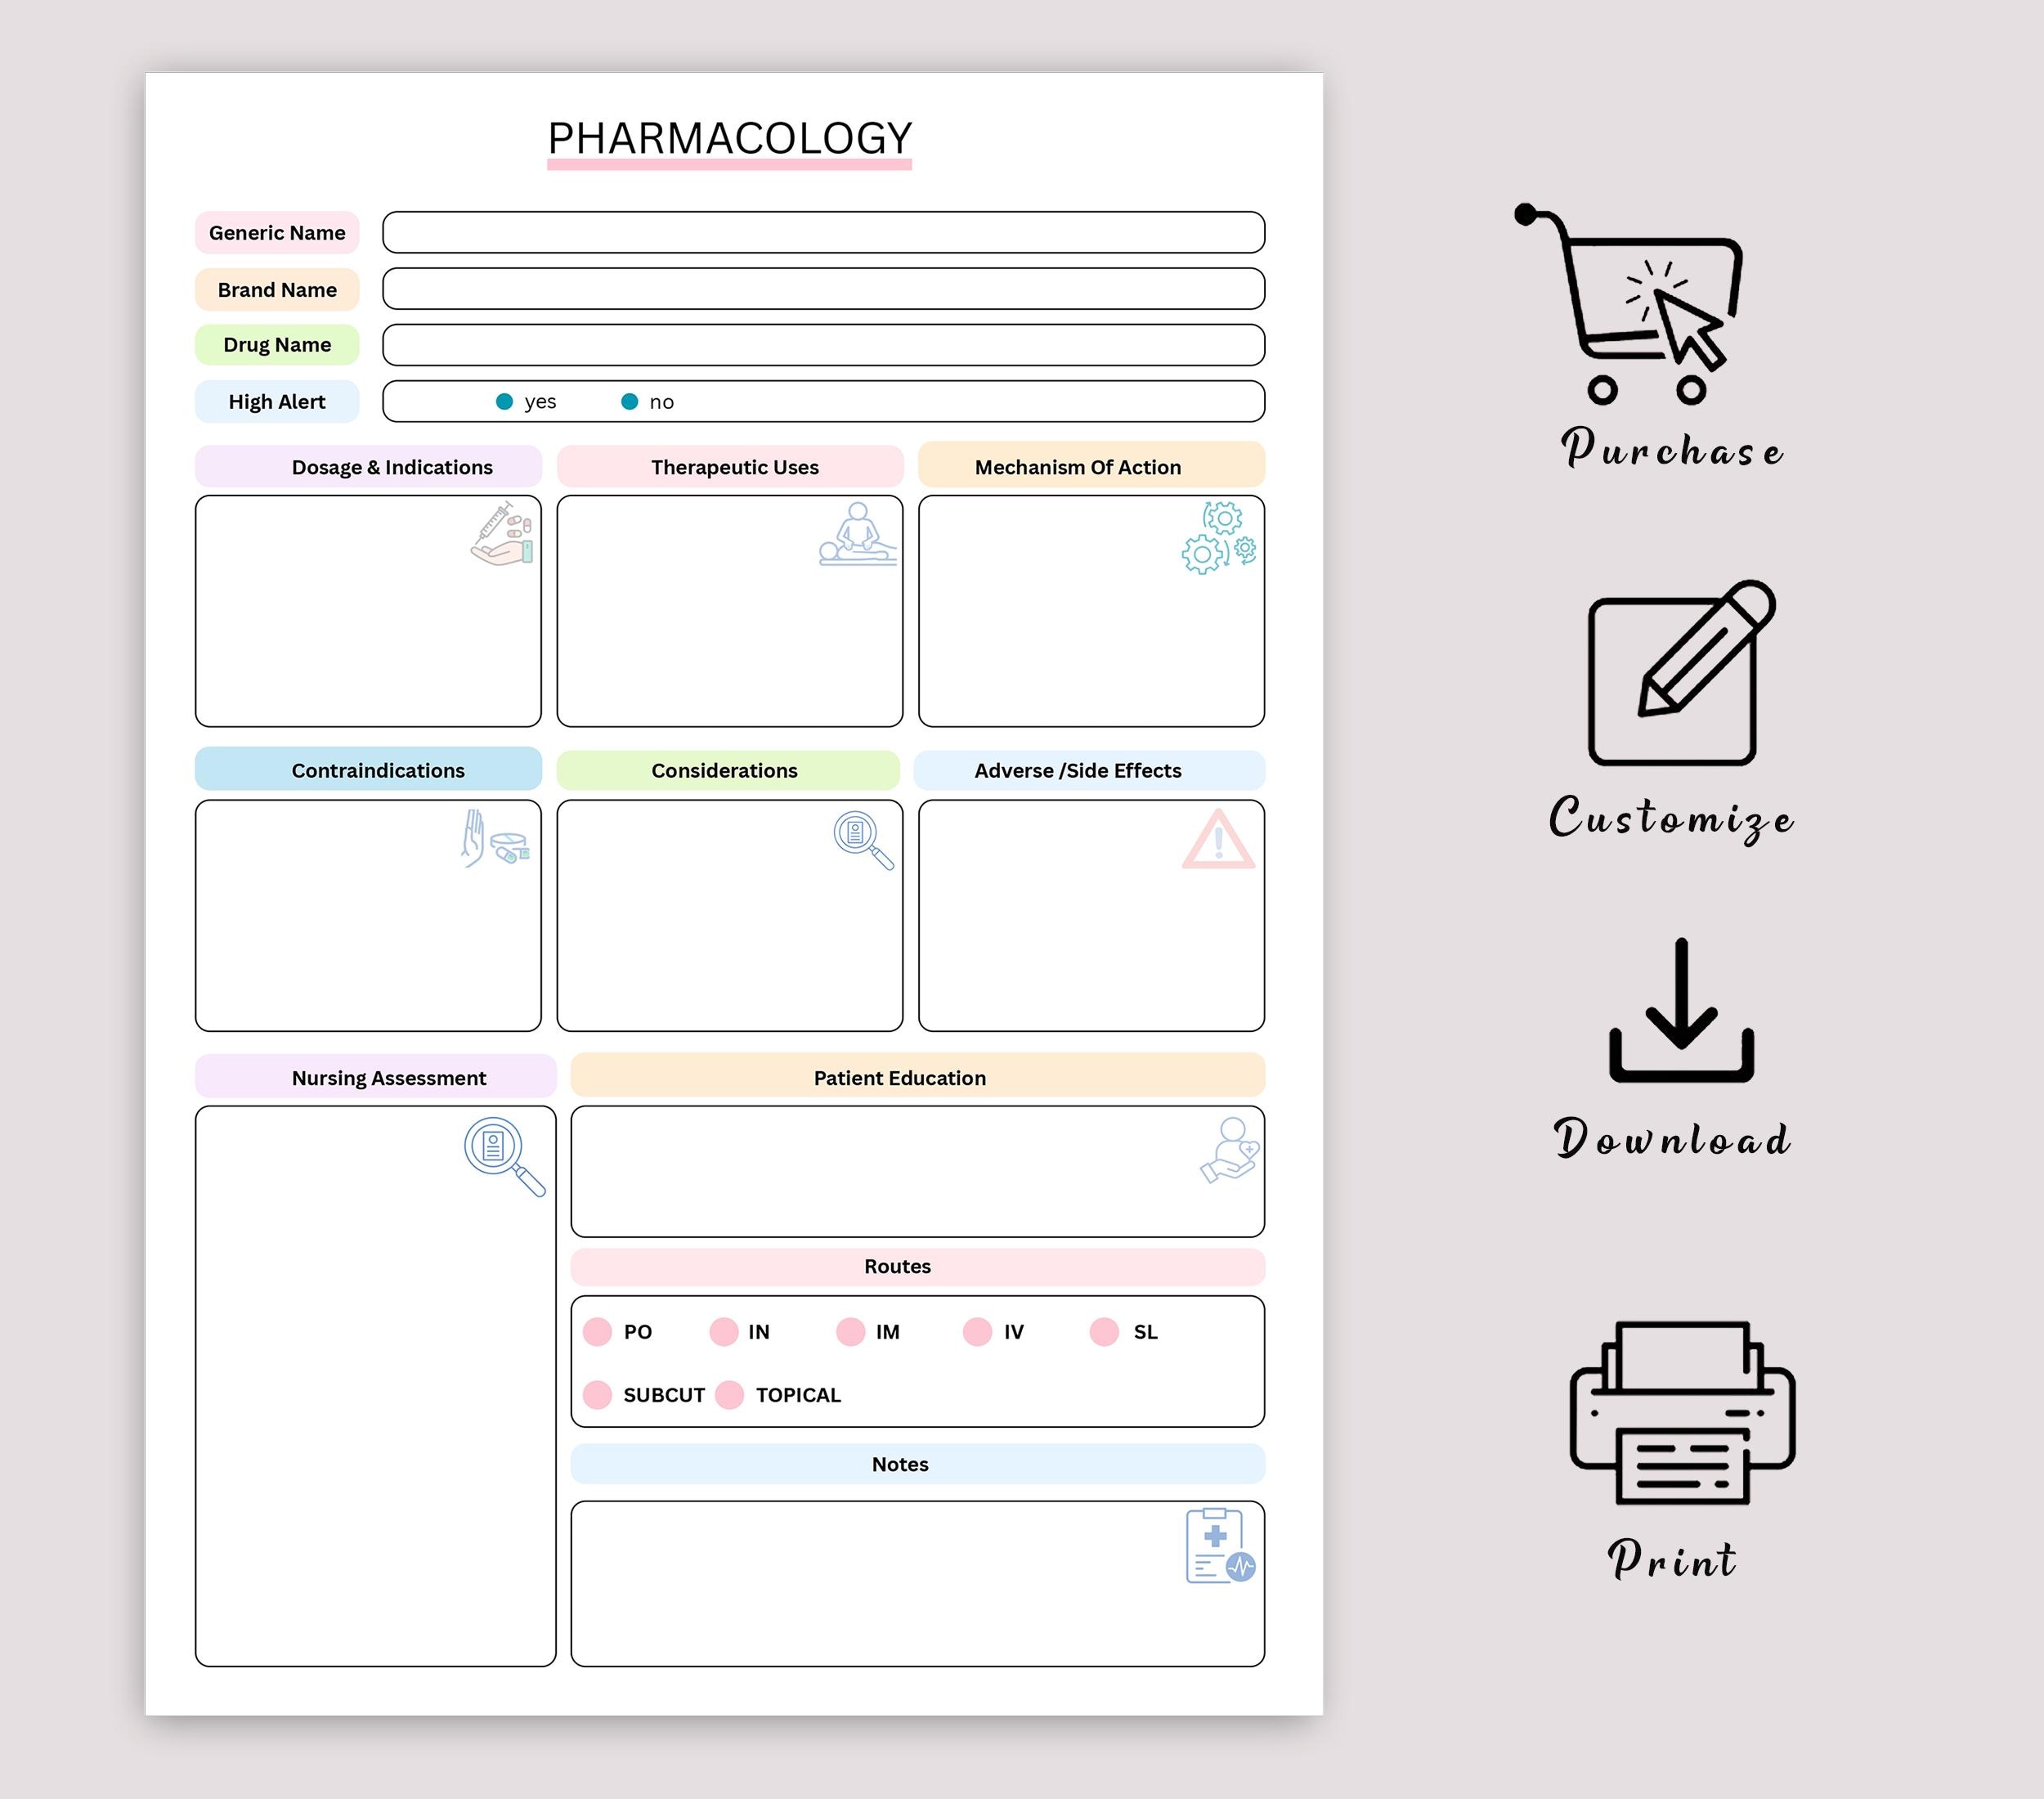
A lot of people treat pharmacology like it's memorization, but it really isn't. If you're just trying to flash-card your way through drug names and mechanisms, you'll be stuck every month looking at a wall of white letters and wondering why they don't stick. The worksheet approach works because it forces you to engage with the material in a way that mirrors how you'll actually use it on the job or in clinical settings. It's a structured tracking document you complete once a month, covering a specific drug class or group of related medications. Instead of cramming random facts, you organize information systematically and build a reference that compounds over time. I've seen students who committed to this for six months end up with a personalized pharmacology handbook they can flip through in under five minutes when they need a quick refresher. The standard template covers mechanism of action, receptor targets, pharmacokinetics, indications, dosing ranges, adverse effects, contraindications, and drug interactions. Some versions also include a column for mnemonic devices or clinical pearls you pick up along the way. The key is consistency, not perfection. Ten minutes a day beats five hours once a month.
Setting Up Your System
Start simple. A spreadsheet with the columns I listed above gets the job done fine. Paper works too if that's what you're comfortable with, though spreadsheets are easier to update and search later. I prefer columns grouped into three sections: Core Profile (mechanism, indications, dosing), Risk Profile (side effects, interactions, contraindications), and Clinical Context (pearls, mnemonics, case examples). This mirrors how I think about drugs in practice. Here's something most beginner worksheets don't mention. Pick your drug classes by clinical relevance, not by whatever chapter your textbook assigns next. Anti-hypertensives in January, anti-diabetics in February, inhaled therapeutics in March. You'll retain more because you're studying systems you'll encounter repeatedly, not isolated facts from a random chapter order. This also means by the time you hit the nervous system drugs later in the year, you already have a foundation of metabolic and cardiovascular pharmacology to anchor against.
The Actual Process
Don't start from scratch every month. Open your previous month's sheet and use it as a scaffold. When you tackle ACE inhibitors after finishing ARBs, immediately compare them side by side on the worksheet. Note where they overlap and where they diverge. This comparison technique alone will cut your memorization time in half because you're building on existing neural pathways instead of creating new ones from nothing. I used to fill out these worksheets passively, copying from textbooks. That stopped working for me around my third month. I was spending an hour per drug and remembering almost nothing. What changed was making myself answer the questions before looking at my sources. Write down what you think the mechanism is first. Get it wrong. Then check. The act of retrieving information and correcting yourself creates a much stronger memory trace than passive reading ever will. It's slightly more painful in the moment, which is probably why most people skip it. Here's an edge case I ran into that tripped me up for weeks. When I covered anticoagulants, the warfarin section kept conflicting with everything else on the page. I had it listed as a vitamin K antagonist, then in the interactions column I noted its narrow therapeutic index and extensive CYP interactions, and somewhere in the dosing section I'd written loading dose protocols. Three completely different cognitive frames for the same drug. My brain couldn't reconcile them.
Get the Full Details

The workaround was adding a dedicated sub-section within each drug entry called "Clinical Decision Points." For warfarin, I wrote a short paragraph covering the specific scenarios where dosing decisions become tricky: when to bridge with heparin, how to handle procedure-related interruptions, and how to read INR trends rather than single values. Once I separated the general pharmacology from the clinical application, everything clicked. That sub-section has been in every worksheet I've built since.
Common Mistakes That Waste Time
The biggest waste I see is treating the worksheet like a research project. You don't need every drug's half-life memorized to four decimal places. You need the clinically relevant numbers. Warfarin's half-life is 36 to 42 hours. For your worksheet, write 36 hours and move on. You'll never recall the exact range under pressure, and you'll never need to. The number that matters clinically is that it takes roughly five days to reach steady state, which is why we load with heparin or enoxaparin when starting warfarin therapy. Another mistake is copying mnemonics without understanding the drugs behind them. "Loose Erythrocytes Make Patients Very Anemic" is cute for lithium side effects, but if you don't actually know what nephrogenic diabetes insipidus looks like in practice, that mnemonic is useless decoration. I learned this the hard way when a preceptor asked me about managing a patient on lithium who presented with tremor and polyuria, and I couldn't connect the dots fast enough. A third pitfall is covering too many drugs per month. I used to do three drugs a month religiously. Two is the right number. One complex class like beta-blockers covers ten drugs anyway. Spread the detail across comparison rows rather than trying to memorize each one individually. This is especially important for drugs that share mechanisms, where the differences between individual agents are often clinically negligible.
Advanced Usage: Making the Worksheet Do More Work for You
After three or four months, you can start cross-referencing between sheets. When studying statins, look back at your anti-hypertensives and note that some blood pressure medications interact with certain statins through CYP3A4. This is where the Monthly Pharmacology Worksheet stops being a study tool and becomes a clinical reference. The connections you make between months are the same connections you'll need during rotations or board exams. You can also use your completed worksheets for self-testing. Cover the right half of your columns and try to fill them in from memory. Then check. This is faster than any third-party flashcard deck because the worksheet is already organized in the structure your brain will use on exam day. I timed this against UWorld questions once. For pharmacology-heavy blocks, reviewing my own worksheets first reduced my question completion time by about forty percent because I already had the information structured the way the questions expected it. There's also a technique I picked up from a clinical pharmacy resident. After finishing a drug entry, write one sentence about the most common wrong answer you've seen for that drug on exams or in practice. For example, with digoxin, the common error is attributing all visual disturbances to dose toxicity when they can also occur at therapeutic levels. Writing that note on your worksheet trains you to recognize the trap before you fall into it.
What This Approach Doesn't Do
Let me be clear about the limitations. A Monthly Pharmacology Worksheet is not a substitute for active clinical exposure. You can build the most thorough worksheet in the world and still freeze when a real patient asks a question you've never encountered. The worksheet builds knowledge, not clinical judgment. Those are different skills. It also doesn't scale well beyond about eighteen to twenty-four months of consistent use. After that point, you're mostly reviewing what you already know, and the incremental value drops significantly. At that stage, question banks and clinical case reviews become more efficient. The worksheet is strongest in the first year when you're building the foundational framework. There's also a scheduling problem. If you fall behind for even two months, catching up requires doubling your weekly investment, which usually leads to burnout and abandoning the system entirely. I've watched several students do this. The compromise is to accept that some months will get less attention and not try to recover perfect coverage. A half-complete set of worksheets is better than zero worksheets because you've maintained the habit.
If the spreadsheet format doesn't work for you, consider switching to Anki or a similar spaced repetition system after the first four months. The worksheet builds the initial structure. Spaced repetition maintains it. Using both together is more effective than relying on either one exclusively.
Downloading a Monthly Pharmacology Worksheet Template
Several pharmacy education websites offer free downloadable templates. The American Society of Health-System Pharmacists maintains a student resources section with worksheet formats, and most pharmacy school study groups share their own versions on student forums. The specific template doesn't matter nearly as much as the discipline of using it consistently. I've seen people succeed with hand-drawn sheets on notebook paper and people fail with beautifully formatted digital templates they never opened after week one. What matters is picking a format you can sustain and starting this month, not next semester. Pick two drug classes. Build the first entries. Compare them when you get to the second month. Add clinical decision points for the drugs that frustrate you. That's the entire method, stripped down to what actually works.