So you're trying to figure out how ethics actually works in clinical nursing
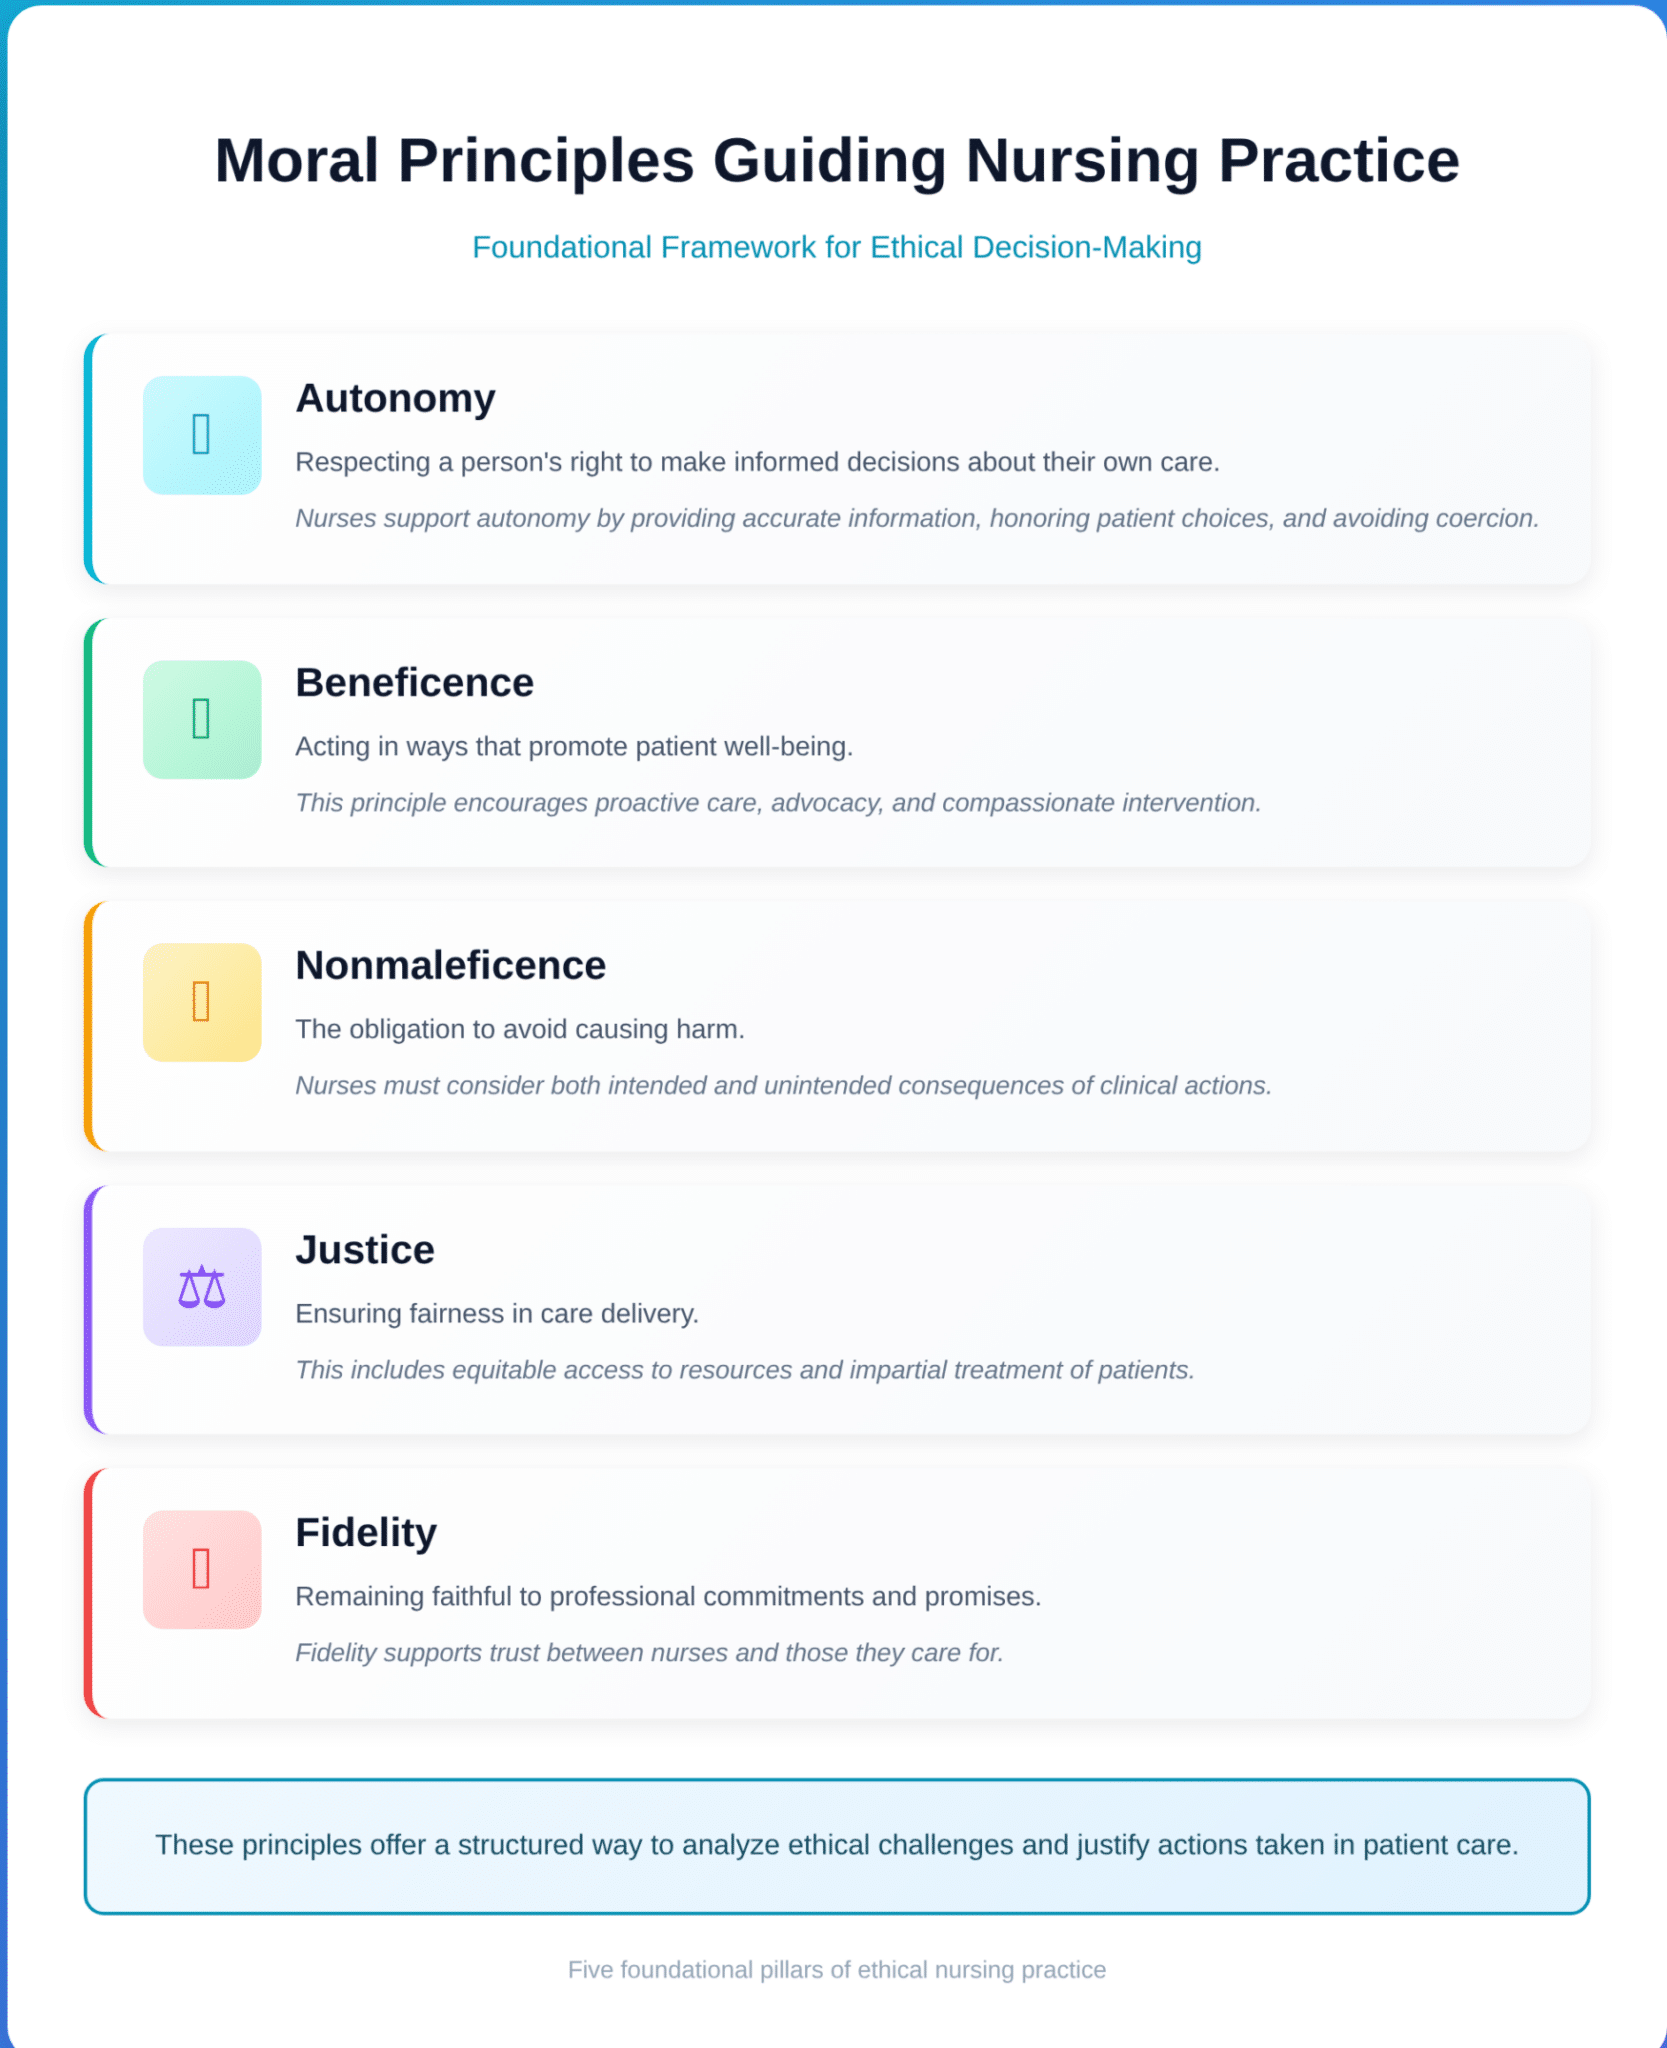
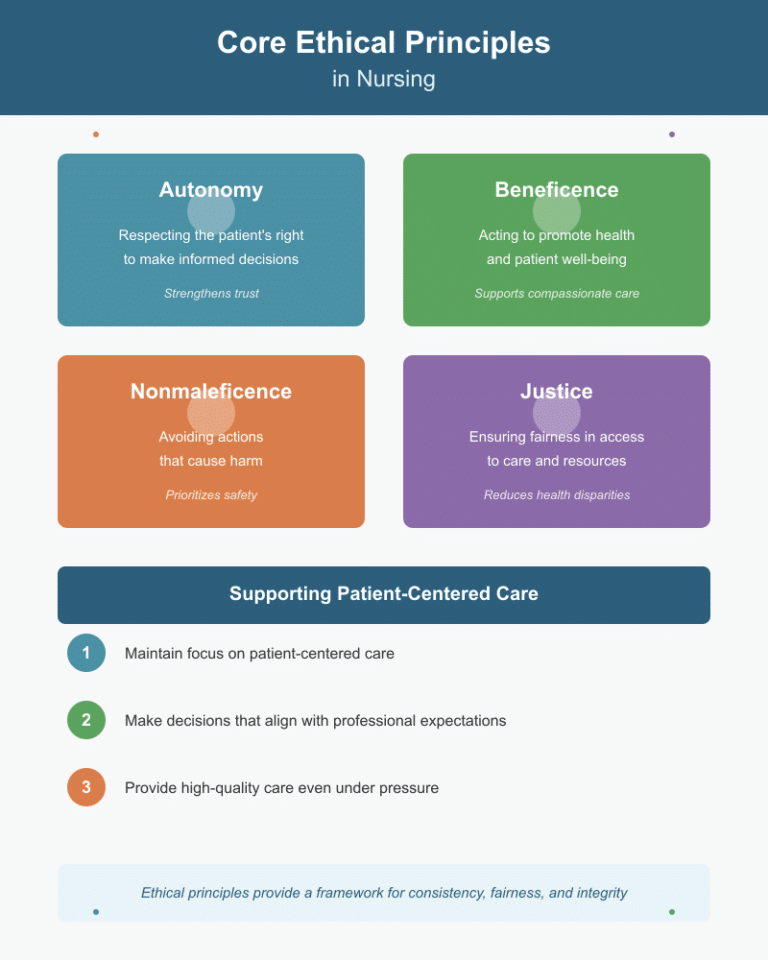
Most nursing programs hand you a flowchart and tell you to memorize four principles. Autonomy, beneficence, non-maleficence, justice. You pass the exam. Then you get assigned to a med-surg floor and watch everything fall apart within a week. That's because the textbook versions of these models don't account for the fact that patients lie, families show up uninvited, and your charge nurse just told you to "handle it yourself" because staffing is at two to a room. The moral model in nursing isn't a single thing. It's a collection of frameworks nurses use to make decisions when there's no clear right answer. The most commonly taught one is Beauchamp and Childress's four-principle approach, but in practice, most experienced nurses are operating more from an ethics of care model without ever having taken a class on it. They prioritize relationship, context, and the specific person in front of them over abstract principles. This matters because the four-principle model breaks down the moment two principles directly contradict each other, which is basically every shift.
Implementing a Moral Model In Nursing on the Floor
Here's how it actually looks. You're working a patient with end-stage COPD who keeps pulling off their O2 cannula because they're restless. The family wants everything done. The patient said three days ago they didn't want intubation. The protocol says maintain oxygen saturation above 90%. The moral model kicks in when you have to decide whether to restrain, sedate, or accept the risk of desaturation. You're not applying a formula. You're weighing the principle of autonomy against non-maleficence and asking which one carries more weight in this specific situation. The practical method most nurses develop involves a quick internal checklist: what did the patient say when they were clear-headed? Who is the legitimate decision-maker if the patient can't speak? What does the evidence say about outcomes? What would happen if every nurse on this unit made the same choice? And finally, can I live with this decision at 3 AM when something goes wrong? I dealt with a case last year where a dementia patient with no advance directive was facing a surgical intervention. The daughter who showed up had been estranged for eight years and demanded full code. The son who visited daily and managed his medications wanted comfort care only. The hospital's ethics committee took four days to convene. Four days. The patient was deteriorating. What I ended up doing was sitting with both siblings together, laying out exactly what full code meant in this specific clinical context with his comorbidities, and having them hear it from each other rather than from me. The daughter agreed to step back after realizing her position wasn't based on what her father would have wanted but on her own guilt. That's the part they don't teach you in ethics classes.
Counter-intuitively, the more experienced nurses I've worked with tend to rely less on formal models and more on what I'd call pattern recognition. They've seen enough morally ambiguous situations to recognize the shape of the problem before they can articulate which framework applies. This is useful until you encounter a situation that doesn't match any pattern you've seen before. That's when you go back to the formal models because your intuition is just your unconscious bias wearing a lab coat. One major pitfall is what I call ethics myopia. You focus so hard on the immediate moral question in front of you that you miss the structural issues creating the problem. A nurse debating whether to report a colleague for a medication error might spend hours on the moral dimensions of honesty versus loyalty while completely missing the fact that the real issue is a staffing ratio that made the error likely regardless of who was working. The moral model gives you tools to analyze the decision, not to fix the system. Another nuance beginners miss is that moral models are descriptive, not prescriptive. They explain how people actually make ethical decisions; they don't reliably predict what you should do. When you read the literature on nursing ethics, you'll find that the same model can produce opposite conclusions in different hands. Two nurses can apply the same four-principle framework to an end-of-life case and reach completely different conclusions while both being logically consistent. That's not a bug in the model. That's the point. Ethics is about reasoning, not arriving at the right answer.
Get the Full Details

The biggest limitation of any moral model in nursing is that it assumes you have time to deliberate. Real clinical ethics rarely works that way. Most moral decisions in nursing happen in under thirty seconds while you're hanging a bag of vancomycin and a patient is asking you a question about their prognosis. The models are built for case conferences, not for shift work. When you do have time, which is usually after the fact during incident reviews, the models become valuable for justifying decisions that were already made intuitively. If you want something more structured than your own pattern recognition, the NANDA-approved ethical decision-making model is worth looking into. It walks through identifying the problem, gathering relevant facts, identifying stakeholders, generating options, evaluating those options against ethical principles, making a decision, and documenting the rationale. The documentation piece is the most important part because when things go wrong, your notes are the only evidence that you thought through the decision rather than just reacting. A well-documented ethical rationale can protect you professionally in ways that being right cannot. There's also the Potter Perry model, which combines nursing values, ethical principles, and critical thinking into a single framework. It's used more in Australian and New Zealand nursing education but has gained traction in the US. The advantage is that it explicitly includes power dynamics and cultural context, which the four-principle model treats as background noise rather than central factors.
What I recommend practically is learning at least two frameworks cold and keeping a third as a fallback. Start with the four-principle model because that's what every ethics committee in the country uses. Learn the ethics of care model because that's how you actually think on the floor. And familiarize yourself with virtue ethics because it's what you fall back on when the other two give you nothing but headache. Virtue ethics basically asks not "what should I do" but "what kind of nurse would I become if I did this." It sounds fluffy until you're the one who has to look at yourself in the mirror after a tough call. The uncomfortable truth is that no model eliminates moral distress. Moral distress happens when you know the right thing to do but can't do it because of institutional constraints, and no ethical framework changes the fact that your hospital might prioritize throughput over patient welfare. Models help you articulate the conflict and make defensible decisions within the constraints you have. They don't remove the constraints. If you're looking for a framework that guarantees the morally correct outcome, you won't find one. The closest thing is good judgment, which comes from doing this work repeatedly over many years and paying attention to what actually happens rather than what the textbook says should happen.