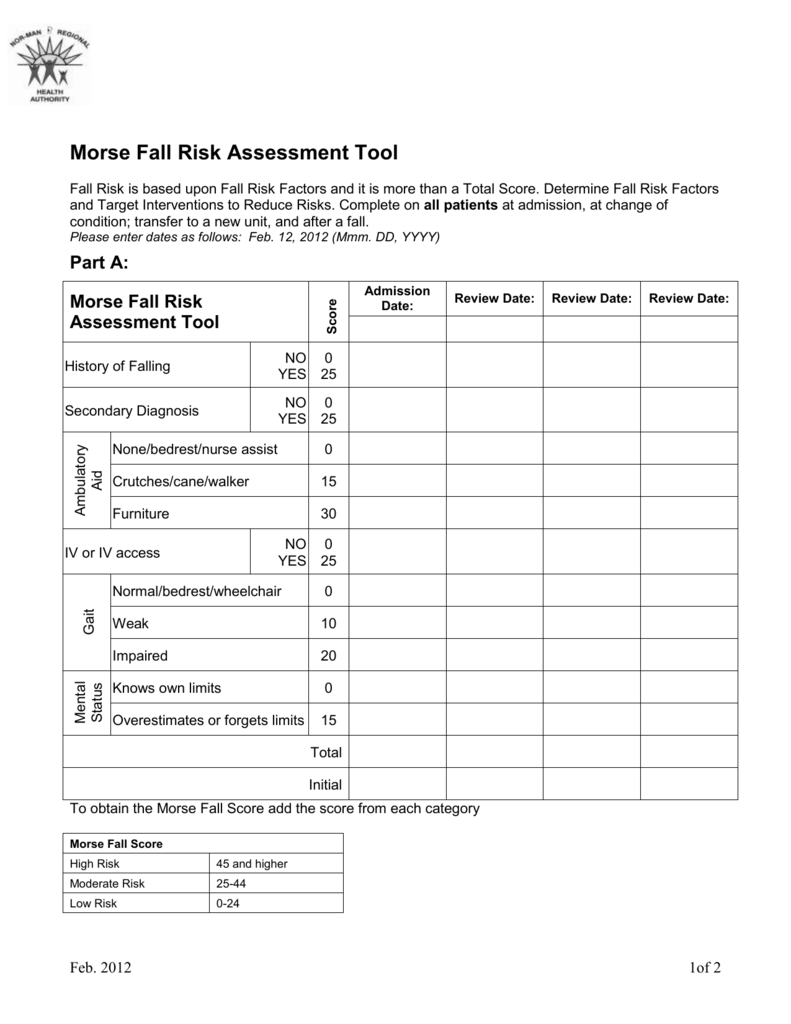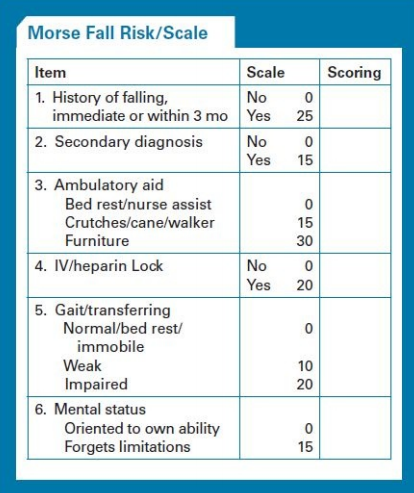
The Morse Fall Risk Scale is a paper tool you fill out in about two minutes per patient.
It gives you a number, and that number tells you whether someone is low risk, medium risk, or high risk for falling in the hospital. That's basically it. The version most people use was published by G.H. Morse in 1989, and it has five items. Each item gets a point value, you add them up, and you get a score between 0 and 125. Here's how the scoring actually works in practice. History of falling gets you 25 points if the patient has fallen within the last three months. Secondary diagnosis is worth 15 points — that means any diagnosis beyond their main admitting reason. Ambulation is where people mess up the most. Normal equals zero points, weakened gets 15, and bedbound or chairbound gets 25. Mental status matters too. Oriented to events gets zero, and forgetful or confused gets 15. IV or heparin lock is just 0 or 5 depending on whether they have one. Gait — normal is zero, weak is 10, impaired is 20. So the math works like this: a patient with no fall history, clear head, normal gait, walking on their own, no IV, and a single primary diagnosis scores a 0. That's the best possible outcome on this tool. A patient who fell recently, is confused, has an impaired gait, uses a wheelchair, and has an IV gets you into the high-risk zone at 100 or above. Risk categories are straightforward: 0 to 24 is low risk, 25 to 50 is medium risk, and 51 and above is high risk.
The thing about the Morse scale that nobody talks about enough is how much the history of falling weighs everything else. If a patient has fallen before, they just rack up 25 points instantly — that's nearly half the medium-risk threshold on its own. I've seen nurses skip the rest of the assessment after scoring a history of falling because the implication felt obvious. That's a mistake. The remaining four items still matter because they tell you what kind of fall prevention to put in place, not just whether to put something in place. I had a patient last year who scored a 13 on the Morse scale. Low risk by the numbers. She was oriented, walked fine, no IV, no extra diagnoses, no fall history. And she still fell. Out of bed, at 3 AM, while her daughter was sitting right there. What the Morse missed entirely was that she had severe orthostatic hypotension from her blood pressure meds, and her gait looked normal when she was standing still in a bright room but her balance collapsed the moment she tried to pivot or navigate around furniture. The scale doesn't account for medication effects or environmental hazards or the fact that hospital beds are basically platforms people slide off of when they're disoriented in the dark. That's the honest limitation of the Morse Fall Risk Scale. It's a snapshot tool, not a prediction engine. It tells you something about baseline risk at one moment in time. It does not measure what happens at 2 AM when the lights are off and the patient decides to get up to use the bathroom without calling for help. It does not capture the compounding effect of delirium, sedation, urinary urgency, and unsecured beds. I've worked in units where we added a second assessment at shift change and again during the night hours because the admission score proved unreliable for patients whose condition changed. That added maybe four minutes per patient per shift but caught things the initial Morse score completely missed.
Another nuance that trips people up is the ambulation and gait items. They sound similar but they're scored separately. Ambulation refers to how the patient moves around the unit — can they walk to the bathroom alone, do they need assistance, are they non-weight-bearing? Gait refers to the quality of their walking pattern when you're observing it right now. A patient can ambulate independently (zero points) but have an impaired gait due to neuropathy or Parkinson's (20 points). I see a lot of documentation where staff write "ambulates independently" and then leave gait blank or mark it as normal because they didn't actually observe the patient walking. That's a documentation gap, not a clinical judgment call. There's also a version called the Morse Fall Scale with a sixth item added in some adaptations — the use of assistive devices. That's not part of the original 1989 instrument, so if your hospital says they use the Morse Scale, they almost certainly mean the five-item version. Don't add points from a sixth item that isn't validated unless your protocol explicitly allows it. If you need the actual printable form, most health systems produce their own branded versions. The original Morse & Galvin instrument from 1992 is in the book "Nursing Research: Developing, Evaluating and Utilizing Evidence for Nursing Practice," and you can find it referenced in the Journal of Nursing Measurement. Some hospital supply companies sell pre-printed forms. The raw scoring sheet itself isn't copyrighted in a way that prevents you from printing it from clinical resources online, but check your facility's policy — some require using their specific electronic version for documentation compliance.
Get the Full Details
The scale takes a real toll when you're dealing with patients who have dementia or aphasia. You can't reliably ask a confused patient if they've fallen in the last three months, and you can't trust their self-report. I've resorted to pulling nursing notes from the previous shift and reviewing incident reports to verify the history item. Sometimes you just have to mark it as unknown and document why rather than guessing, because a wrong score is worse than a missing one. For patients with acute neurological conditions — stroke, TBI, anything affecting cognition or motor control — I find the Morse Scale underestimates risk. It was normed on a general medical-surgical population, not on neurology patients. We switched to the Hendrich Fall Risk Model for our neuro unit because it factors in medications like benzodiazepines and diuretics, which the Morse doesn't address at all. That model takes longer to score — maybe six to eight minutes instead of two — but the trade-off was worth it given how often our Morse scores came back as low risk for patients who then fell within 48 hours. Bottom line: the Morse Fall Risk Scale is fast, easy to learn, and better than nothing. It's not a substitute for clinical judgment, it's not predictive in changing conditions, and it absolutely will miss falls in patients whose risk comes from things the five items don't measure. Use it as one data point in a broader assessment, reassess when the patient's condition changes, and don't let a low score make you complacent about basic fall precautions like bed alarms, non-slip socks, and keeping the call button within reach.