The Reality of the Most Abundant Blood Group
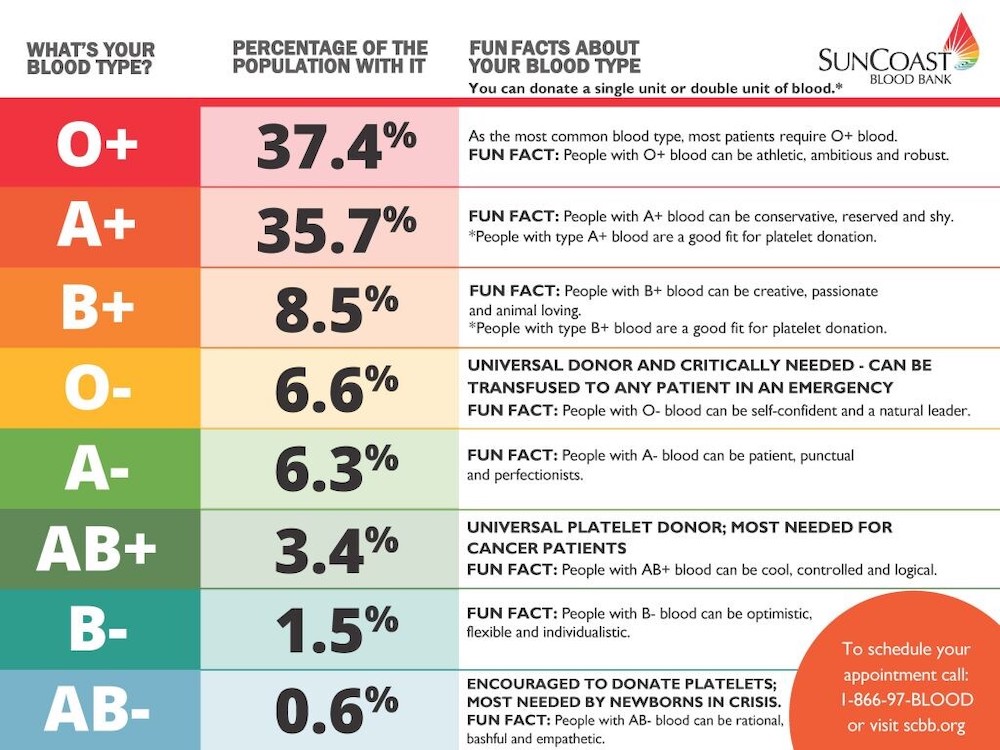
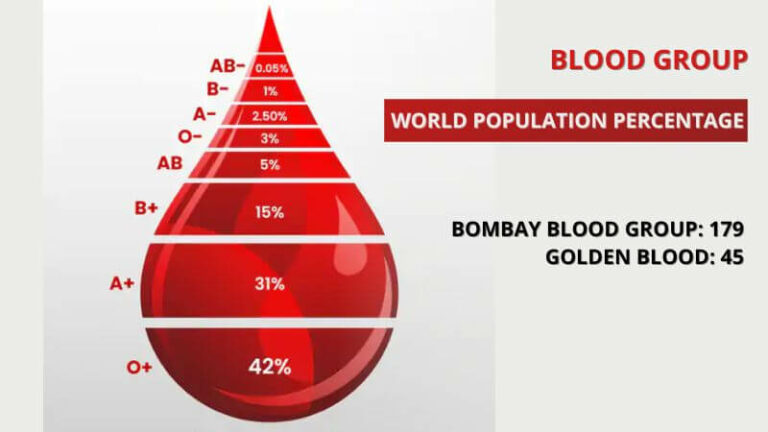
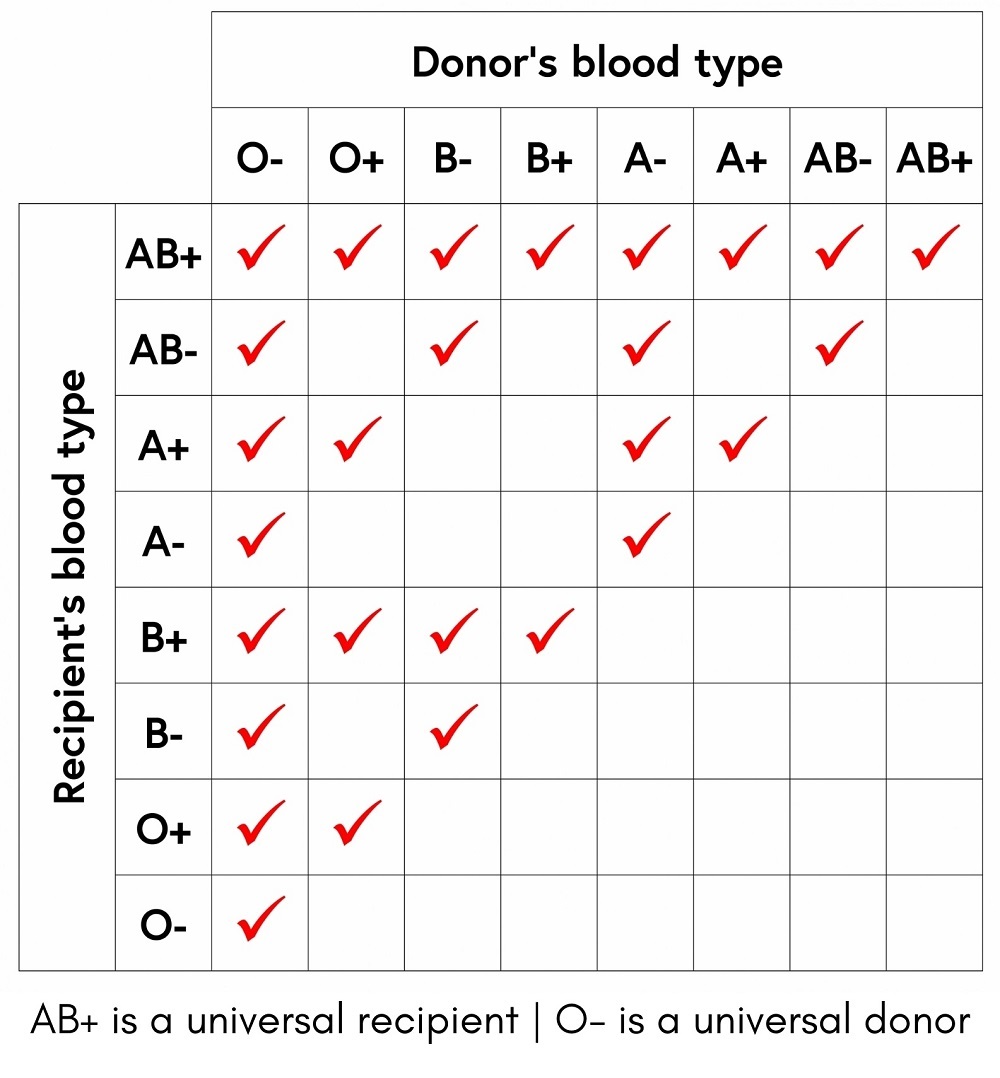
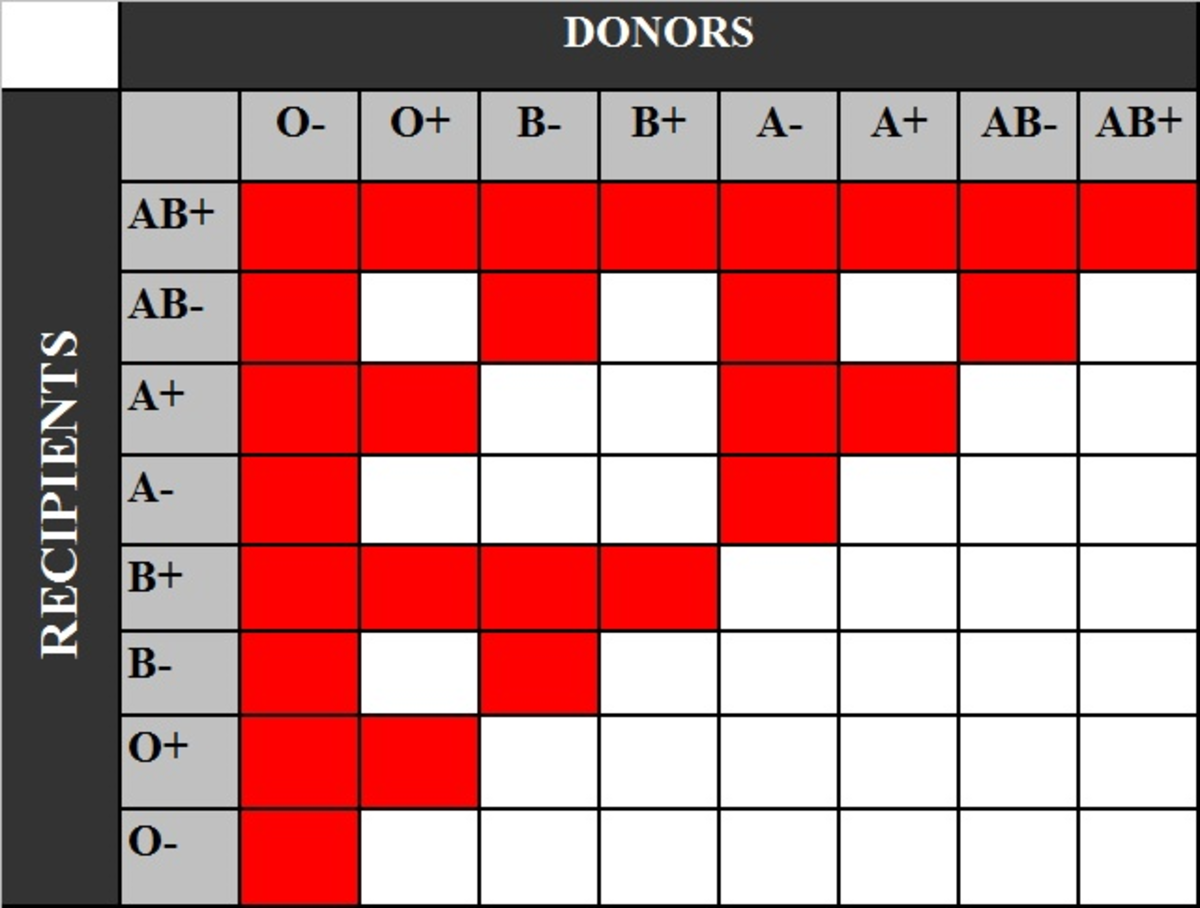
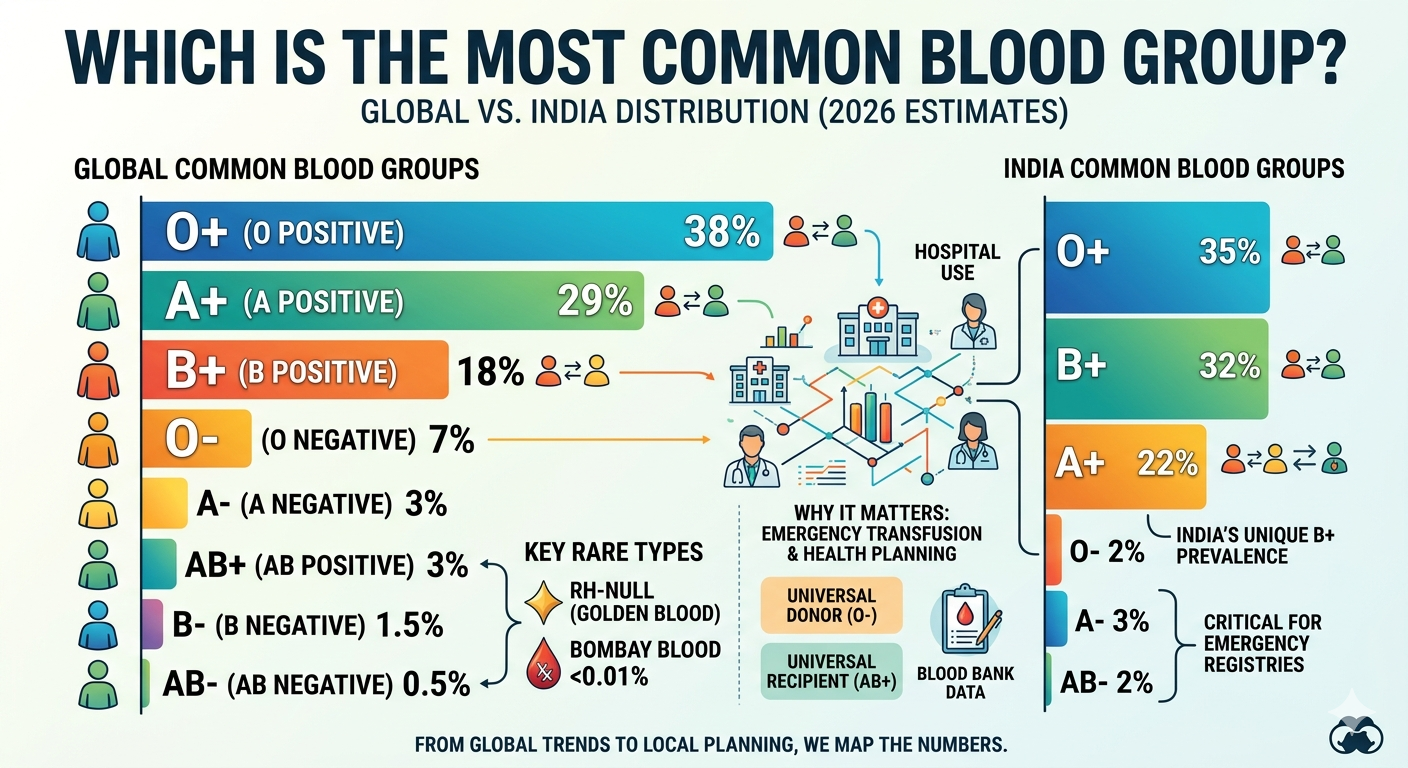
O positive blood is the most common type in the general population, showing up in roughly 37 to 39 percent of people depending on the demographic you look at. This isn't especially surprising when you think about it from a genetics standpoint. The O allele is dominant across most populations, and the Rh-positive factor is itself the more prevalent variant. The combination just compounds that likelihood. I spent years working in transfusion medicine, and the most common blood group being O positive created a specific kind of pressure that nobody warns you about. Blood banks constantly run thin on O positive units because they're in such high demand. Every trauma bay, every surgery, every routine procedure has some chance of needing those bags. When I was covering the evening shift at a community hospital, we once burned through six units in a single night during a mass casualty drill. The supply chain couldn't keep up for about 48 hours. You learn quickly how fragile the system is. The other practical thing nobody emphasizes is that O positive red cells are the universal donor for Rh-positive recipients, which means about 85 percent of the population can receive them without any ABO or Rh mismatch concerns. That makes O positive both the most common and the most versatile unit in the inventory. Hospitals carry less buffer stock on it than they should, assuming demand will always be predictable. It isn't.
The Genetics Behind the Numbers
A quick breakdown of how this works. The ABO system is controlled by three main alleles: A, B, and O. The O allele produces no functional glycosyltransferase enzyme, which means red blood cells end up with just the base H antigen and nothing added on top. That's why type O blood doesn't trigger an immune response from anti-A or anti-B antibodies in the recipient's plasma—there are no A or B antigens present to attack. The Rh system is separate. The D antigen determines whether you're positive or negative. About 85 percent of people of European descent are Rh-positive, though this varies significantly across populations. Sub-Saharan African groups tend to have slightly lower Rh-negative rates, while certain isolated communities actually have higher frequencies of Rh negativity. The most abundant blood group sits at the intersection of the most common ABO type and the most common Rh factor.
Common Misunderstandings and What Beginners Miss
One thing people routinely get wrong is assuming the most common blood type is automatically the easiest to maintain a steady supply of. That's backwards thinking. The very popularity of O positive means it gets consumed faster than any other type. Blood banks actually have more trouble managing O positive inventory than rare types because the turnover rate creates constant restocking pressure. Rare blood types sit on shelves longer and don't generate the same logistical headaches. Another overlooked point is that O positive plasma works differently than O positive red cells. Plasma from O positive donors still contains both anti-A and anti-B antibodies, so it's not universal for plasma transfusions. That distinction matters more than most people realize when you're dealing with massive transfusion protocols. I encountered a specific problem a few years back involving a pregnant patient who was O positive but had developed antibodies against a minor red cell antigen outside the ABO and Rh systems. Standard typing showed her as O positive, which normally simplifies everything. Her antibody profile, however, meant that even O positive blood wasn't straightforward to crossmatch. We had to pull records going back several years of her transfusion history and ultimately used phenotyped matched units from a rare donor registry. It added roughly three days to her treatment timeline. The takeaway is that blood group is just the first layer. Once you start dealing with clinically significant antibodies, the commonality of the blood type becomes almost irrelevant.
Get the Full Details
Supply Chain Realities
Blood donation centers routinely advertise desperate needs for O positive donors, and they mean it. The waste rate on O positive blood is lower than on some rarer types because demand matches supply more closely, but the matching is so tight that any disruption—a bad weather event, a flu outbreak reducing donor turnout, a local emergency—creates immediate shortages. I've seen hospitals implement transfusion protocols that prioritize O positive red cells for Rh-positive patients specifically to conserve O negative units for true emergencies where ABO compatibility is uncertain. The shelf life is another factor. Red blood cells last about 42 days depending on the anticoagulant solution used. Plasma can be frozen for a year. Platelets only last five days with agitation. The most abundant blood group being red cells rather than plasma or platelets means the daily logistics revolve around fresh red cell availability, which is inherently more volatile than frozen products.
Downsides and Where the System Falls Short
The biggest bottleneck with the most abundant blood group is exactly what makes it useful. Because O positive is compatible with the largest number of recipients, there's no strategic reason to reserve it for specific cases, which means it gets used liberally even when alternative types would work equally well. This accelerates depletion without adding clinical value. Some health systems have started implementing type-specific transfusion policies to slow this down, but compliance is inconsistent and the culture in emergency medicine still heavily favors O positive as the default. There's also the demographic blind spot. Global blood type distributions vary enough that "most abundant" is a relative term. In parts of Asia, for example, type B shows higher frequency relative to Western populations. A one-size-fits-all approach to blood banking assumes a demographic distribution that simply doesn't hold everywhere. If you're managing inventory in a diverse urban hospital, you need data on your actual patient population, not national averages. If you're looking to donate, the most practical path is to schedule appointments at centers that serve hospital networks with high surgical volume. O positive units from those donations end up where they're needed fastest. Finding a local center usually takes a quick search for your area, and most organizations let you book specific time slots online now, which cuts down on wait times considerably compared to walk-in donations a decade ago.