Gas Exchange Doesn't Work The Way Most People Think
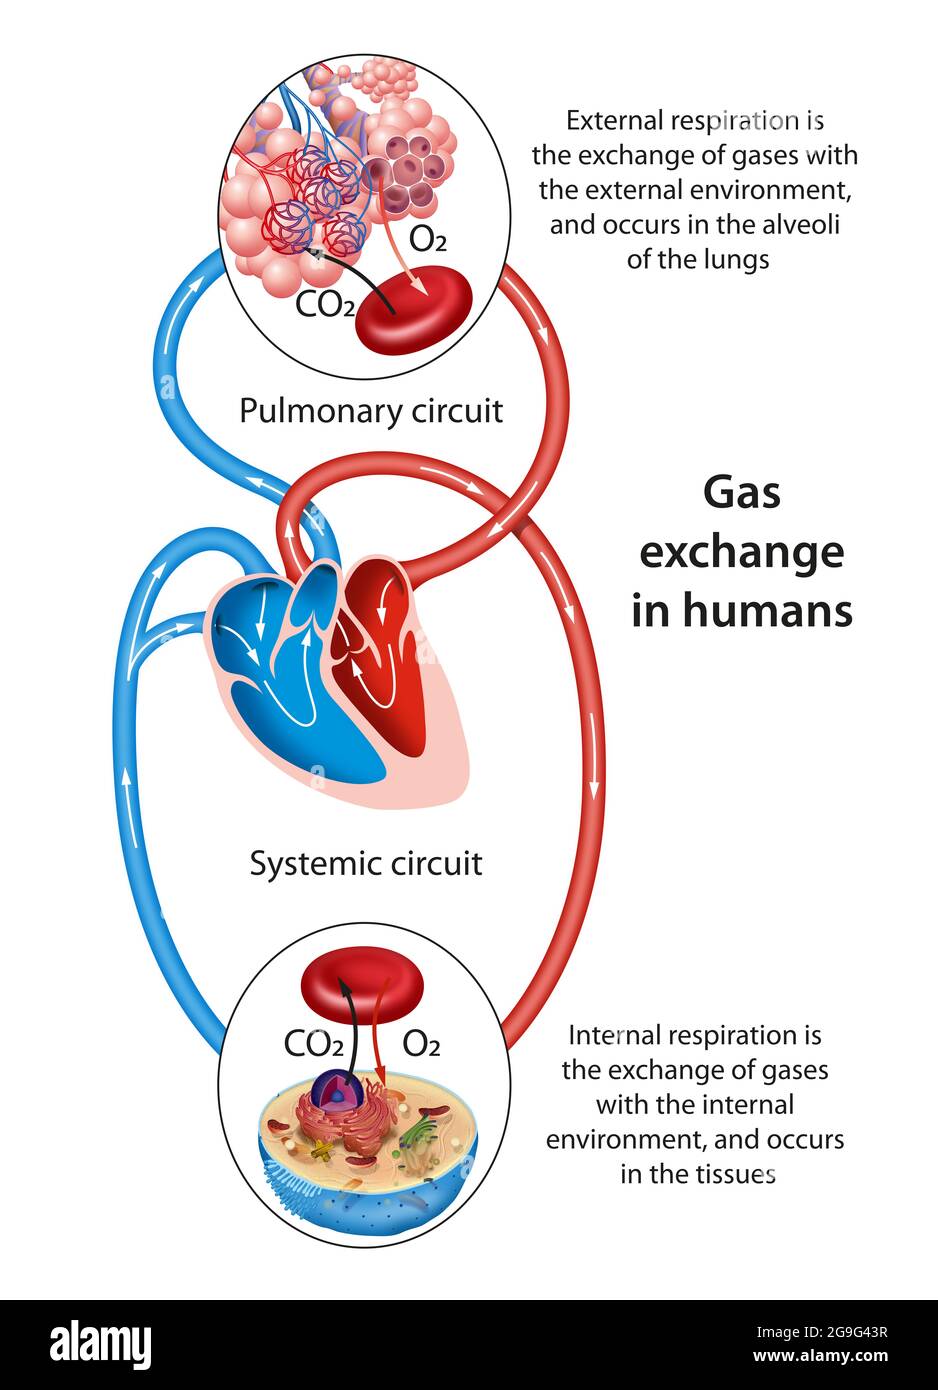
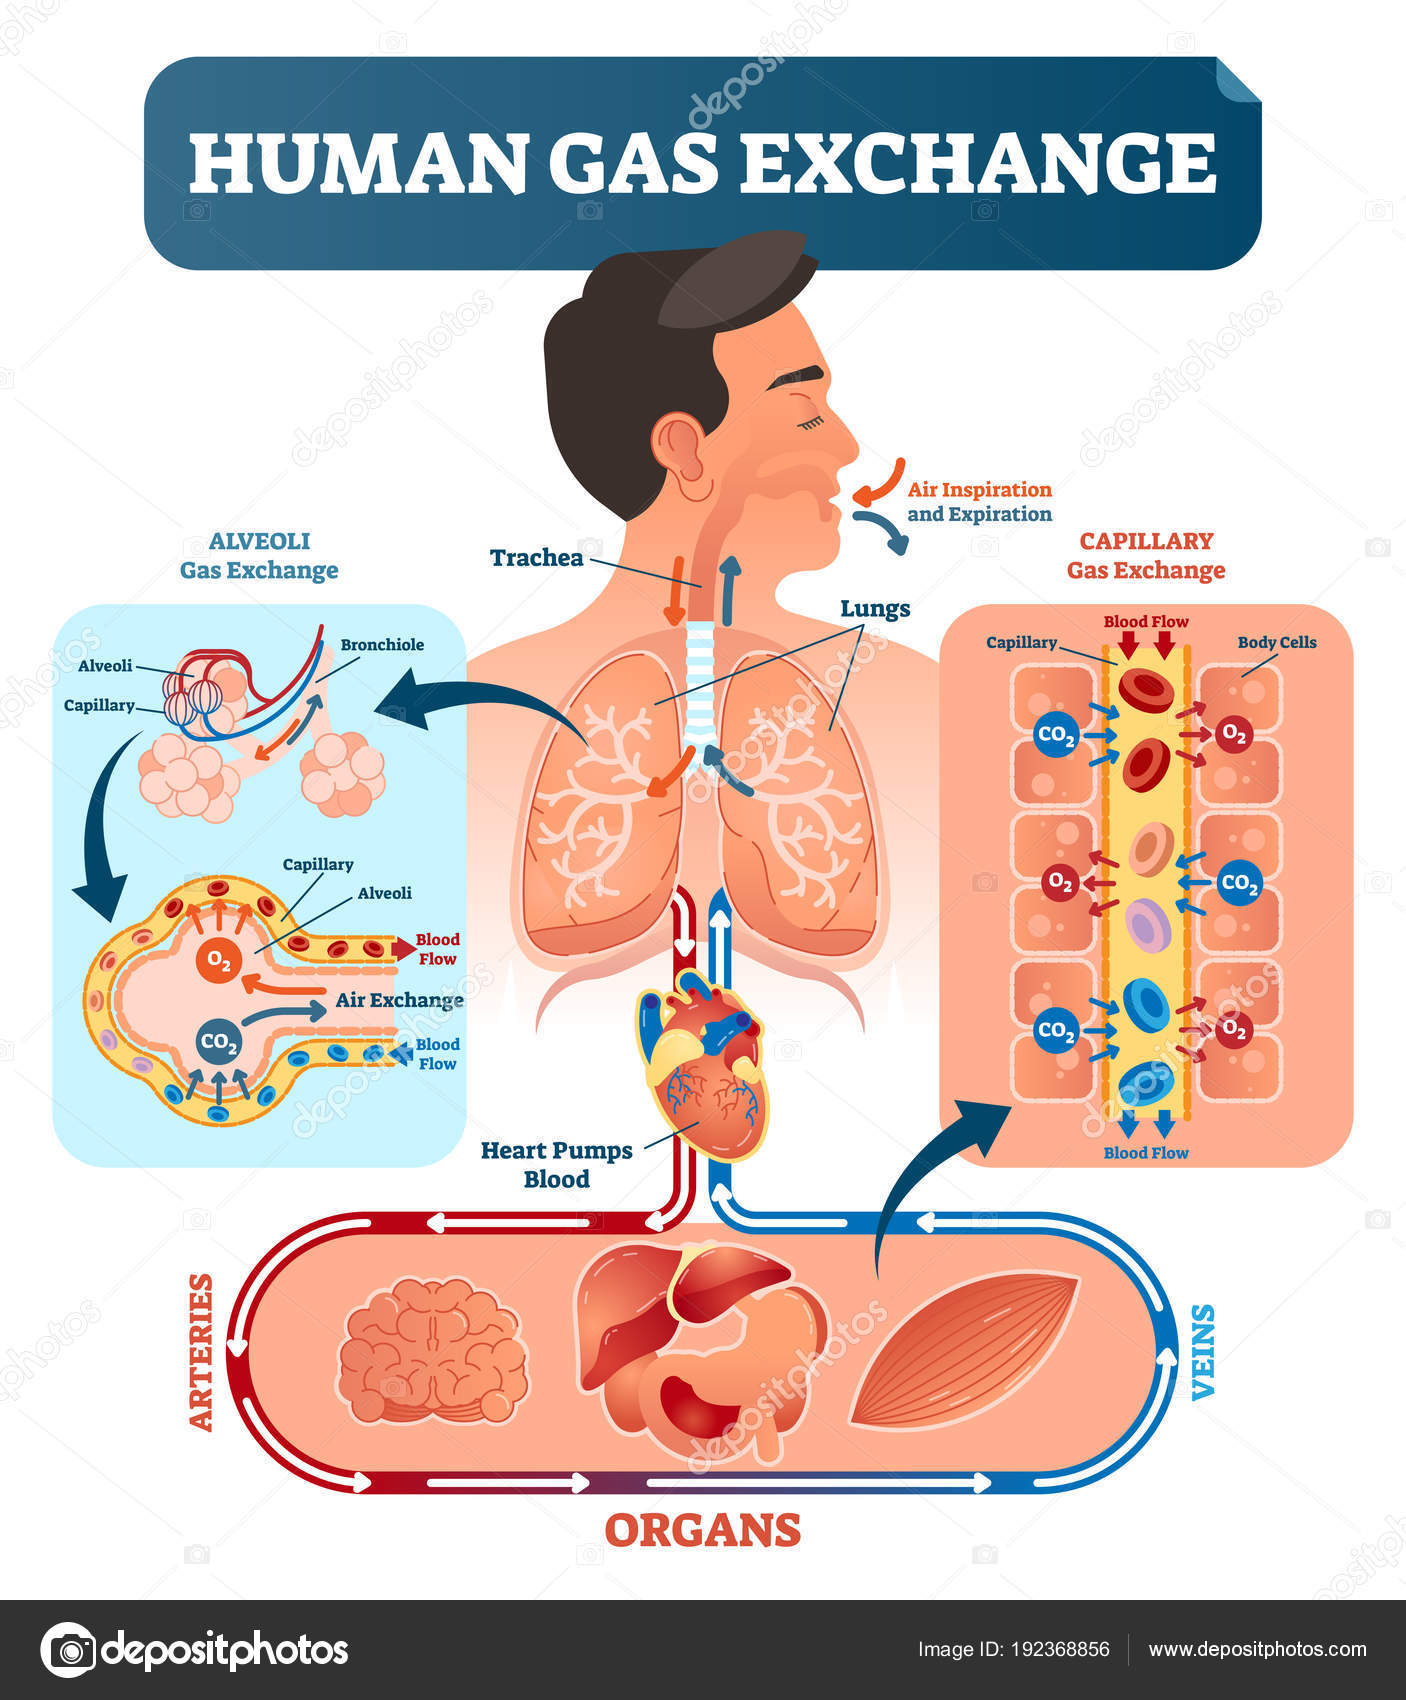
Most textbooks present the Movement Of Gases Throughout The Body as a clean, predictable process. It isn't. You breathe in oxygen, it crosses the alveolar membrane, hemoglobin picks it up, and away it goes. That's the diagram version. The real thing involves partial pressures, diffusion gradients, ventilation-perfusion matching, and enough edge cases to make your head spin if you've actually worked with patients who have compromised lung function.
I spent years reviewing pulmonary function data and watching how gases actually moved through living systems, not petri dishes. What follows is what I've learned from that work.
The Movement Of Gases Throughout The Body Actually Depends On
Partial pressure gradients. That's the driver. Oxygen moves from areas of high PO2 to low PO2. Carbon dioxide moves the opposite direction because its gradient runs the other way. Simple in theory. Complicated in practice because partial pressures shift constantly based on breathing rate, blood flow, hemoglobin saturation, and the condition of the alveolar-capillary membrane itself.
At sea level, atmospheric PO2 sits around 160 mmHg. By the time air reaches the alveoli, it's been humidified and mixed with residual air, dropping to roughly 104 mmHg. Capillary blood arriving at the lungs has a PO2 of about 40 mmHg. That 64 mmHg difference is what pushes oxygen into the blood. For CO2, the gradient runs from 46 mmHg in the blood to 40 mmHg in the alveoli. Smaller gradient, but CO2 is about 20 times more soluble in the membrane, so it diffuses faster anyway.
The alveolar-capillary membrane is thin, roughly 0.5 micrometers at its thinnest point. That thickness matters enormously. In conditions like pulmonary fibrosis or pulmonary edema, that membrane thickens and gas exchange slows down proportionally. I once worked with a patient whose diffusion capacity had dropped to less than 40% of normal due to interstitial lung disease. Their resting gas exchange was barely adequate, and any exertion pushed them into significant hypoxemia because the thicker membrane couldn't keep up with the increased blood flow demand.
Ventilation-Perfusion Mismatch Is The Real Problem
Here's where beginners get tripped up. Perfect gas exchange requires matching ventilation (airflow) to perfusion (blood flow). In reality, the lungs aren't uniform. Gravity creates zones. In an upright person, blood flow is greater at the bases than the apices. Ventilation follows the same pattern but not identically. This creates a natural V/Q mismatch that the body normally compensates for.
When that compensation breaks down, you get dead space ventilation or shunting. Dead space means air reaches alveoli but there's no blood flow to pick up the oxygen. Shunting means blood reaches the capillaries but there's no fresh air. Both situations reduce overall gas exchange efficiency.
I remember a case involving a post-surgical patient with atelectasis in the lower lobes. The collapsed segments had blood flow but essentially no ventilation. That was a right-to-left shunt, and supplemental oxygen alone didn't fix it because the shunted blood never saw the increased FiO2. The workaround was continuous positive airway pressure to recruit the collapsed alveoli and restore ventilation-perfusion matching. O2 therapy without addressing the underlying V/Q mismatch is one of those things people do routinely that doesn't produce the expected results.
Hemoglobin Binding Changes Everything
Oxygen doesn't travel dissolved in plasma in any meaningful quantity. Less than 2% of arterial oxygen is physically dissolved. The rest is bound to hemoglobin. Each gram of hemoglobin can carry about 1.34 mL of oxygen. A typical adult with 15 grams of hemoglobin per deciliter can carry roughly 20 mL of oxygen per 100 mL of blood when fully saturated.
The hemoglobin-oxygen dissociation curve is sigmoidal, not linear. That shape matters clinically. At a PaO2 of 60 mmHg, hemoglobin is still around 90% saturated. This plateau means moderate drops in arterial oxygen don't immediately cause catastrophic desaturation. But once you drop below that 60 mmHg threshold, saturation falls rapidly. That's the steep part of the curve.
Several factors shift this curve to the right, meaning hemoglobin releases oxygen more readily at any given partial pressure. Those factors include increased CO2 (the Bohr effect), decreased pH (acidosis), increased temperature, and elevated 2,3-DPG levels. A rightward shift is actually beneficial during exercise when tissues need oxygen more. The problem comes when conditions cause excessive rightward shift at rest or when leftward shift impairs unloading.
Carboxyhemoglobin from carbon monoxide exposure shifts the curve leftward and blocks oxygen binding sites simultaneously. That's why CO poisoning is so dangerous beyond just displacement. It also makes the remaining hemoglobin hold onto oxygen tighter, reducing delivery to tissues.
Carbon Dioxide Transport Is More Complex Than Oxygen
CO2 travels in three forms: dissolved CO2, bicarbonate ions, and carbaminohemoglobin. About 70% converts to bicarbonate via carbonic anhydrase inside red blood cells. The chloride shift maintains electrical neutrality as bicarbonate leaves the RBC. About 23% binds to hemoglobin as carbaminohemoglobin. Only roughly 7% remains dissolved.
The Haldane effect describes how oxygenated hemoglobin has a reduced capacity for CO2, which is why CO2 loading in the tissues and oxygen loading in the lungs are mutually reinforcing processes. This coupling is essential for efficient gas exchange in both directions.
One thing that catches people off guard: the majority of CO2 transport depends on intact red blood cell function and adequate carbonic anhydrase activity. Conditions affecting RBCs or enzyme function can impair CO2 removal more than you'd expect from looking at oxygenation alone.
Practical Limitations And When Gas Exchange Fails
High altitude reduces the driving pressure for oxygen diffusion because barometric pressure drops. The alveolar PO2 falls proportionally, and below roughly 3,000 meters, most people begin experiencing some degree of hypoxemia without acclimatization. Supplemental oxygen restores the gradient, but that's a treatment, not a solution to the underlying pressure problem.
Pulmonary fibrosis thickens the diffusion barrier and reduces surface area. Diffusion-limited gas exchange becomes the dominant problem rather than perfusion-limited. Exercise intolerance in these patients is partly because increased cardiac output during activity gives red blood cells less time to equilibrate with alveolar gas. The transit time through pulmonary capillaries drops from about 0.75 seconds at rest to potentially 0.3 seconds during heavy exercise. In healthy lungs, equilibrium is reached in about 0.25 seconds, so there's reserve. In fibrotic lungs, that reserve is gone.
Obstructive lung diseases like COPD create regions with poor ventilation relative to perfusion. The V/Q ratio drops locally. These patients often maintain reasonable oxygenation at rest by increasing their minute ventilation, but they're working much closer to their limits. The dead space in emphysema reduces effective alveolar ventilation, meaning a significant portion of each breath goes nowhere useful.
The limitation most people don't consider: gas exchange capacity doesn't decline dramatically with age until around 65, but there is a measurable decrease in diffusing capacity, chest wall compliance, and the effectiveness of ventilatory control. Older adults often tolerate hypoxic challenges poorly not because their lungs are diseased but because their physiological reserve is diminished.
What Actually Improves Gas Exchange In Practice
Improving V/Q matching is more effective than simply increasing inspired oxygen in most clinical scenarios. Pursed-lip breathing in COPD patients maintains positive airway pressure and prevents airway collapse during exhalation, which improves alveolar ventilation and reduces dead space. Positioning matters too. In patients with unilateral lung disease, placing the better lung down improves perfusion to ventilated areas and reduces shunting.
The bottom line is that understanding partial pressures, membrane properties, hemoglobin dynamics, and V/Q relationships gives you a working model that actually predicts what will happen. Textbook diagrams are useful for learning the components. Real physiology is messier, less predictable, and depends heavily on individual variation. If you're working with actual patients or trying to optimize performance, the details matter more than the general principles.
Gallery Movement Of Gases Throughout The Body
Human Body Gas Exchange Process Diagram Lungs Trachea Stock Illustration - Illustration of ...
Human Body Gas Exchange Process Diagram Lungs Liver Stomach Stock Illustration - Illustration of ...
Gas exchange occurs at two sites in the body: in the lungs and at the tissues Stock Photo - Alamy
Alveolus gas exchange and Body tissues gas exchange animation - Images | Picstank.com
Gas Exchange Human Body Anatomical Vector Stock Vector (Royalty Free) 1402450013 | Shutterstock