MPL Gene Analysis for Common Variants: What You Actually Need to Know
The MPL gene encodes the thrombopoietin receptor, and when it mutates, it drives a subset of myeloproliferative neoplasms. The two clinically significant variants most labs test for are MPL W515L and MPL W515K. These are low-frequency somatic mutations that often slip through standard sequencing panels if the assay isn't specifically designed for mutant allele sensitivity in the 1–5% range. That detail matters more than most people realize when they're ordering or interpreting results. For targeted analysis of these common MPL variants, the primary CPT code used in clinical laboratories is 81225 (Molecular pathology procedure, qualitative or quantitative PCR; MPL gene variants, common mutations). This code covers targeted mutation detection using PCR-based methods and is the standard pick when you're running a focused assay for the W515L/K hotspots. There's also 81479 (Unlisted molecular pathology procedure) that sometimes gets used by labs offering custom NGS panels that include MPL alongside other MPN-associated genes like JAK2 and CALR, though its use is a billing gray area and some payers push back on it. I've seen more denials on 81479 than I care to count. If you're submitting claims, stick to 81225 whenever your test is restricted to the common MPL variants. Only reach for the unlisted code when you're genuinely doing something outside the scope of existing codes, and even then, have documentation ready.
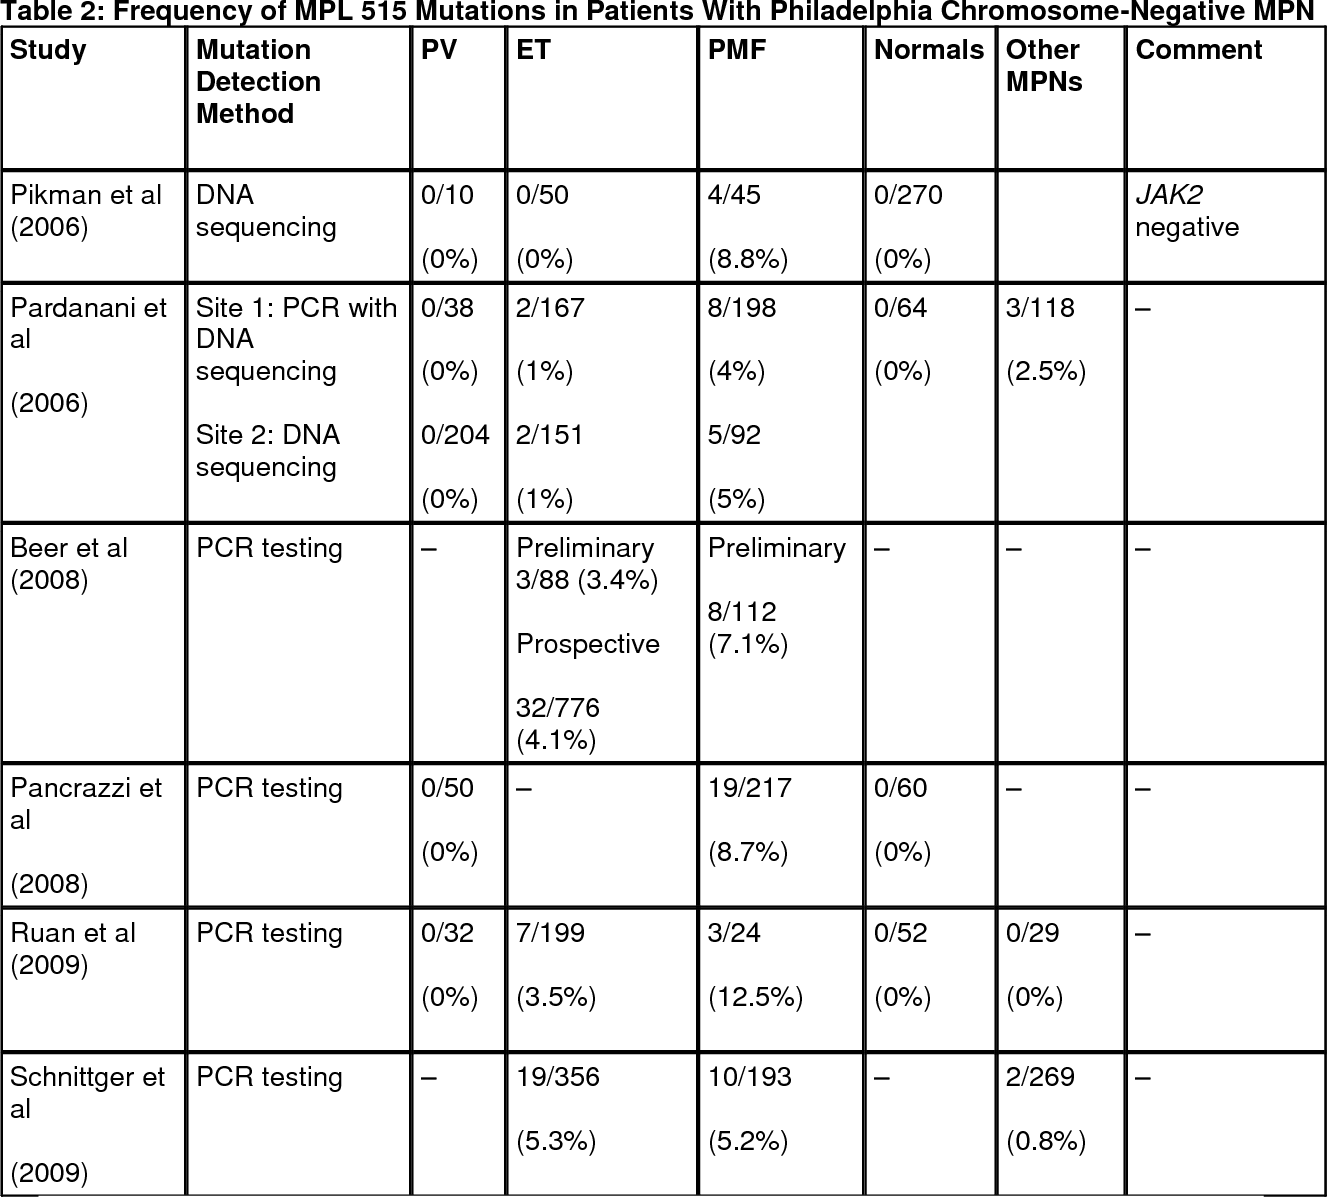
Here's the practical workflow: you extract DNA from a peripheral blood or bone marrow sample, run allele-specific PCR or a targeted digital PCR assay, and interpret the results. The whole process typically takes about 4 to 6 hours in a well-run lab. Turnaround time for the report is usually 3 to 5 business days depending on batch scheduling. Most reference labs run MPL testing in weekly batches, so if you send a specimen on Thursday, it might not run until the following Tuesday. One thing that catches people off guard: the sensitivity threshold matters enormously. A standard Sanger sequencing approach on MPL will reliably detect variants only if the mutant allele frequency is above 15–20%. In practice, many ET and PMF patients present with MPL mutations at 1–5% VAF. If your lab uses Sanger and reports a negative, that doesn't mean the patient doesn't have an MPL mutation. It means their mutation burden is below the detection limit of that particular method. Digital PCR or deep NGS with appropriate depth is needed for low-frequency detection. This distinction comes up constantly in hematology consultations and is worth clarifying before you order the test. Another edge case I ran into repeatedly: sample type. Some labs accept EDTA whole blood for MPL testing, but if the patient has already started treatment with a JAK2 inhibitor or has undergone recent transfusion, the mutant allele signal can be diluted to undetectable levels. Bone marrow samples are more reliable in those scenarios, but getting a marrow sample just for molecular testing is a significant ask. I learned this the hard way after a case where a peripheral blood sample came back negative, the patient's platelet count kept rising, and we went back six weeks later with a marrow sample that showed a clear W515L mutation at 3% VAF. The lesson was straightforward: if clinical suspicion is high and blood is negative, don't just call it negative. Consider repeat testing on a marrow specimen or a more sensitive method.
Billing nuance worth noting: if your lab performs both JAK2 V617F and MPL common variant testing in the same encounter, you generally can't bill two separate molecular pathology codes for each gene. Many labs bundle this under a single MPN panel code when one exists, or use modifier 59 on the second code to indicate a distinct procedural encounter. Payer policies vary significantly on this, and Medicare coverage for molecular testing in MPN workups has tightened over the past few years. Always verify medical necessity documentation requirements before submitting. The main limitation of MPL testing as currently practiced is that it only covers the two well-known hotspot mutations. About 5% of MPL-mutated MPN cases harbor variants outside the W515 region, and standard coding and assay design don't account for those. If you need comprehensive MPL sequencing, you're looking at a different (and less clearly defined) coding landscape. Some labs offer extended MPL sequencing under laboratory-developed test frameworks, but reimbursement for those tests remains uncertain and payer-specific. If you're ordering this test for a patient, make sure the request includes the specific clinical indication—essential thrombocythemia, primary myelofibrosis, or unexplained thrombocytosis. Without that context, labs may request additional information before running the assay, and payers will likely deny the claim for lack of medical necessity. It's a small thing that slows down a lot of otherwise straightforward orders.
Get the Full Details
.png)