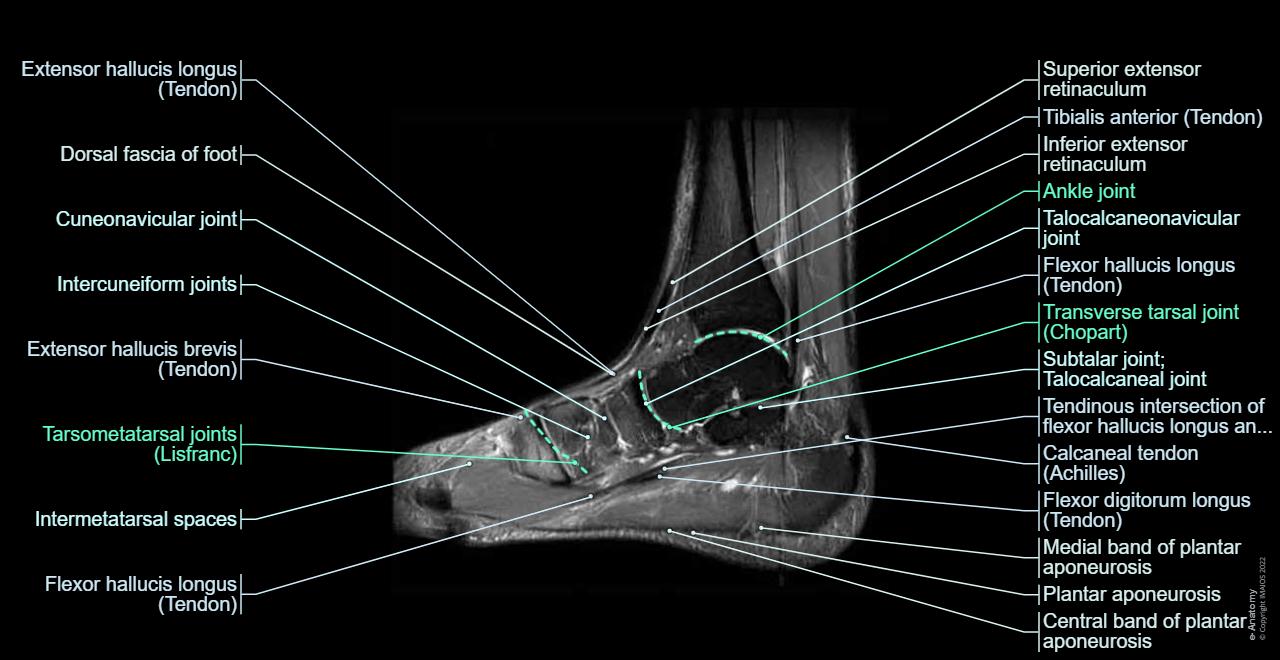
What matters most when you're actually reading a foot MRI
The first problem most people run into is that foot imaging looks deceptively simple. The anatomy is compact, the structures are small, and if you're not using the right oblique planes, you will miss real pathology. I spent years doing this in outpatient radiology before moving into musculoskeletal-specific work, and the things that actually trip people up are rarely the obvious ones. A Lisfranc injury on a routine foot Mri Anatomy Of Foot protocol gets overlooked constantly because nobody bothered to look at the oblique coronal cuts through the midfoot. The standard axial and sagittal slices are not enough. Here is how I would actually approach a dedicated foot MRI, the sequences that deserve your time, the anatomy you need to know cold, and where this modality quietly fails you.
Protocol choices that actually matter for Mri Anatomy Of Foot
A proper adult foot MRI takes roughly 30 to 40 minutes on a 1.5T or 3T scanner. You do not need every sequence available. You need the ones that answer the clinical question. If the referral says plantar fasciitis, you are not running a whole-foot pan-scan. If it says chronic lateral ankle pain with suspected peroneal tendonopathy, you want high-resolution T1 and proton density fat-saturated images in the oblique planes aligned to the foot, not the ankle. The core sequence set I rely on:
- Axial T1 and axial PD fat-sat: These are your bread and butter for the forefoot and midfoot. The Lisfranc ligament, the peroneal tendons, and the interosseous ligaments are all visible here when the slices are truly axial to the foot, not tilted into the ankle axis.
- Sagittal T1 and sagittal PD or STIR fat-sat: This is where you evaluate the plantar fascia, the Achilles insertion, the calcaneus marrow, and the tendons of the sole. The flexor hallucis longus tendon runs right along the plantar aspect of the calcaneus. That groove matters. If you miss it, you miss flexor hallucis longus tenosynovitis.
- Oblique coronal aligned to the metatarsals: I cannot stress this enough. The second through fourth metatarsal bases, the cuneiforms, and the cuboid are best seen when the slices follow the foot's long axis. Standard ankle coronals cut across these structures at an angle and blur the detail you need for a Lisfranc assessment.
- Oblique axial aligned to the plantar fascia: Some people skip this, but if the referral mentions medial heel pain, a dedicated plane through the plantar fascia origin gives you far better visualization than angled sagittal cuts alone.
At 3T, the signal-to-noise ratio is better, which means you can push spatial resolution down to about 0.4 by 0.4 millimeters in the in-plane direction without making the scan unbearably long. At 1.5T, you are usually trading off a bit of resolution for acceptable scan time. Both are clinically adequate if you know what you are looking for. The foot has twenty-six bones, thirty-three joints, and more than one hundred intrinsic muscles and tendons. Most of the clinically relevant pathology sits in a surprisingly small subset of those structures. When I read a foot MRI, my brain is constantly checking these regions in order: Plantar fascia origin: It inserts on the medial calcaneal tubercle and the plantar aspect of the calcaneus. Normal signal is low on all sequences. Thickening beyond 4 millimeters at the insertion with adjacent fat stranding on fat-sat images is the classic plantar fasciitis pattern. Deep ulceration into the calcaneal cortex suggests advanced disease or atypical infection. I once spent twenty minutes chasing a suspected stress fracture in a runner's calcaneus before I realized the real problem was a thickened plantar fascia with perifascial fluid. The stress reaction was incidental and asymptomatic. Clinical correlation is not optional here.
Get the Full Details

Tibialis posterior tendon: This tendon passes behind the medial malleolus, crosses the sustentaculum tali, and inserts primarily on the navicular bone. It is the main dynamic stabilizer of the medial arch. On axial images at the level of the subtalar joint, you should see the tendon as a round, low-signal structure sitting anterior to the flexor digitorum longus and medial to the flexor hallucis longus. Degeneration shows as intermediate signal within the tendon substance. Full-thickness tears often retract. I had a case where the tendon looked intact on the initial read because the slices were slightly misaligned. The oblique coronal view through the navicular insertion revealed a complete rupture with retraction. That is the kind of error that happens when you only look at one plane. Peroneal tendons: The peroneus longus and brevis run behind the lateral malleolus in a shared retromalleolar groove. The brevis sits posterior and the longus anterior on axial slices. Split tears of the peroneus brevis are common in dancers and soccer players. They appear as linear high signal tracking within the tendon on fat-sat sequences. The key is distinguishing intrasubstance splitting from tenosynovial fluid. Fluid tracks around the tendon and displaces it. A split tear stays within the tendon boundaries. Confusing the two leads to completely different treatment paths. Flexor hallucis longus: This tendon runs in a shallow groove on the posterior calcaneus, passes between the two heads of the flexor hallucis brevis, and inserts on the distal phalanx of the big toe. It is prone to tenosynovitis, particularly in ballet dancers who spend years on en pointe. The Dorsalis pedis artery and the medial plantar nerve run close by on the dorsum. Nerve compression here is rare but devastating when missed.
Lisfranc complex: The tarsometatarsal joints form the Lisfranc complex. The most important ligament is the dorsal Lisfranc ligament, which runs from the medial cuneiform to the base of the second metatarsal. This is the keystone. If this ligament is disrupted, the second metatarsal base subluxes laterally. On axial images, look for a gap larger than 2 millimeters between the medial cuneiform and the second metatarsal base. On oblique coronal slices, look for loss of the normal arc formed by the articular surfaces of the cuneiforms and the cuboid. The homolaterality sign is your friend: all three cuneiforms should align with their corresponding metatarsal bases. If the second metatarsal base is dorsal to the middle cuneiform on sagittal images, you have a Lisfranc injury until proven otherwise. Sesamoid bones: Two sesamoids sit beneath the first metatarsal head within the flexor hallucis brevis tendon. They are frequently fractured in athletes. On axial and sagittal images, they should be symmetric in size and signal. Asymmetric size with marrow edema in one and not the other suggests a stress reaction. Complete fragmentation with surrounding fluid suggests an acute fracture. I once misread a bipartite sesamoid as a fracture in a soccer player because I did not check the contralateral foot first. A quick scout view of the other foot would have saved me the embarrassment. Tarsal tunnel contents: The tibial nerve and its branches, the posterior tibial artery and vein, and the tendons of the tibialis posterior, flexor digitorum longus, and flexor hallucis longus all pass through the tarsal tunnel posterior to the medial malleolus. Space-occupying lesions here, including ganglion cysts and varicosities, cause compressive neuropathy. The nerve should be oval and low-signal. Abnormal intraneural signal on fat-sat sequences indicates neuritis or more severe compression. I evaluated a patient with chronic medial foot pain where the standard imaging was unremarkable. A small ganglion cyst arising from the talonavicular joint was compressing the medial plantar nerve. It was only visible on the oblique axial plane through the tunnel. This is the kind of finding that demands you look beyond the obvious.
A specific edge case that changed how I read these studies
About four years ago, I was reading a routine foot MRI for a diabetic patient with chronic lateral foot pain. The initial impression was degenerative changes and mild peroneal tenosynovitis. Everything looked essentially normal except for some subtle bone marrow edema in the lateral cuneiform and the base of the second metatarsal. I signed it out as nonspecific. Three months later, the patient returned with acute worsening, and an orthopedic surgeon mentioned they had found an occult Lisfranc injury on a weight-bearing CT that we had completely missed on the MRI. The problem was not that the MRI was bad. The problem was that I was reading it supine, non-weight-bearing, which is the standard protocol. The Lisfranc ligament is a stabilizer against dorsalis flexion and axial loading. Without weight, the subtle diastasis can remain hidden, especially in early or incomplete injuries. Bone marrow edema patterns alone are not diagnostic. After that case, I started pushing for weight-bearing coronal views whenever the clinical suspicion was high and the non-weight-bearing scan was equivocal. Weight-bearing MRI is not widely available, but even weight-bearing radiographs in the same session can change the management pathway. The takeaway is simple: a negative MRI does not rule out a ligamentous injury if the clinical picture does not fit. Always keep the diagnosis broad enough to explain the symptoms.

Common misread patterns and how to avoid them
The foot is a minefield of normal variants and incidental findings. A few of the most common traps I see repeatedly: Os peroneum fractures versus bipartite os peroneum: The os peroneum is a small sesamoid bone within the peroneus longus tendon as it wraps around the cuboid. It is present in about 2 to 3 percent of the population as a separate ossicle, and it can be fractured. A fractured os peroneum shows irregular margins, marrow edema in the adjacent bone and soft tissues, and often fragment displacement. A bipartite os peroneum has smooth, corticated margins on all sides and no surrounding edema. If you see edema, treat it as a fracture until proven otherwise. If the margins are smooth and symmetric, it is a variant. Stress reactions versus stress fractures: Bone marrow edema on fat-sat sequences is sensitive but not specific. A stress reaction shows diffuse marrow edema without a visible fracture line. A stress fracture shows a low-signal line traversing the cortex, often surrounded by edema. The metatarsal necks and the proximal phalanx of the hallux are the most common sites. In runners, a stress reaction in the second metatarsal shaft is so common that it is almost expected. The question is whether it is the pain generator. I cor


