Why Hands Wrist MRIs Usually Come Back as "No Acute Abnormality"
I read enough of these studies to know exactly which ones are worth your time and which ones are just radiologist noise. The problem isn't the technology. It's that most protocols are run on low-field scanners with coil setups that were designed five years ago, and the technologist is rushing because the schedule is backed up three hours. A good hand and wrist study takes about 25 to 30 minutes on a 3 Tesla system with a dedicated phased-array extremity coil. A rushed one on a 1.5T open scanner with a wrap-around surface coil will miss a partial-thickness scapholunate tear every single time you ask me about it. I've seen it repeatedly.
What Mri Of The Hand And Wrist Actually Shows You
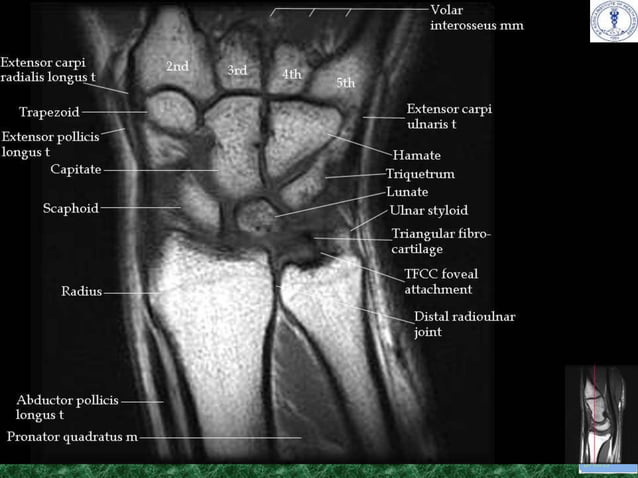
Most people ordering this study think it's going to answer one question. It rarely does. The hand and wrist contain more complex ligamentous anatomy than almost any other region in the body, and the standard protocol is designed to look at multiple structures simultaneously. That's the point, but it's also the source of most errors. The primary pathologies you're looking for fall into clear categories. Ligamentous injuries dominate—the scapholunate ligament, the lunotriquetral ligament, and the volar radiocarpal ligaments are the big three. Then there's TFCC pathology in the distal ulna, ganglion cysts arising from the dorsal or volar capsule, EPL ruptures secondary to distal radius fractures, and chronic tenosynovitis that looks completely different on T1 versus T2 fat-suppressed sequences. Don't forget stress reactions of the scaphoid or hamate, which only show up clearly on STIR or fat-sat PD sequences.
The Protocol Matters More Than the Field Strength
I've read studies from 3T machines that were worse than 1.5T exams from ten years ago, purely because the protocol was wrong. Here's what I actually expect to see in a competent hand and wrist MRI: T1-weighted FSE in at least two planes—coronal and sagittal are mandatory, axial is nice to have but not essential for ligament work. Then a T2-weighted or PD fat-saturated sequence in the same planes. STIR is useful for bone marrow edema and acute ligament injury, but it has lower spatial resolution, so I don't rely on it alone. A dedicated high-resolution gradient echo sequence with a small FOV—something like 8 centimeters—is where the subtle stuff lives. Matrix sizes around 384 by 256 or higher with a 1.5 millimeter slice thickness are what separate a useful exam from a useless one. The coil positioning is where most outpatient centers mess this up. The wrist needs to be truly neutral. Not supinated, not pronated, not awkwardly cranked to fit inside the coil. If the hand is rotated even 15 degrees off neutral, the scapholunate interval gets distorted and you'll either miss a tear or create a false-positive appearance of widening. I've had to recommend repeat imaging at least four times in the last year because the initial study was technically inadequate. That's costly for everyone involved.
Get the Full Details

The Specific Problem I Keep Running Into
There's one issue that comes up constantly and nobody seems to think about it. Motion artifact from patient tremor or inability to stay still. Hand and wrist MRI requires submillimeter resolution, and a tremor of just 0.5 millimeters during a 4-minute acquisition will blur the scapholunate ligament enough to make a complete tear look intact or vice versa. This isn't theoretical. I saw a case last year where a patient with Parkinson's was imaged without any motion compensation, and the resulting images showed what looked like a normal scapholunate ligament. The patient actually had a complete tear confirmed at surgery three weeks later. The motion had simply averaged the signal across the ligament bed. The workaround is straightforward if the technologist knows to do it. Use a shorter TE, increase the number of signal averages, and if the scanner supports it, apply prospective motion correction. Some newer systems have real-time navigator echoes that can pause and resume acquisition when motion is detected. On older systems, breath-hold commands don't help here since this is the periphery, but having the patient hold their arm perfectly still with proper immobilization padding makes a measurable difference. I always check the raw images, not just the reformatted slices, before signing out these studies. A single corrupted k-space line can ruin an entire acquisition and the technologist won't always catch it.
Common Pitfalls That Waste Time and Money
The biggest mistake I see is ordering a whole-wrist protocol when the clinical question is localized. If you suspect a ganglion cyst on the dorsal aspect, a dedicated small FOV study focused on that region with high-resolution sequences will take 12 minutes and give you better answers than a 30-minute whole-wrist sweep. The inverse is also true—if you're evaluating for occult fracture or diffuse synovitis, a limited protocol will miss everything outside the box. Another pitfall is relying on T2-weighted images without fat saturation. Ganglion cysts and synovial tissue both have high signal on T2, but so does normal subcutaneous fat. Without fat suppression, you're essentially looking at a foggy window. The difference between a diagnostic and non-diagnostic study often comes down to whether fat saturation was applied correctly and consistently across all sequences. Contrast is almost never necessary for routine hand and wrist imaging. I've seen gadolinium ordered for supposed "better ligament visualization" and it simply doesn't work that way. The ligaments are avascular. Contrast helps with synovitis, tenosynovitis, and post-surgical scar versus recurrent tumor, but for the common ligamentous and TFCC injuries, a well-performed non-contrast study is sufficient and avoids the additional time and cost.
When MRI Isn't the Right Call
I need to be honest about the limitations here. MRI is poor at detecting early osteoarthritis compared to CT or even high-quality radiographs. If you're looking for subchondral cysts, osteophyte formation, or joint space narrowing in the carpometacarpal joint of the thumb, a dedicated CBCT or even a standard X-ray series will give you more actionable information faster and cheaper. MRI also struggles with metallic artifacts from prior surgical hardware. A plate and screws from a distal radius fixation will create enough susceptibility artifact to render most of the adjacent carpal bones uninterpretable. In those cases, ultrasound or CT arthrography is more practical. There's also the issue of cost and access. A comprehensive hand and wrist MRI on a commercial system runs between 800 and 2,400 dollars depending on your region and facility. Insurance prior authorization is increasingly common, and denials happen when the ordering documentation doesn't specify the clinical indication with enough detail. "Wrist pain" is not an acceptable indication. You need something like "chronic ulnar-sided wrist pain rule out TFCC tear" or "dorsal wrist mass rule out ganglion cyst." The specificity matters for authorization and for the radiologist interpreting the study.

Practical Advice for Anyone Getting This Scan
If you're the patient, keep your arm absolutely still. Don't try to help by adjusting your position mid-scan. The coil is positioned for a reason, and moving it will degrade the entire study. If you have claustrophobia, ask about an open 1.5T system, but understand that image quality will be lower. If you have a tremor disorder, tell the technologist beforehand so they can adjust the protocol. Bring any prior imaging if available—comparing to old studies is often more useful than the current study alone for tracking ligament healing or cyst progression. If you're the ordering clinician, be specific about the clinical question. A focused protocol beats a blanket protocol every time. Make sure the referring information includes mechanism of injury, duration of symptoms, and any prior treatment. The radiologist needs to know whether this is acute trauma or chronic degenerative change, because the expected findings and the appropriate sequences differ significantly between those two scenarios. The bottom line is that hand and wrist MRI is a high-resolution, high-detail exam that demands proper technique from start to finish. It's not a screening tool, it's not fast, and it's not interchangeable with other imaging modalities. When done correctly on the right indication, it's incredibly informative. When done poorly, it's just an expensive way to see nothing clearly.