Getting the Basics Right Before You Start
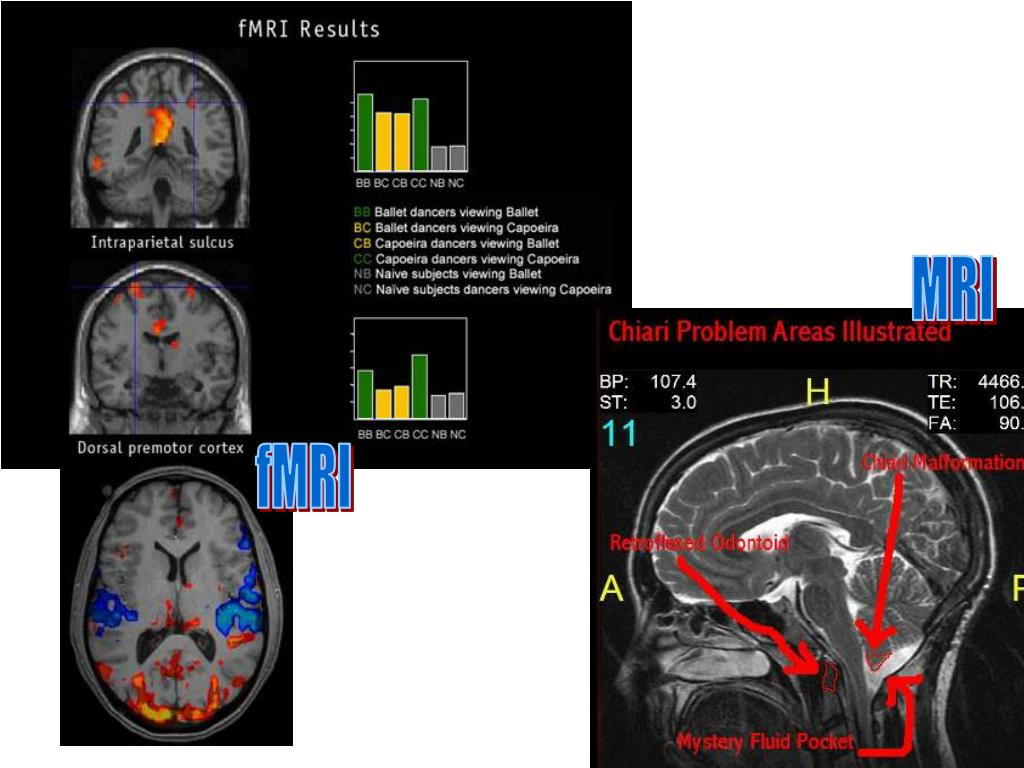
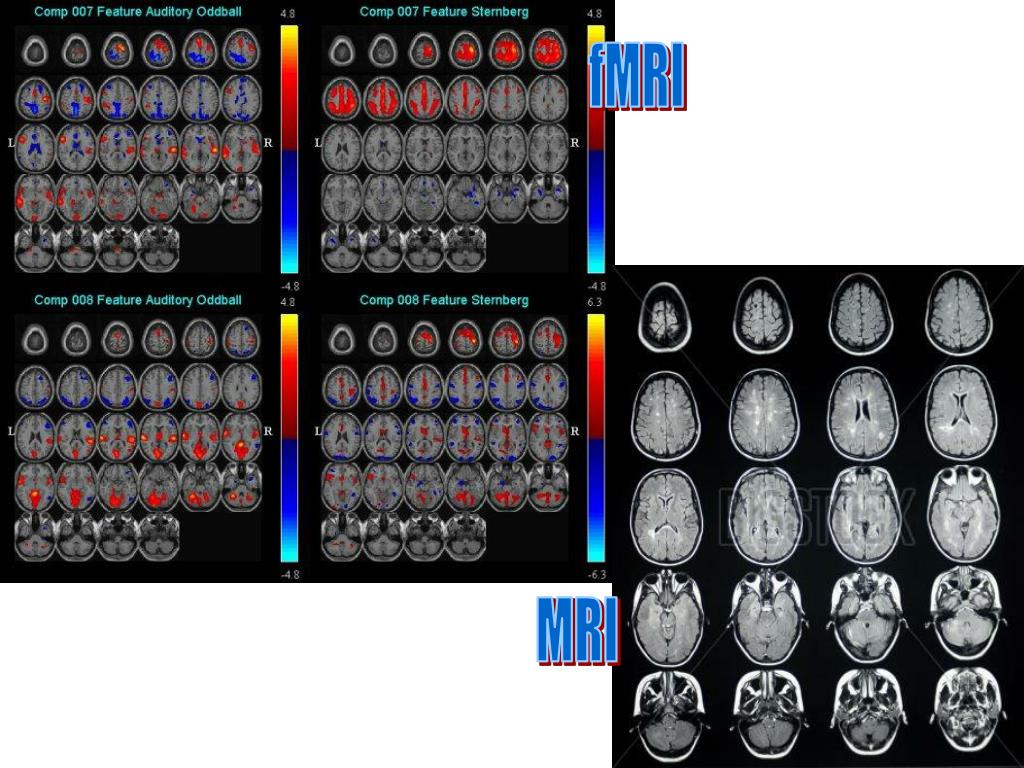
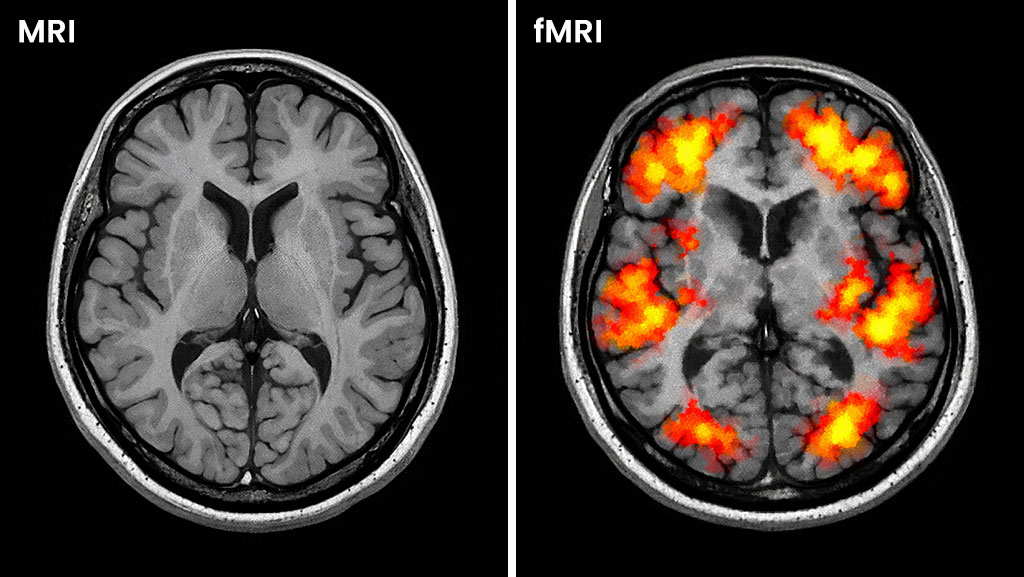
MRI and fMRI are often lumped together because the hardware looks identical, but they solve fundamentally different problems. A structural MRI gives you a high-resolution anatomical map. It shows you what the brain looks like. An fMRI shows you what the brain is doing, roughly speaking, by measuring blood oxygenation changes that accompany neural activity. That distinction matters because it determines everything from how you set up the scan to how you interpret the output. I spent years running clinical and research protocols side by side, and the most common mistake I see people make is treating them as interchangeable. They are not. One tells you where things are. The other tells you when things light up, and even then, it does so with a time resolution measured in seconds rather than milliseconds.
Mri Scan Vs Fmri: What Each One Actually Measures
The structural MRI uses a strong static magnetic field, typically 1.5 to 3 Tesla in clinical settings, and sometimes 7T in research. Radiofrequency pulses excite hydrogen protons in water and fat molecules. Different tissues relax at different rates, and that relaxation difference is what creates contrast. T1-weighted images emphasize anatomy. T2-weighted images highlight fluid. FLAIR suppresses CSF signal to make lesions more visible. You pick the sequence based on what you are looking for. fMRI works differently. It relies on the BOLD signal, which stands for Blood Oxygenation Level Dependent. When a brain region becomes active, blood flow increases to that area, and the ratio of oxygenated to deoxygenated hemoglobin shifts. Oxygenated hemoglobin is less paramagnetic than deoxygenated hemoglobin, so the MR signal changes slightly. The change is tiny, usually around 1 to 3 percent above baseline. You need careful experimental design and decent statistics to pull a meaningful signal out of that noise. The TR, or repetition time, on a standard echo-planar imaging fMRI sequence runs somewhere between 2 and 3 seconds. That means you get one whole-brain volume every few seconds. Structural scans at 1mm isotropic resolution take longer to acquire but give you detail you simply cannot get from the functional run. A typical high-quality MPRAGE T1 sequence might take 5 to 8 minutes on a 3T scanner.
Here is something most guides skip: fMRI does not measure neuronal firing directly. It measures a hemodynamic response that lags the actual neural activity by about 4 to 6 seconds. The shape of that response function varies across regions and across individuals. If you are designing a task-based experiment and your condition duration is shorter than the hemodynamic response, your conditions will blur together and your analysis will suffer. Keep your blocks or events long enough to let the BOLD signal do its thing.
Get the Full Details
Setting Up a Practical Workflow
If you are running a study that needs both, the standard approach is to acquire the structural scan first while the participant is still fresh. Motion degrades both kinds of data, but motion during the functional run is especially destructive because even sub-millimeter shifts can create artificial activation patterns that look real in your statistical maps. I have seen entire time series ruined by a participant who drifted two millimeters over twenty minutes. You can correct for some of it with realignment algorithms, but prevention is cheaper than correction. Before the participant enters the scanner, run a quick localizer. This is a low-resolution scan that gives you a rough anatomical reference for planning your slices. Modern scanners do this automatically in most cases, but checking the positioning manually saves you from discovering later that your functional volumes missed the region you actually cared about. I once had a fMRI run where the posterior cingulate was partially cut off because the localizer angle was off by a few degrees. That wasted forty-five minutes and required a rescan. For the functional run itself, you need a task or a resting state protocol. Task-based fMRI requires careful timing. You design blocks or events, align them to the scanner clock, and hope the participant stays still and follows instructions. Resting-state fMRI is simpler to run but harder to analyze cleanly because you are looking for spontaneous low-frequency fluctuations rather than task-evoked responses. Both approaches are valid. They just answer different questions.
One practical detail that people overlook: head coil selection matters more than you might think. A 32-channel head coil gives you better signal-to-noise ratio than an older 8-channel or 16-channel system, and that advantage compounds during preprocessing. Parallel imaging techniques like SENSE or GRAPPA use the spatial information from multiple coil elements to reduce distortion and speed up acquisition. If your scanner has a modern coil, use it and adjust your sequence parameters accordingly. I ran into a specific problem once where a participant had dental braces. The metal created a massive susceptibility artifact that warped the entire anterior portion of the brain in both the structural and functional images. Standard field-map correction did not help because the artifact was too severe. What worked was switching to a multi-echo EPI sequence and combining the echoes during post-processing. The multi-echo approach separates BOLD signal from non-BOLD artifacts based on their T2* decay properties. It added about three minutes to the scan, but it recovered usable data from a subject we would otherwise have had to exclude. Not every site has the sequence available, so check with your technologist before you commit to a design that might run into this issue.
Processing and Analysis Considerations
Structural data goes through segmentation, normalization, and smoothing. Tools like FSL, SPM, and FreeSurfer handle this differently, and each has its own assumptions. FreeSurfer is thorough but slow. It can take six to eight hours per subject on a decent workstation. FSL's FAST is faster but less detailed in terms of cortical reconstruction. Pick the pipeline that matches your question and your compute resources. Functional preprocessing is more steps and more places for things to go wrong. You typically start with slice-timing correction, then motion correction, then spatial normalization into standard space, and finally spatial smoothing. Some pipelines also include physiological noise regression using RETROICOR or similar methods if you collected cardiac and respiratory data during the scan. You do not have to collect that extra data, but if you are doing high-quality work and your scanner supports it, it improves your noise modeling significantly. A counter-intuitive point about smoothing: more smoothing does not always mean better results. Smoothing increases signal-to-noise ratio by averaging adjacent voxels, but it also reduces spatial specificity. If you are doing regional analysis or comparing small structures, heavy smoothing can blur signals together and make distinct activations indistinguishable. A common rule of thumb is to smooth to about twice the voxel size, but that is a guideline, not a law. Match your smoothing kernel to your hypothesis and your voxel dimensions.
Another thing that trips people up is multiple comparison correction. When you test thousands of voxels, you will find apparently significant clusters purely by chance if you do not correct. False discovery rate correction is popular because it is less conservative than family-wise error correction, but it is not a free pass. At lenient FDR thresholds, you can still get false positives, especially in low-power studies with small sample sizes. The field has moved toward stricter standards over the past decade, and with good reason. Replication rates for uncorrected or lightly corrected fMRI findings are not great. Sample size is another area where expectations and reality diverge. A powered task-based fMRI study with adequate correction often needs thirty to fifty participants to detect moderate effects reliably. Many published papers use far fewer. This is not a new problem, and it is not going away because scanner time is expensive and recruitment is slow. If you are designing a study, do not skimp on N. An underpowered study wastes more than just money. It produces results that look convincing and do not hold up.
When to Choose One Over the Other
Structural MRI is the right choice when you need to identify lesions, measure atrophy, plan surgical trajectories, or establish baseline anatomy. It is also essential as a reference image for normalizing functional data. You almost never run fMRI without a co-registered structural scan. fMRI is the right choice when you need to localize function, study connectivity, or test hypotheses about cognitive processes. It cannot replace structural imaging for any of the reasons listed above, and it cannot tell you whether a observed activation is pathological or normal without anatomical context. There are scenarios where neither is sufficient. If you need millisecond-level temporal resolution, you need EEG or MEG. If you need to know whether a specific neural population is involved, you need invasive recording or at minimum a very high-field combined PET-MRI setup. fMRI is powerful for what it does, but it is a blunt instrument compared to electrophysiology. Recognizing its limits is part of using it well.
The cost difference is also worth mentioning. A clinical structural MRI exam at 3T typically runs between 800 and 2500 dollars depending on the region and the facility. A research-grade fMRI session on top of that, including scan time, personnel, and preprocessing, can add another 500 to 1500 dollars per subject. Multiply that by a reasonable sample size and the budget adds up quickly. Grant reviewers know this, and they will ask hard questions if your methods section suggests you underestimated the cost or the complexity. Finally, a word on data management. A single subject's structural scan in high resolution can be 200 to 400 megabytes. The functional data for the same subject might be another 500 megabytes to a gigabyte depending on sequence parameters and number of time points. Preprocessed data takes up less space, but intermediate files add up. Plan your storage before you start scanning. I have seen projects stall because someone forgot that raw DICOM files from a multi-echo sequence on a 3T scanner with 1200 time points could fill a terabyte in a single day of scanning.