Strategic Family Therapy Is Probably Not What Most People Think It Is
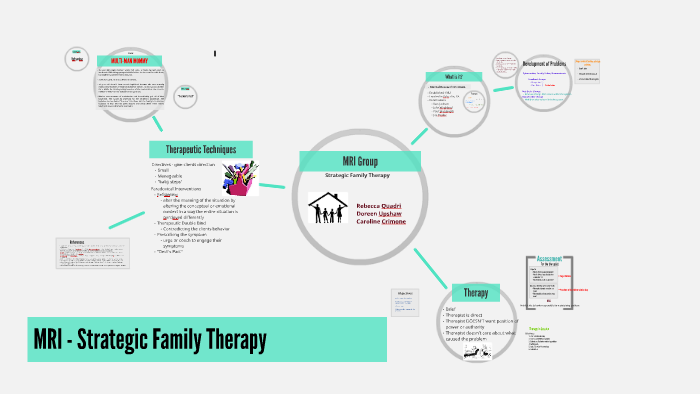
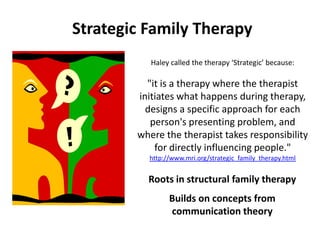
It got started in the late 1950s at the Mental Research Institute in Palo Alto, before most of the people doing family therapy had even heard of families as a treatment unit. The founding team — Don Jackson, Jay Haley, John Weakland, Paul Watzlawick — were working out of a building that doubled as a research lab. They weren't trying to build a school of thought. They were trying to figure out why certain people came back for more therapy after being declared "cured." The answer kept coming back to the same thing: the problem wasn't inside the individual. It was in the loop of interactions that kept reproducing it.
What Mri Strategic Family Therapy Actually Looks Like
The MRI approach has a few core moves, and they're simpler than they sound. The therapist spends the first session or two mapping the complaint not as a symptom but as a solution that's been tried too many times. Everyone in the family has been trying to fix something — a kid's tantrums, a parent's drinking, a teenager's refusal to leave the house — and each attempt just tightens the noose. The therapist's job is to interrupt that cycle, usually by prescribing the opposite of what everyone's been doing. Here's a case that comes to mind from when I was running sessions in this framework. A family came in with their 14-year-old who wouldn't go to school. Standard presentation. The parents were enmeshed in a pattern of nagging, threatening, pleading, and then eventually just driving the kid themselves because it was faster than the argument. The kid's behavior was maintaining parental conflict — whenever the parents fought about forcing the issue, they weren't fighting about their own marriage. Classic homeostasis move. The intervention I used was straightforward and kind of brutal in its simplicity. I told the parents to stop all school-related conversations for two weeks. No reminders, no threats, no driving them. They were to say exactly one thing: "It's your education. You decide." And they had to do it every time the kid brought it up, in the same flat tone. I also told the parents to schedule a date night twice that week with no discussion of the child. That was the real intervention, honestly. The school thing was just the lever.
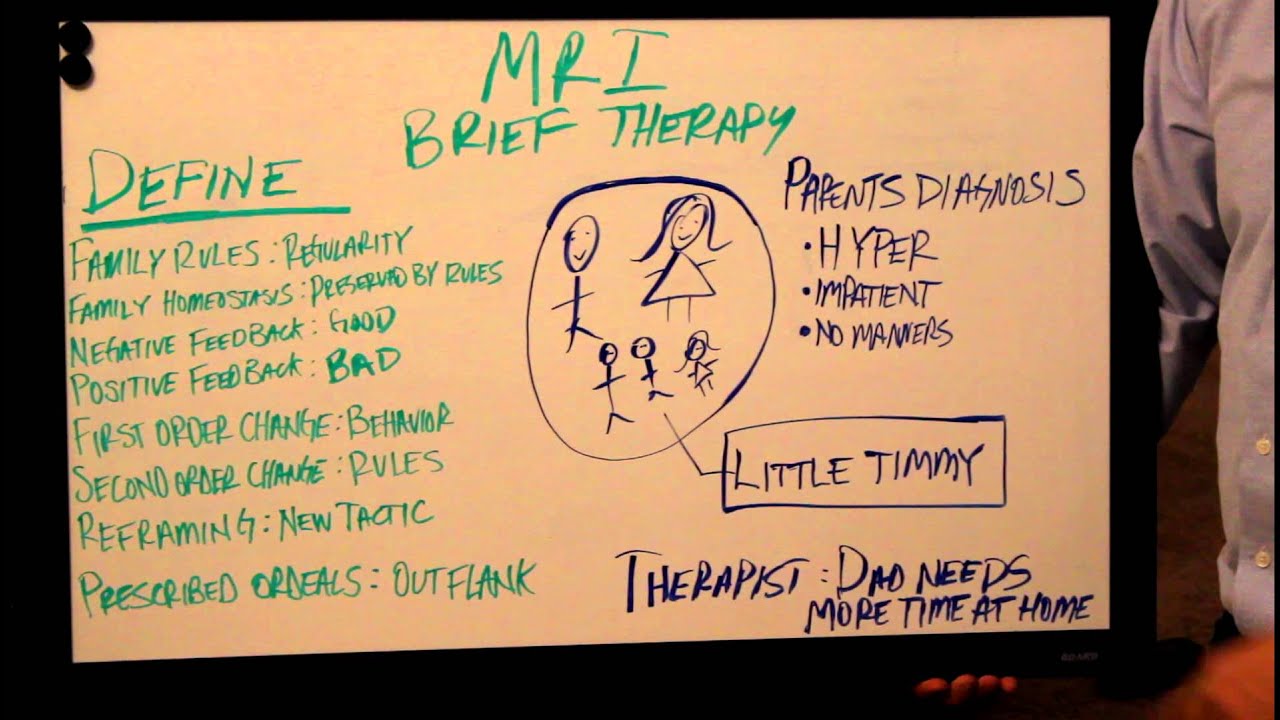
Within three weeks the kid started asking about school again. Not because the directive changed her mind directly, but because the parental system had shifted. The enmeshment loosened. The kid had to occupy a position instead of being the symptom-bearer for two people avoiding each other. This is the part beginners miss. The directive isn't the therapy. The directive is just how you create the conditions for the family to reorganize. If you focus on whether the kid goes to school on Monday, you've already lost. There are several intervention types that show up repeatedly in this work. Prescribing the symptom is the most famous one — you tell the family to intentionally continue the problematic behavior on a schedule. So a mother who compulsively checks on her depressed son gets told to check on him three times a day at set hours. It sounds absurd. It usually works because it removes the anxiety-driven spontaneity that fuels the compulsion. Another common one is the paradoxical intention, where you ask the person to try to produce the symptom on purpose. Restless legs? Try to keep them still for ten minutes. The attempt to resist the urge often neutralizes it.
Get the Full Details

Then there's the restraint directive, which is basically telling the family not to change too fast. "You can change, but only once a week and only when I tell you to." It sounds counterproductive. It bypasses resistance by removing the family's ability to fight the therapy itself. The positioning technique is less known and more useful. The therapist aligns with the most resistant member of the family — usually the identified patient — and treats their behavior as reasonable given the context. This disarms the power struggle. The resistant kid stops resisting the therapist because the therapist isn't trying to make them behave.
The Core Mechanism: Second-Order Change
Underneath all of this is a distinction between first-order and second-order change that comes from systems theory and cybernetics. First-order change is movement within a system. The family argues longer, the parent threatens more harshly, the kid screams louder. It's all happening inside the same rules. Second-order change is when the rules themselves shift. The family stops arguing about the symptom and starts noticing that the arguing was the problem. A common mistake — and I see this a lot in training — is that people confuse directive compliance with therapeutic change. The family follows the prescription perfectly and the behavior shifts temporarily, but the interactional rules are identical. That's first-order change dressed up as progress. The difference matters because first-order fixes tend to relapse. Second-order changes stick because the family's operating system has been rewritten, not just its output. Getting to second-order change requires what Watzlawick called "enough difference." The therapist can't be just another voice in the family system telling them what to do. That lands squarely in first-order. The intervention has to come from a frame the family doesn't already have. Sometimes that means literal unusualness — doing something in session that would be bizarre and break the pattern. Sometimes it's just reframing the symptom as a misguided attempt at care rather than defiance.
Reframing is probably the single most important tool in this model and also the most neglected by people who skim the surface. A reframing isn't positive thinking. It's a deliberate reinterpretation that changes the meaning of the behavior within the family system. When a father sees his daughter's anorexia not as manipulation but as her way of preserving the marriage by keeping both parents focused on her instead of their own issues, the entire dynamic becomes visible. The father can then choose to step out of that role. That's when change actually happens.
Where This Approach Breaks Down
Strategic therapy isn't universal. It fails in a few predictable situations and it's worth knowing before you commit to it. Severe personality disorders, especially borderline and active psychopathy, don't respond well to indirect interventions. These clients will use the therapist's ambiguity against them. Paradoxical prescriptions become manipulation tactics rather than change agents. You need a more structured, direct, and often longer-term approach with those populations. Active substance abuse is another area where the model stumbles. Strategic therapy assumes a certain level of cognitive flexibility and willingness to engage with abstract interventions. Acute intoxication or withdrawal doesn't provide that foundation. Stabilization has to come first, usually through medical intervention and motivational frameworks. Family systems that are actively violent or abusive present a different problem entirely. The strategic model's emphasis on homeostasis and circular causality can unintentionally blame the victim. When you frame domestic abuse as an interactional pattern, you risk implying the abused person is contributing to the cycle. That's not just ethically wrong, it's dangerous. Safety planning and trauma-informed approaches take priority here.
Another practical limitation is the therapist dependency problem. Strategic therapy concentrates power in the therapist's directives. For families that have been powerless in other contexts, this can create a new dependency rather than genuine autonomy. The therapist becomes the authority figure who tells them how to live, which replicates the very dynamic the therapy is supposed to disrupt. I've seen cases where families became unable to make decisions without consulting their therapist, which required a deliberate phase-out strategy that most training programs don't cover well. The model also struggles with chronic, multi-generational trauma. Strategic interventions can shift surface behavior in families with deep historical wounds, but the underlying attachment patterns and internalized shame often require deeper structural work. I've watched good strategic therapists hit a wall with families where the identified patient's symptoms were literally the only language available for expressing generational grief. Directives fell flat because the symptom wasn't maintaining a current interaction — it was echoing a history that predated the therapy room.
How to Actually Learn This
The original MRI materials are scattered. Jay Haley's Mstrategies of Psychotherapy and Uncommon Therapy are the closest things to textbooks, though they read more like case collections than manuals. Watzlawick, Weakland, and Fisch's Change is the theoretical backbone — it's short and dense and still the best single volume on the first-order/second-order distinction. There's no single comprehensive curriculum. Most people learn this through apprenticeship or specialized training programs, which is one reason the approach never achieved the visibility of structural or systemic family therapy models. If you're looking to get trained, the MRI itself no longer operates as a training institution. Its legacy lives through people like Cloe Madanes, who adapted the strategic approach for cultural contexts and gender dynamics. The Satir Institute and the Bowlby-centered attachment programs have absorbed some strategic elements but diluted the directiveness. For pure strategic work, you're mostly looking at private practitioners and smaller institutes that charge significant fees for weekend intensives. The practical reality is that strategic family therapy is a skill you develop through supervision, not through reading. The interventions look simple in print. Executing them in a room full of defensive people requires timing, calibration, and the ability to read interactional patterns in real time. A misfire — prescribing a directive that the family interprets as mockery — can shut down engagement for months.
What works in practice is starting small. Pick one interactional pattern in a family you're working with. Map it for two sessions. Identify where the attempted solutions are maintaining the problem. Then try one intervention that breaks the pattern slightly. Watch what happens. Adjust. Don't stack directives. The family system will tell you whether you've hit something real through its response — resistance, compliance, confusion, laughter, silence. Those responses are data. Most beginning therapists ignore them and keep prescribing. The model's greatest strength and its greatest weakness are the same thing: it treats the family as a system of information and interaction. If you believe that changing the information flow changes the behavior, this approach is powerful and efficient. Many problems that drag on for months in other models resolve in six to twelve sessions. If you believe that behavior is rooted in deeper structures — personality, trauma, biology — then strategic interventions feel shallow and potentially harmful. Neither position is wrong. They're just different assumptions about where change lives. I've practiced both. The strategic work produces faster results but higher relapse rates in complex cases. The deeper work produces more durable change but takes considerably longer and requires more emotional tolerance from both therapist and family. The best practitioners I know blend them, which means they've had to abandon the identity politics that dominate training programs. That's usually the hardest part.


