What MST Actually Is, And Where It Gets Messy
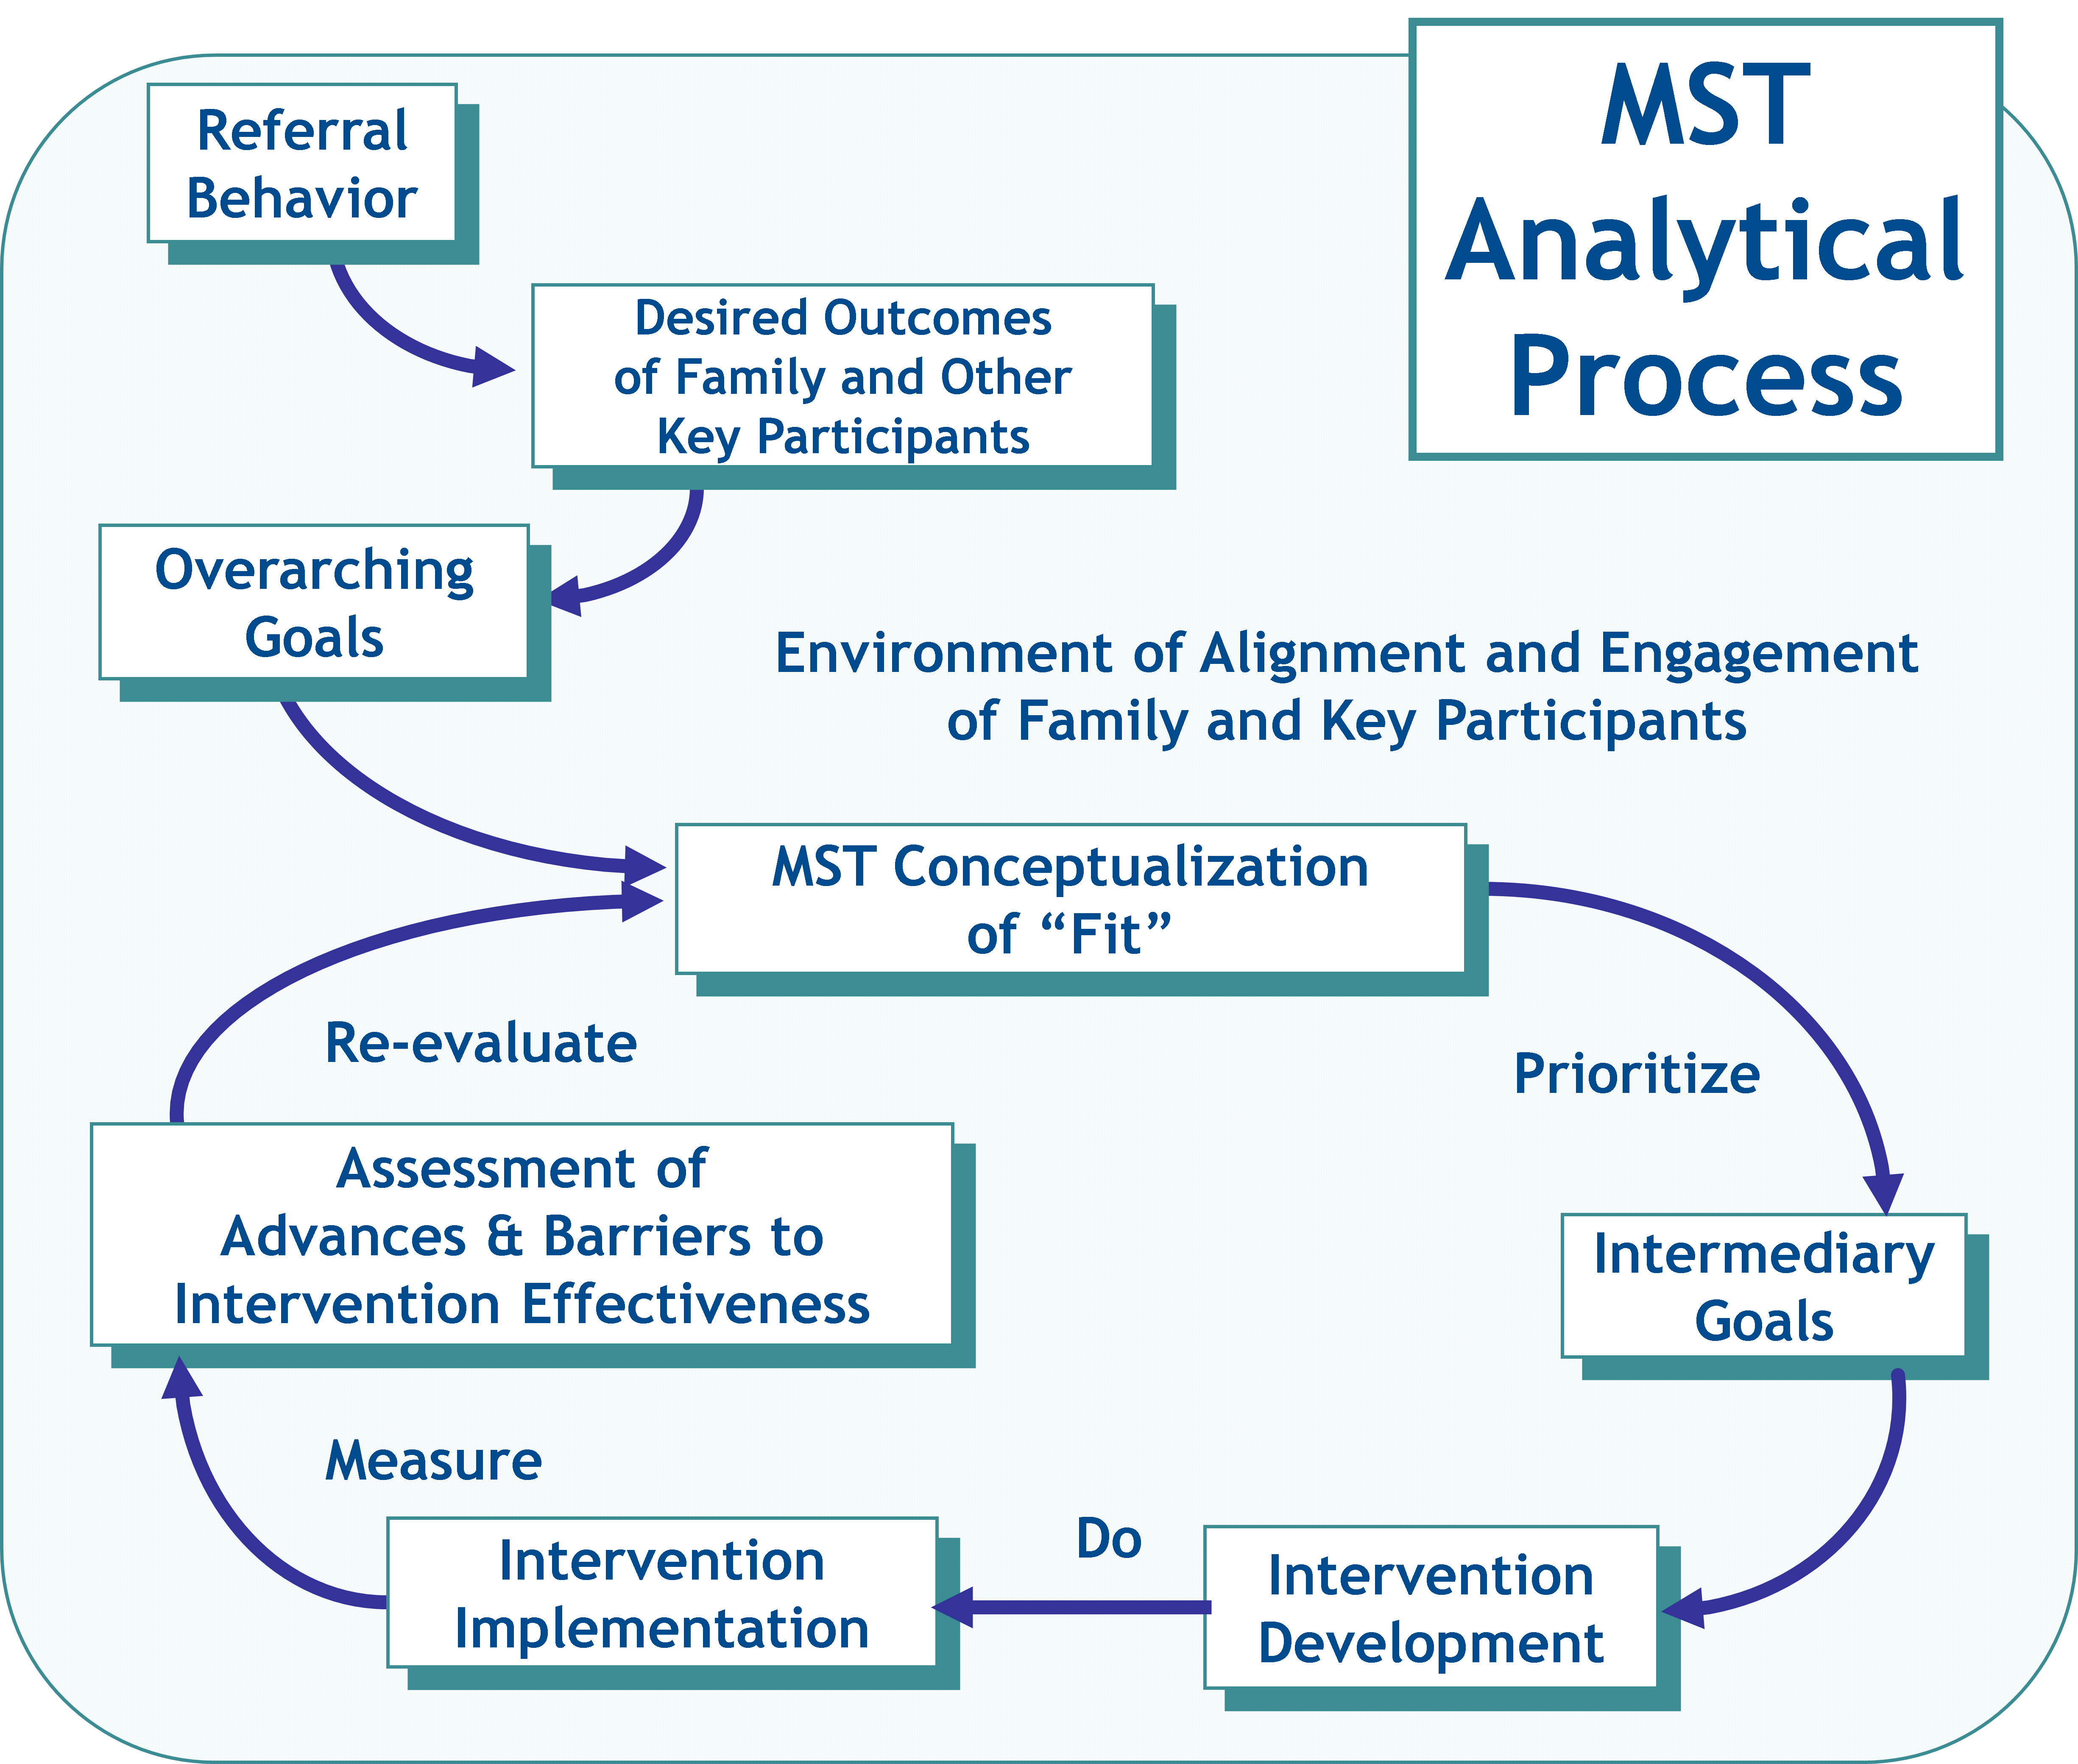
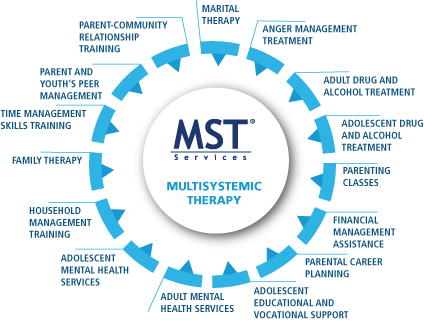
Multisystemic Therapy is a home-based, family-centered treatment model designed primarily for serious juvenile offending and conduct disorder. It wasn't built for kids who skip school and lie occasionally. It was built for kids who are facing felony-level charges, running from probation officers, and setting fires. The therapist comes to your house. They see the kid's bedroom. They sit at the kitchen table and watch how the family actually communicates, not how they say they communicate. That distinction matters more than anything you'll read in a textbook. The therapy targets multiple systems simultaneously: the individual child, the family unit, the peer network, the school, and the broader community. These aren't abstract concepts. In practice, that means a single MST session might involve confronting a father about his inconsistent discipline, calling a school resource officer to renegotiate a suspension that's pushing the kid further out of school, and arranging a community recreation activity that doesn't involve the kid's usual crew. All of this happens on the same day.
Multisystemic Therapy For Conduct Disorder
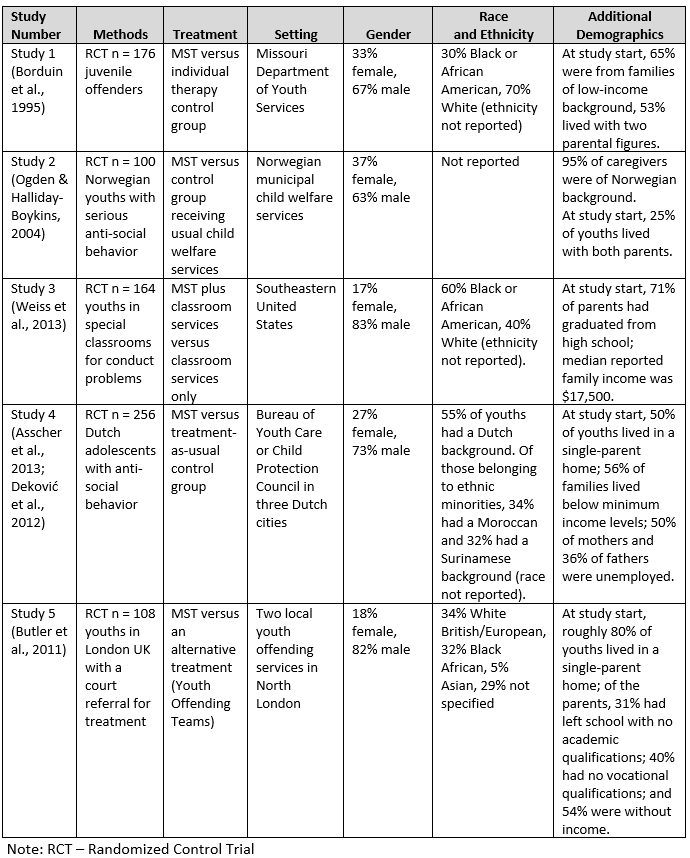
The theoretical foundation comes from Brown and McGoldrick's family systems theory, combined with Henggeler's original framework in the early 1980s. The evidence base is one of the stronger ones in the juvenile justice space. Randomized controlled trials from the 1990s through the 2010s consistently show reduced recidivism, particularly for youth who meet the criteria for Oppositional Defiant Disorder or Conduct Disorder. Some meta-analyses put the recidivism reduction at roughly 25 to 50 percent depending on the study population. Those are significant numbers, but the conditions under which those outcomes appear are specific and often uncomfortable. MST requires therapists to carry a caseload of 4 to 6 families. Full-time availability including evenings and weekends is non-negotiable. The original model expects therapists to be reachable at all hours because crises don't respect 9 to 5 boundaries. If a therapist can't get home to their own family because they're fielding calls at 11 PM on a Tuesday, something's wrong with their boundary management. That's just reality. The intervention structure typically runs 3 to 5 months. Each family receives roughly 60 to 90 hours of direct contact. The intensity is the entire point. Standard outpatient therapy, once a week for an hour, rarely moves the needle on severe conduct problems because the problems exist across every system the child touches, and the family needs support across every system too. One hour a week doesn't touch that.
How It Actually Works In Practice
The initial assessment phase is where most people misunderstand MST. It's not a checklist you fill out and file. It's a three-day intensive evaluation where the therapist observes the family in their natural environment. They note who sits where at the dinner table, who talks over whom, what triggers escalation, whether the parent enforces consequences or just threatens them, and what the kid does when authority figures are absent from the room. That last piece is the most important one. Intervention begins immediately after the assessment. There is no waiting period. The treatment plan is collaborative, meaning the family helps write it, not the other way around. This isn't softness. Kids who present with conduct disorder will reject any plan they didn't help create. The resistance is predictable and usually test-driven. They want to see if you'll fold under pressure. The therapeutic techniques draw heavily from behavioral family therapy, cognitive-behavioral strategies, and solution-focused brief therapy. Parent Management Training is a core component. You're teaching caregivers how to deliver consistent, immediate consequences. Most parents already know this intellectually. They fail at it because of emotional reactivity, inconsistency between caregivers, and exhaustion. The therapist addresses all three in real time.
Get the Full Details
School-based interventions are where MST differs from standard CBT. A typical CBT therapist works with the kid on anger management skills in a clinic room. An MST therapist is in the classroom with the school counselor, negotiating a behavior support plan that the teacher actually implements. They track the kid's behavior data daily. When the data shows a pattern—say, aggression spikes during math class—the therapist adjusts the intervention, not the kid. That shift in locus of change is significant. Peer intervention is the hardest system to influence. The therapist doesn't just tell the kid to find better friends. They arrange structured activities, coordinate with community programs, and work with the family to modify the child's social environment. Sometimes that means removing the kid from their neighborhood altogether during the intervention period. That's a big ask for families and it creates its own set of logistical problems.
A Problem I Actually Faced, And What I Did About It
I worked with a 14-year-old male with a history of arson, burglary, and assault. Standard MST protocol was in place: weekly family sessions, school coordination, community activities. The kid responded well initially. Six weeks in, everything looked solid. Then his biological father, who lived two counties away and had visitation rights, started taking him to a friend's house on weekends. That friend's older cousin was already on parole for gun charges. The kid stopped attending school on Mondays. The family couldn't enforce anything because the father wasn't present during the week and didn't coordinate on weekends. The workaround wasn't theoretical. I called the probation officer that same morning and requested an emergency court hearing to temporarily restrict weekend unsupervised contact. I also coordinated with the mother to implement a GPS monitoring agreement for the kid during those weekend hours. The father pushed back hard, calling it control rather than accountability. I didn't argue. I presented the probation officer with a single document: the three prior incidents of the kid acquiring weapons through that weekend arrangement. The court granted the restriction. Not permanent. Eight weeks. That was enough to rebuild the treatment momentum. The lesson here is that MST therapists don't have authority over external systems. Schools, courts, probation departments, and extended family members operate independently. You need to build working relationships with them before you need them. That means identifying who holds decision-making power in each system and learning how that person operates. Some probation officers respond to data. Others respond to pressure from supervisors. Knowing the difference saves months of frustration.
Things Beginners Miss
Most people entering this work think the therapeutic alliance with the family is the primary vehicle for change. It's not. The alliance matters, but the mechanism of change is structural. You're changing the environment the child lives in, not the child's internal cognitions. A kid can understand perfectly well that hitting someone is wrong and still do it every day if the environment reinforces it or fails to prevent it. Structure matters more than insight here. Another common failure point is therapist drift. After eight to ten weeks, the novelty wears off and the family starts functioning moderately well. Some therapists loosen their intensity at this point. This is almost always a mistake. The research shows that the highest-risk period for relapse is weeks 10 through 14. The family has adjusted to the presence of outside intervention and may become overconfident. That's when parents stop enforcing rules because things seem under control. The therapist needs to maintain intensity through the final weeks, even when things look good. A third nuance that doesn't get enough attention is the importance of caregiver coalition. If one parent is actively undermining the treatment plan—whether through sabotage, denial, or simply refusing to engage—the outcomes deteriorate significantly. I've seen cases where the non-custodial parent deliberately contradicted the custodial parent's consequences in front of the kid. This isn't rare. It's a structural problem that requires direct intervention, not just noting it in supervision. You address it explicitly in a family session or a separate caregiver meeting. Avoiding the conflict makes it worse.

Where MST Fails
MST is not a universal solution. It fails consistently in several scenarios. Families with active substance abuse disorders in the primary caregivers often can't engage sufficiently with the treatment. The kid's behavior becomes secondary to household chaos. You can work on the conduct issues while substance abuse is unaddressed, but the outcomes are dramatically weaker. In these cases, integrated treatment that addresses substance use concurrently produces better results. Sometimes that means family therapy focused on addiction, sometimes that means referring the caregiver to a substance abuse program before continuing MST. Severe parental psychopathology is another limiting factor. A caregiver with active untreated bipolar disorder, severe borderline personality pathology, or ongoing domestic violence creates an environment where consistent discipline is structurally impossible. MST assumes a baseline of caregiver capacity. When that baseline isn't there, the model strains. You either work with the caregiver on stabilization first or you escalate to alternative arrangements like kinship care or residential placement while continuing targeted family work. The model also has a demographic blind spot. The original research samples were predominantly African American males from urban environments. More recent adaptations have expanded the population base, but the core intervention wasn't designed for rural families with limited community resources, or for girls with conduct disorder who present differently—more relational aggression, more running away, less physical violence. I've seen MST applied to girls with conduct disorder and it works, but the intervention needs modification. The peer network work for girls looks different. The school coordination piece often involves different types of conflicts. Don't just paste the male protocol onto a female presentation and expect identical outcomes.
Cost is a practical limitation. MST is expensive. The original model costs roughly $6,000 to $12,000 per family depending on intensity and duration. Many public systems can't sustain it. When funding cuts hit, the first thing to go is the home-based model, and families get shuffled into office-based group therapy that has far less evidence. That's a systems problem, not a treatment problem, but it affects who actually gets access to the model.
Alternatives When MST Isn't Available
Functional Family Therapy is the closest evidence-based alternative. It's also home-based or clinic-based, shorter in duration—usually 12 to 16 weeks—and targets the same population. The evidence base is solid though not quite as extensive as MST's. FFT has a stronger emphasis on motivational interviewing elements and adolescent individuation within the family system. Multi-Systemic Therapy Plus adds substance abuse treatment components to the standard model. If the family has both conduct disorder and substance use issues, the plus version is the appropriate choice. Standard MST without the substance focus tends to produce partial or temporary gains in co-occurring cases. For families who simply can't access any home-based model, parent-child interaction therapy has decent evidence for younger children in the conduct disorder range. It's more structured, more directive, and typically runs longer. It's less comprehensive than MST in terms of school and community coordination, but it's something.
When the conduct problems are severe and the family system is too unstable for any outpatient model, residential treatment or therapeutic foster care becomes necessary. These aren't failures of the family. They're acknowledgments that the current environment can't support behavioral change, and the child needs a structured setting while the family works toward stability. Returning home after residential treatment without ongoing MST or a similar model dramatically increases recidivism. The transition back into the home environment is where most programs fall apart.
What To Look For In a Provider
Not every clinic offering MST delivers it properly. The model has fidelity measures—specific protocols and supervision requirements that genuine MST programs must maintain. Ask whether the provider is empirically validated through the Multi-Systemic Therapy International organization or their local equivalent. Fidelity scores matter. Programs with low fidelity scores produce outcomes closer to standard outpatient therapy than to the MST research base. The therapist-to-family ratio is another indicator. If a therapist is carrying more than 6 families, the model is being diluted. That doesn't mean the therapist is incompetent. It means the organizational structure can't support the intensity the model requires. Accept that reality and adjust expectations accordingly. Supervision structure is the third thing to verify. MST requires weekly individual supervision and monthly team supervision. If the program can't produce a supervision schedule, walk away. Supervision isn't paperwork. It's where therapists process the intense family dynamics that arise in home-based work. Without it, therapist burnout and treatment drift become inevitable within three to four months.
There's no universal download or software package for this therapy. It's a manualized clinical model requiring trained therapists. If someone is selling you a workbook or an online course that claims to teach MST, they're not selling you MST. They're selling you a simplified approximation that won't work for the populations the model was designed for. Be careful about what you accept as legitimate training. The research literature is accessible through journals like the Journal of Consulting and Clinical Psychology and the Journal of the American Academy of Child and Adolescent Psychiatry. Henggeler's work is the foundational source. More recent reviews appear in Cochrane and Campbell Collaboration databases. The evidence quality is generally high for MST compared to most juvenile justice interventions, but it's not perfect. The field has been pushing toward adapting the model for younger children, for girls, and for families with complex trauma histories. Those adaptations are still being evaluated.