How the Muscle Test Scale Actually Works in Practice
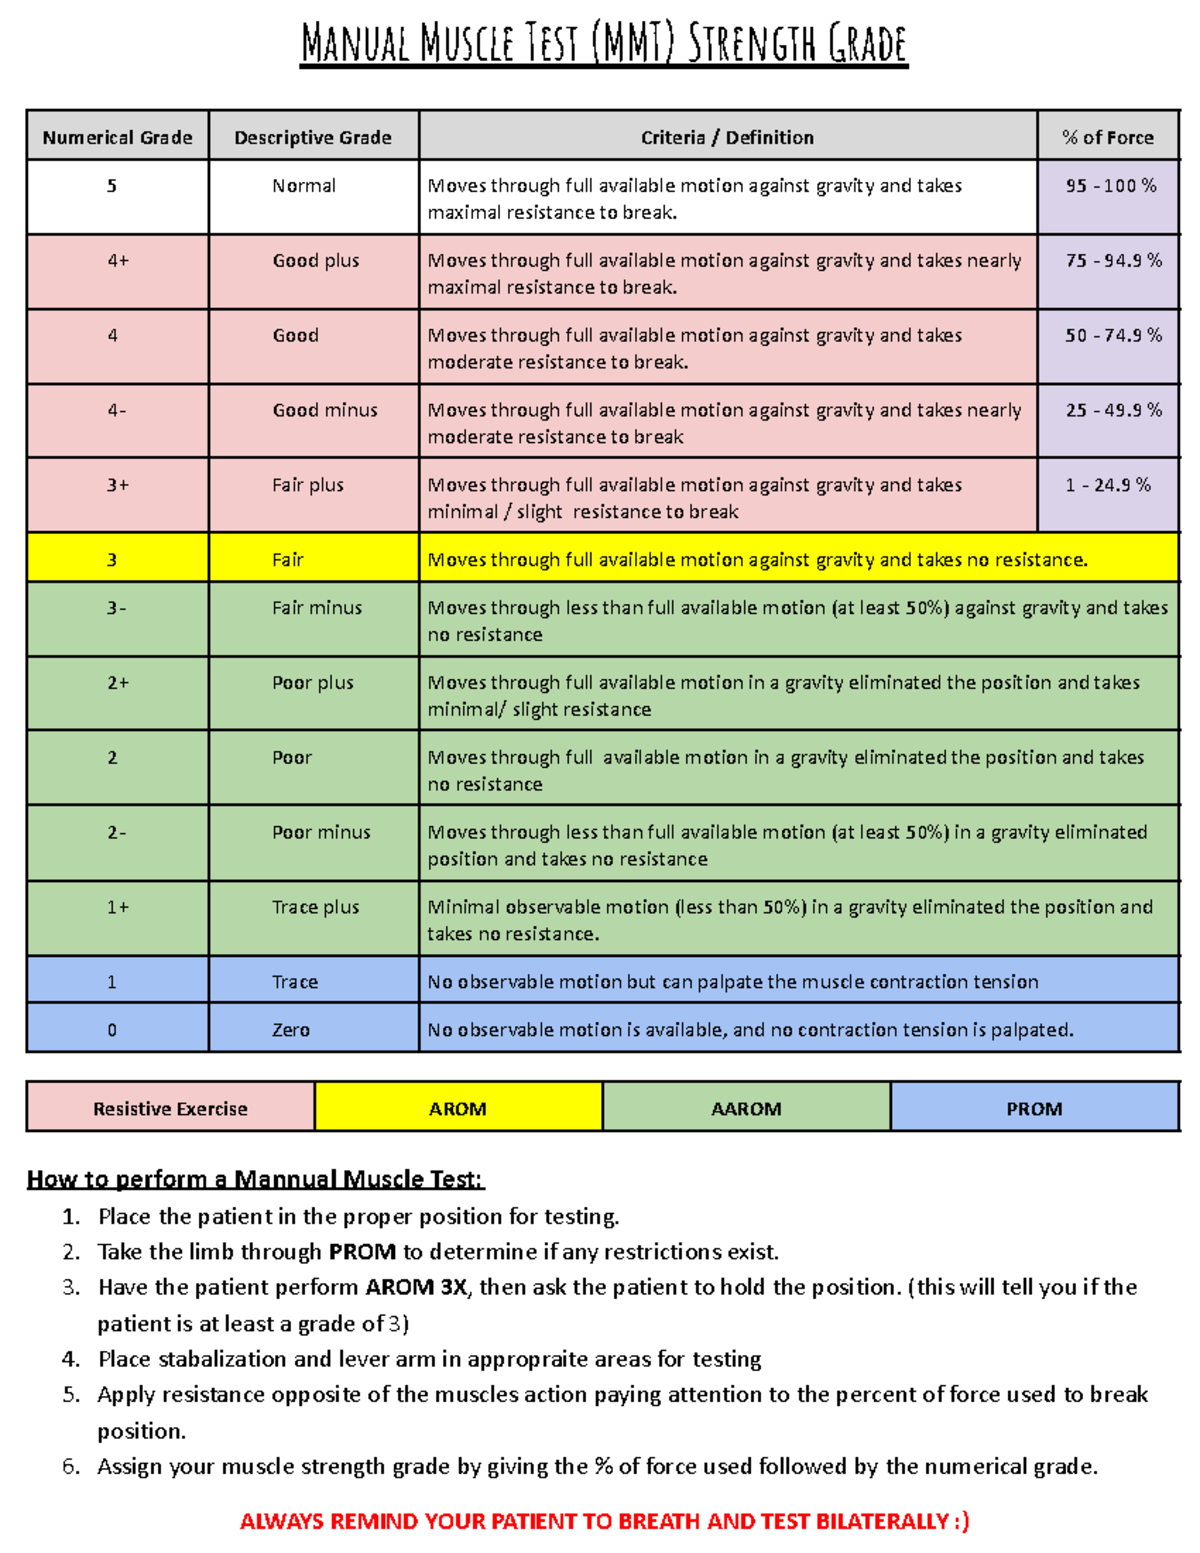
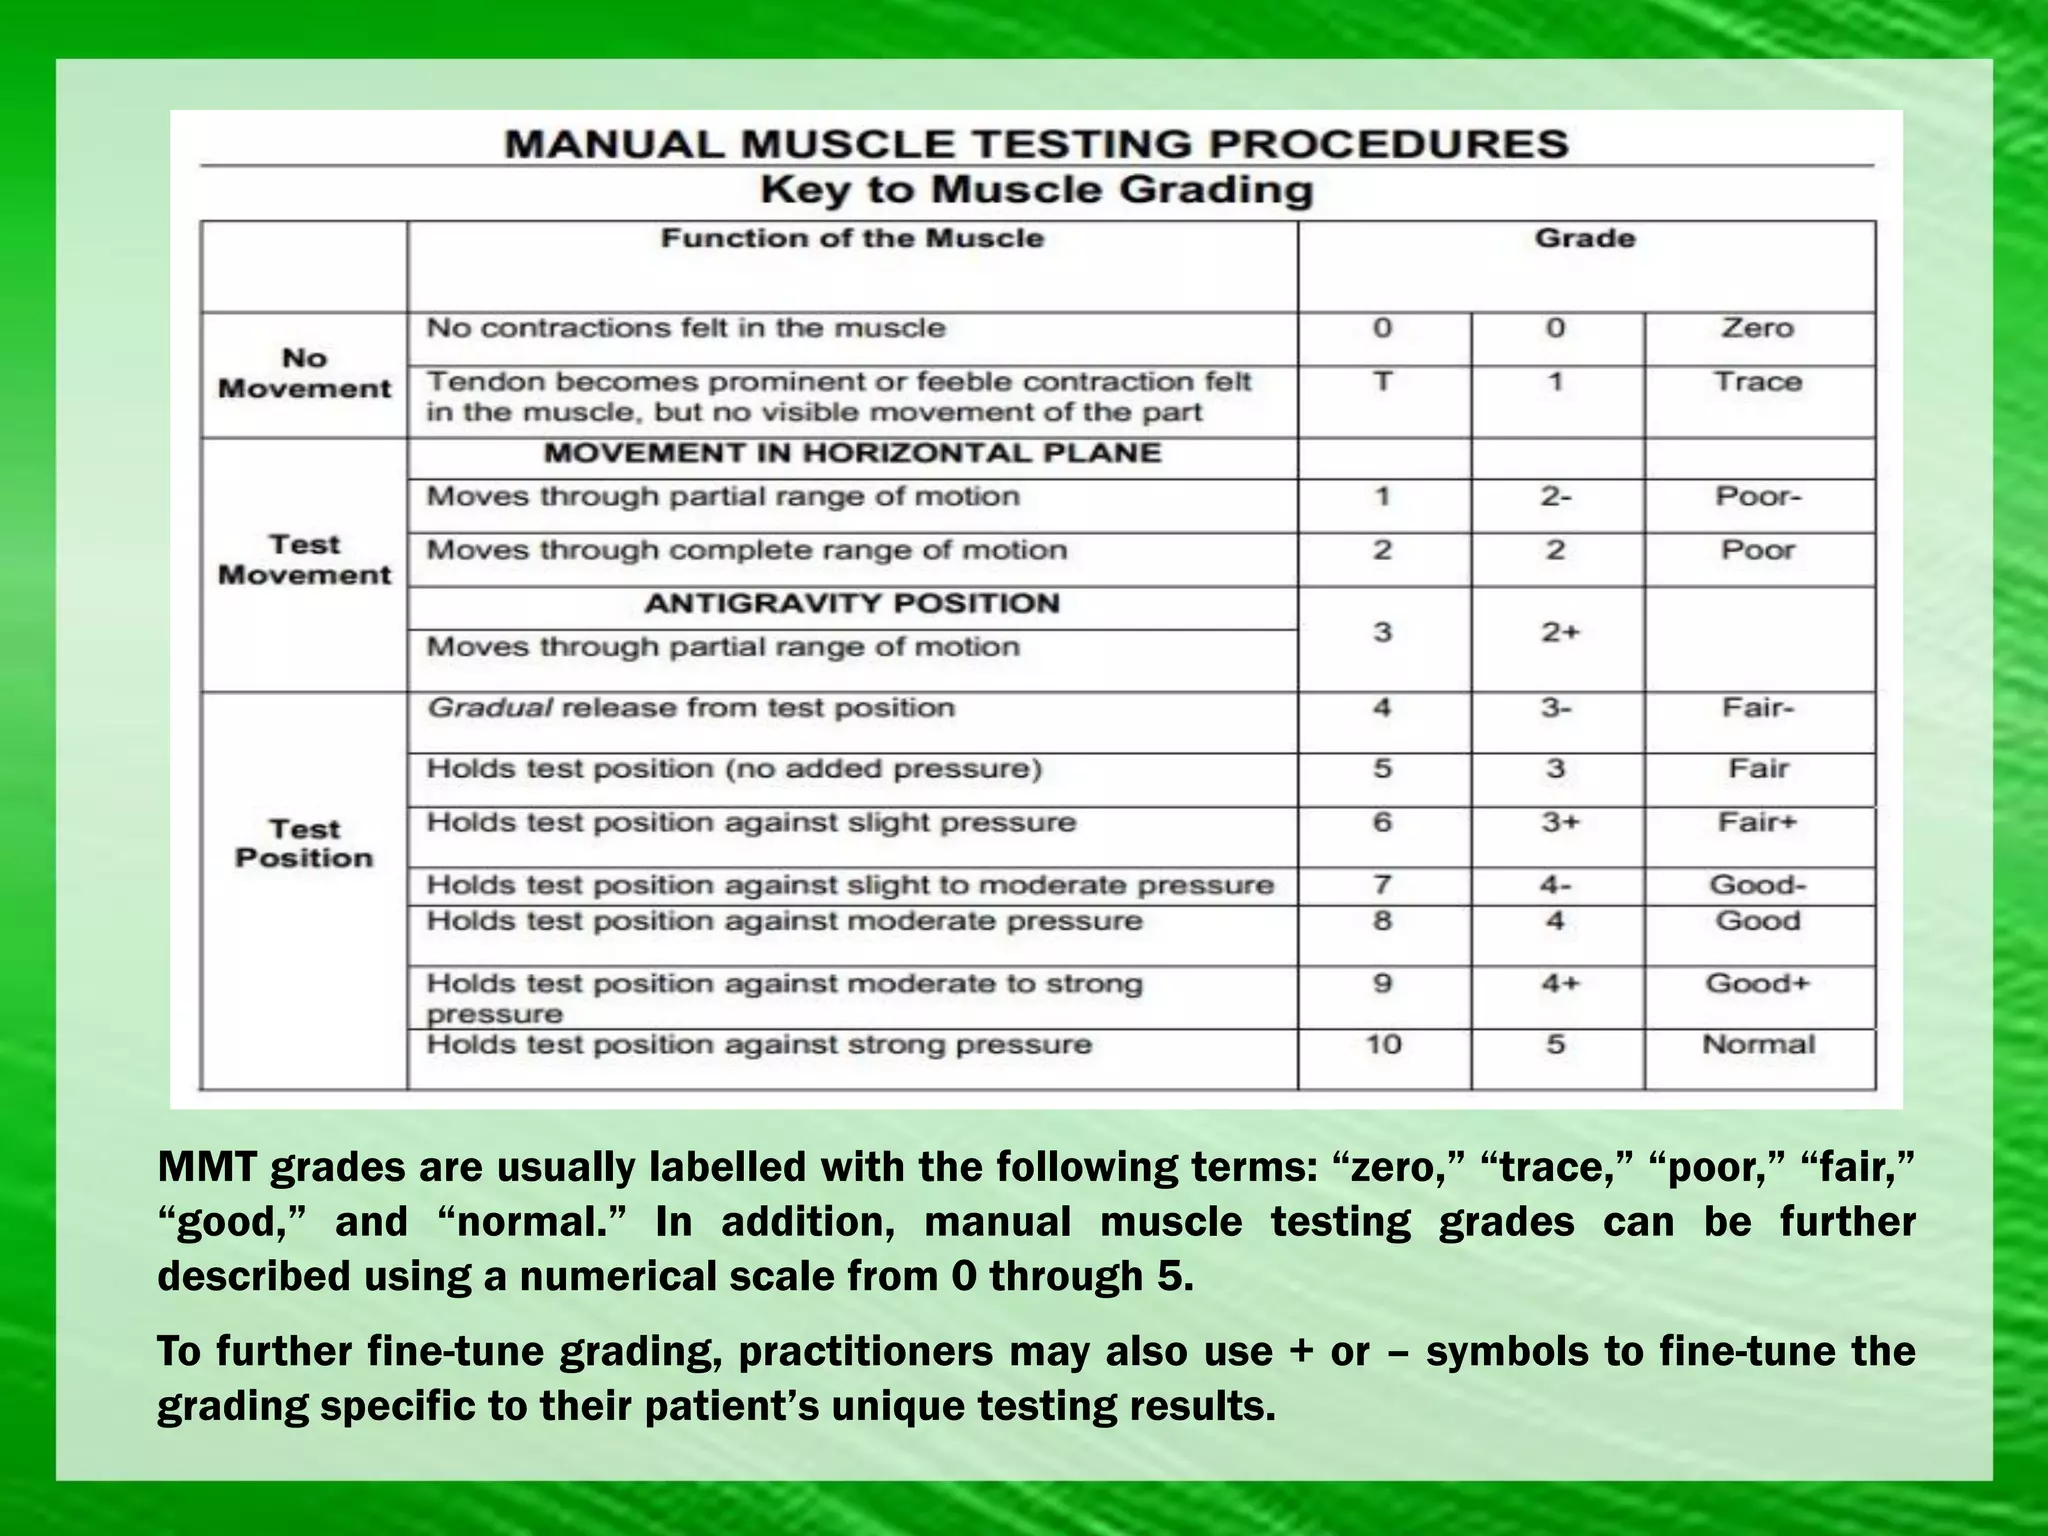
The Manual Muscle Test scale is a 0 through 5 grading system used by physical therapists, occupational therapists, and sports medicine clinicians to document baseline strength and track progress over time. It is simple in concept but messy in execution. I learned this the hard way about eight years ago when I was doing post-op knee rehab and realized two different therapists had graded the same patient as a 3+ and a 4, which created real confusion in the treatment plan. That experience made me pay attention to the nuances that most people gloss over. Here is how the standard Oxford scale works. A 0 means no visible or palpable muscle contraction at all. A 1 is a flicker — you can feel a tiny contraction but there is absolutely no joint movement. A 2 is full range of motion but only in a gravity-eliminated position, meaning the limb is supported so gravity does not factor into the test. A 3 is the ability to move through the full range against gravity but without any added resistance. A 4 is weaker than normal but can tolerate some manual resistance, and this is where most people split hairs between a 4-, 4, and 4+. A 5 is normal strength for that person's body type and age, meaning they can handle full resistance through the complete range. The 3 grade is where things get subjective. The patient has to hold the limb against gravity through the entire range and it has to look clean — no shaking, no substitution patterns, no compensatory movement from adjacent joints. I once watched a therapist call a 3 on a shoulder abduction when the patient was clearly hiking her scapula up toward her ear. That is not a clean 3, it is a 2+ at best because trapezius substitution was carrying the load. You have to watch the whole kinetic chain, not just the prime mover.
How to Actually Perform the Test
Position the patient correctly first. Supine for most upper extremity tests, side-lying for hip abductors, prone for hamstrings and shoulder extension. Stabilize the proximal segment firmly before you ask for movement. The stabilization point matters more than people realize — if the scapula is not stabilized during a deltoid test, the result is unreliable every time. Apply resistance at the distal segment, usually near the joint line of the limb being tested, and increase pressure steadily rather than slamming it on. The resistance should build over about three seconds. If the patient gives out in the first second, you went too hard and you will not get a valid reading. Test the stronger side first. This establishes a reference for what normal feels like for that individual patient. Bilateral comparison catches asymmetries that a single-side test might miss. I keep a pocket notebook and jot down the grade, the position, and any notable observations like pain at a certain angle or a tremor partway through the range. That note about pain matters because pain can artificially limit strength, and confusing pain inhibition with true weakness leads to the wrong diagnosis and the wrong exercise progression.
Pitfalls That Beginners Keep Making
The biggest issue is failing to account for edema, swelling, and recent injury. A swollen ankle makes weight-bearing testing practically impossible and skews lower extremity grades across the board. I once graded a patient's ankle dorsiflexors as a 2 when the real problem was a significant effusion making the joint too uncomfortable to load. Once the swelling came down a week later with compression and elevation, she moved to a solid 4 without any additional intervention. The muscle was fine, the joint was just inflamed. Another common error is using resistance that is completely inappropriate for the patient's condition. Testing a post-stroke patient with spasticity the same way you would test a healthy athlete produces garbage data. Spasticity creates velocity-dependent resistance that mimics strength, and you can easily mistake a hypertonic muscle for a 4 or 5. I learned to back off on resistance and rely more on observation and functional movement in those cases. Sometimes I just skip the resisted portion entirely and note the grade as fair with poor or good based on range and quality of movement alone. Body habitus is another factor that gets ignored. A larger patient with more adipose tissue around the limb can make manual resistance feel weaker than it actually is because you are working through more soft tissue to reach the muscle. Conversely, a very lean patient makes it easy to feel every tremor and substitution. I adjust my resistance application and grading criteria accordingly, and I always document the patient's build in my notes so the next therapist knows what to expect.
Get the Full Details

When the Muscle Test Scale Fails Completely
There are scenarios where this tool simply does not work. Acute inflammatory conditions, recent fractures, post-surgical restrictions, and neurological conditions with abnormal tone all compromise validity. In those cases, the scale gives you numbers that look reasonable but mean nothing clinically. I have seen therapists graph out improvement from a 2 to a 3 and present it as progress when really the patient just stopped guarding due to pain medication. That is not strength gain, that is altered perception. For patients in those situations, I switch to dynamometry when available. A hand-held dynamometer gives you objective force readings in Newtons or kilograms-force and removes the subjective element of your own manual resistance. It takes about two minutes per muscle group and provides data that holds up better across different evaluators. If dynamometry is not an option, functional tests like timed sit-to-stand, grip duration, or single-leg heel raises provide more meaningful information than a forced MMT grade in compromised patients. The scale itself is not going anywhere, but treating it as gospel without understanding its limitations is how you end up with treatment plans built on shaky foundations. Grade carefully, document honestly, and know when to put the scale down and use something else.