How to Actually Test Plantar Flexion Without Getting Confused
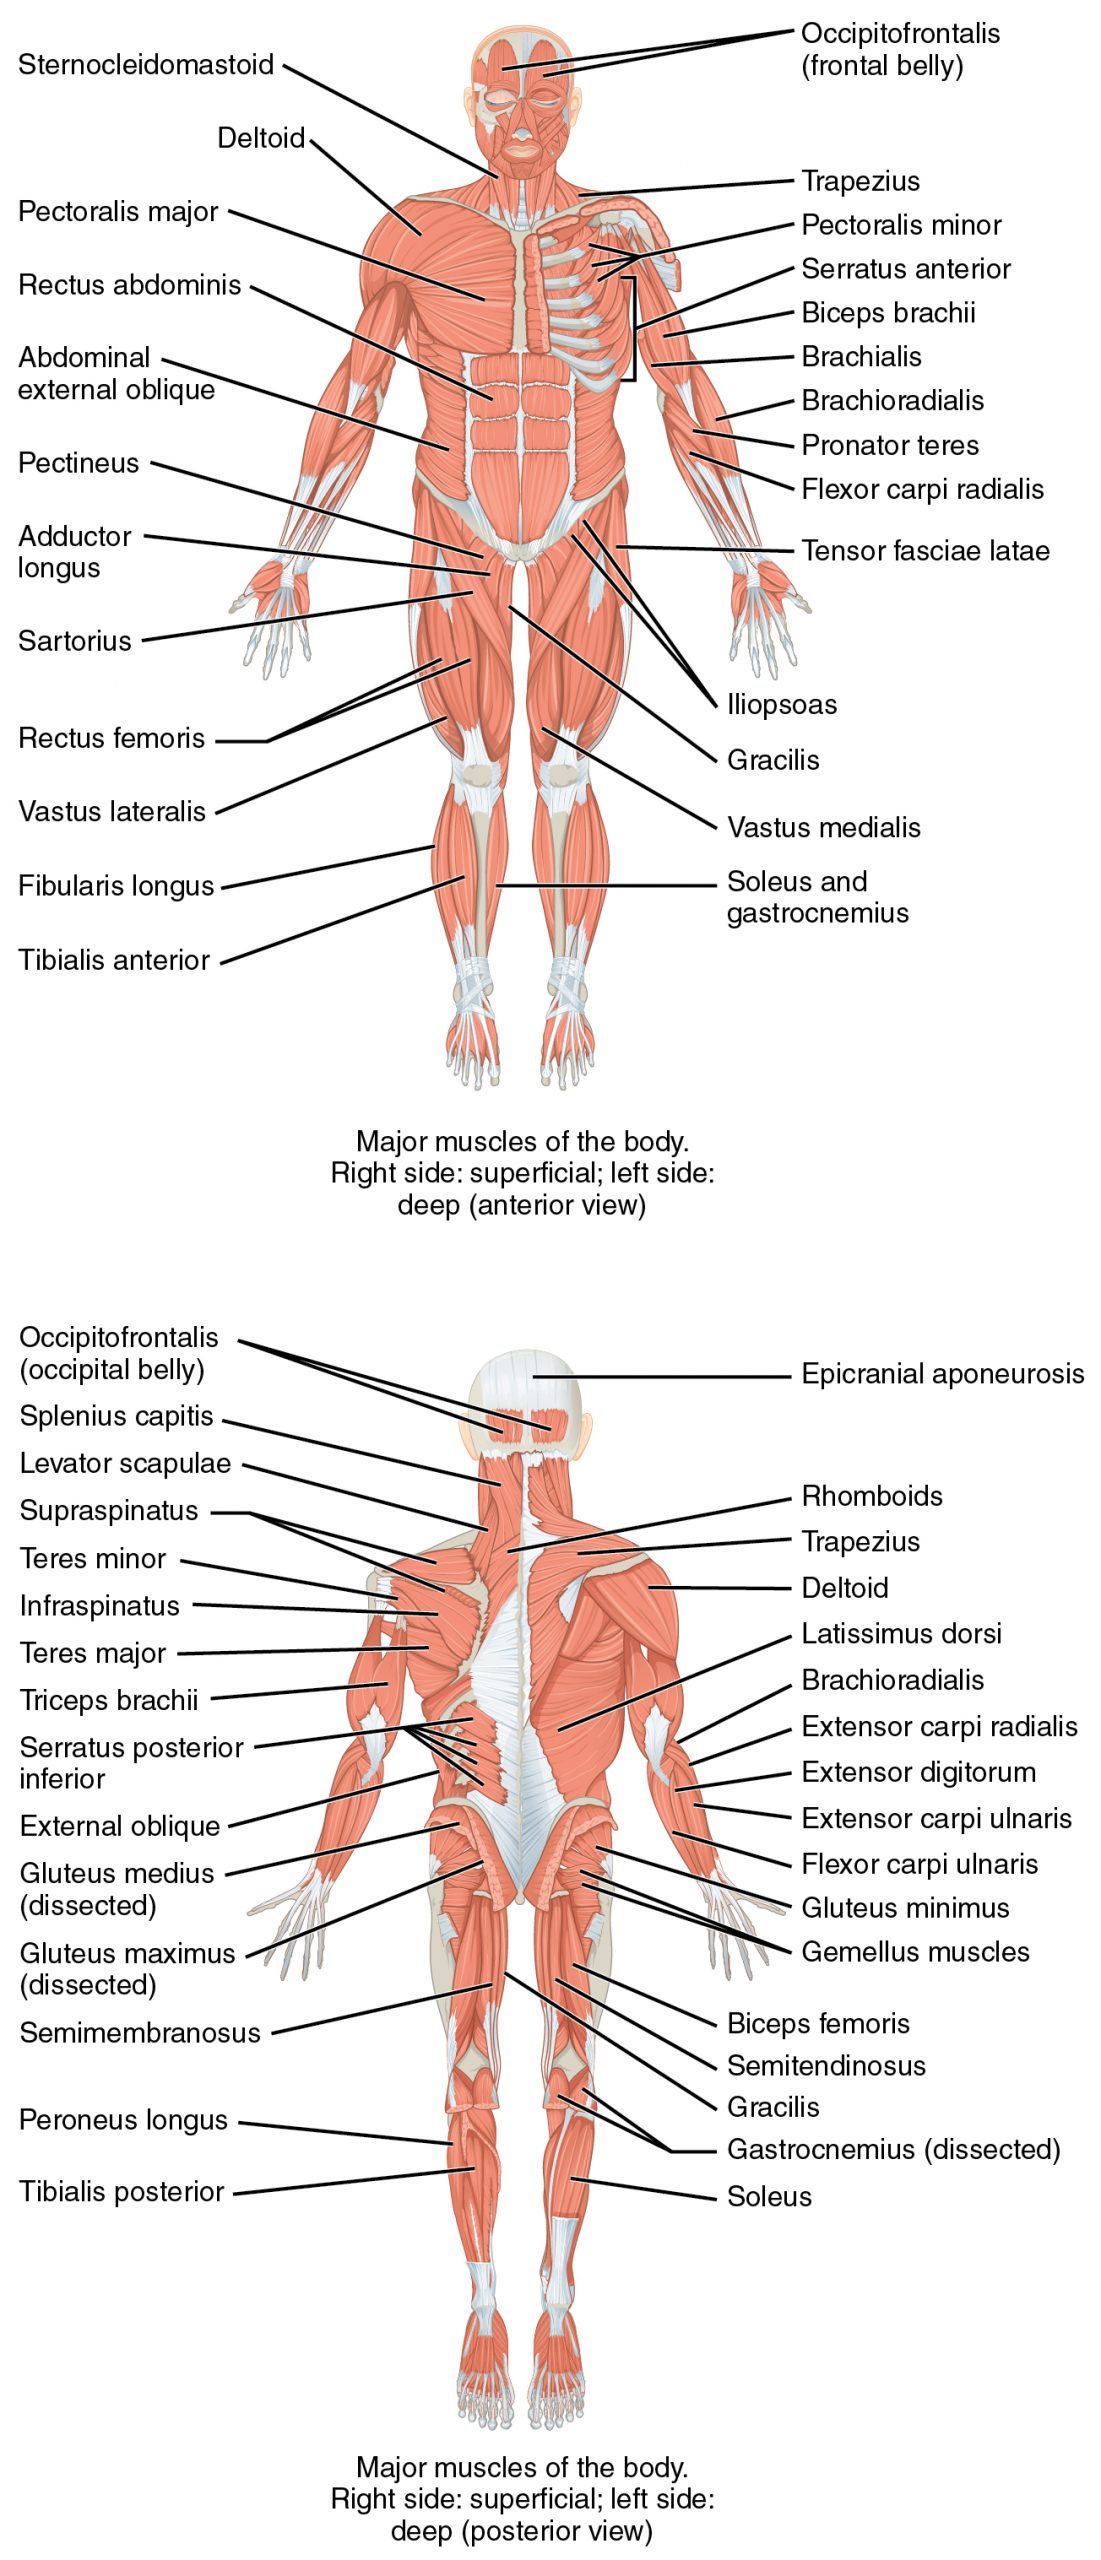
Most people learn the basics of lower extremity muscle testing in school and then never really understand what they're measuring. The gastrocnemius and soleus get lumped together as "the calf," but they behave completely differently under load, and if you're only testing one position, you're missing half the picture. I spent years doing rehab work where we'd miss soleus weakness because the standard seated test looks too much like normal unless you're paying attention to subtle changes in end-feel. Here is how I actually approach this. The patient needs to be positioned to isolate each muscle properly. For the gastrocnemius, the knee must be extended. The gastrocnemius crosses both the knee and the ankle joint, so a bent knee puts it at a mechanical disadvantage and removes it from the equation. The soleus, on the other hand, only crosses the ankle, which means knee flexion isolates it cleanly.
Muscle Testing Ankle Plantar Flexion
The standard prone technique for gastrocnemius starts with the patient lying face down on a plinth. The knee is fully extended. You stand at the side of the table, place your hand under the patient's heel, and apply a firm downward resistance as the patient pushes the foot toward the floor. That's plantar flexion. The patient should be able to hold against your resistance for about five seconds without giving way. Anything less, and you're looking at a deficit worth tracking. For soleus testing, the position changes. The patient sits on the edge of the table with the knee flexed at roughly 90 degrees. Your stabilizing hand goes on the distal anterior tibia to prevent the knee from extending under load. The test resistance goes against the plantar surface of the foot, pushing down. It feels different than the prone test. The torque is lower, the muscle is shorter at rest, and a weak soleus shows up faster because you can't compensate with hip extension or lumbar extension the way you can in the prone position. I keep a simple grading scale posted in my notes. Zero is no visible contraction. One is a flicker, something barely detectable. Two is full range of motion with no resistance. Three is full range against gravity alone. Four is partial resistance held steadily. Five is normal strength with full resistance. Anything between the numbers gets a plus or minus modifier. Two-plus means they can complete the movement but drift into weakness partway through. Four-minus means they resist but not consistently across the full range.
One thing nobody tells you during training is that bilateral comparison matters more than absolute numbers. A patient might score a solid four on the right and a three on the left, and you'd write it off as normal variance. But if that same patient has had a prior Achilles repair or chronic ankle instability on the left side, that three isn't a minor finding. It's significant. You have to know the baseline for each individual, not just compare against some textbook ideal. I run into this constantly in post-surgical cases where the limb looks fine but the neuromuscular drive hasn't recovered proportionally. Another common mistake is testing speed. Most people rush through the resistance application. Apply the force too quickly and you trigger a stretch reflex that masks true weakness. The patient's muscle fires defensively before you've even established a meaningful resistance challenge. Slow, steady pressure over two to three seconds gives you a much cleaner read. If they can hold against slow constant force, they actually have the strength. If they collapse under it, the weakness is real and not just a timing artifact. There is a specific problem I ran into with ankle plantar flexion testing that almost cost us a surgical decision. A patient came in reporting persistent weakness after an extended period of immobilization for a lateral malleolus fracture. The gastrocnemius tested four-plus bilaterally, which looked fine. The soleus tested three-plus on the injured side versus four on the uninvolved side. On paper, three-plus is serviceable strength. But this patient couldn't single-leg heel raise on the injured side. Not even close. The gap between the soleus grade and functional performance was too wide to ignore. We ordered an ultrasound to check for partial tendon pathology, and sure enough, there was a partial-thickness tear at the myotendinous junction that plain imaging had missed. The muscle testing flagged it as a discrepancy worth investigating further.
Get the Full Details
The workaround for cases like that is adding functional tests alongside the manual assessment. Single-leg heel raise, wall push-off test, and timed calf raise count are all practical measures that don't rely solely on hands-on grading. You can score them, track them over time, and use them to triangulate whether a manual grade is accurate or misleading. I should mention the limitations too because people tend to treat manual muscle testing like it's the gold standard. It isn't. Inter-rater reliability for grades below five is mediocre at best. One therapist might call a three another calls a four-minus, and there's no objective way to resolve that without additional data. The technique is highly dependent on the tester's experience, the patient's ability to cooperate and follow commands, and the specific joint mechanics of the individual being tested. If a patient has severe osteoarthritis in the ankle or a contracture that limits range of motion, the test becomes about pain and mobility more than pure strength. Pain also throws everything off. If a patient guards during the resisted movement, you're not measuring strength, you're measuring pain inhibition. I've seen people who could easily do thirty single-leg heel raises walk in and produce a two on manual testing because the resistance position irritated their achilles insertion. The weakness wasn't there. The pain response was. In those cases, you back off to unresisted range of motion first, assess pain separately, and only then move to resistance testing if the joint is comfortable through the full arc.
For clinical documentation, I recommend recording the position tested, the side, the grade, and whether pain was present. That's it. Three lines of data per test. Don't overcomplicate it. If you need to track progress over time, use the same position and the same resistance technique each session. Consistency matters more than precision when you're monitoring change. If you're looking for a reference sheet to keep at your desk, most university kinesiology departments have freely available printable versions. Search for "manual muscle testing quick reference gastrocnemius soleus" and you'll find clean, no-nonsense charts that show the position, the resistance vector, and the grading criteria. Nothing fancy, just something to keep handy when you're running through a full lower extremity exam and need to stay organized.