How to Read and Record Muscle Testing Scores
Muscle testing scores are a way of quantifying the results of applied kinesiology examinations. The basic system uses a three-point scale: strong, weak, and neutral, though more detailed scoring systems exist for research and clinical documentation. What most people don't understand is that the score itself is far less important than the consistency of the testing conditions. A weak score from an inconsistent baseline means nothing. Here is how I actually do it in practice. The subject stands or sits in a stable position. The examiner applies resistance to an outstretched arm while the subject mentally affirms or denies a stimulus. The resistance should be firm but not violent. You press downward at about two to three kilograms of force. The arm either stays locked or breaks. That's it. But within that binary outcome sits the entire scoring problem.
Muscle Testing Scores Breakdown
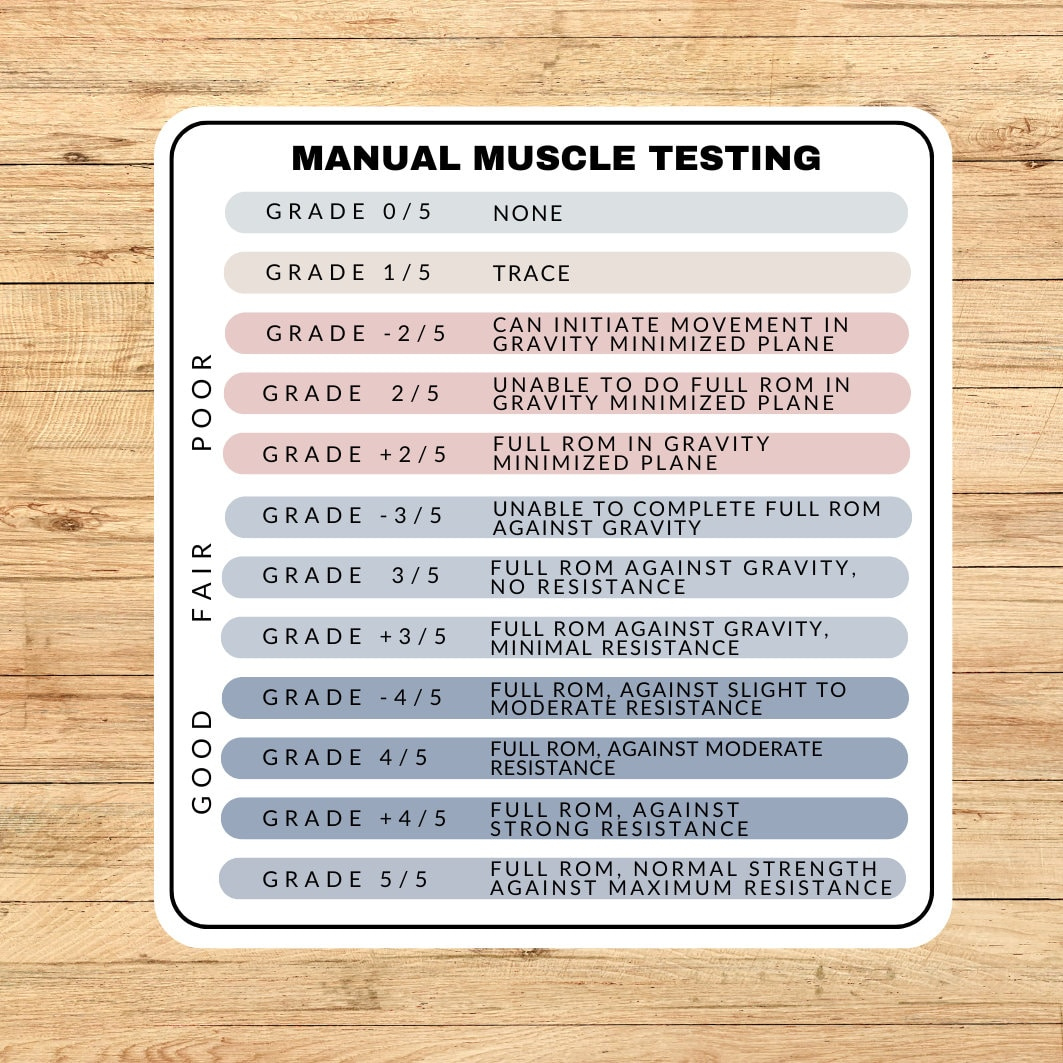
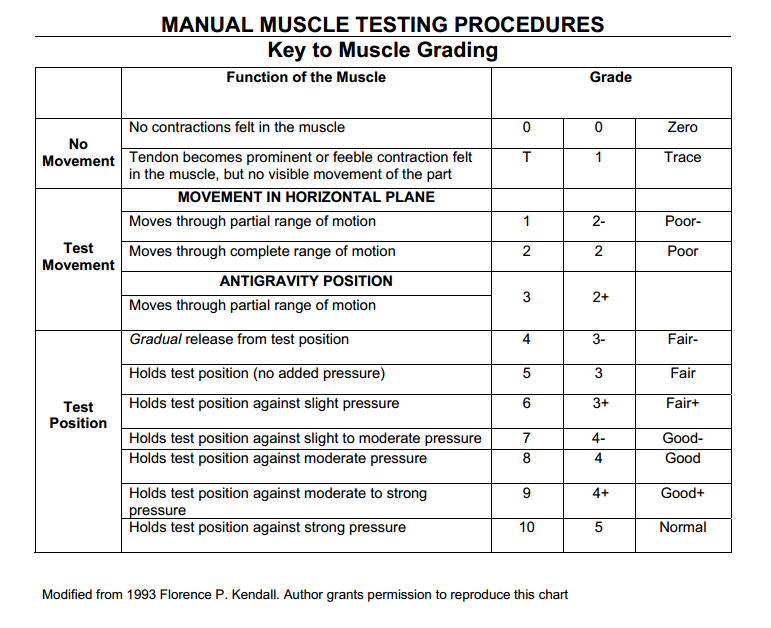
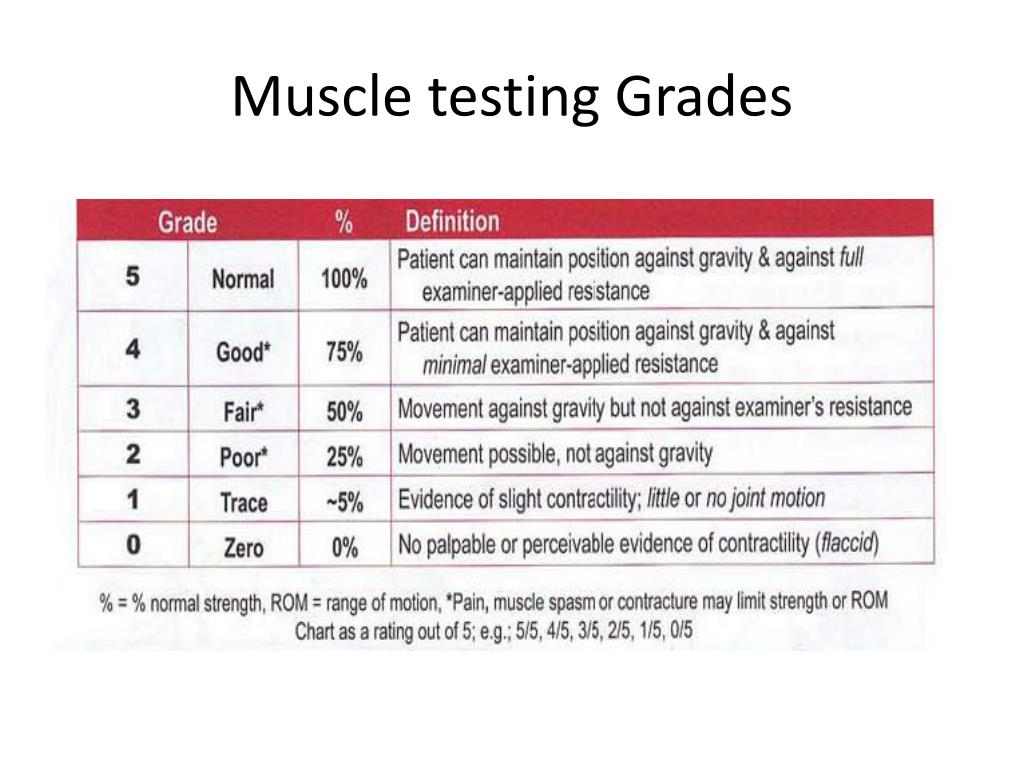
A standard scoring rubric looks like this: Score 3 — Strong: Arm maintains resistance fully. Tissue response is immediate and sustained. Score 2 — Weak: Arm collapses under light pressure. Response may be delayed by half a second or more.
Score 1 — Neutral/Unchanged: No measurable difference from baseline. The tested stimulus produced no neural response. Score 0 — Inconclusive: The subject moved involuntarily, shifted position, or the tester's hand slipped. Retest required. I stopped relying on this simple rubric years ago. The real problem shows up when you're testing someone who has poor proprioception or a naturally low muscle tone. My first serious headache came from a client with mild hypotonia from a previous spinal injury. Every single muscle registered as weak by the standard protocol. Three consecutive sessions. I was about to write the whole nervous system assessment off as a failure until I switched to a paired comparison method instead. I had the subject hold two items — one that was supposedly disruptive and one that was neutral — and I tested which one caused the arm to weaken relative to the other. The hypotonia became a non-issue because I wasn't measuring absolute strength, only differential response. Saved probably forty hours of wasted testing across six months of trying to calibrate.
Get the Full Details
Here is something the textbooks rarely mention about scoring reliability. Most practitioners will tell you that inter-examiner reliability for muscle testing hovers around sixty to seventy percent on blind trials. That number is accurate but misleading if you don't separate skilled examiners from beginners. The difference comes down to pressure consistency and timing. A practiced examiner applies resistance at exactly the right moment in the subject's respiratory cycle. Testing during exhalation tends to produce slightly stronger responses across the board compared to inhalation. I track this by having the subject breathe in through the nose for four counts and testing on the exhale. It adds maybe twelve seconds to each test sequence but improves consistency enough to notice over a full session. The scoring system you choose matters more than you'd think. The original KAS (Kinesiology Applied Scoring) system from the 1980s used a ten-point numeric scale, but it required calibration against a known strong and weak stimulus before every single test. Most people skip that calibration step entirely, which means their five-point scores aren't actually comparable across days or between practitioners. A score of three from one session isn't the same biological event as a score of three from another session unless the calibration baseline was held constant. For anyone building a personal database of muscle test results, I recommend keeping three things in a log: the ambient temperature of the room, the time of day relative to the subject's last meal, and the examiner's dominant hand position. Temperature fluctuations of more than four degrees between sessions can shift baseline readings by one full score point. I've seen it happen. Food intake timing affects blood glucose levels, which directly influences muscle response speed. Testing someone two hours post-meal versus four hours post-meal can flip a borderline weak result into a strong one without any change in the actual stimulus.
Another thing nobody warns you about is the fatigue factor in repeated testing. After about twenty to twenty-five consecutive tests, even a healthy subject shows declining response amplitude. The muscle memory of holding the arm extended causes micro-fatigue that registers as increasingly weak scores. I handle this by grouping tests into sets of twelve with a sixty-second rest period between sets where the subject shakes out the arm. It roughly doubles the time required for a full assessment but prevents the slow drift into false-positive weak scores that ruins later data points. If you want a downloadable scoring template, search for the Original Neuromuscular Test Score Sheet, which is available from several kinesiology education sites. The basic version is free and tracks strong, weak, and neutral responses across multiple muscle groups with date, time, and condition notes. More detailed versions include columns for breathing phase, meal timing, and environmental factors, but those tend to be behind paywalls from kinesiology training programs. There is a legitimate limitation to everything I just described. Muscle testing scores are not diagnostic in the conventional medical sense. They register a neuromuscular response, nothing more. The interpretation of what that response means requires additional clinical correlation and often subjective judgment from the examiner. Automated scoring systems do not exist for this method because the resistance application itself is inherently manual. Anyone selling a device that claims to read and score muscle testing automatically should be treated with extreme skepticism. The variability in human touch is not a bug in this system. It's the fundamental mechanism. The score comes from the interaction between two nervous systems, not from a machine reading a muscle.
That said, when used carefully with consistent methodology, recorded conditions, and awareness of the fatigue and calibration variables, muscle testing scores can provide a repeatable framework for tracking neuromuscular responses over time. The scores themselves are rough approximations at best. The trend lines across repeated sessions are where the actual signal lives.