What Cardiac Muscle Tissue Actually Is
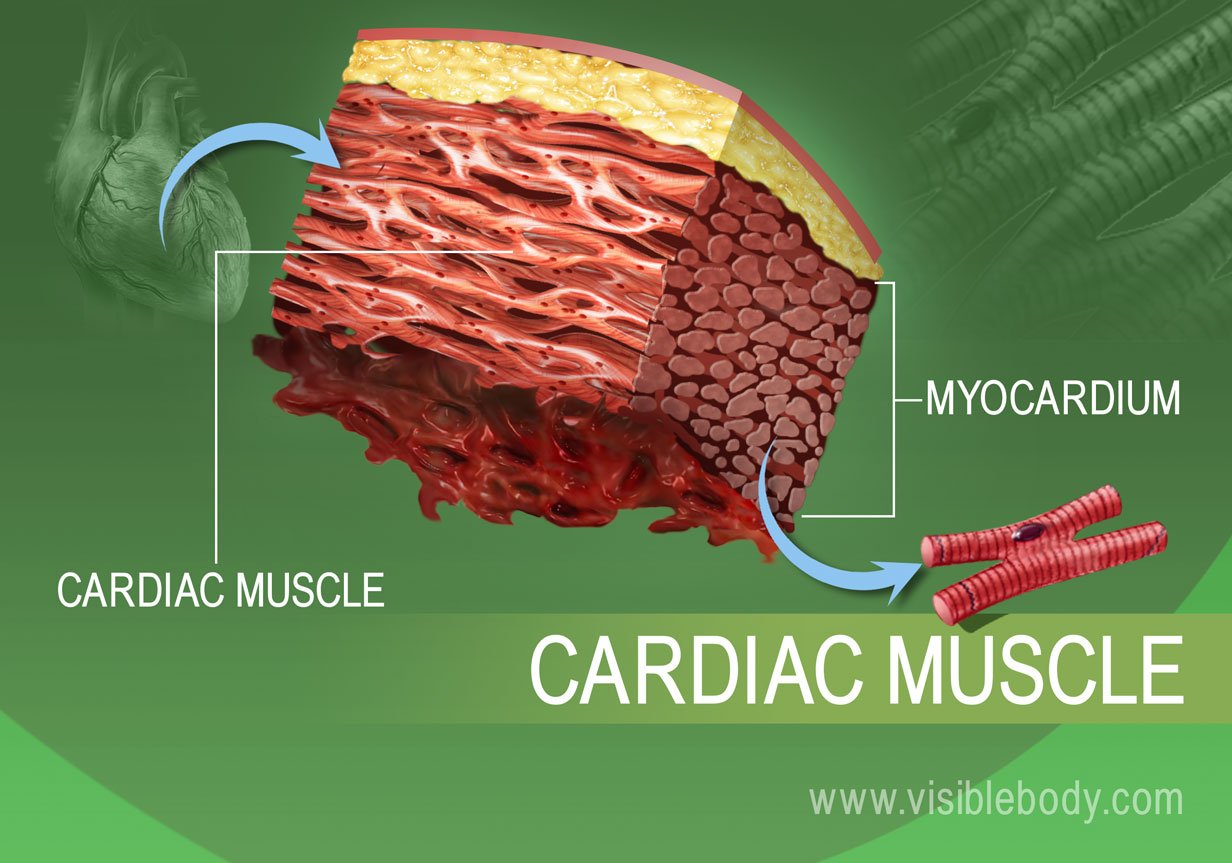
The heart runs on specialized striated muscle that is structurally similar to skeletal muscle but operates under completely different rules. You get this from embryonic lateral plate mesoderm. It forms the myocardium, which sits between the endocardium and the epicardium. The tissue is involuntary, meaning you can not consciously control it the way you control a bicep flex. Individual cardiac muscle cells are called cardiomyocytes. They are typically single-nucleated, though some cells in the adult heart become binucleated as they mature. Each cell branches, interlocking with neighboring cells to form a three-dimensional syncytial network. That branching pattern matters because it determines how force propagates through the ventricular wall during contraction.
Identifying the Muscle Tissue Of The Heart
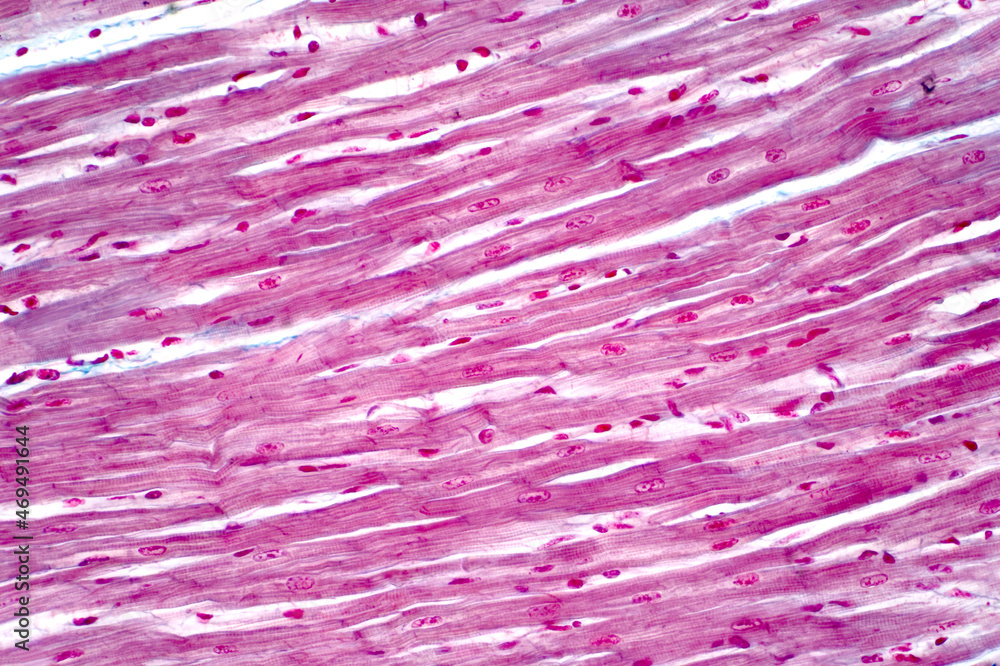
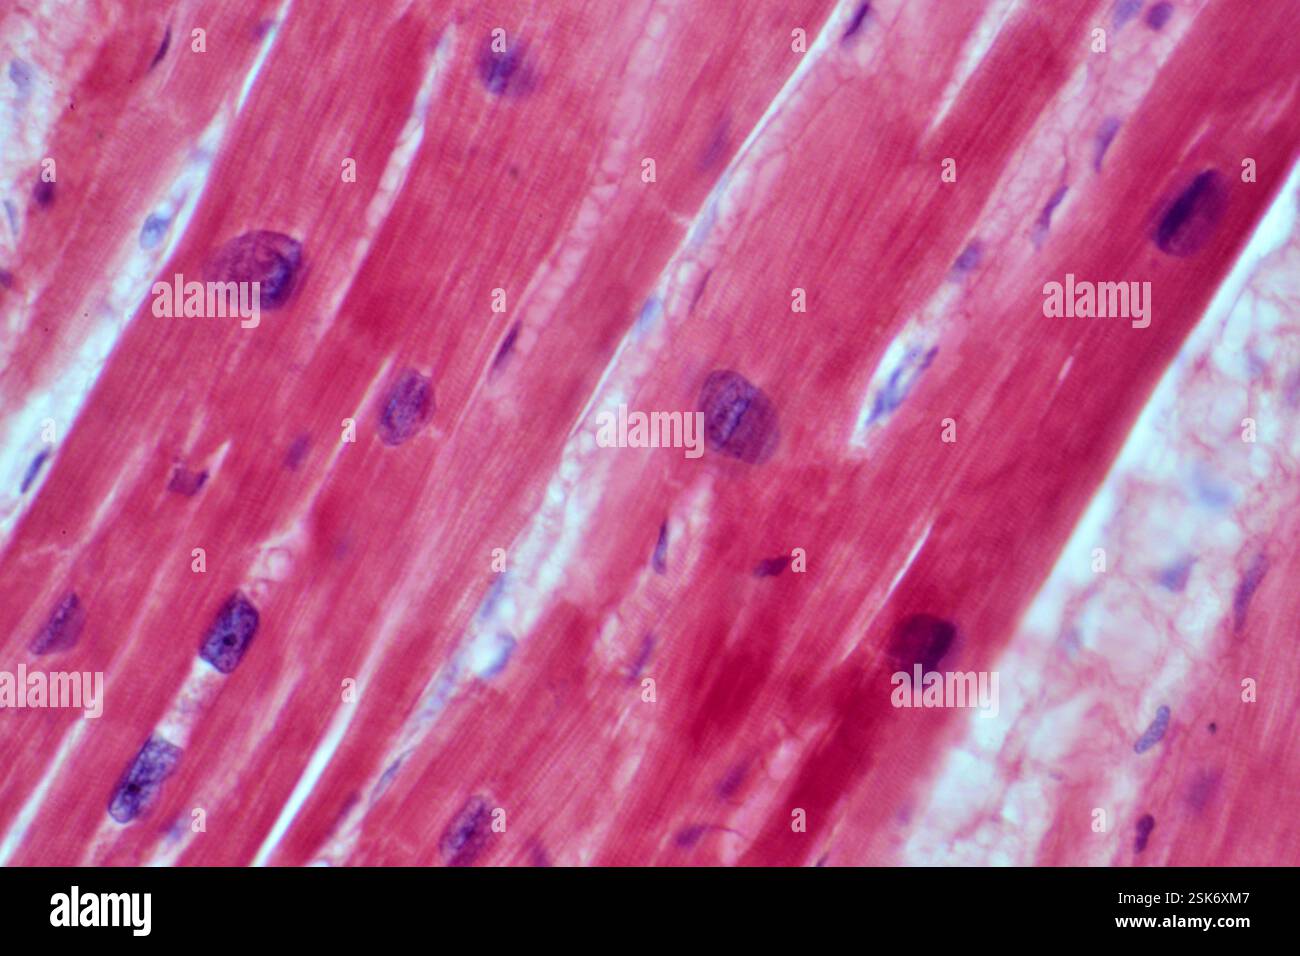
Under a microscope, you tell cardiac muscle apart from skeletal muscle pretty quickly. The fibers are shorter than skeletal myofibers, they branch, and the nuclei sit centrally rather than being pushed to the periphery. The striations come from the same sarcomere arrangement you see in skeletal tissue, but the overall architecture is different. You also look for intercalated discs, which appear as dark, irregular lines running perpendicular to the fiber axis. Those discs contain gap junctions and desmosomes. Gap junctions let ions flow between cells, which is what allows electrical signals to spread rapidly across the myocardium. Desmosomes hold the cells together mechanically so they do not pull apart during each contraction cycle. I spent a lot of time going over histology slides during my degree, and honestly the intercalated discs are the detail people miss most often. Beginners will scan a slide looking for striations and call it skeletal muscle because they forget to check the cell boundaries. Once you start seeing those discs regularly, the tissue is unmistakable.
How It Functions Under Normal Conditions
Cardiac muscle has four functional properties: excitability, conductivity, contractility, and automaticity. Automaticity is the one that sets it apart most clearly. Specialized pacemaker cells in the sinoatrial node generate action potentials without any neural input. The resting membrane potential of these cells is unstable, which means they slowly depolarize on their own until they hit threshold. That is why your heart beats even when you are under general anesthesia and completely disconnected from autonomic nerve signaling. The action potential in ventricular cardiomyocytes looks different from a neuron or skeletal muscle fiber. You get a rapid upstroke from sodium influx, followed by a plateau phase maintained by calcium entry through L-type channels. That plateau is critical. It keeps the cell depolarized for around 200 to 300 milliseconds, which produces a long absolute refractory period. The refractory period prevents tetanus, meaning the heart muscle can not sustain a prolonged contraction the way skeletal muscle can. It must relax between beats, and that relaxation is what allows the chambers to fill with blood. The refractory period also explains why ventricular fibrillation is so dangerous. Instead of contracting in a coordinated sweep, individual bundles of muscle fire randomly because the normal refractory window has been disrupted by abnormal electrical activity.
Get the Full Details

Architecture and the Conduction System
The myocardium is not a uniform slab of muscle. It has a layered arrangement that changes from the endocardium to the epicardium. The subendocardial layer runs longitudinally around the chambers. The midmyocardial layer forms circular sleeves, especially prominent around the atrioventricular junctions. The subepicardial layer runs obliquely, and this oblique arrangement is what allows the heart to twist during systole, wringing out the chambers much like you would squeeze a wet towel. That wringing motion is a major contributor to stroke volume, and it gets lost if you think of the heart as simply a squeezing balloon. I once worked through a case where a patient had apical hypertrophic cardiomyopathy, and the twist mechanics were completely compromised even though the ejection fraction looked fine on echocardiography. Standard metrics missed it because nobody was looking at the rotational component of the contraction. You need feature-tracking MRI or speckle-tracking echocardiography to catch that. That was a genuinely frustrating case because the obvious numbers said everything was normal.
Cellular Structure and the Sarcomere
Inside each cardiomyocyte, the contractile machinery is organized into sarcomeres, just like in skeletal muscle. Actin and myosin filaments slide past each other according to the sliding filament mechanism. Calcium binds to troponin C, moving tropomyosin out of the way, and cross-bridge cycling begins. The source of calcium is different though. In skeletal muscle, calcium comes almost entirely from the sarcoplasmic reticulum. In cardiac muscle, you get a smaller initial influx from the extracellular space through those L-type calcium channels, and that trigger calcium then causes a much larger release from the sarcoplasmic reticulum. This is calcium-induced calcium release, and it is one of those details that matters a lot if you are thinking about how certain drugs affect contractility. Calcium channel blockers like verapamil reduce the trigger influx, which weakens the subsequent sarcoplasmic reticulum release and decreases contractility. That is why they are used cautiously in patients with already reduced ejection fractions. It sounds obvious in retrospect, but I have seen it overlooked in practice more times than I care to admit.
Metabolic Characteristics
Cardiac muscle is metabolically demanding. A resting heart beats roughly 60 to 100 times per minute, and each beat consumes ATP at a high rate. The tissue relies predominantly on aerobic metabolism, oxidizing fatty acids as its primary fuel source under normal conditions. About 60 to 90 percent of the ATP comes from fatty acid beta-oxidation. The rest is split between glucose oxidation, lactate, and ketone bodies depending on metabolic state. The mitochondria occupy about 30 to 35 percent of the cardiomyocyte volume, which is significantly higher than in skeletal muscle. That density reflects the continuous energy demand. If coronary blood flow is reduced, the tissue switches to anaerobic metabolism quickly, and lactate accumulates within minutes. Prolonged ischemia leads to cell death because the ATP deficit prevents ion pumps from maintaining membrane potential, which causes calcium overload and activates degradative enzymes.
Common Misconceptions
People frequently assume cardiac muscle regenerates like liver tissue does. It does not. Adult cardiomyocytes have extremely limited proliferative capacity. The best estimates suggest renewal happens at less than 1 percent per year after age 25, dropping further with advancing age. When heart muscle is lost to infarction, it gets replaced by fibrous scar tissue, not new muscle. That scar does not contract, and it does not conduct electrical signals the same way, which is one reason why arrhythmias are such a common complication after a myocardial infarction. There is also confusion about the term syncytium. True syncytial tissue means cells are physically fused into a single multinucleated mass. Cardiac muscle is a functional syncytium because gap junctions allow the electrical signal to pass freely between cells, but the cells themselves remain individual and separated by intercalated discs. That distinction matters when you are studying how conduction blocks develop or how re-entrant circuits form in diseased tissue.
Pathology Briefly
Dilated cardiomyopathy involves stretching and thinning of the ventricular walls, reducing contractile efficiency. Hypertrophic cardiomyopathy creates abnormal thickening, often asymmetric, which can obstruct outflow tracts and disrupt electrical pathways. Myocarditis, usually inflammatory or infectious in origin, introduces immune cells into the muscle and can cause both acute dysfunction and long-term scarring. Amyloidosis causes protein deposits within the myocardium that stiffen the ventricle and impair diastolic filling, which is a common cause of heart failure with preserved ejection fraction that is frequently underdiagnosed because the primary complaint is just shortness of breath and fatigue. The take-away here is not that you need to memorize every disease category. It is that the structure of the tissue directly determines how it fails. The branching architecture, the gap junctions, the high mitochondrial density, and the limited regenerative capacity all shape the clinical picture. Understanding the tissue itself makes the pathology less arbitrary.