Understanding The Muscles Of Lower Leg
The lower leg compartment system is a pain point for students and clinicians alike. I've seen people mix up peroneus longus with peroneus brevis on exams and real palpation too. The muscles here aren't that complex, but they sit in tight fascial compartments, which makes everything about them functionally tighter than it looks on paper. You're dealing with four main compartments. Anterior, lateral, superficial posterior, and deep posterior. Each has its own nerve supply and arterial source. That matters more than most people realize when something goes wrong.
Muscles Of Lower Leg: The Anterior Compartment
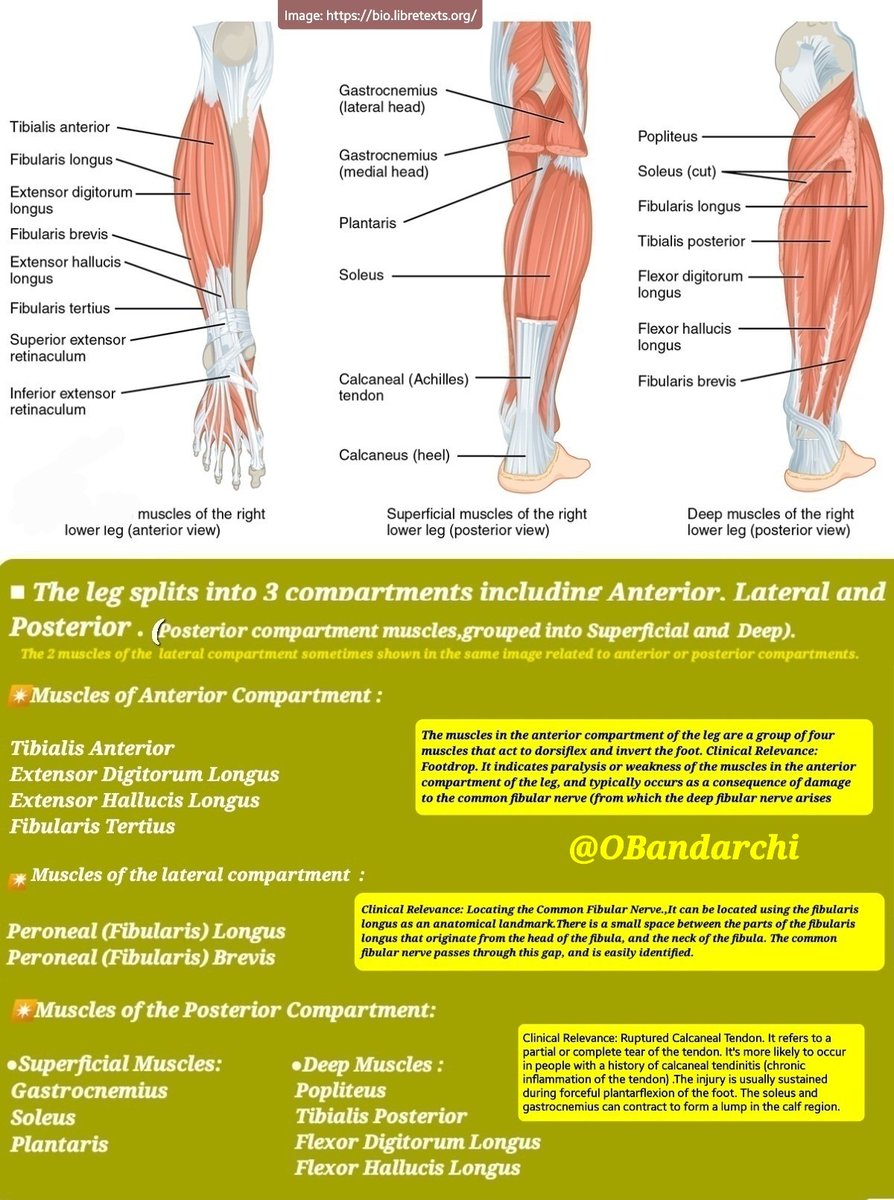
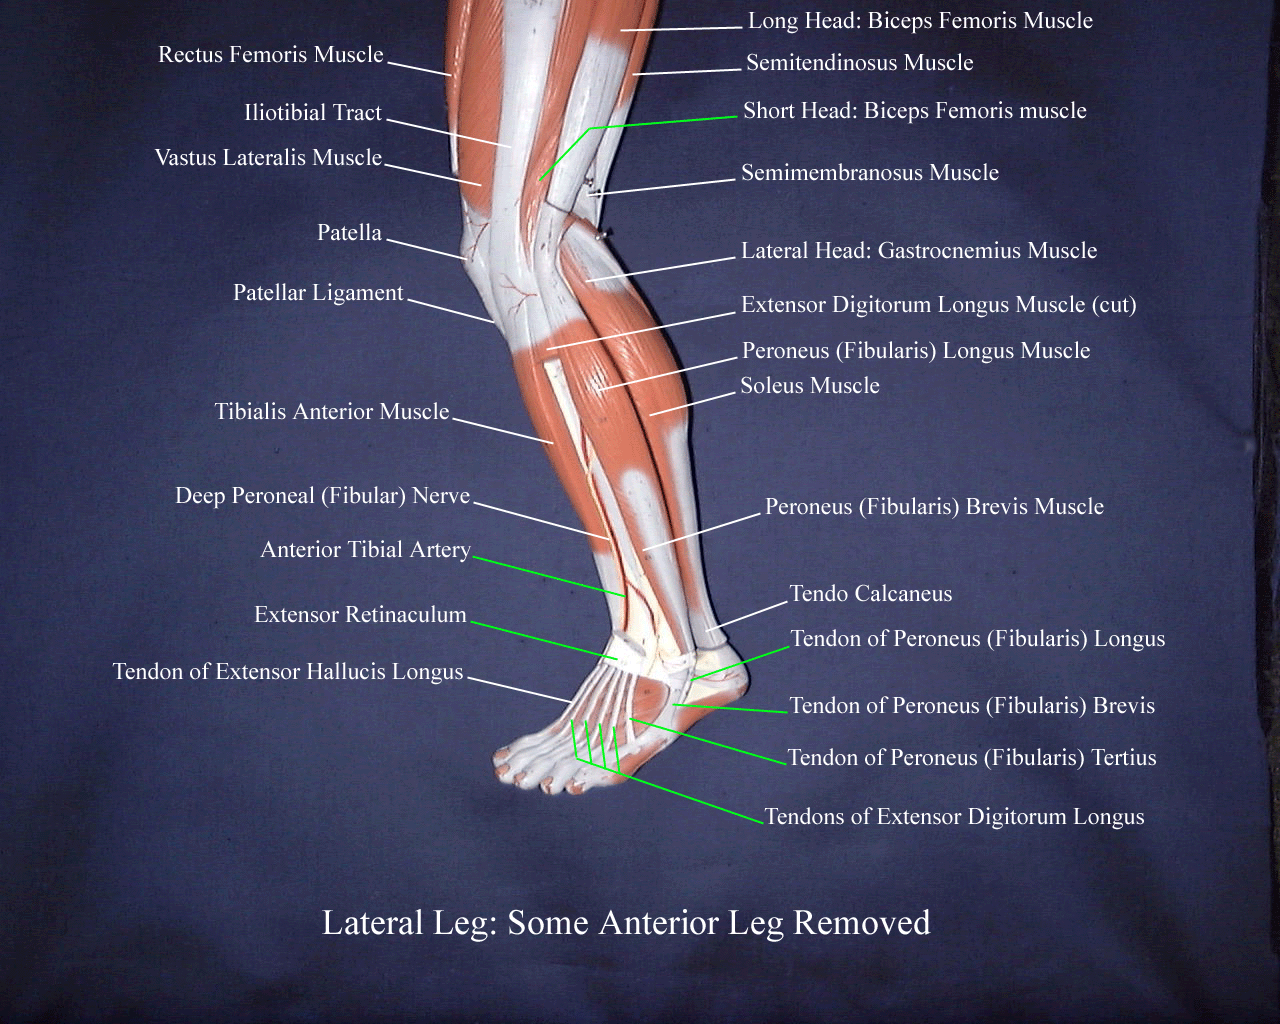
The anterior compartment contains tibialis anterior, extensor digitorum longus, extensor hallucis longus, and peroneus tertius. They're all innervated by the deep peroneal nerve, which comes off the common peroneal nerve at the fibular neck. Blood supply runs through the anterior tibial artery. Tibialis anterior is the big one. It dorsiflexes the foot and inverts it. When you walk, it controls plantarflexion on the eccentric phase so your foot doesn't slap the ground. If someone has foot drop from a L4-L5 radiculopathy or peroneal nerve injury, this muscle is usually the first to show weakness. You can test it by having the person dorsifflex against resistance while seated with the knee extended. Extensor hallucis longus extends the big toe and assists with dorsiflexion. It's clinically useful because isolated weakness here can point to deep peroneal nerve compression at the ankle, not just proximal pathology. Extensor digitorum longus does the same for toes two through five. Peroneus tertius is the smallest and often the most inconsistent — some people don't have it at all. It's not worth stress-testing unless you're doing a full anatomical dissection anyway.
Superficial Posterior Compartment
Gastrocnemius, soleus, and plantaris make up the superficial posterior group. This is the triceps surae. Innervated by the tibial nerve. The gastrocnemius has two heads — medial and lateral — that originate from the femoral condyles. Soleus sits underneath and originates from the posterior tibia and fibula. Plantaris is the tiny vestigial muscle with the long thin tendon that everyone argues about during dissection. The Achilles tendon is where gastrocnemius and soleus converge. Ruptures here are common in people who play weekend sports and haven't been doing calf work regularly. The typical mechanism is a sudden push-off or jumping motion. You hear it, you feel it, you can't push off the affected side anymore. Here's something people miss: gastrocnemius is a knee-dependent plantar flexor. It tightens when the knee is extended and loosens when flexed. Soleus doesn't care about the knee. That means if you're testing calf tightness and the person only has limitation with the knee extended, it's gastrocnemius. If it's limited with the knee both flexed and extended, soleus is involved. Straight knee wall test for gastrocnemius, bent knee for soleus. Both need to be checked.
Get the Full Details

Lateral Compartment
Peroneus longus and peroneus brevis. Common peroneal nerve, superficial branch. These evert the foot and assist with plantar flexion. They run along the fibula and cross behind the lateral malleolus together, held by the superior and inferior peroneal retinacula. Peroneus longus inserts on the medial cuneiform and first metatarsal base. Peroneus brevis goes to the fifth metatarsal base. I had a patient once who kept getting "ankle sprains" on the left side. Turns out they had chronic peroneal tendon subluxation because the retinaculum was loose. Standard sprain treatment did nothing. The workaround was simply checking for tender swelling behind the lateral malleolus during active eversion. If the tendons popped out, that's your diagnosis. MRI confirmed it. Surgical repair fixed it.
Deep Posterior Compartment
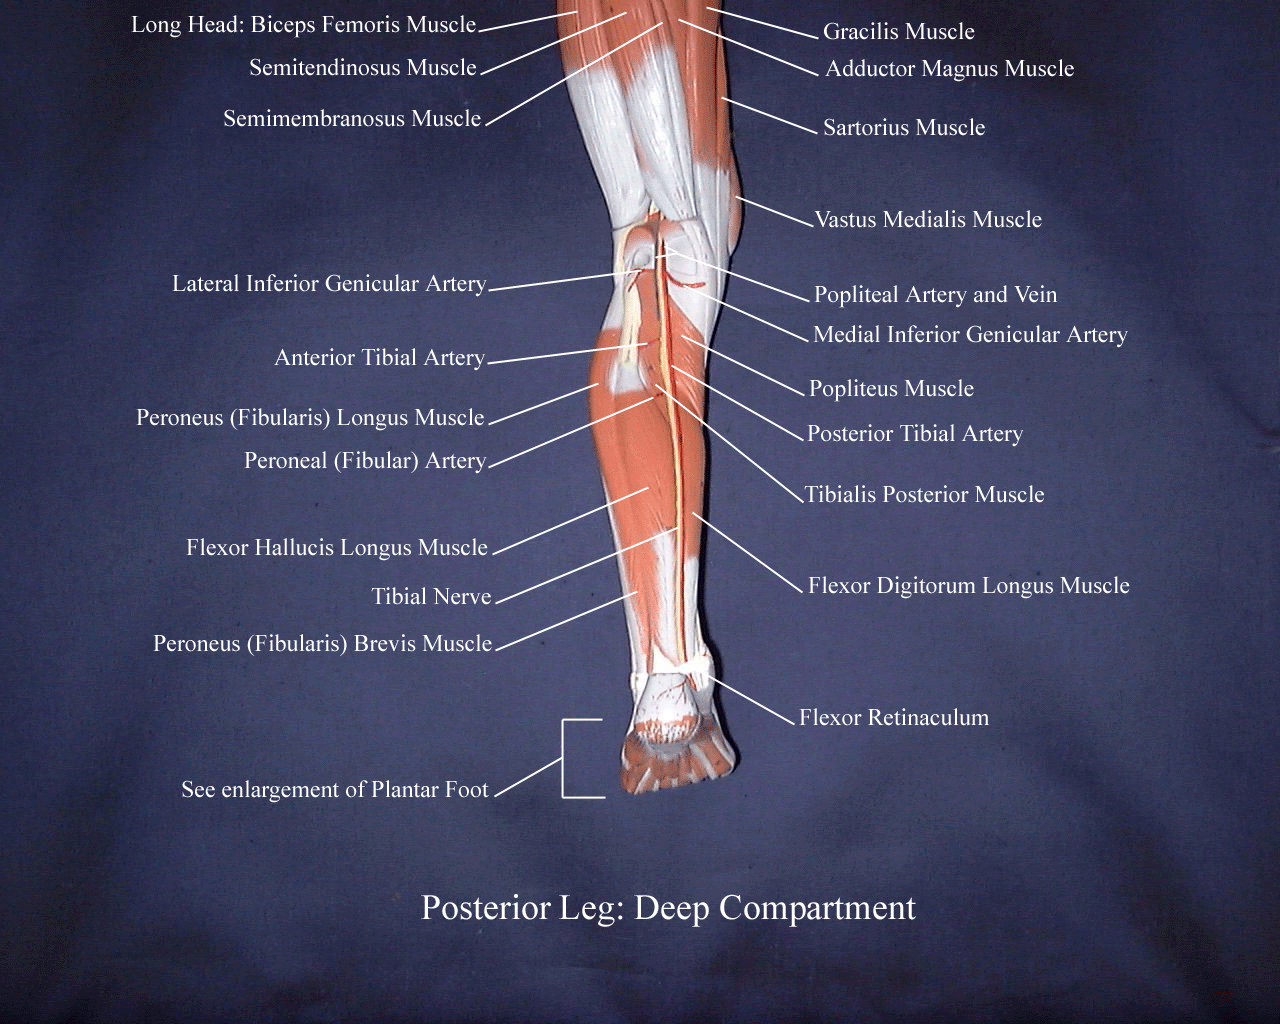
Tibialis posterior, flexor digitorum longus, flexor hallucis longus, and popliteus. Tibial nerve again. These are the intrinsic stabilizers of the arch and the toe flexors. Tibialis posterior is the most clinically significant here. It inverts the foot and supports the medial longitudinal arch. Posterior tibial tendon dysfunction is rampant in middle-aged women and people with rheumatoid arthritis. It progresses slowly — flat foot develops over years, not days. Early stage just means posterior ankle pain and weakness on single-leg heel raise. Late stage means the foot is already pronated and rigid. By then surgery is usually the only option. Flexor hallucis longus runs behind the medial malleolus alongside tibialis posterior and flexor digitorum longus. That's the tarsal tunnel. All three tendons plus the posterior tibial artery and tibial nerve pass through here. Compression causes burning pain, tingling, and numbness in the sole. I've had patients misdiagnosed with plantar fasciitis for months when it was actually tarsal tunnel syndrome. The difference is the pain pattern — PF is worst with first steps in the morning, TTS burns continuously along the sole and sometimes up the medial ankle.
Functional Notes And Common Mistakes
One counter-intuitive thing about the lower leg muscles: the peroneals and tibialis anterior work together during normal gait, not against each other. They co-contract to stabilize the ankle during midstance. Treating one as "tight" and the other as "weak" without looking at the gait cycle leads to bad stretching protocols. The Peroneals aren't always the problem. Sometimes they're just overworked because tibialis posterior is failing. Another practical issue: the soleus recovers faster than gastrocnemius after exercise damage. If someone complains of posterior lower leg stiffness after a run, it's usually soleus. Stretching and foam rolling there helps. Gastrocnemius tightness responds better to knee-extension-based stretching. Same muscle group, different approach depending on which one is actually restricted. Compartment syndrome is the edge case that kills if missed. Acute compartment syndrome of the lower leg presents with pain out of proportion to injury, pain on passive stretch of the toes, paresthesia, and tight swollen compartments. It's a surgical emergency. Don't massage it. Don't wait. Measure compartment pressures if you're in a position to do that. Time to fasciotomy under six hours is the window where outcome changes dramatically.