Reading The Lower Limb Correctly
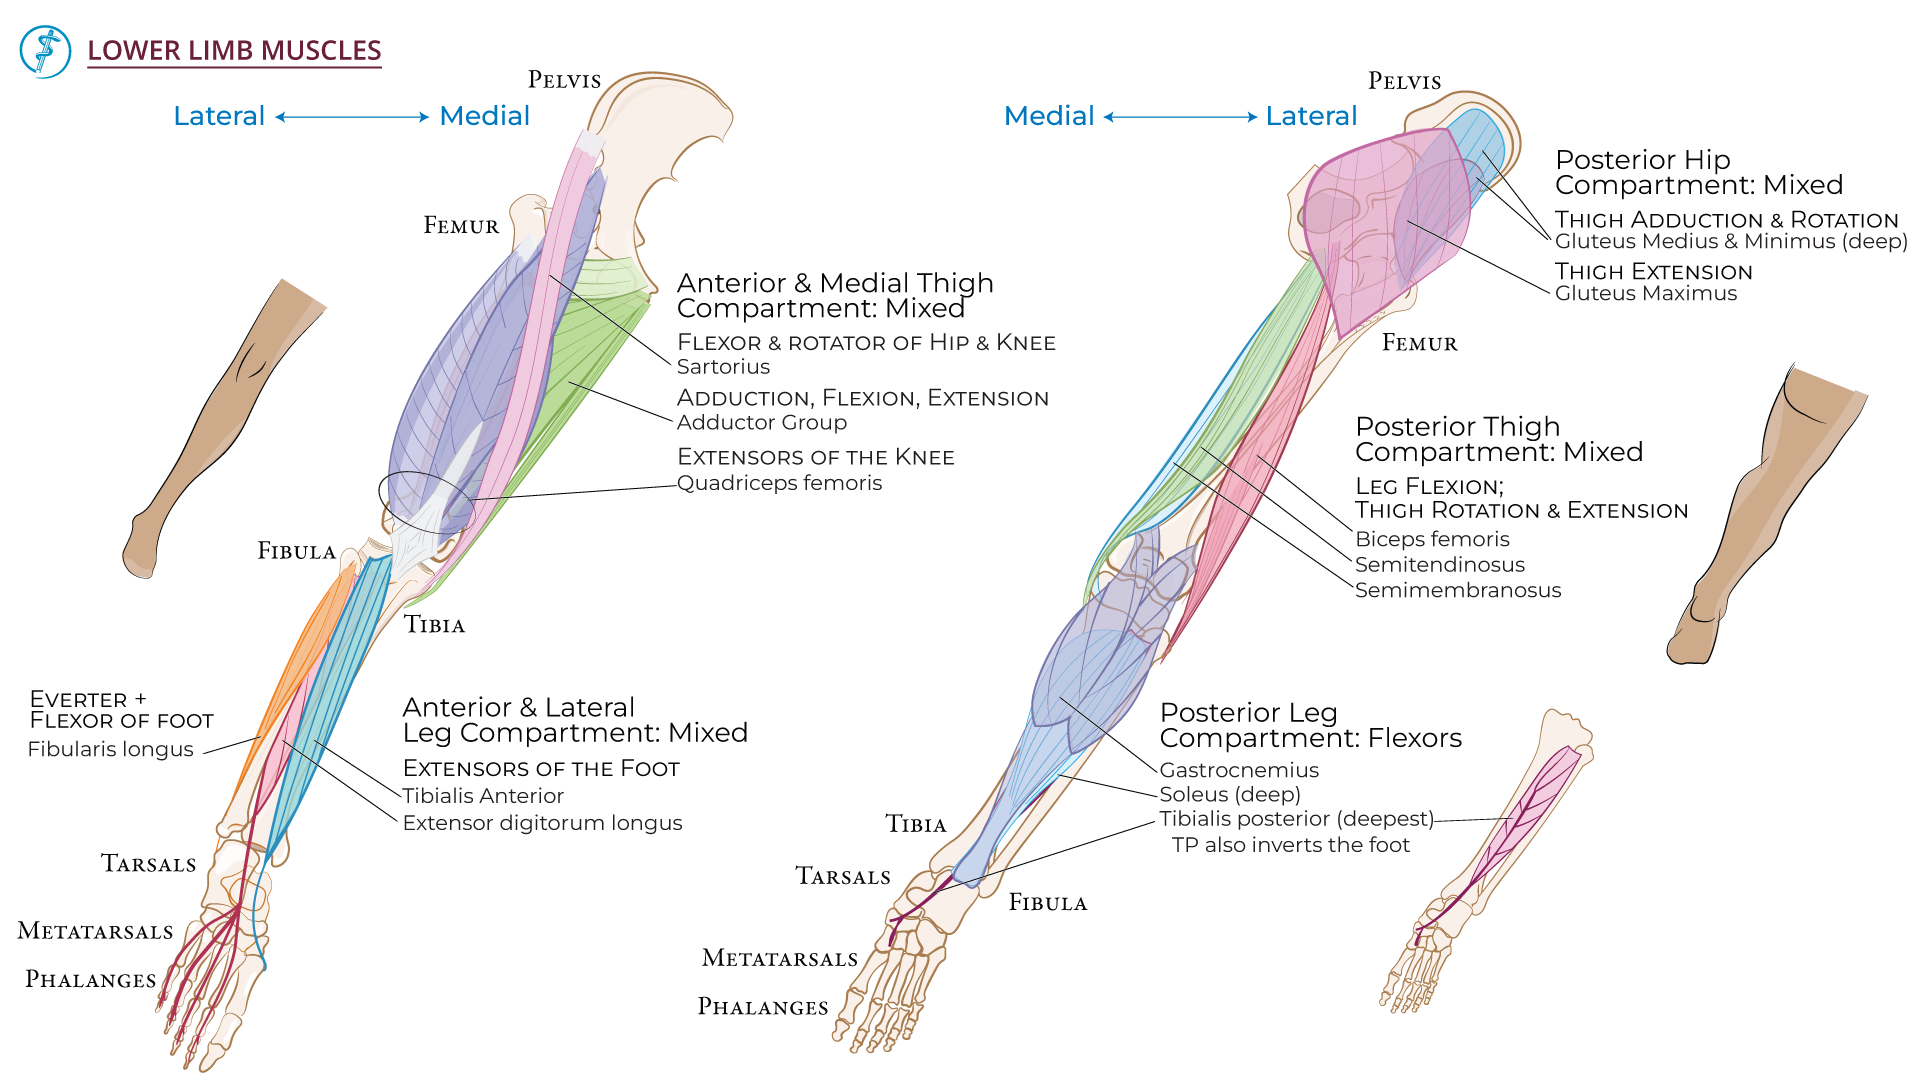
The gluteus maximus isn't just a big muscle you push around on a cadaver. It's a three-dimensional structure with fiber directions that change how it stabilizes the hip during single-leg stance. If you're memorizing attachments without thinking about the line of pull, you'll struggle when a patient presents with an antalgic gait. I've seen residents lose points on practical exams for listing attachments in the wrong order. The anterior fibers of the gluteus medius abduct and internally rotate. The posterior fibers abduct and externally rotate. That distinction matters clinically. It's not decorative detail. The anterior compartment of the thigh is dominated by the quadriceps femoris, which has four heads: rectus femoris, vastus lateralis, vastus medialis, and vastus intermedius. They all converge into the quadriceps tendon and insert on the patella, then continue as the patellar ligament to the tibial tuberosity. The rectus femoris is the only biarticular muscle in that group, crossing both the hip and the knee. That makes it relevant for both hip flexion and knee extension, but it also makes it the most commonly strained muscle in athletes during sprinting and kicking movements. Beneath the rectus femoris lies the vastus intermedius, and honestly it's the most overlooked head. It's deep to the other three and almost never discussed in basic textbooks. Yet on ultrasound-guided injections for quadriceps tendinopathy, intermedius hypertrophy shows up frequently as a compressive factor. I learned about this the hard way after a sports med rotation where a runner came in with anterior knee pain and every treatment plan failed until we realized the vastus intermedius was the actual irritant.
The adductor compartment sits medial to the femur. Adductor longus, adductor brevis, adductor magnus, gracilis, and pectineus. The adductor magnus deserves special attention because it has dual innervation. The adductor part is innervated by the obturator nerve, but the hamstring part is innervated by the tibial division of the sciatic nerve. That's a detail that comes up repeatedly in dissection labs and clinical reasoning questions. If you miss it, you might mislocalize a lesion that presents with isolated weakness in the hamstring portion of the magnus.
The Posterior Thigh And Knee Mechanics
The hamstrings include biceps femoris long head, semitendinosus, semimembranosus, and the short head of biceps femoris, which is unique because it's the only hamstring fiber not innervated by the sciatic nerve in its typical form. It's actually supplied by the common fibular division of the sciatic nerve directly from its origin. That means a high fibular head fracture can selectively knock out the short head while sparing the rest of the hamstrings. I ran into this exact scenario in a neurology clerkship. A patient with a fibular head fracture had preserved hamstring strength on manual testing, which initially confused everyone until someone remembered the short head anatomy. Understanding the hamstrings as knee flexors and hip extensors is standard curriculum. What people rarely grasp is the role each head plays in rotational control of the tibia. The semitendinosus and semimembranosus internally rotate the tibia when the knee is flexed. The biceps femoris externally rotates. This matters for ACL reconstruction graft choice and post-operative rehab progression. Picking the wrong graft without accounting for these rotational dynamics can lead to persistent rotational instability even when the knee feels stable in sagittal plane testing.
Get the Full Details

Innervation Patterns That Actually Matter
Femoral nerve supplies the anterior compartment. Obturator nerve supplies the medial compartment. Sciatic nerve supplies the posterior compartment. This rule holds for the vast majority of people. But the sciatic nerve itself branches into the tibial and common fibular divisions, and those divisions have their own territory mappings that get tested constantly. The tibial nerve continues down into the foot, innervating the plantar intrinsic muscles. The common fibular nerve wraps around the fibular neck, which is why it's the most commonly injured nerve in the lower limb. Peroneal neuropraxia from a crossed-leg position is one of the most common nerve injuries I've documented. Here's a nuance that isn't emphasized enough: the superior and inferior gluteal nerves don't just innervate gluteus medius, minimus, and tensor fasciae latae. They also carry proprioceptive fibers from the hip joint capsule. When gluteal nerve injury occurs, patients don't just lose abduction. They lose joint position sense, which translates to a positive Trendelenburg sign and a waddling gait pattern. I worked with a physical therapist who used this insight to design balance retraining protocols that specifically targeted proprioceptive deficit after hip arthroplasty. Standard strengthening alone didn't fix the gait abnormality. Proprioceptive work did.
The Leg Muscles: Anterior, Lateral, And Posterior Compartments
The anterior compartment of the leg contains the tibialis anterior, extensor digitorum longus, extensor hallucis longus, and fibularis tertius. These are all innervated by the deep fibular nerve. Tibialis anterior is the primary dorsiflexor, and its tendinitis is extremely common in runners. But here's what's interesting: tibialis anterior doesn't just dorsiflex the ankle. It also inverts the foot. So weakness here causes both foot drop and reduced inversion strength during midstance. The lateral compartment houses the fibularis longus and fibularis brevis, innervated by the superficial fibular nerve. These evert the foot and assist in plantarflexion. Many students underestimate their contribution to lateral ankle stability. The fibularis muscles are the dynamic stabilizers against inversion injuries, which account for the vast majority of ankle sprains. When you rehab an ankle sprain without addressing fibularis strength, you're leaving the main dynamic stabilizer weak. The posterior compartment splits into superficial and deep layers. The superficial layer includes gastrocnemius, soleus, and plantaris. The deep layer includes popliteus, tibialis posterior, flexor digitorum longus, and flexor hallucis longus. The Achilles tendon carries the force of both gastrocnemius and soleus, which together generate approximately 80 percent of the plantarflexion torque needed for normal walking. Running increases that demand dramatically. I remember evaluating a marathon runner with recurrent Achilles tendinopathy. The issue wasn't just the tendon. It was a significant soleus weakness relative to the gastrocnemius, creating an uneven load distribution across the tendon during the push-off phase. Targeted soleus strengthening resolved the issue over twelve weeks.
The Foot And Intrinsic Musculature
The foot contains twenty-six bones and over one hundred muscles, ligaments, and tendons working together. The intrinsic muscles are organized into four layers on the plantar surface. Layer one contains abductor hallucis, flexor digitorum brevis, and abductor digiti minimi. Layer two includes the lumbricals and quadratus plantae. Layer three has flexor hallucis brevis, adductor hallucis, and flexor digiti minimi brevis. Layer four contains the plantar and dorsal interossei plus the tendons of peroneus longus and tibialis posterior. The lumbricals are particularly noteworthy. They originate from the flexor digitorum longus tendons and insert on the extensor expansions of the lateral four toes. Their action is to flex the metatarsophalangeal joints and extend the interphalangeal joints. This coordinated action prevents toe clawing during gait. When lumbrical function is compromised, which happens in conditions like Charcot-Marie-Tooth disease or following Morton's neuroma surgery, patients develop claw toes and metatarsalgia. Treatment usually involves intrinsic strengthening exercises and sometimes surgical intervention depending on severity.

Practical Approaches To Learning This Material
Passive reading through textbooks gets you so far. The most effective approach I found combines anatomical atlas study with palpation practice on live subjects. Find your own quadriceps tendon first. It's thick and rope-like just above the patella. Trace it upward to where it merges with the sartorius and gracilis to form the sartorial bearing, which is part of the aponeurosis covering the rectus femoris origin. Now try to isolate rectus femoris contraction versus the vastus heads. Contract the quad with the knee extended and hip flexed. The bulge you feel distal to the anterior superior iliac spine is the rectus femoris. The bulk around the knee is the vasti. For the hip flexors, lie supine and actively lift your leg about thirty degrees off the table. Feel the deep cord-like structure lateral to the pubic tubercle. That's the iliopsoas tendon. It's not always easy to palpate, especially in people with more subcutaneous tissue. But once you locate it, you have a reliable landmark for the femoral triangle contents: the femoral artery is lateral to the tendon, the femoral vein is lateral to the artery, and the femoral nerve is lateral to the vein. Remember the mnemonic NAVEL from lateral to medial: Nerve, Artery, Vein, Empty space, Lymphatics. This arrangement stays consistent, though the exact measurements vary between individuals. For the posterior thigh, sit on the edge of a table with one leg hanging freely. Flex the knee against resistance while palpating the medial and lateral borders of the popliteal fossa. The medial border is formed by semitendinosus and semimembranosus. The lateral border is biceps femoris. The floor of the fossa contains the popliteal artery and vein, with the tibial nerve lying deepest. During knee flexion, you should feel these structures tension appropriately. If there's asymmetry or painful limitation on one side, that's worth investigating further.
Common Pitfalls And Where The Standard Models Break Down
One persistent problem I encountered involved understanding the piriformis muscle and its relationship to the sciatic nerve. Standard anatomy teaches that the sciatic nerve passes inferior to the piriformis. But approximately fifteen to twenty percent of the population has an anomalous relationship where the common fibular division pierces through the piriformis. This is clinically significant because piriformis syndrome presents differently depending on the variant. In the common variant, irritation of the sciatic nerve produces posterior hip pain radiating down the posterior thigh. In the piercing variant, symptoms may present more laterally because the fibular division is preferentially compressed. I had a patient who was misdiagnosed for months with typical sciatica before a colleague noticed the lateral radiation pattern and ordered an MRI that revealed the anatomical variant. Targeted piriformis release resolved the symptoms. Another area where textbook models fall short is the concept of the hip extensors. Most people think gluteus maximus and hamstrings are the primary hip extensors. They are, but the adductor magnus contributes significantly, especially during the late swing and early stance phases of gait. The hamstring portion of the adductor magnus acts as a hip extensor and is innervated by the tibial nerve, not the obturator nerve. This distinction matters when assessing proximal hamstring avulsions because patients with partial adductor magnus involvement may retain some hip extension strength despite significant hamstring dysfunction. I learned this during a case where a cyclist presented with posterior hip pain and partial strength loss, and the initial diagnosis of hamstring strain was incomplete without recognizing the adductor magnus contribution.
Putting It All Together Clinically
When you move from pure anatomy into clinical application, the relationships become clearer. A patient with foot drop likely has deep fibular nerve involvement, which could be from L5 radiculopathy, peroneal nerve compression at the fibular neck, or anterior compartment syndrome. Distinguishing between these requires knowledge of the entire pathway. The deep fibular nerve originates from the common fibular nerve, which branches from the sciatic nerve, which arises from the L4-S2 nerve roots. A lesion at any point along this chain produces similar weakness patterns, but associated symptoms help localize the level. Ankle dorsiflexion and toe extension are weak in deep fibular nerve palsy. Hip flexion and knee extension strength remain normal if the femoral nerve is intact. Sensory loss over the first web space localizes to the deep fibular nerve. Loss of sensation along the lateral leg and dorsum of the foot suggests common fibular involvement. Absence of sensory changes with motor weakness points toward an L5 root problem. The lower limb musculature functions as an integrated system, not a collection of independent parts. Understanding how the gluteus medius works with the tensor fasciae latae to stabilize the pelvis during single-leg stance explains why weak hip abductors cause contralateral pelvic drop. Understanding how the tibialis posterior supports the medial longitudinal arch explains why its dysfunction leads to acquired flatfoot. Understanding how the gastrocnemius-soleus complex controls anterior tibial translation during gait explains why Achilles tendon integrity is essential for normal locomotion. I've spent years watching people struggle with this material, and the pattern is always the same. They memorize attachments and insertions without building a functional mental model. The result is fragile knowledge that collapses under any clinical application. The alternative is to learn each muscle group as a system, understand the nerve supply as a mapping tool rather than a trivia fact, and practice palpation until the anatomy becomes something you can feel rather than just recite. That shift from theoretical to tactile understanding is what separates people who can pass an exam from people who can actually use this knowledge in practice.

If you want a structured reference, the comprehensive Muscle Atlas of the Lower Limb provides detailed anatomical illustrations and clinical correlation notes. It covers the same material here but with higher resolution imaging and additional variation notes that go beyond standard textbook coverage. The download link is available through the standard academic resource portals.


