
Why This Field Exists and What It Actually Looks Like
Muscular Dystrophy Occupational Therapy is the practice of helping people with progressive muscle weakening maintain as much independence as possible through adaptive techniques, equipment modifications, and energy conservation strategies. It is not curative. It is not dramatic. It is mostly tedious, repetitive problem-solving conducted one client at a time. I spent years doing this work across multiple clinics before moving into consulting. The biggest thing no one tells you about it is that most sessions are not about exercises. They are about figuring out how someone manages to brush their teeth with shoulders that no longer hold their arms up, or how they get dressed when hip flexion drops below 45 degrees and they cannot tolerate a transfer chair because of skin integrity concerns. The second thing nobody mentions is that progression rates vary wildly even within the same genetic diagnosis. I had two clients with dystrophinopathy who were a year apart in age and diagnosis but needed completely different intervention timelines. One was losing ambulation and needed a wheelchair assessment immediately. The other held onto walking for another three years and needed upper extremity splinting and home modification work instead.
Muscular Dystrophy Occupational Therapy: The Day-to-Day
A typical evaluation takes between 90 and 120 minutes for a new client. You start with a detailed history — not just the medical records, but what their actual day looks like right now. Can they feed themselves? How long does it take? Do they have assistance with bathing or are they managing with a bath bench and grab bars? What is their current room setup? Are there stairs? How do they access a car if they still drive? Then you move to functional assessment. This is where people often go wrong. They test joint ranges and muscle grades and stop there. That is insufficient. You need to observe the actual tasks. Have them reach for a cup on a high shelf. Have them button a shirt. Have them transfer from bed to chair. What you see in observation tells you more than any manual muscle test ever will, especially in MD where fatigability and inconsistent strength make isolated testing unreliable. The standard tool I use alongside everything else is the COPM — Canadian Occupational Performance Measure. It is a semi-structured interview that identifies what the client actually considers problematic, ranked by their own importance. Generic goal-setting fails here because the therapist's priorities and the patient's priorities rarely align. A client may not care about maintaining elbow extension if they cannot manage their lunch independently. Prioritize accordingly.
Equipment and Modifications That Actually Matter
Adaptive equipment selection is where most guidelines fall apart. Textbooks list everything and pretend it all applies equally. In practice, you are choosing between maybe three items that fit this specific person's progression stage, budget, and living situation. For upper extremity support, custom resting hand splints are frequently indicated in DMD and similar conditions. The argument against them is that they encourage disuse. The argument for them is that contracture prevention and pain reduction allow the person to continue using their hands for longer. I lean toward the splint side when the client already has resting flexion exceeding 30 degrees at the MCP joints. Beyond that point, soft tissue shortening becomes the dominant issue and splinting alone cannot reverse it, but early intervention helps. Adaptive dressings are an underrated category. Long-handled shoehorns, button hooks, elastic laces, and zipper pulls are standard. But the more important item is clothing modification. I have clients whose occupational therapists sew magnetic closures into their shirts and modify pants with elastic waistbands and side openings. This takes 20 minutes per garment and dramatically reduces dressing time. Standard catalogs sell the tools. Few people suggest the modifications.
Get the Full Details
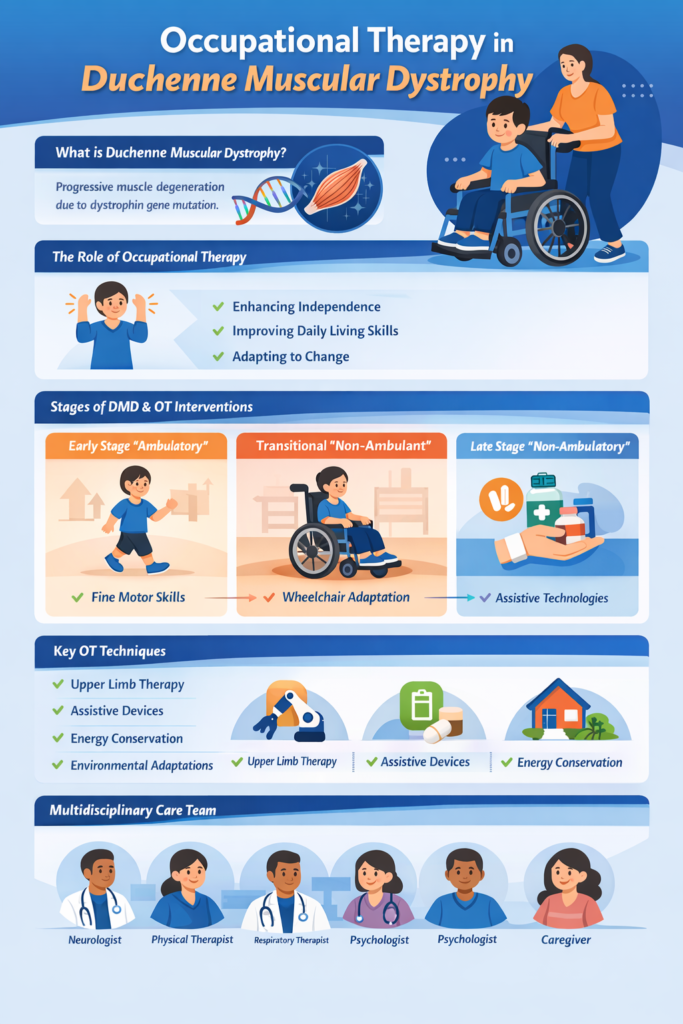
Environment control systems have become essential for advanced stages. Voice-activated home automation used to cost several thousand dollars. Now basic setups with smart plugs and voice assistants run under $200 and cover lighting, fans, television, and door locks. The transition from independent home management to full caregiver dependency happens faster than most families prepare for, and environmental controls buy real autonomy during that window. Bathroom setup deserves specific attention. A transfer bench beats a shower chair for most MD clients because it allows lateral transfer from wheelchair without a standing pivot. Grab bars mounted into wall studs are non-negotiable — drywall anchors fail under dynamic loading every time someone tests them. I had a client last year who installed a grab bar on a hollow core bathroom door. The door gave way during a morning transfer. Minor injury, but entirely preventable.
Energy Conservation and Activity Pacing
This is where the work gets less tangible and more frustrating. There is no objective measure for fatigue management the way there is for range of motion. You teach pacing strategies — scheduling demanding tasks for higher energy periods, breaking activities into smaller segments, alternating between high and low demand tasks. It sounds simple. It is difficult to implement consistently. The common pitfall is assuming energy conservation means doing less. It does not. It means distributing effort so the person can do the things that matter to them throughout the day rather than exhausting themselves in the morning and being done by 2 PM. I track this through activity logs for two weeks before prescribing a regimen. The log reveals patterns that the client may not consciously notice, like how social interactions drain them faster than solitary tasks or how certain room temperatures make everything feel harder. For clients who are still ambulatory, the question of when to transition to a wheelchair is the most emotionally charged decision in this work. The clinical indicators are clear — six-minute walk distance declining below 150 meters, forced vital capacity dropping below 50 percent predicted, increased energy expenditure during basic mobility. But the decision is personal. I have seen clients resist wheelchairs until they were falling frequently or experiencing secondary complications from compromised gait mechanics. I have also seen clients adopt them early and gain function they did not expect because the energy previously spent on walking became available for other activities.
Communication changes are another area where occupational therapy overlaps heavily with speech-language pathology. As respiratory muscles weaken and fine motor control declines, alternative and augmentative communication becomes relevant. Eye-gaze technology used to be prohibitively expensive and required extensive calibration sessions. Modern systems are more accessible but still require professional setup and ongoing adjustment as the client's abilities change. The timing of introduction matters — presenting it too early creates anxiety, presenting it too late means the client loses communication options while frustrated.

What Most People Get Wrong
The first mistake is treating this as a static intervention. Muscular dystrophy progresses. An equipment plan written in January may be completely inadequate by June. Follow-up cadence should be every three to six months during active progression phases, not annual check-ins. I once saw a client whose home modifications were assessed in 2021 and never revisited. By 2023 they could not use the kitchen counters they had been fitted for because their seated height and reach had changed significantly with scoliosis progression and shoulder weakness. The second mistake is underestimating the family and caregiver burden. Occupational therapy in this context is not just about the client. It is about teaching caregivers safe transfer techniques, efficient assistance methods, and pressure relief scheduling. A caregiver who learns proper body mechanics reduces their own injury risk and provides better assistance. The training usually takes two to three sessions and directly impacts how long the client can remain at home versus requiring residential care. The third mistake is ignoring psychosocial factors. This is not a counseling role, but untreated depression and anxiety significantly reduce engagement with therapy and adaptive strategies. Screening with a brief tool like the PHQ-2 during initial evaluation takes ninety seconds and flags people who need referral. I stopped skipping this step after a client disengaged completely from their wheelchair training and I could not figure out why until a casual conversation revealed they were depressed about the visibility of the chair and had given up entirely.
Practical Workflow for Clinicians Starting Out
If you are new to this population, start with the basics and build from there. Establish a relationship with the coordinating neurologist or neuromuscular clinic. Case coordination is where most referrals come from and where you get the most accurate clinical picture. The neurologist knows the progression trajectory. You know the functional and adaptive piece. Together you can anticipate needs before they become crises. Build a equipment inventory you actually understand. Do not recommend a product you have never handled. Rent or borrow items before purchasing for clients. Some manufacturers offer demo programs. Local DMD centers sometimes have equipment lending libraries. The cost of returning a $800 adaptive utensil set because the client could not grip it is far less than the cost of a client losing trust in your recommendations. Documentation should focus on functional outcomes, not just interventions performed. Insurers and funding bodies increasingly require this. Instead of writing "provided splinting education," document that the client demonstrated independent donning and doffing of resting hand splints and reported improved ability to complete morning hygiene routine within 20 minutes without assistance.
When Occupational Therapy Cannot Help
Saying this outright is uncomfortable but necessary. There are stages of disease progression where occupational therapy has limited impact on overall quality of life. When a client requires total assistance for all activities of daily living and has minimal voluntary movement, the focus shifts from independence maintenance to comfort positioning, skin protection, and caregiver support. This is not failure. It is an accurate assessment of what the intervention can and cannot do at that point. Recognizing it early prevents unnecessary appointments and redirects energy toward what actually helps. Respiratory involvement is another boundary. Occupational therapists do not manage ventilator weaning or tracheostomy care. But we do collaborate closely with respiratory therapists on positioning strategies that support lung function, energy conservation techniques that reduce respiratory demand, and equipment modifications that accommodate breathing apparatus. Knowing when to refer and when to co-manage is part of the skill set. The field changes slowly. New research on disease-modifying treatments like exon-skipping therapies is altering the population we serve. Clients who would have progressed rapidly a decade ago are now maintaining function longer, which changes equipment timelines and intervention priorities. Stay current with neurology literature, not just OT journals. The treatment landscape is shifting faster than most clinical guidelines reflect.



