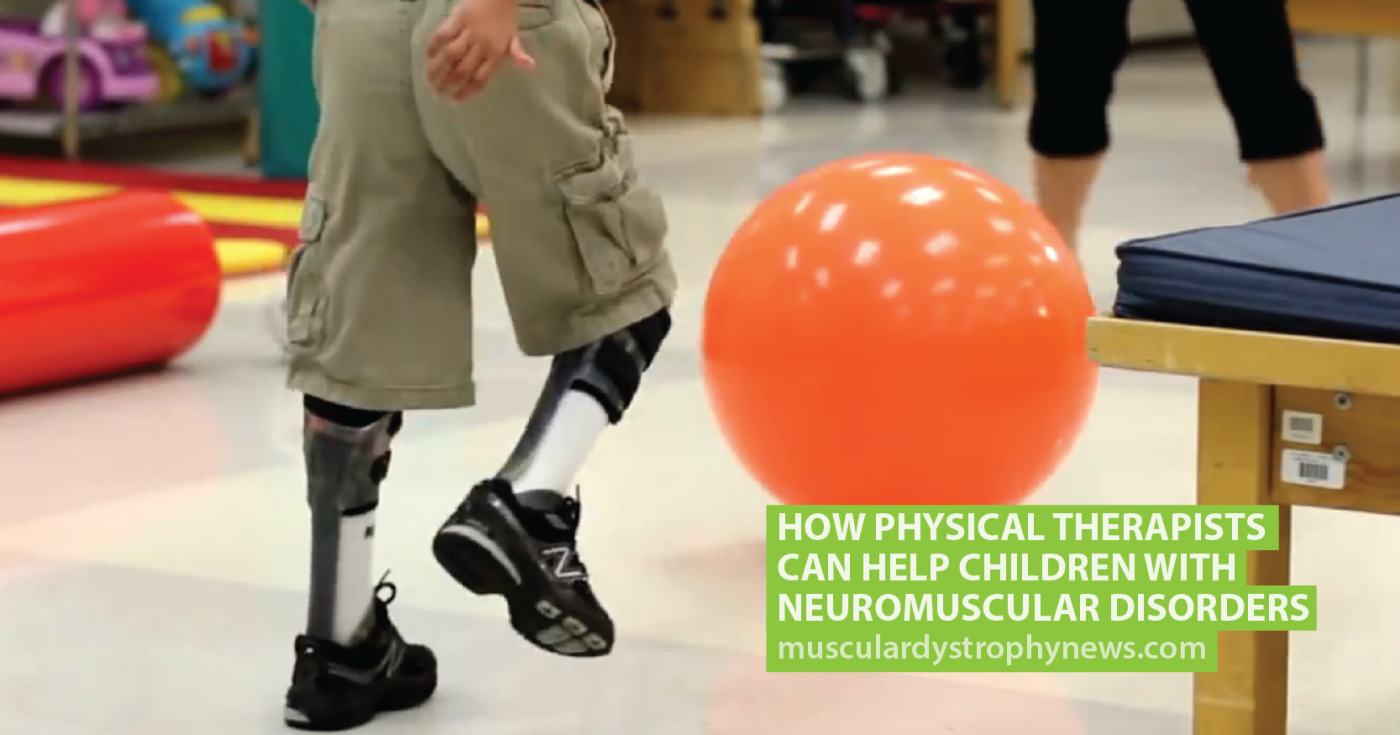
What Actually Happens During a Muscular Dystrophy PT Session
A lot of people walk into their first session thinking it is just stretching and light exercise. It is not. The work is more precise than that, and the margin for error is smaller than most clinics account for. You are dealing with a group of progressive diseases that affect skeletal muscle differently depending on the type. Dystrophinopathies like Duchenne and Becker behave very differently from myotonic dystrophy, facioscapulohumeral dystrophy, or limb-girdle subtypes. A program designed for one will actively harm another if applied blindly. The goal is maintenance of function for as long as possible, not reversal. That distinction matters because a lot of well-meaning therapists push too hard in the name of strengthening, and then wonder why the patient is worse six months later. Muscle damage from eccentric loading is the primary mechanism behind regression in mdx mouse models, and the same principle carries over to humans even if the data in people is less clean.
Where Muscular Dystrophy Physical Therapy Fits In
It sits somewhere between routine outpatient orthopedics and neurology clinic work. The equipment is similar, but the reasoning is entirely different. Standard strengthening protocols assume a working repair response. In MD, that response is blunted. So the approach shifts toward submaximal resistance, sustained gentle range of motion, and aerobics that do not push into the damage zone. I worked with a boy with Becker muscular dystrophy who had a good baseline. His grandmother insisted he keep up with his older cousins in the neighborhood football games. He was fine until one particularly rough Saturday. Next morning he could not climb stairs, his creatine kinase spiked to around 12,000, and he was deconditioned for three weeks. What happened is straightforward: unaccustomed eccentric effort in an already weakened muscle causes disproportionate damage in MD. The workaround is not restriction. It is pacing with a known ceiling. We ended up using a rate of perceived exertion scale capped at 5 out of 10, timed bouts of cycling at 60 to 70 percent of maximum heart rate, and a strict no-eccentric-load rule for anything outside the clinic. He stabilized after that and eventually got back to supervised swimming, which turned out to be the right compromise.
The Core Components You Will See
A solid program typically covers several areas, and the order in which they are addressed depends entirely on where the patient sits in the disease trajectory. Range of motion work. This is the bread and butter. Contractures develop in a predictable sequence. Ankles plantarflex first, then knees flex, hips flex, and elbows flex. The later stages bring shoulder external rotation loss and spinal curvature. Stretching here is low load, long duration. Holding a stretch for two to three minutes per position beats the old quick bounce method by a wide margin. I use a seated ankle pump with a towel wrap and a timer rather than having the patient push against a wall, which tends to recruit compensatory hip hiking and does not actually move the joint through its available arc. Aerobic conditioning. Channeling is acceptable and often beneficial. Stationary cycling at low resistance, hand-arm ergometry for upper-limb–predominant cases, and aquatic therapy all fit. The key threshold is keeping oxygen consumption below the lactate threshold. Push past that and you are causing microtrauma. Heart rate monitoring is useful but sometimes misleading in patients on beta-blockers or with autonomic involvement. Pairing it with perceived exertion and a conversation test usually keeps things honest.
Get the Full Details

Strengthening. This is the most controversial piece. The old dogma said no strengthening at all. The newer evidence, including the 2018 standard of care update and subsequent studies, supports light resistance training at intensities below 50 to 60 percent of one repetition maximum, two to three times per week, with concentric focus and no forced lengthening under load. The effect size is modest but real. Patients gain enough strength to delay functional decline by months, not years. That is still clinically meaningful when every month counts. Orthotics and positioning. Ankle-foot orthoses, knee braces, wheelchair seating systems, and night splints are not add-ons. They are part of the treatment. An AFO set in neutral dorsiflexion reduces energy cost of walking in ambulatory DMD patients by roughly 15 to 20 percent, according to the kinetics studies. Getting the fit right matters more than the brand. I had a patient who kept getting medial malleolar skin breakdown from a custom fiberglass AFO because the therapist never checked the shank alignment after the heel cord tightened. We switched to a thermoplastic design with a medial keel cutout and dropped the recurrence rate to zero over the next eight months.
How to Build a Program That Does Not Backfire
Start with a baseline that includesManual Muscle Testing where feasible, 6-minute walk distance, timed up-and-go, and vital capacity. Repeat every three to six months in ambulatory patients, every six to twelve months in nonambulatory. Trends matter more than any single number. Prescribe within the safe window. Submaximal aerobic work, gentle stretching, and light concentric-only resistance. Avoid eccentric-heavy exercises, plyometrics, high-impact jumping, and maximal lifts. The list of contraindicated movements is short but the consequences are not worth ignoring. Monitor creatine kinase after introducing any new activity. A rise of less than two to three times baseline is acceptable. Anything higher means you pushed past the damage threshold and need to scale back immediately.
Coordinate with pulmonology and cardiology early. Noninvasive ventilation timing, steroid side effects, and arrhythmia risk all change what is safe in the gym. A patient on prednisone has different bone density and tendon integrity than the same patient off it. Do not treat these as separate tracks.

What Most People Get Wrong
The biggest mistake is treating MD like post-stroke rehab or general orthopedic recovery. In those conditions, more is usually better up to a point. In MD, the point is much closer than you think, and the fall-off after that point is steep. Another common error is focusing only on what the patient can do now instead of mapping the trajectory. Contracture prevention in the ankles buys you walking time. Shoulder external rotation maintenance preserves feeding independence. Elbow flexion contractures make wheelchair transfers hard. Each decision should tie back to a functional outcome that matters to the patient, not just a range of motion number on a goniometer. A third pitfall is using standard progressive overload templates. Linear increases in weight or reps do not apply here. Progression is slower and often nonlinear. Some months you hold steady and that is a win. A few patients actually gain a little, but you plan for that rather than betting your program on it.
When This Approach Stops Working
Physical therapy cannot stop progression. It can slow certain downstream complications, but the underlying pathology runs on its own timeline. Once ambulation is lost, the focus shifts almost entirely to positioning, contracture management, and respiratory support coordination. Strengthening becomes irrelevant at that stage. Continuing to prescribe resistance training for a patient who no longer walks is not just useless, it is a waste of finite energy reserves they already lack. Steroid treatment changes everything about how you approach exercise. Dose, timing, and type of glucocorticoid all interact with tissue response. Deflazacort and prednisone are the most common. Both carry metabolic and skeletal side effects that alter risk profiles. A program written before the steroid conversation is almost always wrong once the medication starts. If you are looking for a starting point, the 2018 international standard of care recommendations for DMD and Becker are the best freely available guideline. They cover screening schedules, exercise guidance, orthotics, and referral triggers in one document. Most major neuromuscular clinics use them as their baseline protocol.