How the Muscular System and Organs Actually Connect
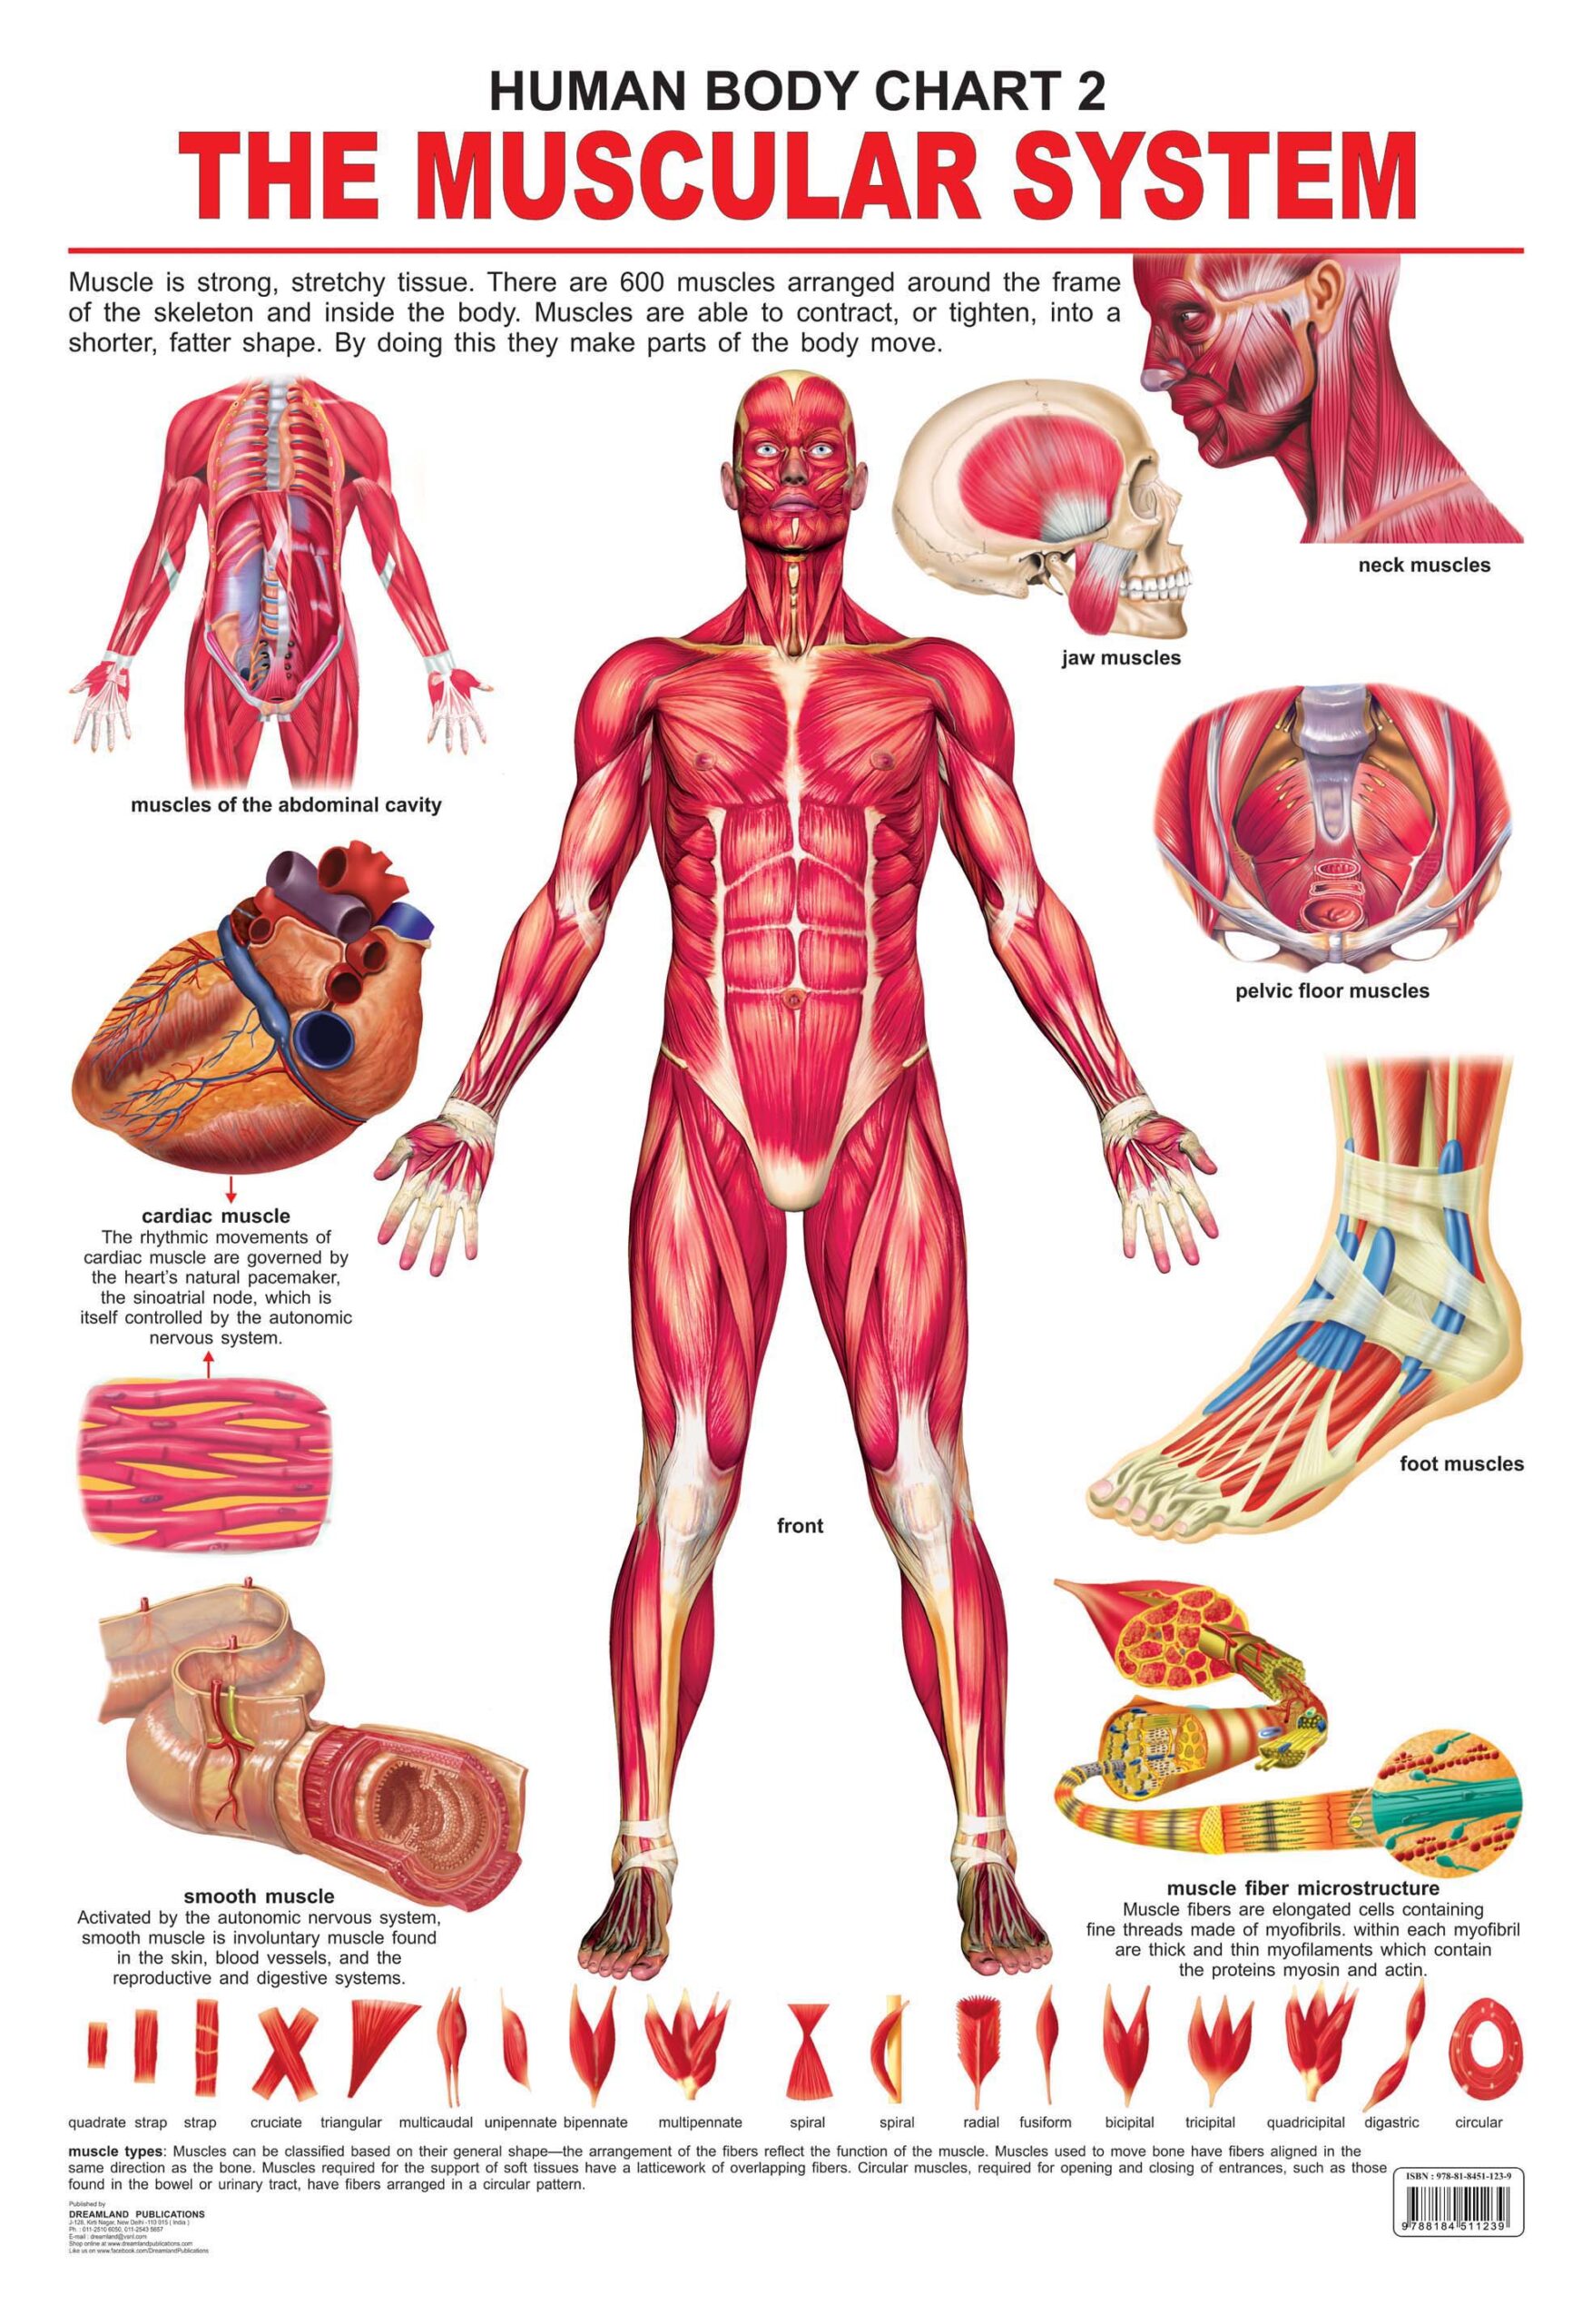
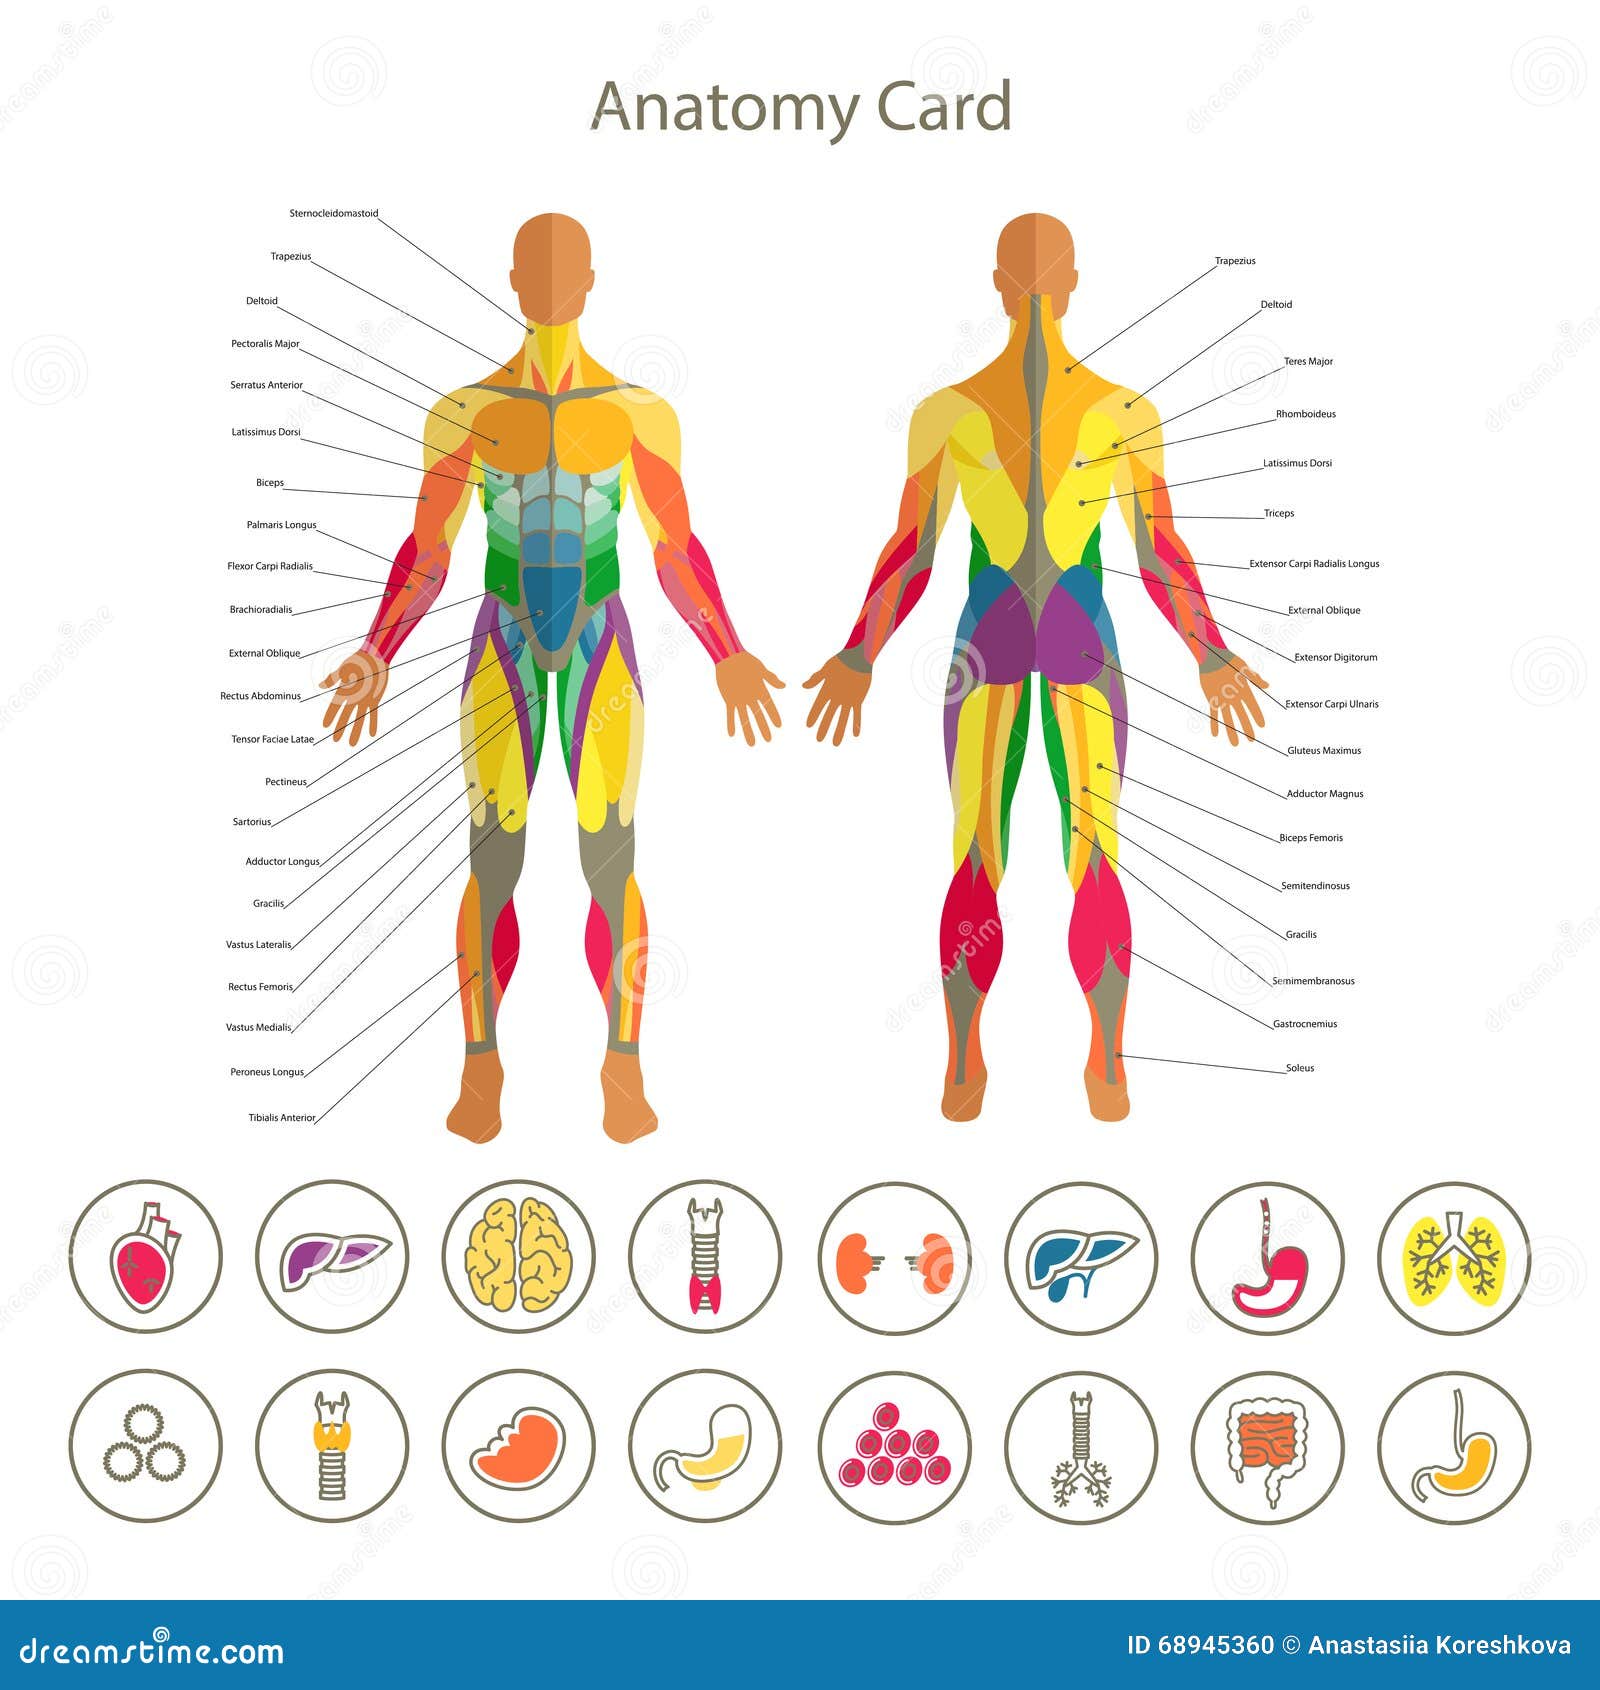
Most people think of muscles and organs as separate systems. They learn about skeletal muscle in one chapter and digestive or cardiovascular organs in another. That separation exists in textbooks because it's useful for teaching, but it doesn't reflect how the body actually functions. The Muscular System And Organs are linked through fascial continuities, shared nerve pathways, and mechanical forces that cross organizational boundaries constantly. Fascia is the connective tissue network that surrounds and penetrates every structure in the body. It doesn't stop at muscle bellies. The thoracolumbar fascia continues anteriorly as the transversalis fascia, which lines the inside of the abdominal wall. That same fascial plane wraps around the peritoneum, creating a continuous sheet from your lower back through your core and into your pelvic floor. When you understand this continuity, you start seeing why abdominal organ dysfunction and lower back pain show up together in clinical settings more often than coincidence would explain. Here's a concrete example from my own work. A client came in with chronic, diffuse upper abdominal tightness that resisted standard stretching and myofascial release on the abs. The tissue felt dense and unyielding, almost like scar tissue, but there was no history of surgery or trauma in that region. We traced the tension along the linea alba and rectus sheath superiorly through the diaphragmatic crura. The restriction wasn't in the abdominal wall itself. It was in the fascial attachments where the diaphragm meets the liver and stomach. Working on those deep diaphragmatic attachments with slow, sustained pressure changed the abdominal tone within a few sessions. The local tissue wasn't the problem. The anchored fascial load was.
This fascial web means that pulling on one point creates tension changes across multiple organ systems. The costal margin, where the ribs attach to cartilage, transfers force into the liver capsule and the diaphragm simultaneously. A golf swing or a heavy deadlift creates shear forces that travel through these planes. You can't isolate muscle work from organ position without ignoring real biomechanics.
The Diaphragm as the Primary Interface
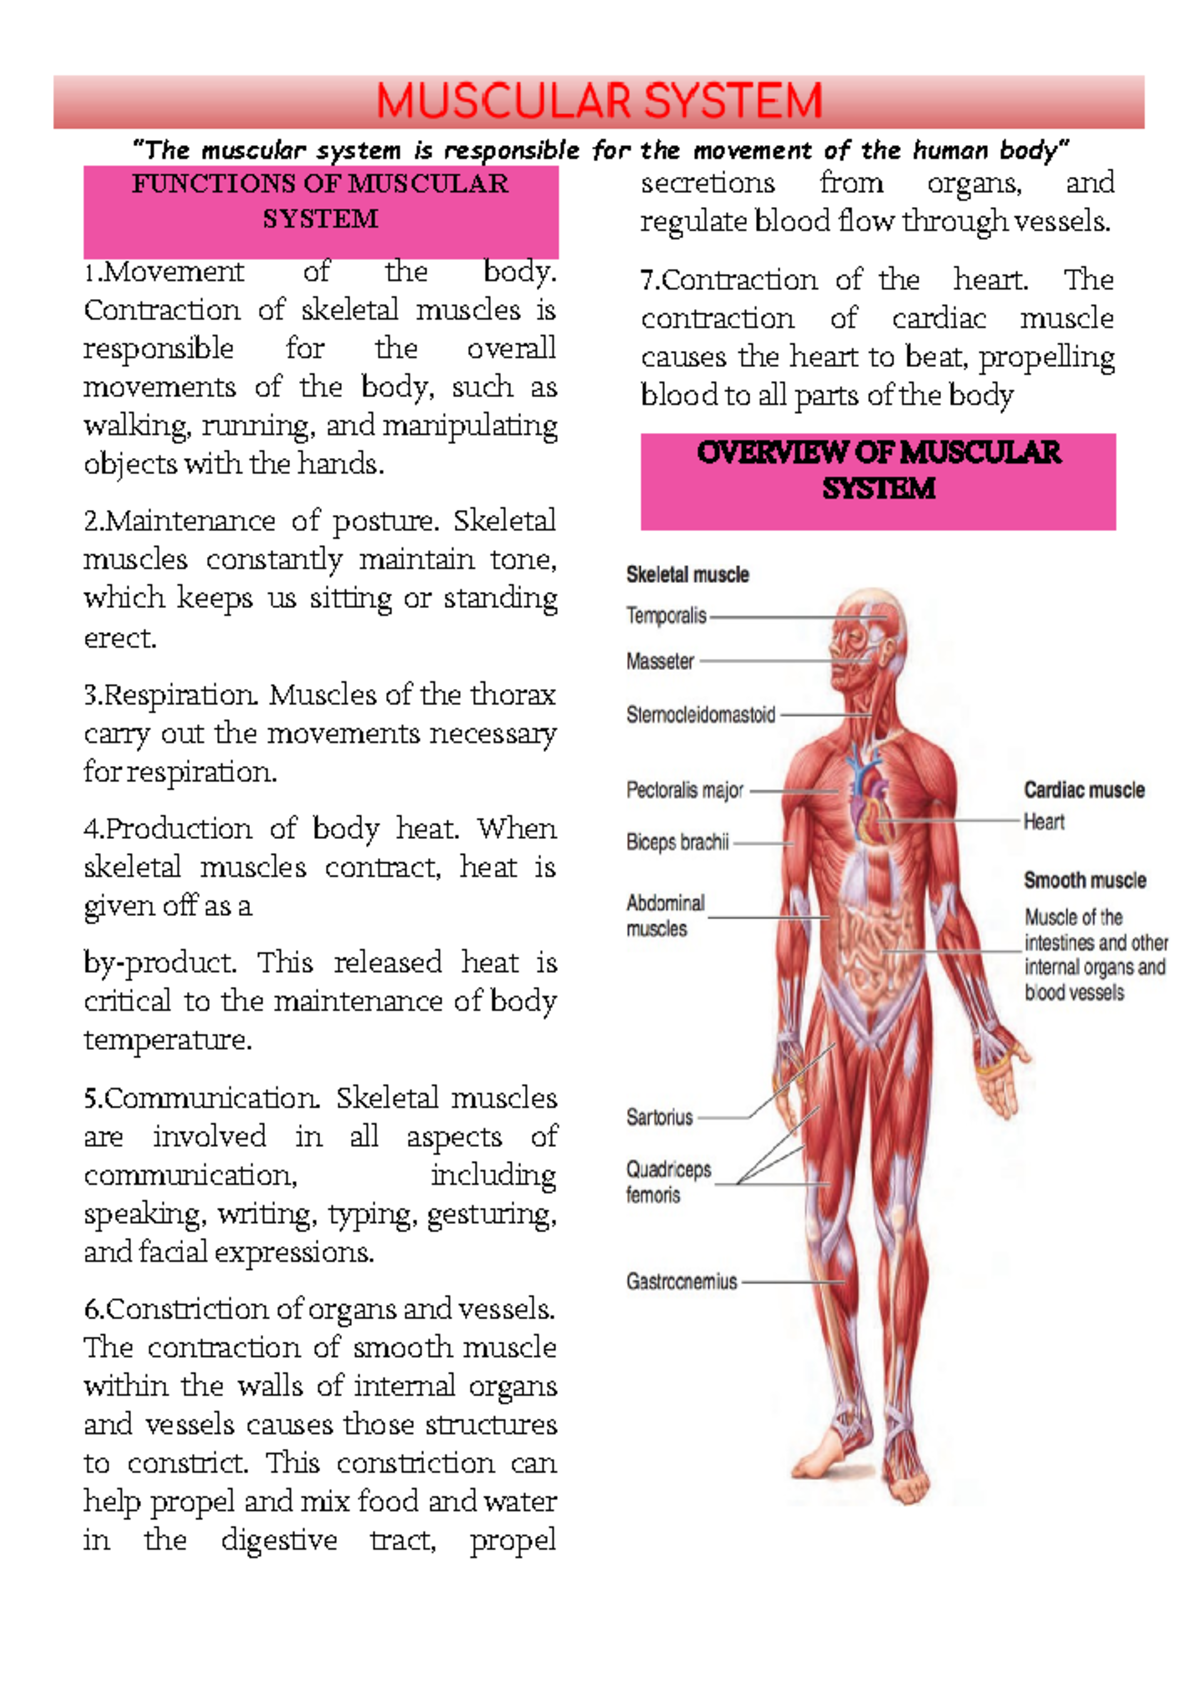
The diaphragm is the single most important structure at the intersection of the muscular and organ systems. It's a skeletal muscle under voluntary control that also drives every breath involuntarily. Its crura attach to the upper lumbar vertebrae, and its costal fibers blend with the transverse abdominis and internal oblique. The central tendon serves as an anchor point for ligaments connecting to the liver, pericardium, and stomach. When the diaphragm doesn't move freely — and most people's diaphragms have restricted glide due to stress, poor posture, or prolonged sitting — it creates downstream effects. The liver sits directly underneath the right dome. Restricted diaphragmatic excursion reduces the mechanical decompression that normally happens during inhalation, leading to subtle hepatic congestion over time. Same deal with the heart. The pericardium anchors to the central tendon. Poor diaphragmatic function correlates with reduced cardiac vagal tone, which shows up as lower heart rate variability and higher resting heart rate. These aren't theoretical connections. They're measurable physiological relationships. The practical implication for training and recovery is straightforward. Breathwork that improves diaphragmatic mobility — not the gimmicky box breathing routines, but actual 360-degree expansion drills that mobilize the posterior and lateral costal margins — tends to improve both respiratory efficiency and visceral comfort within weeks. I typically have clients spend about ten minutes daily on diaphragmatic self-myofascial release using a therapy ball against a wall, focusing on the posterior lower ribs first before moving anteriorly. Most people skip the posterior aspect entirely, which is where the biggest restrictions accumulate.
Get the Full Details

Smooth Muscle in Organ Walls
The smooth muscle in your organ walls operates on completely different principles than skeletal muscle. Skeletal muscle uses motor units recruited by the somatic nervous system. You can voluntarily contract your biceps. Smooth muscle in the gastrointestinal tract, blood vessels, and urinary tract operates through the autonomic nervous system, local chemical signals, and intrinsic pacemaker cells. The enteric nervous system alone contains roughly 500 million neurons — more than the spinal cord — and can coordinate peristalsis independently of brain input. The autonomic balance between sympathetic and parasympathetic input directly affects smooth muscle tone. Chronic sympathetic dominance — which is the default state for most office workers and people under sustained stress — causes vasoconstriction, reduced GI motility, and increased urinary tract sphincter tone. This isn't vague wellness language. Reduced splanchnic blood flow from sympathetic overactivity is a documented mechanism behind functional dyspepsia and irritable bowel symptoms. Parasympathetic activation through slow breathing, meditation, or even just lying down with legs elevated reverses these effects in most people within minutes. Training doesn't directly strengthen smooth muscle the way it strengthens skeletal muscle. But exercise modulates autonomic tone. Moderate aerobic activity increases vagal tone over time, which improves gut motility, blood flow regulation, and stress resilience. High-intensity training without adequate recovery does the opposite. The dose-response curve matters significantly here. Most people either don't exercise enough or train at intensities that chronically elevate cortisol and sympathetic drive, both of which degrade organ function indirectly.
The Pelvic Floor Connection
The pelvic floor is where this entire system converges at the bottom. The levator ani and coccygeus muscles form a hammock-like support for the bladder, reproductive organs, and rectum. These muscles receive dual innervation — the pudendal nerve for voluntary control and pelvic splanchnic nerves for autonomic regulation. This dual supply is why you can voluntarily contract your pelvic floor during a Kegel exercise but can't directly control the smooth muscle in your bladder wall. Pelvic floor dysfunction affects far more people than publicly discussed. Overactive pelvic floor muscles, often called hypertonic pelvic floor, present as urinary urgency, chronic pelvic pain, and sometimes lower back pain. The connection to the abdominal wall and diaphragm is direct: the pelvic floor and diaphragm act as opposing pistons in the intra-abdominal pressure system. When one is chronically tight, the other compensates. I've seen cases where treating the pelvic floor with internal work and nervous system downregulation resolved refractory upper abdominal tension that hadn't responded to any amount of core strengthening.
Common Pitfalls in Understanding This System
The biggest mistake beginners make is treating muscles and organs as hierarchically organized systems where one controls the other. The reality is more distributed and parallel. Neural control, mechanical loading, chemical signaling, and fascial tension all operate simultaneously across both systems without a single centralized controller. Your psoas major attaches to the lumbar vertebrae and passes deep to the abdominal organs on its way to the femur. It doesn't just flex the hip. It's mechanically coupled to the kidney and ureter through fascial planes, and it shares sympathetic innervation with splanchnic organs. Pulling on the psoas affects organ position and autonomic signaling. Another pitfall is assuming that strengthening abdominal muscles protects internal organs. A strong rectus abdominis doesn't shield your intestines from the effects of poor fascial glide, autonomic imbalance, or diaphragmatic restriction. Core stability comes from coordinated activation across multiple layers — transversus abdominis, internal obliques, pelvic floor, diaphragm, and multifidus — operating as a pressurized cylinder. Isolating any single muscle in that group misses the functional reality.
Limitations and Where This Model Breaks Down
The fascial continuity model I've described is widely accepted in manual therapy and rehabilitation circles, but it has real limitations. Fascial research is still evolving, and many claims about fascial "memories" or emotional storage in tissue aren't supported by rigorous evidence. The model works well for explaining mechanical transmission of force and some aspects of referred pain, but it shouldn't be stretched into a catch-all explanation for every symptom. Sometimes upper abdominal tightness is gallbladder pathology, not diaphragmatic restriction. Sometimes pelvic pain is endometriosis, not a hypertonic pelvic floor. The autonomic framework is better established but harder to measure directly. Heart rate variability is a reasonable proxy for vagal tone, but it's influenced by age, medications, caffeine, sleep quality, and many other factors. Using HRV to guide training load decisions is useful, but it's not precise enough to diagnose autonomic dysfunction on its own. Blood flow measurements to specific organs require Doppler ultrasound or similar imaging that most people don't have access to outside a clinical setting. For practical purposes, combining movement practice that addresses diaphragmatic mobility, pelvic floor awareness, and core cylinder coordination covers the majority of musculoskeletal-visceral complaints that show up in a non-clinical setting. If symptoms persist beyond four to six weeks of consistent practice, or if they include red flags like unexplained weight loss, blood in stool or urine, or severe localized pain, medical evaluation is necessary. The muscular-organ connection is real, but it's one system among many, and it doesn't replace diagnostic medicine.
The takeaway isn't that everything is connected to everything else through fascia. It's that specific, well-documented anatomical continuities exist between the musculoskeletal and visceral systems, and ignoring them leads to incomplete assessments and treatments. The diaphragm, pelvic floor, and abdominal fascial planes are the key junctions. Working with them directly — through breathwork, targeted mobility, and autonomic regulation — tends to produce more noticeable results than treating muscles and organs in isolation.